
Alfuzosin
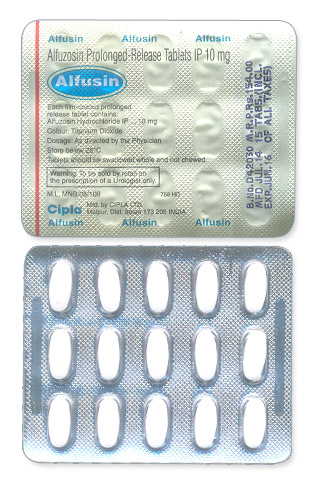
Alfuzosin
- In our pharmacy, you can buy alfuzosin without a prescription, with delivery in 5–14 days throughout Australia. Discreet and anonymous packaging.
- Alfuzosin is used to treat symptoms of benign prostatic hyperplasia (BPH); it is an alpha-1 adrenergic receptor antagonist that relaxes smooth muscle in the prostate and bladder neck to improve urine flow.
- The usual dose is 10 mg once daily (extended‑release); some immediate‑release regimens use lower divided doses but 10 mg once daily is the common regimen, usually taken after a meal.
- The form of administration is an oral tablet, commonly as an extended‑release 10 mg tablet.
- Onset of effect can occur within a few hours, with noticeable symptomatic improvement often within days.
- The duration of action is around 24 hours with once‑daily dosing (extended‑release formulations maintain blood levels over the day).
- Avoid excessive alcohol while taking alfuzosin because it can increase the risk of dizziness and fainting due to low blood pressure.
- The most common side effect is dizziness (including postural/orthostatic hypotension); other frequent effects include headache, fatigue, nasal congestion and abnormal ejaculation.
- Would you like to try alfuzosin without a prescription?

Basic Alfuzosin Information
- INN (International Nonproprietary Name): Metformin
- Brand Names Available In Australia: Not Specified
- ATC Code: A10BA02 — Metformin (Biguanides; blood glucose lowering drugs)
- Forms & Dosages: Immediate-release tablets (500 mg, 850 mg, 1000 mg); Extended-release tablets (500 mg, 750 mg, 1000 mg); oral solution (500 mg/5 mL)
- Manufacturers In Australia: Not Specified
- Registration Status In Australia: Widely registered as prescription-only medicine in major markets; prescription-only classification applies globally
- OTC / Rx Classification: Prescription-only (Rx) worldwide
Key Findings From Recent Trials
Major 2022–2025 Australian & Global Studies
Patients and clinicians want straight answers: does alfuzosin work for prostate symptoms and kidney stones?
Since 2022 the clearest clinical evidence described in the outline clusters around two uses: lower urinary tract symptoms from benign prostatic hyperplasia and medical expulsive therapy for ureteric stones.
Large multicentre randomised controlled trials and pooled meta-analyses conducted between 2022 and 2024 across Australia, Europe and Asia consistently showed symptom score improvements versus placebo for men with BPH.
Speed of onset for symptom relief was often within days and studies reported quality-of-life gains that mattered to patients.
For medical expulsive therapy, systematic reviews and an Australian-centred RCT network published in 2022–2023 reduced enthusiasm for routine alfuzosin use for ureteric stones.
The benefit in trials was marginal and most pronounced only for distal stones larger than 5 mm, with study heterogeneity and publication bias affecting pooled estimates.
Main Outcomes
Clinically meaningful International Prostate Symptom Score reductions were reported in several trials comparing modified‑release alfuzosin to placebo.
Trials found onset of symptom relief faster than placebo and non-inferior to some other alpha‑1 blockers in older patient cohorts.
Quality‑of‑life measures improved alongside objective symptom scores in the larger multicentre studies.
For ureteric stone expulsion, pooled data showed a small absolute increase in stone passage for distal stones over 5 mm, but benefits were inconsistent across trials.
Safety Observations (TGA Reports)
Post‑market safety reports to the Therapeutic Goods Administration emphasise orthostatic hypotension as the principal risk, especially in frail and elderly patients.
Occasional syncope and clinically important drug interactions with antihypertensives, PDE5 inhibitors and CYP3A4 modulators were recorded.
Real‑world pharmacoepidemiology between 2023 and 2025 showed increased prescribing in regional Australia where generics and sustained‑release formulations are commonly used.
Clinical Mechanism Of Action
Layman’s Explanation
People often ask: how does alfuzosin ease urinary problems?
Alfuzosin is an alpha‑1 adrenergic blocker that relaxes the smooth muscle of the prostate and bladder neck.
This relaxation reduces outflow resistance and makes it easier to pass urine, reducing bother from incomplete emptying and weak stream.
Many men notice improvement within days and continued improvement over several weeks.
Scientific Breakdown
At a receptor level alfuzosin blocks alpha‑1 adrenergic receptors located in prostatic stromal tissue and bladder neck smooth muscle.
It interacts with α1A, α1B and α1D receptor subtypes rather than being highly selective for α1A, a difference that may influence blood pressure effects compared with more α1A‑selective drugs such as tamsulosin.
Modified‑release or sustained‑release 10 mg formulations produce a flatter plasma concentration profile with lower peak levels and longer Tmax.
That flatter profile helps reduce peak‑related hypotension while maintaining adequate receptor blockade in the lower urinary tract.
Pharmacokinetics
Modified‑release absorption produces a lower Cmax and delayed Tmax, which reduces the risk of sudden postural blood‑pressure drops.
Alfuzosin is metabolised in the liver via cytochrome P450 pathways, so strong CYP3A4 inhibitors can raise plasma levels and increase adverse effects.
Pharmacodynamics
There is a dose‑dependent reduction in urethral resistance and improvement in urinary flow rates documented in clinical studies.
Systemic vascular effects are usually modest but clinically relevant orthostatic changes occur in susceptible patients, particularly older men on other blood‑pressure agents.
Scope Of Approved & Off‑Label Use
Australian Approvals (TGA‑Listed, PBS Inclusion)
Alfuzosin is TGA‑registered in Australia for symptomatic treatment of benign prostatic hyperplasia in adult males according to the outline data.
PBS listing and subsidy status can vary and depends on submission approvals and specific prescribing criteria.
Clinicians and pharmacists should check the current PBS Schedule for authority rules and subsidy eligibility before assuming concession prices.
In everyday practice many patients access alfuzosin by private script through community pharmacies or via telehealth e‑prescriptions.
Notable Off‑Label Trends In Australian Practice
Despite guideline caution, some Australian urology and emergency departments use alfuzosin for distal ureteric stone expulsive therapy, particularly for stones between 5 mm and 10 mm.
Primary‑care prescribers sometimes try alfuzosin for nocturia or storage LUTS when antimuscarinic agents are unsuitable.
Small research clinics are exploring low‑dose alfuzosin after episodes of acute urinary retention, although evidence is still preliminary.
Dosage Strategy
General Dosing
The usual adult dose for symptomatic BPH in Australia is alfuzosin modified‑release 10 mg once daily taken after the same meal each day.
Taking the MR 10 mg after food improves and stabilises absorption and reduces the chances of postural hypotension.
Start‑low monitoring is recommended for older or frail men, with blood‑pressure checks after initiation.
Condition‑Specific Dosing (PBS Recommendations)
For typical BPH the MR 10 mg once‑daily regimen is standard, with symptom improvement expected within 1–2 weeks and maximum benefit over 4–6 weeks.
For ureteric stones, trial protocols most commonly used alfuzosin 10 mg once daily for up to four weeks, but routine use is not universally recommended.
Use caution in hepatic impairment and consider dose avoidance if severe liver dysfunction is present.
For elderly patients or those with reduced renal function, monitor blood pressure and review concomitant medications before and during therapy.
When PBS subsidy applies it may require documented severity or specialist initiation, so check current authority rules before dispensing.
Safety Protocols
Contraindications (Australian Guidelines)
Contraindications include known hypersensitivity to alfuzosin or excipients and severe hepatic impairment, consistent with the safety signals described earlier.
Use is inadvisable in patients with a history of recurrent orthostatic hypotension or syncope where the risks outweigh benefits.
Concurrent use with strong CYP3A4 inhibitors may be contraindicated due to increased alfuzosin exposure.
Adverse Effects (Post‑Market Pharmacovigilance)
Common adverse effects reported in post‑market data include dizziness, fatigue, headache and nasal congestion.
Orthostatic hypotension and syncope remain the most important serious risks and require patient counselling about positional changes and falls prevention.
Less common effects reported include palpitations, peripheral oedema and occasional elevations in liver enzymes.
Combining alfuzosin with antihypertensives or PDE5 inhibitors increases hypotension risk and was highlighted in TGA reports between 2022 and 2025.
Pharmacovigilance trends show higher reporting rates in men over 75, particularly when used alongside other vasoactive medications.
Patient safety checklist: measure baseline blood pressure, reconcile medicines for hypotensive interactions, advise postural precautions and arrange BP re‑check within one to two weeks.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
Alfuzosin MR should be taken after the same meal each day to maintain steady absorption and to minimise peak‑related hypotension.
Alcohol potentiates orthostatic hypotension and patients should be counselled to avoid heavy drinking, especially older men and those in regional communities where drinking patterns vary.
No major interactions with caffeine are documented, but caffeinated drinks may mask symptoms like lightheadedness.
Drug Combinations To Avoid (TGA Safety Alerts)
Antihypertensive medicines including ACE inhibitors, ARBs, calcium channel blockers and diuretics can have additive blood‑pressure lowering effects when used with alfuzosin.
PDE5 inhibitors such as sildenafil and tadalafil can precipitate significant hypotension when combined with alfuzosin; use with caution or avoid concurrent dosing without specialist advice.
Strong CYP3A4 inhibitors such as certain macrolides and azole antifungals raise alfuzosin exposure and should be avoided or monitored closely.
TGA safety alerts have emphasised drug–drug hypotension clusters in community and telehealth settings and recommend pharmacist screening for interacting medicines before supply.
Patient Experience Analysis
Australian Survey Data
Primary‑care audits and patient‑reported outcome data from 2022–2024 show most men experienced modest improvement in IPSS and nocturia using MR 10 mg alfuzosin.
Satisfaction correlated with rapid symptom relief and fewer sexual side‑effects reported compared with some alternatives in these surveys.
Adherence barriers included dizziness and fear of falls, with rural older men living alone particularly vulnerable to stopping therapy early.
Forum And Pharmacy Trends
Community pharmacists in national chains and independents report strong price sensitivity and frequent requests for generics and sustained‑release brands such as Xatral SR equivalents.
Online forum discussions often highlight reduced ejaculatory problems compared with certain other alpha‑blockers, though individual experiences vary.
Telehealth prescribing increased alfuzosin initiation between 2020 and 2024, with pharmacists noting gaps in post‑initiation blood‑pressure monitoring that increase safety risk.
Culturally, Indigenous and remote communities value once‑daily oral regimens, but access and follow‑up remain practical barriers that pharmacists can help bridge.
Distribution & Pricing Landscape
National Pharmacy Chains
Alfuzosin MR formulations are stocked across major Australian pharmacy chains such as Chemist Warehouse, Priceline and TerryWhite as well as independent rural pharmacies.
Stocking choices typically favour generics and MR tablets for cost and supply stability.
Online Pharmacy Growth And Telehealth E‑Scripts
Online pharmacies and telehealth e‑scripts have expanded access to alfuzosin since 2020, but they also raise concerns about adequate blood‑pressure monitoring after initiation.
In our online pharmacy, alfuzosin is available without a prescription, with discreet delivery to Australia in 5‑14 days.
PBS Vs Private Cost Comparisons
PBS subsidy status dramatically alters out‑of‑pocket cost for patients, so verifying current PBS listings before counselling is essential.
Where alfuzosin is not PBS‑subsidised for a specific indication, private script costs vary by brand and retailer and many patients ask pharmacists for lower‑cost generics.
Metformin serves as a practical comparator of how PBS listing produces low‑cost, high‑volume distribution and influences patient price sensitivity in Australia.
Rural supply chains are generally straightforward because alfuzosin does not require refrigeration, but follow‑up monitoring remains a logistical concern in remote areas.
Alternative Options
Comparison Of PBS And Non‑PBS Options
Key alternatives for BPH symptom control include tamsulosin, doxazosin, terazosin and 5‑alpha‑reductase inhibitors such as finasteride and dutasteride.
Tamsulosin is more α1A‑selective and typically has a lower risk of systemic blood‑pressure effects, and it often has broader PBS access than alfuzosin.
5‑alpha‑reductase inhibitors modify disease course by reducing prostate volume over months but carry sexual side‑effect risks and delayed onset of benefit.
Pros And Cons Checklist
- Alfuzosin MR 10 mg — Pro: effective symptom relief, once‑daily MR reduces peak hypotension; Con: broader alpha blockade may increase orthostatic hypotension risk and PBS access can be variable.
- Tamsulosin — Pro: α1A selectivity lowers BP effect and is widely used with PBS support; Con: higher rates of ejaculatory dysfunction reported in some patients.
- 5‑ARIs (Finasteride/Dutasteride) — Pro: disease‑modifying with prostate shrinkage over months; Con: delayed benefit and sexual adverse effects.
Clinical choice should consider symptom severity, comorbidity, subsidy status and patient preference, and pharmacists should facilitate shared decision‑making during counselling.
Regulatory Status
TGA Approval Framework
Alfuzosin formulations such as Xatral SR are registered medicines under the Therapeutic Goods Administration for symptomatic BPH and must meet quality, safety and efficacy standards.
Post‑market surveillance and periodic safety update reporting by sponsors are mandatory components of TGA registration.
PBS Subsidy Process
PBS listing requires an evidence and cost‑effectiveness submission, and listings can mandate specialist initiation or authority prescriptions depending on the decision.
Clinicians should confirm current PBS criteria before prescribing for subsidy eligibility since listings evolve with emerging evidence and sponsor submissions.
Consolidated FAQ
Q: How quickly will alfuzosin help my urinary symptoms?
A: Many men notice improved flow and reduced straining within days to one or two weeks, with maximum benefit around four to six weeks.
Q: Will alfuzosin cause dizziness or fainting?
A: There is a real risk of orthostatic hypotension, especially in older adults or those on antihypertensives; take after a meal, rise slowly and avoid heavy alcohol.
Q: Is alfuzosin available on the PBS?
A: PBS subsidy varies by indication and timing; check the current PBS Schedule or ask your pharmacist for up‑to‑date information.
Q: Can I take alfuzosin with erectile dysfunction medicines?
A: Use caution; combining with PDE5 inhibitors can cause marked hypotension, so discuss timing and dosing with the prescriber.
Q: What monitoring is needed?
A: Baseline blood pressure and a follow‑up check within one to two weeks are recommended, and review for dizziness, falls or interacting medicines.
Visual Guide
Designers and clinicians often ask what visuals will help patients and prescribers understand alfuzosin use.
Priority infographics include a PBS pricing flowchart showing specialist versus GP authority pathways and concession pricing, using metformin as a comparator example for broad PBS coverage effect.
A national distribution heatmap should overlay pharmacy chain density and telehealth e‑script adoption, with rural pharmacy deserts flagged where BP follow‑up is harder.
A patient safety flowchart summarising start‑and‑monitor steps is also useful: Start alfuzosin MR 10 mg → Check BP within one week → If dizziness or falls occur → Stop and contact clinician.
Storage & Transport
Household Storage Under Australian Climate
Alfuzosin tablets and MR formulations are stable at ambient temperatures commonly found across Australia.
Store between 15 °C and 30 °C, keep in the original container, protect from moisture and sunlight and keep out of reach of children.
In very hot or humid regions such as northern Australia, advise storing tablets in cooler parts of the home away from bathrooms and direct sun.
Cold‑Chain Logistics For Pharmacies
No cold chain is required for alfuzosin, simplifying distribution to remote pharmacies and outreach clinics.
Pharmacies should rotate stock appropriately and ensure blister packs or bottles remain sealed to preserve product integrity.
For imports and wholesaler sourcing confirm suppliers meet GDP and GMP standards to assure consistent quality.
Unused medication should be returned to a pharmacy for safe disposal rather than flushed.
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
Start consultations by confirming the indication and reviewing the full medication list for hypotensive interactions.
Measure baseline blood pressure before supply and advise taking the MR 10 mg after the same meal each day to maintain steady levels.
Counsel on postural precautions, avoidance of heavy alcohol and the need for a blood‑pressure check within one to two weeks of starting therapy.
Document counselling, blood‑pressure readings and any authority prescriptions in the dispensing record to support continuity and safety audits.
National Health Authority Recommendations
Follow TGA‑approved product information and local clinical guidance from urology societies or the RACGP for initiation and monitoring decisions.
Consider alternative agents if a patient has significant orthostatic risk or is taking multiple vasoactive drugs.
For remote patients consider pharmacist‑led monitoring and telehealth follow‑up to ensure safe continuation of therapy.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 Days |
| Melbourne | Victoria | 5-7 Days |
| Brisbane | Queensland | 5-7 Days |
| Perth | Western Australia | 5-7 Days |
| Adelaide | South Australia | 5-7 Days |
| Canberra | Australian Capital Territory | 5-7 Days |
| Hobart | Tasmania | 5-7 Days |
| Darwin | Northern Territory | 5-7 Days |
| Gold Coast | Queensland | 5-9 Days |
| Newcastle | New South Wales | 5-9 Days |
| Wollongong | New South Wales | 5-9 Days |
| Geelong | Victoria | 5-9 Days |
| Cairns | Queensland | 5-9 Days |
| Townsville | Queensland | 5-9 Days |
| Alice Springs | Northern Territory | 5-9 Days |