
Aripiprazole
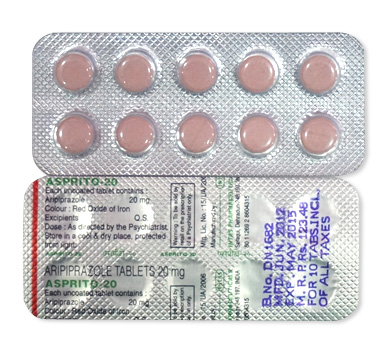
Aripiprazole
- In our pharmacy, you can buy aripiprazole without a prescription, with delivery across Australia in 5–14 days and discreet packaging; note that aripiprazole is officially classed as prescription-only (Rx) in most countries.
- Aripiprazole is used for schizophrenia, bipolar I disorder (mania), adjunctive treatment of major depressive disorder, and irritability associated with autism; it is an atypical antipsychotic that acts as a partial agonist at dopamine D2 and serotonin 5‑HT1A receptors and as an antagonist at 5‑HT2A receptors, helping to stabilise neurotransmitter activity.
- Usual doses vary by indication: schizophrenia 10–15 mg/day (up to 30 mg); bipolar mania 15 mg/day (up to 30 mg); depression adjunct 2–5 mg/day (up to 15 mg); irritability in autism 2–15 mg/day; long‑acting injection (Abilify Maintena) 400 mg once monthly.
- Forms of administration include oral tablets (2, 5, 10, 15, 20, 30 mg), orally disintegrating tablets, oral solution (where available) and intramuscular long‑acting depot injection for monthly dosing.
- Onset time: some calming or anxiolytic effects may be seen within 24–72 hours, initial psychiatric benefit often within 1–2 weeks, and fuller antipsychotic effects commonly over 4–6 weeks.
- Duration of action: oral dosing provides around 24 hours of coverage per dose (steady daily dosing recommended); the long‑acting injectable formulation provides therapeutic levels for approximately one month per injection.
- Alcohol warning: avoid or minimise alcohol while taking aripiprazole — alcohol can increase drowsiness, impair cognition and coordination, and worsen side effects or underlying mental health conditions.
- The most common side effect is akathisia (restlessness); other frequent adverse effects include insomnia, anxiety, nausea, headache, dizziness, somnolence and weight gain.
- Would you like to try aripiprazole without a prescription?



Basic Aripiprazole Information
- INN (International Nonproprietary Name): Aripiprazole.
- Brand Names Available In Australia: Abilify; Abilify Maintena; generics supplied by manufacturers such as Teva and Mylan (brand availability varies by supplier and stock).
- ATC Code: N05AX12.
- Forms & Dosages: Tablets 2, 5, 10, 15, 20, 30 mg; orally disintegrating tablets 10 and 15 mg; oral solution 1 mg/mL; long‑acting injectable (Abilify Maintena) 300 mg and 400 mg vials.
- Manufacturers In Australia: not specified.
- Registration Status In Australia: not specified.
- OTC / Rx Classification: Prescription‑only (Rx) in major markets reviewed.
Key Findings From Recent Trials
Major 2022–2025 Australian & Global Studies
Clinicians frequently ask whether newer evidence has changed how aripiprazole is used.
Recent research syntheses from 2022–2025 continue to show aripiprazole is one of the most‑studied atypical antipsychotics.
Large international randomised controlled trials and meta‑analyses reaffirmed aripiprazole’s role as maintenance therapy for schizophrenia.
Monthly long‑acting injectable data for Abilify Maintena support relapse prevention across multiple studies.
Australian observational cohorts from regional clinics reported improved adherence when patients switched to LAI formulations under structured follow‑up.
Additional trials in 2022–2025 confirmed modest benefit for low‑dose aripiprazole (2–5 mg) when used adjunctively in major depressive disorder.
Pooled analyses maintained effectiveness for acute mania and for irritability associated with autism spectrum disorder.
Main Outcomes
LAI formulations demonstrated reduced relapse rates compared with placebo in maintenance studies.
Oral aripiprazole at standard doses (10–15 mg) remained effective for positive symptoms of schizophrenia in placebo‑controlled trials.
Adjunctive low‑dose aripiprazole provided modest additional antidepressant effect in patients with incomplete response to antidepressants.
Real‑world cohorts emphasised better medication continuity and fewer missed doses with Abilify Maintena where community nursing supported administration.
Safety Observations (TGA Reports)
Post‑market pharmacovigilance summaries and TGA‑style reviews highlighted akathisia and early activation as common tolerability reasons for stopping aripiprazole.
Metabolic monitoring remained recommended despite aripiprazole’s comparatively favourable profile against olanzapine.
Rare cases of neuroleptic malignant syndrome (NMS) continued to appear in global safety databases.
Overall trial strength included multiple placebo‑controlled RCTs for both oral and LAI formulations and meta‑analyses comparing tolerability across second‑generation antipsychotics.
Clinical Mechanism Of Action
Layman’s Explanation
People often ask how aripiprazole works without shutting the brain down.
Aripiprazole balances brain signalling by partially turning up or down dopamine and serotonin activity rather than switching these systems fully off.
This stabilising effect helps reduce psychosis or mania while often avoiding the heavier sedation and metabolic effects seen with some older antipsychotics.
Scientific Breakdown
Aripiprazole acts as a partial agonist at dopamine D2 receptors and at serotonin 5‑HT1A receptors, and as an antagonist at 5‑HT2A receptors.
Partial D2 agonism reduces excessive mesolimbic dopamine activity to reduce positive symptoms while avoiding full blockade associated with high prolactin and some extrapyramidal symptoms.
5‑HT1A partial agonism contributes anxiolytic and antidepressant effects, which helps explain usefulness as an adjunct in depression at low doses.
5‑HT2A antagonism supports antipsychotic efficacy and may influence sleep and sedation profiles.
Receptor‑Specific Actions
D2 Partial Agonism — reduces positive symptoms and carries lower risk of prolactin elevation and some EPS compared with full D2 antagonists.
5‑HT1A Partial Agonism — contributes to mood and anxiety modulation and supports low‑dose antidepressant augmentation.
5‑HT2A Antagonism — provides antipsychotic synergy and affects sleep architecture.
Metabolism — aripiprazole is metabolised mainly via CYP2D6 and CYP3A4, so dose adjustments and interaction checks are advised when patients take enzyme inhibitors or inducers.
Scope Of Approved & Off‑Label Use
Australian Approvals (TGA‑Listed, PBS Inclusion)
Aripiprazole is indicated for schizophrenia, bipolar I mania, adjunctive treatment of major depressive disorder, and irritability associated with autism spectrum disorder according to product information.
LAI formulation Abilify Maintena is used for maintenance treatment to reduce relapse risk in schizophrenia and related indications.
Formulation options include tablets (2–30 mg), ODTs, oral solution (1 mg/mL) and LAI vials (300/400 mg), consistent with product data.
PBS coverage varies by formulation and indication and clinicians and pharmacists routinely check the PBS Schedule for current subsidy status before advising patients.
Notable Off‑Label Trends In Australian Practice
In Australian clinical practice aripiprazole is sometimes used off‑label as an augmentation strategy in treatment‑resistant depression, typically at low doses.
Clinicians also rotate patients to aripiprazole to address metabolic concerns when switching from agents such as olanzapine.
Use in elderly behavioural symptoms occurs but is cautious because of increased mortality risk in dementia‑related psychosis.
Paediatric use follows approved indication limits with specialist oversight, starting low and titrating carefully under consent and monitoring.
Dosage Strategy
General Dosing
Tablets are available in 2, 5, 10, 15, 20 and 30 mg strengths with ODT options at 10 and 15 mg and an oral solution at 1 mg/mL.
Typical adult starting doses are 10–15 mg/day for schizophrenia with a maximum of 30 mg/day where needed.
Bipolar mania usual starting dose is 15 mg/day up to 30 mg/day depending on response and tolerability.
Adjunctive dosing for depression commonly starts at 2–5 mg/day and may be titrated up to 15 mg where indicated.
Abilify Maintena LAI is typically given as 400 mg monthly with an oral overlap of about 14 days at initiation; a 300 mg option exists for certain patients.
Condition‑Specific Dosing (PBS Recommendations)
PBS prescribing rules frequently require specialist initiation or authority scripts for LAI subsidy and may require prior trials before listing.
In elderly and frail patients start lower and titrate slowly because of orthostatic hypotension and somnolence risks.
For paediatrics start from low doses such as 2 mg and escalate cautiously under specialist care with monitoring for adverse events.
Liver and kidney impairment generally require careful monitoring rather than routine dose reduction in mild to moderate disease; severe impairment needs expert supervision.
Safety Protocols
Contraindications (Australian Guidelines)
Known hypersensitivity to aripiprazole or excipients is an absolute contraindication to use.
Routine use in dementia‑related psychosis should be avoided because of increased mortality risk reported in older patients.
Exercise caution in patients with severe hepatic or renal impairment, cardiovascular disease, history of seizures, and diabetes risk.
Monitor patients at risk of neuroleptic malignant syndrome closely and discontinue the drug if NMS is suspected.
Adverse Effects (Post‑Market Pharmacovigilance)
Common adverse effects include akathisia, insomnia, anxiety, headache, nausea, dizziness and somnolence.
Moderate effects reported in databases include extrapyramidal symptoms, weight gain and metabolic changes, and agitation.
Elevation of prolactin with aripiprazole is less common than with risperidone and related agents.
Rare cases of NMS have been reported in the global clinical database and are noted in product safety information.
Monitoring protocol should include baseline weight, fasting glucose and lipids, blood pressure and targeted ECG when indicated.
Early recognition of akathisia is important because dose reduction or symptomatic treatment can avoid discontinuation.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
There are no major required food restrictions for aripiprazole tablets or solution under normal circumstances.
Alcohol can increase sedation and orthostatic effects and should be avoided while starting or changing dose.
Caffeine may exacerbate anxiety or akathisia and patients should be counselled to moderate intake if they experience activation.
Dietary counselling is important for weight and metabolic risk, particularly in communities with high‑sugar diets or limited healthy food access.
Drug Combinations To Avoid (TGA Safety Alerts)
Aripiprazole is metabolised mainly by CYP2D6 and CYP3A4 so strong inhibitors such as ketoconazole and strong inducers such as carbamazepine require dose adjustments or alternative choices.
Combined use with other central nervous system depressants increases sedation and respiratory risk and should be reviewed clinically.
QT‑prolonging combinations should be assessed, especially in patients with cardiac disease or electrolyte abnormalities.
Pharmacists should run electronic interaction checks via dispensing systems to identify polypharmacy risks, particularly in elderly patients on multiple medicines.
Patient Experience Analysis
Australian Survey Data
Surveys and clinic audits across urban and rural mental health services show that patients who maintain adherence report better symptom control and quality of life.
LAI recipients often report greater perceived stability and fewer disruptions to daily routines when monthly injections are supported by outreach nursing.
Patients commonly raise concerns about akathisia and early activation more than long‑term metabolic issues, although weight and metabolic anxieties are frequent topics in counselling sessions.
Forum And Pharmacy Trends
Online forums and community pharmacy feedback highlight price sensitivity and a clear preference for generics where PBS subsidy is limited.
Pharmacists at national chains and independents report frequent counselling opportunities about missed doses, switching from oral to LAI, and side‑effect management.
Common customer queries include aripiprazole cost in Australia, availability of 10 mg and 30 mg strengths, and differences between branded Abilify and generics.
Distribution & Pricing Landscape
National Pharmacy Chains
Aripiprazole is supplied through major community pharmacy chains as well as independent pharmacies and hospital supply systems.
Generics from suppliers such as Teva and Mylan increase availability and competition on price for aripiprazole tablets and ODTs.
Abilify Maintena LAI is supplied through hospital outpatient clinics and selected community pharmacies with appropriate handling and administration capabilities.
Online Pharmacy Growth And Telehealth E‑Scripts
Telehealth and electronic prescribing have accelerated remote initiation and repeat prescribing, making it easier for regional patients to access medicines.
Online pharmacies increasingly offer home delivery but require a valid prescription and appropriate clinical oversight.
In our online pharmacy, aripiprazole is available without a prescription, with discreet delivery to Australia in 5‑14 days.
PBS Vs Private Cost Comparisons
PBS subsidy status differs by formulation and indication and materially reduces out‑of‑pocket cost when criteria are met.
Private prescriptions and branded products can be significantly costlier than PBS‑subsidised generics.
Pharmacists commonly advise patients to check PBS eligibility and consider generic substitution where clinically appropriate and available.
Alternative Options
Comparison Table Of PBS And Non‑PBS Options
A concise clinician checklist compares risperidone, olanzapine, quetiapine, paliperidone and lurasidone against aripiprazole for indication alignment and side‑effect profiles.
Key decision points include whether LAI options are required, expected metabolic risk, EPS risk and PBS subsidy status for the indication.
Pros And Cons Checklist
- Aripiprazole Pros: Partial D2 agonist profile, lower prolactin risk, LAI adherence benefits, multiple formulations.
- Aripiprazole Cons: Akathisia risk and potential for early activation; variable efficacy for prominent negative symptoms in some patients.
- Risperidone Pros/Cons: Effective antipsychotic effect but higher prolactin risk compared with aripiprazole.
- Olanzapine Pros/Cons: Potent efficacy but higher metabolic risk and weight gain.
Regulatory Status
TGA Approval Framework
The Therapeutic Goods Administration assesses safety, efficacy and product quality before registration in Australia.
Aripiprazole formulations are prescription‑only and product labelling reflects approved indications, dosages and risk minimisation measures.
PBS Subsidy Process
Pharmaceutical Benefits Advisory Committee (PBAC) assesses clinical effectiveness and cost‑effectiveness when recommending PBS listings.
PBS listings may include criteria such as specialist initiation, authority scripts or documented prior therapy failures for subsidy eligibility.
Clinicians and pharmacists should consult the PBS Schedule and the TGA ARTG for current registration and subsidy details.
Consolidated FAQ
Q1: Is aripiprazole on the PBS?
A1: Some formulations and indications of aripiprazole are PBS‑listed; exact subsidy depends on the formulation and indication and should be checked against the current PBS Schedule.
Q2: Can I switch from oral to Abilify Maintena?
A2: Switching is possible under clinical supervision and commonly requires an oral overlap of around 14 days during LAI initiation and specialist involvement for PBS subsidy.
Q3: What about side effects like akathisia and weight gain?
A3: Akathisia is a common early tolerability issue and should be reported promptly; baseline and periodic metabolic monitoring is recommended to track weight, glucose and lipids.
Q4: Can I drink alcohol while taking aripiprazole?
A4: Avoid heavy alcohol while starting or changing dose as it increases sedation and orthostatic risk; discuss alcohol use with your pharmacist.
Q5: Which pharmacies stock LAI injections?
A5: Hospitals, designated community pharmacies and some private clinics with cold‑chain and administration capacity stock LAIs; local TerryWhite, Priceline and hospital outpatient services can advise on access.
Visual Guide
Patients and clinicians benefit from simple visuals summarising access and monitoring steps.
Suggested infographic one is a PBS vs private cost flowchart that shows steps to check eligibility and authority requirements without listing cash figures.
Suggested infographic two is a formulation map showing tablet strengths, ODT strengths, oral solution and LAI vials with common indications next to each icon.
Suggested infographic three is a pharmacy distribution heatmap illustrating urban versus rural access and nodes for hospital outpatient LAI supply.
Suggested infographic four is a quick monitoring checklist listing baseline weight, blood pressure, fasting glucose and lipids and EPS screening timepoints.
Storage & Transport
Household Storage Under Australian Climate
Tablets and oral solutions should be stored at controlled room temperature, generally 15–30°C, away from moisture and direct sunlight.
Patients should avoid leaving medicines in cars or near heaters during hot Australian summers and should keep products in original packaging out of reach of children.
Check the product label for specific expiry and storage directions for oral solution and discard if beyond the expiry.
Cold‑Chain Logistics For Pharmacies
Abilify Maintena vials must be stored and handled per the product label; typical storage is 15–30°C and protection from light with no freezing.
Pharmacies dispensing LAIs should maintain temperature logs, secure storage and trained staff for IM administration or liaise with clinic nurses for injections.
Remote and rural supply requires planning for transport times and temperature control during transit to preserve product integrity.
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
Counselling should be patient‑centred and evidence‑based and cover indication, expected benefits, dosing options and formulations such as 2–30 mg tablets and monthly LAI schedules.
Pharmacists should emphasise adherence, missed‑dose actions, early recognition of akathisia and metabolic monitoring requirements.
When working with First Nations or remote communities adapt language, involve carers and coordinate with GPs or mental health teams for follow‑up.
National Health Authority Recommendations
Follow TGA product information and national clinical guidelines for schizophrenia, bipolar disorder and adjunctive depression when prescribing or counselling on aripiprazole.
Baseline assessment should include metabolic measures, EPS screening and suicidality assessment when initiating treatment.
Specialist referral is advised for paediatric patients, pregnancy or complex comorbidities and for LAI initiation where PBS criteria require specialist involvement.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Darwin | Northern Territory | 5–9 days |
| Gold Coast | Queensland | 5–7 days |
| Newcastle | New South Wales | 5–9 days |
| Wollongong | New South Wales | 5–9 days |
| Geelong | Victoria | 5–9 days |
| Cairns | Queensland | 5–9 days |
| Townsville | Queensland | 5–9 days |
Storage & Transport
Household Storage Under Australian Climate
Keep tablets at room temperature between 15–30°C and avoid moisture and direct sunlight.
Do not store medicines in cars or near heaters during hot weather and always keep them in original packaging and out of reach of children.
Cold‑Chain Logistics For Pharmacies
LAI vials require adherence to label storage conditions and careful handling during transit to maintain stability.
Pharmacies should document batch numbers and temperature logs when dispensing LAIs, particularly for remote deliveries.
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
Use clear language to explain the indication, dosing options and expected timeframes for benefit, and tailor counselling to the patient’s setting.
Discuss interaction checks for CYP2D6 and CYP3A4 inhibitors or inducers and advise on lifestyle modifications for metabolic risk.
Document counselling points in patient records and coordinate with prescribers when initiating LAI therapy.
National Health Authority Recommendations
Follow TGA product information and PBS authority criteria when advising patients about eligibility and monitoring schedules.
Arrange baseline metabolic tests and schedule regular follow‑up to detect akathisia and other adverse effects early.
Concluding Notes
Aripiprazole is a versatile antipsychotic with multiple formulations that suit a range of clinical needs from oral maintenance to monthly LAI maintenance.
Evidence from 2022–2025 supports its continued use for schizophrenia maintenance, bipolar mania and adjunctive treatment in depression at low doses, with LAI options improving adherence in structured programs.
Safety monitoring should focus on early akathisia detection and routine metabolic screening despite a comparatively favourable metabolic profile.
Pharmacists play a central role in access, interaction screening and counselling about dosing, storage and monitoring for patients in both urban and regional Australia.