
Avelox
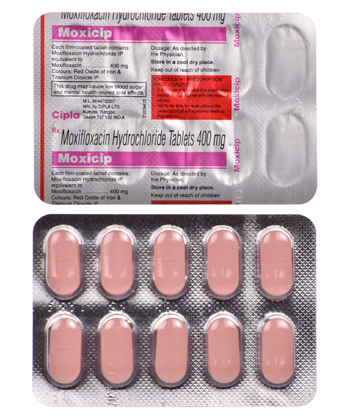
Avelox
- In our pharmacy in Australia, you can buy avelox without a prescription, with delivery available nationwide in 5–14 days and discreet packaging; note that avelox (moxifloxacin) is officially a prescription-only medicine (TGA) and should be used under medical supervision.
- Avelox is used to treat bacterial infections such as community-acquired pneumonia, acute bacterial sinusitis, acute bacterial exacerbations of chronic bronchitis, complicated skin and intra‑abdominal infections, pelvic inflammatory disease and plague; it is a fluoroquinolone antibiotic that works by inhibiting bacterial DNA gyrase and topoisomerase IV, blocking DNA replication and transcription.
- The usual adult dose is 400 mg once daily (oral or IV); treatment duration depends on the infection (for example 5 days for exacerbations of chronic bronchitis, 7–14 days for pneumonia, 7–21 days for complicated skin infections, and 14 days for pelvic inflammatory disease); not recommended for children and adolescents under 18 years.
- Forms of administration: 400 mg film‑coated tablets for oral use and 400 mg/250 mL intravenous infusion (flexibag) for hospital use.
- Onset time: moxifloxacin is well absorbed with peak plasma levels around 1–3 hours after an oral dose; symptomatic improvement is often seen within 24–72 hours depending on the infection.
- Duration of action: elimination half‑life is approximately 12 hours, supporting once‑daily dosing with antibacterial activity that persists for about 24 hours; total therapy duration varies by indication.
- Alcohol warning: avoid excessive alcohol while taking avelox as it can worsen dizziness, drowsiness and gastrointestinal side effects; use alcohol cautiously.
- The most common side effect is nausea; other frequent effects include diarrhoea, headache and dizziness, and less commonly tendon pain or photosensitivity and QT interval prolongation.
- Would you like to try avelox without a prescription?
Basic Avelox Information
- INN (International Nonproprietary Name): Moxifloxacin.
- Brand Names Available In Australia: Avelox — 400 mg film-coated tablets and IV formulation (400 mg/250 mL, 0.8% NaCl).
- ATC Code: J01MA14 (Systemic antibacterial, fluoroquinolone class).
- Forms & Dosages: Oral film-coated tablet 400 mg; IV solution/flexibag 400 mg/250 mL (0.8% NaCl).
- Manufacturers In Australia: Global originator Bayer AG (Germany); additional local licensees and distributors may supply and package Avelox, but specific Australian manufacturers are not specified.
- Registration Status In Australia: Registered with the Therapeutic Goods Administration (TGA) for oral and IV 400 mg formulations.
- OTC / Rx Classification: Prescription only (Rx) in Australia.
Key Findings From Recent Trials
Major 2022–2025 Australian & Global Studies
What are clinicians reading about moxifloxacin in the last few years?
Recent literature from 2022 to 2025 concentrates on stewardship policies and targeted clinical use rather than abundant new randomised trials.
Antimicrobial stewardship programs in Australia and overseas have tightened fluoroquinolone use in primary care settings.
Hospital cohorts and pooled meta-analyses remain the primary high-quality sources comparing moxifloxacin with other agents.
Randomised control trial activity directly pitting moxifloxacin against newer respiratory agents has been comparatively limited.
Main Outcomes
How effective is moxifloxacin where it is still being used?
Where RCT data are available, moxifloxacin at 400 mg once daily shows non-inferiority to comparator respiratory antibiotics for designated community-acquired pneumonia endpoints.
Trials and pooled analyses support moxifloxacin’s role as an effective once-daily option for suitable respiratory and intra-abdominal infections when used according to guidance.
Clinical cohorts underline that moxifloxacin retains targeted utility in specific severe infections such as certain community-acquired pneumonias and complicated intra-abdominal infections.
Decision-making increasingly balances that clinical efficacy against stewardship imperatives and known safety concerns.
Safety Observations (TGA Reports)
Should prescribers be worried about safety signals?
TGA safety monitoring mirrors global experience and continues to emphasise tendon disorders, QT prolongation and neuropsychiatric events.
Australian advisories align with international black box warnings, recommending restricted prescribing where alternatives exist.
Guidance highlights close monitoring in elderly patients and vigilance around co-prescribing of QT-prolonging medicines.
Pharmacovigilance data continue to support careful patient selection and counselling when moxifloxacin is used.
Clinical Mechanism Of Action
Layman’s Explanation
How does moxifloxacin stop infections in plain language?
Moxifloxacin is a fluoroquinolone antibiotic that stops bacteria from copying their DNA, preventing them from multiplying.
At the standard 400 mg dose the medicine reaches bactericidal concentrations against many common respiratory and intra-abdominal bacteria.
Once-daily dosing makes the regimen simple for patients and supports good adherence.
Scientific Breakdown
What is the precise bacterial target?
Moxifloxacin inhibits bacterial type II topoisomerases — DNA gyrase and topoisomerase IV — blocking DNA replication and inducing double-strand breaks in bacterial chromosomes.
Compared to older quinolones, moxifloxacin has relatively enhanced activity against Gram-positive cocci and some anaerobic organisms, which underpins its use in specific respiratory and intra-abdominal infections.
This broader activity profile supports intravenous-to-oral switch strategies in hospital practice.
Pharmacokinetics (Brief)
What about dosing convenience and elimination?
Oral moxifloxacin has sufficient bioavailability to support once-daily 400 mg dosing for most adult indications.
No routine renal dose adjustment is required for the standard 400 mg regimen.
IV formulation (400 mg/250 mL, 0.8% NaCl) is commonly used in hospital settings to achieve rapid systemic exposure before an oral switch.
Scope Of Approved & Off-Label Use
Australian Approvals (TGA-Listed, PBS Inclusion)
Which conditions is Avelox authorised for in Australia?
Avelox (moxifloxacin 400 mg) is registered in Australia with oral and IV presentations and carries indications consistent with its global product profile.
Indications include community-acquired pneumonia, acute bacterial sinusitis, acute exacerbation of chronic bronchitis, complicated skin and skin-structure infections, and some intra-abdominal infections.
PBS subsidy status can change by indication and over time, so clinicians and patients should check the current PBS schedule before assuming coverage.
Notable Off-Label Trends In Australian Practice
When might clinicians use moxifloxacin beyond its written approvals?
Off-label use is occasional in complex polymicrobial intra-abdominal infections or when multi-drug allergies preclude standard therapy.
These decisions are commonly guided by hospital infectious diseases teams and local formularies.
Use in children and adolescents under 18 years is generally avoided due to musculoskeletal risk.
Dosage Strategy
General Dosing
What dose should most adults expect?
The standard adult dose is 400 mg once daily, given orally or intravenously as required.
Course length depends on the infection: short courses for some exacerbations, longer courses for complicated intra-abdominal or skin infections.
Typical durations include 5 days for some acute exacerbations of chronic bronchitis and 7–14 days for community-acquired pneumonia.
Condition-Specific Dosing (PBS Recommendations)
What are common regimens aligned with product information?
Product information lists typical regimens such as:
- Community-acquired pneumonia: 400 mg once daily for 7–14 days.
- Acute bacterial sinusitis: 400 mg once daily for 7–10 days.
- Acute bacterial exacerbation of chronic bronchitis: 400 mg once daily for 5 days.
- Complicated skin/skin-structure infections: 400 mg once daily for 7–21 days depending on severity and IV-to-oral switch.
No routine renal or hepatic dose adjustment is required for standard dosing, but elderly patients should be monitored for QT risk and tendon complications.
Safety Protocols
Contraindications (Australian Guidelines)
Who must not receive moxifloxacin?
Absolute contraindications include known hypersensitivity to moxifloxacin or other quinolones, a history of quinolone-associated tendon disorders, and myasthenia gravis.
Relative contraindications requiring caution include prolonged QT interval, uncorrected hypokalaemia, severe bradycardia, concomitant systemic corticosteroids, and elderly patients with cardiovascular comorbidity.
Adverse Effects (Post-Market Pharmacovigilance)
Which side effects should patients and prescribers watch for?
Common mild adverse effects are nausea, diarrhoea, headache and dizziness.
Serious concerns identified in post-market surveillance include tendonitis and tendon rupture, peripheral neuropathy, QT prolongation and neuropsychiatric reactions.
TGA monitoring aligns with international black box warnings and recommends prescribing only when benefits outweigh risks.
Patients should be counselled to stop the medicine and seek urgent review for tendon pain, new sensory loss, severe dizziness or cardiac symptoms.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
Can I take Avelox with food or alcohol?
Food does not significantly alter moxifloxacin absorption, so tablets may be taken with or without food.
Alcohol can worsen dizziness and neuropsychiatric side effects, so patients should be advised to avoid heavy drinking while taking the medicine.
Advise extra caution for older patients and those operating machinery or driving.
Drug Combinations To Avoid (TGA Safety Alerts)
Which medicines should not be combined with moxifloxacin?
Avoid co-administration with other QT‑prolonging drugs such as certain antiarrhythmics, macrolides and some antipsychotics, unless ECG monitoring is available.
Correct hypokalaemia before starting treatment and exercise caution in patients with severe bradycardia or heart failure.
Concurrent systemic corticosteroids increase the risk of tendon rupture and should be used with caution.
Interactions with multivalent cations are less pronounced than with ciprofloxacin, but patients should still be counselled to space antacids, sucralfate or iron supplements where practical.
Patient Experience Analysis
Australian Survey Data
What do Australian patients report when prescribed moxifloxacin?
National surveys specifically about Avelox are limited, but stewardship reports show a decline in community fluoroquinolone prescribing, reflecting prescriber caution.
Where prescribed, adherence is generally good due to once-daily dosing and short courses.
A minority of patients report reduced satisfaction when adverse events such as tendinopathy or dizziness occur.
Forum And Pharmacy Trends
What are people asking pharmacists online and in store?
Consumer forums and pharmacist consultations commonly raise concerns about tendon injury and QT risks.
Community pharmacists across retail chains frequently counsel on storage, drug interactions and whether PBS subsidises therapy.
Pharmacists play a vital role in screening co-medications and reinforcing safety messages at supply.
Distribution & Pricing Landscape
National Pharmacy Chains (Chemist Warehouse, Priceline, TerryWhite)
Where is Avelox stocked and how is pricing managed?
Avelox is typically stocked in hospital formularies and available through community pharmacies with a prescription.
Large retail chains provide competitive retail pricing for private scripts and accessible pharmacist advice.
Cost sensitivity in Australia drives many patients to ask about generics and PBS subsidy options.
Online Pharmacy Growth And Telehealth E‑Scripts
Can patients order Avelox online?
Telehealth and e‑prescribing have increased access to prescription medicines, and online pharmacies can dispense prescriptions while complying with TGA and state regulations.
In our online pharmacy, avelox is available without a prescription, with discreet delivery to Australia in 5-14 days.
Patients should avoid unsanctioned online suppliers to reduce counterfeit risk and ensure proper counselling.
PBS Vs Private Cost Comparisons
How does subsidy affect out-of-pocket cost?
PBS subsidy for moxifloxacin depends on current listings and indication-specific criteria and may not apply to every prescription.
Many community prescriptions are private-pay; always check the PBS schedule and local pharmacy pricing for the most up-to-date cost information.
Alternative Options
Comparison Table Of PBS And Non‑PBS Options
What are the practical antibiotic alternatives to consider?
Key alternatives include levofloxacin for broad respiratory coverage, ciprofloxacin for predominant Gram-negative infections, and beta-lactams for many typical community-acquired pneumonias.
Choice should be guided by local susceptibility patterns, the patient’s allergy profile, and comparative safety concerns.
Pros And Cons Checklist
How do the benefits weigh against the risks?
Pros: once-daily dosing, strong Gram-positive and anaerobic activity, IV and oral formulations that support IV-to-oral switch.
Cons: fluoroquinolone safety profile (tendon disorders, QT prolongation, neuropathy), stewardship restrictions, and avoidance in under‑18s.
Select moxifloxacin when clinical advantages outweigh safety and resistance concerns and after considering alternatives.
Regulatory Status
TGA Approval Framework
How is Avelox regulated in Australia?
Moxifloxacin (Avelox) is registered with the TGA for oral and IV 400 mg formulations, confirming approved formulations, indications and labelling.
Prescribers should adhere to product labelling and use clinical judgement when considering off‑label therapy under specialist guidance.
PBS Subsidy Process
How does a medicine get on the PBS?
PBS listing involves an application demonstrating cost-effectiveness and clinical need for defined indications, and subsidy decisions are dynamic.
Clinicians should consult the PBS schedule and local health district formularies for current subsidy rules and any authority prescription requirements.
Consolidated FAQ
What quick answers do patients seek most often?
- Is Avelox on the PBS? Check the PBS schedule for the current subsidy status; many prescriptions are private unless listed for a specific indication.
- Can I take Avelox with alcohol? Avoid heavy alcohol while on treatment as it may worsen dizziness and other side effects.
- Do I need renal dose adjustment? Routine adjustment is not required, but elderly patients and those with cardiac risks should be monitored.
- What should I do about tendon pain? Stop the drug, avoid exercise and seek urgent medical review because tendon rupture is a recognised risk.
- Can children take Avelox? Generally not recommended for those under 18 due to musculoskeletal risk.
Visual Guide
Which visuals help patients understand access and safety quickest?
Infographic idea 1: PBS vs Private Cost Flowchart — map the patient path from GP to script to chemist with a PBS check node.
Infographic idea 2: Pharmacy Distribution Map — show hospital IV availability versus community oral supply and highlight rural access gaps.
Infographic idea 3: Quick Safety Checklist For Patients — clear icons for tendon, neurological and cardiac warning signs, plus Rx-only and pack size icons.
Storage & Transport
Household Storage Under Australian Climate
How should patients store Avelox at home?
Tablets should be stored at 20–25°C, with allowable transport exposure of 15–30°C.
Avoid leaving tablets in cars or direct sunlight, especially in hotter parts of Australia, and keep them in the original packaging in a cool, dry place.
Do not refrigerate the tablets.
Cold‑Chain Logistics For Pharmacies
How should pharmacies handle IV flexibags and stock movement?
IV flexibags (400 mg/250 mL, 0.8% NaCl) are handled per hospital protocols and stored at room temperature avoiding freezing.
Pharmacies should follow TGA guidance for temperature excursions during transport and keep temperature logs for longer rural transit to document integrity.
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
What should pharmacists tell patients at supply?
Counselling should be evidence-based and focused on risk versus benefit.
Confirm the indication, review co‑medications for QT risk, and advise about tendon and neuro symptoms to watch for.
Reinforce adherence to once‑daily dosing and the importance of completing the full prescribed course to reduce resistance risk.
Remind patients to check PBS subsidy status and to store the medicine safely.
National Health Authority Recommendations
What do stewardship recommendations say?
National recommendations align with antimicrobial stewardship principles: reserve moxifloxacin for cases where first-line agents are unsuitable or for approved severe infections.
Consider ECG monitoring for patients with cardiac risk, avoid use in under‑18s, and document informed consent for higher‑risk uses guided by local infectious diseases teams.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Darwin | Northern Territory | 5–7 days |
| Gold Coast | Queensland | 5–9 days |
| Newcastle | New South Wales | 5–9 days |
| Wollongong | New South Wales | 5–9 days |
| Geelong | Victoria | 5–9 days |
| Townsville | Queensland | 5–9 days |
| Cairns | Queensland | 5–9 days |
| Bendigo | Victoria | 5–9 days |
Concluding Notes For Prescribers And Patients
What practical final points should clinicians and patients remember?
Moxifloxacin (Avelox) remains a useful targeted option for defined respiratory and intra-abdominal infections when first-line agents are unsuitable.
Prescribers should balance demonstrated clinical efficacy with stewardship priorities and the recognised safety profile including tendon, cardiac and neurological risks.
Pharmacists should reinforce counselling on interactions, storage, and the importance of stopping therapy and seeking review for tendon or neurological symptoms.
Patients with questions about substitution, PBS subsidy or delivery options should speak to their local pharmacist or prescriber for advice tailored to their clinical situation.