
Bactrim
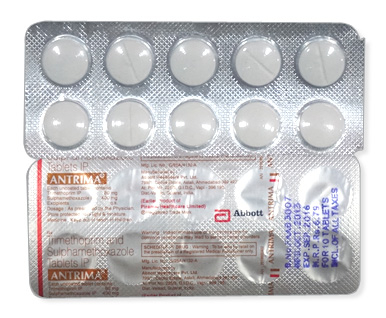
Bactrim
- In our pharmacy, you can buy bactrim without a prescription, with delivery in 5–14 days throughout Australia. Discreet and anonymous packaging.
- Bactrim (sulfamethoxazole and trimethoprim) is used to treat urinary tract infections, acute otitis media in children, bronchitis, traveller’s diarrhoea, shigellosis and to prevent or treat Pneumocystis pneumonia (PCP). It acts by combining a sulfonamide (sulfamethoxazole) that inhibits dihydropteroate synthase and trimethoprim that inhibits dihydrofolate reductase, blocking sequential steps in bacterial folate synthesis for a synergistic antibacterial effect.
- The usual dose for adults is one double‑strength tablet (800 mg sulfamethoxazole / 160 mg trimethoprim) every 12 hours for many infections; PCP prophylaxis is often one DS tablet once daily or three times weekly; PCP treatment dosing is higher (around 15–20 mg/kg/day TMP divided q6–8h). Paediatric dosing is weight‑based (approximately 8 mg/kg TMP + 40 mg/kg SMX divided every 12 hours).
- Forms of administration include oral tablets (400/80 mg and 800/160 mg DS), oral suspension (200 mg/40 mg per 5 mL) and intravenous injection in hospital settings.
- Onset time: antibacterial activity begins soon after the first dose, and many people notice symptom improvement within 24–72 hours, although full resolution may take longer depending on the infection.
- Duration of action: double‑strength tablets are typically dosed every 12 hours (therapeutic effect lasts around 12 hours); total course length varies by indication (commonly 3–14 days for UTIs, up to 21 days for PCP treatment).
- Alcohol warning: avoid excessive alcohol while taking bactrim as it can increase the risk of side effects (such as dizziness, nausea and liver strain); if you have liver disease or are dehydrated, do not drink alcohol while on this medicine.
- The most common side effec are nausea, vomiting, diarrhoea and rash; other frequent effects include headache, hyperkalaemia (especially in older people or those with renal impairment) and mild increases in liver enzymes.
- Would you like to try bactrim without a prescription?
Basic Bactrim Information
- INN (International Nonproprietary Name): Sulfamethoxazole and Trimethoprim (also referred to as “co‑trimoxazole” in some international guidelines).
- Brand Names Available In Australia: Alprim, Triprim, Trimpex.
- ATC Code: J01EE01 — Combinations of sulfonamides and trimethoprim (Sulfamethoxazole and Trimethoprim).
- Forms & Dosages: Tablets 400 mg SMX/80 mg TMP and 800 mg SMX/160 mg TMP (double strength); oral suspension 200 mg SMX/40 mg TMP per 5 mL; IV vial 80 mg TMP/400 mg SMX per 5 mL where available.
- Manufacturers In Australia: Not specified; internationally supplied by Eumedica and numerous generic manufacturers (Sun Pharma, Teva, Sandoz, Cipla, etc.).
- Registration Status In Australia: Products appear under Australian/New Zealand brands and formulations; prescription supply is governed by the Therapeutic Goods Administration registration framework.
- OTC / Rx Classification: Rx Only — prescription required.
Key Findings From Recent Trials
Are clinicians still comfortable prescribing Bactrim for common infections in 2025?
Recent surveillance and guideline reviews from 2022–2025 show two consistent themes in Australia and internationally.
The first theme is declining susceptibility of common urinary pathogens, notably Escherichia coli, to co‑trimoxazole in many regions.
The second theme is preservation of a high‑value role for sulfamethoxazole/trimethoprim in specific indications such as Pneumocystis jirovecii pneumonia prophylaxis and treatment and for some community MRSA strains.
Main Outcomes
Laboratory surveillance from Australian state microbiology networks and private pathology reported variable E. coli resistance exceeding thresholds that have led some GPs and eTG contributors (2023–24) to favour nitrofurantoin or fosfomycin for uncomplicated lower urinary tract infection.
Randomised trial data since 2022 remain limited for first‑line UTI comparisons, and the bulk of evidence is surveillance, meta‑analysis or stewardship platform studies rather than new large RCTs.
For PCP prophylaxis and treatment, the established TMP exposure regimens remain the standard of care where indicated by risk and susceptibility.
Safety Observations (TGA Reports)
TGA pharmacovigilance 2022–25 flagged severe cutaneous adverse reactions, bone marrow suppression and hyperkalaemia as key safety signals in older patients and those with renal impairment.
Those safety signals align with international pharmacovigilance databases and public summaries of product characteristics.
Clinicians are advised to match indication to updated local antibiograms and to reserve co‑trimoxazole where the expected benefit outweighs the resistance and adverse‑event risks.
Clinical Mechanism Of Action
How does Bactrim work, in plain terms?
Bactrim combines two antibiotics that block different steps in a bacterium’s ability to make folate, a vitamin bacteria need to replicate.
The combination means the two drugs together are stronger than either alone, allowing lower doses to be effective against many infections.
Scientific Breakdown
Sulfamethoxazole is a sulfonamide that competitively inhibits dihydropteroate synthase, reducing dihydropteroate synthesis.
Trimethoprim inhibits bacterial dihydrofolate reductase, preventing formation of tetrahydrofolate.
The sequential blockade produces bactericidal activity against many Gram‑negative organisms and selected Gram‑positive organisms.
Pharmacodynamics & Synergy
The fixed mass ratio in standard tablets is typically 5:1 SMX:TMP, reflected in common strengths such as 400/80 mg and 800/160 mg tablets.
This ratio yields synergistic inhibition with a post‑antibiotic effect for susceptible strains and useful tissue penetration into urine and lung.
Resistance mechanisms include plasmid‑mediated altered enzymes, sul gene variants and decreased uptake; consult local antibiogram data to guide empirical choice.
Scope Of Approved & Off‑Label Use
What is Bactrim approved for in Australia and how do prescribers use it off‑label?
Australian Approvals (TGA‑Listed, PBS Inclusion)
Product monographs and international summaries list UTI, shigellosis, some ear and chest infections in children and importantly PCP prophylaxis and treatment as indications.
In Australia the active ingredient is sulfamethoxazole and trimethoprim sold under brand names including Alprim and Triprim in tablet and suspension forms.
PBS listing varies by indication and formulation, and subsidy status should be checked at point of care because it can change with submissions.
When not subsidised, clinicians and patients commonly source generics through community pharmacies.
Notable Off‑Label Trends In Australian Practice
Off‑label uses observed 2022–25 include selective use for community‑acquired MRSA skin infections, some traveller’s diarrhoea cases and as oral step‑down from IV therapy when susceptibilities are confirmed.
Prescribers should document the clinical rationale when choosing co‑trimoxazole instead of PBS‑recommended first‑line options.
Dosage Strategy
What dose should I expect for adults and children?
General Dosing
For most adult infections adult dosing follows product information: one double‑strength tablet (800 mg SMX/160 mg TMP) every 12 hours.
Paediatric dosing uses 8 mg/kg TMP plus 40 mg/kg SMX divided every 12 hours, typically using the 200 mg SMX/40 mg TMP per 5 mL suspension.
Condition‑Specific Dosing (PBS Recommendations)
For PCP treatment higher TMP exposure is required: 15–20 mg/kg TMP daily in divided doses q6–8h for 14–21 days.
Uncomplicated UTI durations commonly range 3–14 days depending on severity; shigellosis courses typically 5 days; PCP prophylaxis is often one DS tablet daily or three times weekly while risk persists.
Dosage adjustments are required for renal impairment and the drug should be avoided if creatinine clearance is less than 15 mL/min.
Elderly patients need monitoring for hyperkalaemia and renal function prior to and during therapy when indicated.
Safety Protocols
Who should not take Bactrim and what should be watched for?
Contraindications (Australian Guidelines)
Absolute contraindications include known allergy to sulfonamides or trimethoprim, severe renal or hepatic impairment and megaloblastic anaemia due to folate deficiency.
Infants under two months, pregnancy (especially near term) and breastfeeding are listed as situations that generally contraindicate use or require specialist advice.
Relative cautions include G6PD deficiency, porphyria, haematological disorders and the elderly.
Adverse Effects (Post‑Market Pharmacovigilance)
Common adverse effects are nausea, vomiting, diarrhoea, rash, headache, hyperkalaemia and mild liver enzyme rises.
TGA reports 2022–25 emphasise rare but serious risks such as Stevens–Johnson syndrome, toxic epidermal necrolysis and blood dyscrasias including aplastic anaemia.
Recommended monitoring includes baseline renal function and electrolytes, particularly potassium, and a full blood count for prolonged therapy.
Advise patients to stop and seek urgent review for widespread rash, mucosal involvement or systemic symptoms.
Interaction Mapping
Will Bactrim interact with the medicines the patient already takes?
Food Interactions (Alcohol, Coffee, Diet In Australia)
No major food or coffee interactions are reported with co‑trimoxazole.
Patients should avoid excessive alcohol while unwell because alcohol can worsen gastrointestinal side effects and dehydration.
Advise good hydration during therapy, especially in hot Australian climates.
Drug Combinations To Avoid (TGA Safety Alerts)
Co‑trimoxazole potentiates warfarin and can increase INR, so closer monitoring is required when warfarin is co‑prescribed.
Trimethoprim interacts with methotrexate increasing toxicity, and it can raise serum potassium when combined with ACE inhibitors, ARBs or potassium‑sparing diuretics including spironolactone.
Trimethoprim may also reduce tubular secretion of creatinine, causing an apparent creatinine rise without true loss of glomerular filtration.
TGA safety communications advise regular INR checks with warfarin co‑prescription and avoidance or close monitoring when combined with drugs that predispose to hyperkalaemia or marrow suppression.
Patient Experience Analysis
What do Australian patients say about taking Bactrim?
Australian Survey Data
Primary‑care and pharmacy surveys from 2022–25 highlight cost sensitivity, concern about sulfa allergy and variable tolerance of GI upset or rash.
Patients frequently ask about whether a generic Bactrim tablet is as effective as a brand and whether the suspension tastes acceptable for children.
Forum And Pharmacy Trends
Community pharmacist notes show frequent counselling on allergy screening, pregnancy checks and monitoring for rash or jaundice.
Online forums often show confusion around DS versus regular tablets and concern about severe reactions, which increases pharmacist engagement and advice requirements.
Rural patients report occasional stock variability and longer waits for e‑scripts from telehealth providers.
Overall satisfaction is higher when pharmacists provide clear side‑effect recognition advice, interaction checks and rationale for antibiotic selection.
Distribution & Pricing Landscape
Where do Australians obtain co‑trimoxazole and what does it cost?
National Pharmacy Chains
Sulfamethoxazole and trimethoprim formulations are widely available through national chains such as Chemist Warehouse, Priceline and TerryWhite as well as independent pharmacies.
Generics and branded products such as Alprim and Triprim are commonly stocked.
Online Pharmacy Growth And Telehealth E‑Scripts
Online pharmacy services and telehealth e‑scripts expanded over 2020–25, increasing home delivery and remote counselling for antibiotics.
In our online pharmacy, Bactrim can be ordered with a valid prescription and delivered discreetly across Australia in 5–14 days.
PBS Vs Private Cost Comparisons
When SMX‑TMP is PBS‑listed for an indication, the patient co‑payment is substantially reduced compared with private scripts.
If not subsidised, generic tablets are usually more economical than branded products and price varies by retailer, pack size and promotions.
Rural pharmacies can face higher freight costs and intermittent stock shortages that affect availability and pricing.
Alternative Options
What are reasonable alternatives to consider for common infections?
Comparison Table Of PBS And Non‑PBS Options
For uncomplicated cystitis Australian guidelines increasingly prioritise nitrofurantoin and fosfomycin where available because of favourable E. coli susceptibility profiles.
Trimethoprim alone may be appropriate depending on local resistance patterns; fluoroquinolones such as ciprofloxacin are effective but reserved due to collateral effects and safety warnings.
Pros And Cons Checklist
- Co‑Trimoxazole Pros: Broad spectrum, oral and IV options, established efficacy for PCP and some community MRSA strains.
- Co‑Trimoxazole Cons: Rising E. coli resistance for UTI, sulfa allergy risk, notable drug interactions and monitoring requirements.
Regulatory Status
How is Bactrim regulated in Australia?
TGA Approval Framework
The international nonproprietary name is sulfamethoxazole and trimethoprim (ATC J01EE01) and products are registered through the Therapeutic Goods Administration for legal supply and labelling.
All presentations are prescription‑only in major markets and TGA pharmacovigilance collects and publishes adverse event reports that inform updates to product information.
PBS Subsidy Process
PBS listing requires submission demonstrating clinical need, cost‑effectiveness and defined criteria and may be indication‑specific.
Prescribers must follow PBS authority rules when prescribing for subsidised indications such as PCP prophylaxis where applicable.
Consolidated FAQ
What common questions do patients ask about Bactrim in Australia?
- Can I get Bactrim without a prescription in Australia? No — sulfamethoxazole and trimethoprim is prescription‑only; see a GP or telehealth service for an e‑script.
- Is Bactrim safe in pregnancy or breastfeeding? It is generally avoided in late pregnancy and used cautiously when breastfeeding; discuss alternatives with a prescriber.
- What should I do if I miss a dose? Take the missed dose as soon as remembered unless it is almost time for the next dose; do not double doses.
- How long until it works for a UTI? Symptom improvement often occurs within 48–72 hours if the infecting organism is susceptible; return for review if there is no improvement.
- Should I stop if I get a rash? Stop immediately and seek urgent medical review for any widespread rash or systemic symptoms.
Visual Guide
What visual tools help patients and clinicians understand use and cost?
Recommended assets include a PBS pricing flowchart that shows when PBS applies and the likely patient co‑payment versus private cost for DS tablets, regular tablets and suspension.
A pharmacy distribution map that contrasts urban and rural stock reliability and common supply routes helps telehealth providers anticipate delays.
A clinical UTI decision tree using local antibiogram thresholds can guide when to choose nitrofurantoin versus co‑trimoxazole.
A safety poster with red flags (rash, jaundice, severe GI bleed, breathlessness) and a monitoring checklist (baseline renal, potassium, FBC if prolonged) is recommended for dispensing areas.
Storage & Transport
How should patients and pharmacies store and transport Bactrim in Australian conditions?
Household Storage Under Australian Climate
Tablets and suspensions should be stored at room temperature (20–25°C) away from sunlight and humidity and not in bathrooms.
Reconstituted suspensions must be protected from light, not frozen and discarded after the manufacturer recommended period.
Advise patients not to leave medicine in parked cars during hot Australian summers.
Cold‑Chain Logistics For Pharmacies
Tablets are generally stable at ambient temperature and IV vials should follow hospital supply procedures and labelled storage requirements.
Rural pharmacies must plan for temperature‑monitored shipping for sensitive consignments and stock rotation to manage freight delays.
Guidelines For Proper Use
How should pharmacists counsel patients receiving Bactrim?
Pharmacist Counselling Style In Australia
Confirm the indication, pregnancy status and allergy history including sulfonamide allergy before supply.
Check other medicines for interactions (warfarin, ACE inhibitors, spironolactone, methotrexate) and calculate paediatric doses by weight using the suspension where required.
Explain dosing schedule (one DS tablet q12h for many infections), discuss likely time to symptom improvement and outline red flags that require urgent assessment.
National Health Authority Recommendations
TGA and eTG alignment encourages use of local antibiograms to select empiric therapy and to reserve SMX‑TMP where resistance patterns and clinical needs support its use.
For telehealth e‑scripts arrange appropriate pathology or follow‑up and document counselling in the patient record to support antimicrobial stewardship.
Concluding Notes
When chosen appropriately, co‑trimoxazole remains a valuable antibiotic for particular indications such as PCP and selected community infections.
Rising E. coli resistance for urinary infections and the drug’s interaction and safety profile mean careful patient selection, monitoring and use of local antibiograms are essential.
Pharmacists and prescribers should keep updated with TGA communications and PBS changes to ensure safe, cost‑effective care.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-9 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-7 days |
| Wollongong | New South Wales | 5-7 days |
| Cairns | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Geelong | Victoria | 5-7 days |
| Ballarat | Victoria | 5-9 days |