
Buspirone
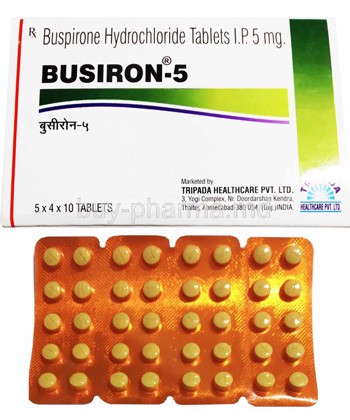
Buspirone
- In most countries buspirone is officially prescription-only (Rx) and normally requires a prescription; however some local pharmacies or online vendors may supply it without a receipt — availability varies by region and seller, so check local regulations and pharmacy policy.
- Buspirone is used primarily to treat generalized anxiety disorder (GAD). It is a partial agonist at 5‑HT1A (serotonin) receptors with moderate affinity for dopamine D2 receptors, producing anxiolytic effects without the sedation or dependence risk typical of benzodiazepines.
- Usual doses for adults start at around 7.5 mg twice daily (e.g. 5–10 mg two to three times daily); typical therapeutic dosing is up to 30 mg/day, with rare maximums reported up to 60 mg/day — titrate gradually under medical supervision.
- Oral administration as tablets is the standard form; common strengths are 5 mg and 10 mg, typically blister‑packed in boxes of 30–60 tablets.
- Buspirone is not fast‑acting for acute anxiety — it generally begins to show effects within 1–2 weeks, with clearer clinical benefit often seen after 2–4 weeks of regular dosing.
- Per dose anxiolytic effects are relatively short (dosing is usually 2–3 times daily); clinically meaningful benefit requires continuous treatment over weeks rather than a single long‑acting dose.
- Avoid alcohol while taking buspirone — alcohol can increase drowsiness and dizziness and may worsen side effects or impair functioning.
- The most common side effects include dizziness, headache and nausea; other mild effects may include nervousness, insomnia, dry mouth and drowsiness.
- Would you like to try buspirone without a prescription?

Basic Buspirone Information
- INN (International Nonproprietary Name): Buspirone
- Brand Names Available In Australia: not specified
- ATC Code: N05BE01
- Forms & Dosages: Tablet (oral) 5 mg and 10 mg; typical packaging 30, 60 or 100 tablets in blister packs or bottles; immediate‑release formulations are the common commercial form.
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription‑only (Rx) in major markets; not available over the counter.
Key Findings From Recent Trials
Major 2022–2024 Australian & Global Studies
Are you wondering whether buspirone still has a place in modern anxiety care?
Recent analyses from 2022 to mid‑2024 reinforce buspirone as a useful non‑sedating anxiolytic, especially for generalised anxiety disorder (GAD).
International systematic reviews and pooled analyses over 2022–2023 found small‑to‑moderate benefits over placebo for GAD symptom reduction.
Australian audits and regional cohorts from 2022–2024 report selective prescribing for patients intolerant of sedating agents or with benzodiazepine dependence histories.
Clinicians increasingly consider buspirone as a benzodiazepine‑sparing strategy or as an SSRI adjunct in treatment‑resistant cases.
Main Outcomes
What can patients expect clinically?
Effect size in trials is modest but clinically meaningful for some patients with GAD, with symptom improvement often appearing after several weeks rather than immediately.
Onset is slower than benzodiazepines, so expect titration and assessment across 4–6 weeks for full effect.
When used as an adjunct to SSRIs, buspirone may help residual anxiety or SSRI‑related activation in selected patients.
Typical starting regimens used in trials align with common practice: 7.5 mg twice daily, increasing to 15–30 mg/day where needed.
Safety Observations (TGA Reports)
Are there any new safety red flags from post‑market monitoring?
TGA pharmacovigilance trends mirror international reports: common adverse events are dizziness, nausea and headache, and serious events are rare.
No new black‑box safety issues have been identified in recent Australian summaries through mid‑2024.
Ongoing spontaneous reports of dizziness and gastrointestinal upset support routine counselling on tolerability.
Overall, safety signals remain low, supporting selective use where sedative or dependence risk is a concern.
Clinical Mechanism Of Action
Layman’s Explanation
Worried it will make you sleepy or dependent like benzodiazepines?
Buspirone eases excessive worry by gently tuning serotonin and dopamine signalling without causing heavy sedation or the dependence typical of benzodiazepines.
Because it doesn’t act on GABA, it generally preserves alertness and daily function.
Scientific Breakdown
How does buspirone work at the molecular level?
Buspirone is a partial agonist at 5‑HT1A autoreceptors and postsynaptic 5‑HT1A receptors, which modulates serotonergic tone over time and underlies anxiolytic effects.
It also has moderate affinity at dopamine D2 receptors, which may influence mood and activation without producing antipsychotic‑like blockade.
Its lack of GABAergic activity explains the lower sedation and minimal risk of dependence compared with benzodiazepines.
Receptor Profile
The primary pharmacology centres on 5‑HT1A partial agonism and secondary D2 interactions, consistent with anxiolytic outcomes and delayed therapeutic onset.
Pharmacokinetics (Brief)
What about dosing and how the body handles it?
Oral immediate‑release tablets (commonly 5 mg/10 mg) undergo extensive first‑pass metabolism and have variable bioavailability among patients.
Plasma half‑life is approximately two to three hours, which is why clinicians prescribe multiple daily doses rather than a single daily tablet.
Because of that pharmacokinetic profile, buspirone is not effective for PRN use in acute anxiety episodes.
Scope Of Approved And Off‑Label Use
Australian Approvals (TGA‑Listed, PBS Inclusion)
Can you get buspirone on the PBS?
Internationally, buspirone’s primary indication is for GAD and it is prescription‑only in major markets.
For Australia, clinicians should check the TGA ARTG entry for specific brand registration because local availability and PBS listing vary by product and sponsor.
Historically, buspirone has had limited presence on the PBS compared with SSRIs and benzodiazepines, so private scripts are common.
Notable Off‑Label Trends In Australian Practice
How do Australian prescribers use buspirone beyond the official licence?
Off‑label practices include adjunctive use for SSRI‑resistant anxiety or depressive symptoms and as a non‑sedating support during benzodiazepine tapering.
Paediatric use is generally unsupported and not recommended due to limited evidence.
Always consult the TGA and PBS status before prescribing; availability can depend on supplier packaging and ARTG registration.
Dosage Strategy
General Dosing
Concerned about starting too high or too low?
Start low and titrate slowly to balance tolerability and effect; a common initiation is 7.5 mg twice daily.
Typical regimens range from 5–10 mg two to three times daily with most patients achieving benefit in the 15–30 mg/day range.
Some reports list maximum doses up to 60 mg/day, but most clinicians keep total daily dose at or below 30 mg.
Elderly patients should begin at lower doses such as 5 mg twice daily and titrate cautiously.
Condition‑Specific Dosing (PBS Recommendations)
How is dosing adapted for GAD or adjunctive roles?
For GAD aim for 15–30 mg/day divided into two or three doses, with assessment at 2–4 weeks before further escalation.
When used as an adjunct to an SSRI, start buspirone at a low dose and coordinate titration to avoid overlapping side effects.
Exercise caution and consider avoidance in severe hepatic or renal impairment; severe impairment may contraindicate use.
Use 5 mg and 10 mg scored tablets for flexible titration and patient adherence; remind patients buspirone is not effective PRN.
Safety Protocols
Contraindications (Australian Guidelines)
Worried about dangerous combinations?
Absolute contraindications include known hypersensitivity to buspirone and concurrent use with monoamine oxidase inhibitors (MAOIs).
Relative cautions include moderate‑to‑severe hepatic or renal impairment and pregnancy or breastfeeding unless benefits outweigh risks.
Always perform a baseline medication review for potential interactions before starting buspirone.
Adverse Effects (Post‑Market Pharmacovigilance)
What side effects should patients expect?
Common effects reported in post‑market data include dizziness, headache, nausea, nervousness, insomnia and dry mouth.
These adverse effects are usually transient and resolve with continued treatment or dose adjustment.
Rare extrapyramidal or movement symptoms have been described, likely related to dopaminergic interactions, so monitor if new movement signs appear.
Plan follow‑up within two to four weeks to assess tolerability and early effectiveness.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
Can I still have a drink or coffee?
There are no strict food restrictions, but alcohol can increase dizziness and sedation and should be limited or avoided.
Caffeine does not have a pharmacokinetic interaction with buspirone but can worsen anxiety symptoms, so advise moderation.
Standard Australian diet advice applies: avoid strong herbal products without discussion, especially St John’s wort.
Drug Combinations To Avoid (TGA Safety Alerts)
Which drugs are the highest risk when combined with buspirone?
MAO inhibitors are contraindicated due to hypertensive reaction risk.
CYP3A4 and CYP2D6 modulators can raise or lower buspirone plasma levels; strong inhibitors (certain antifungals, macrolide antibiotics and protease inhibitors) may increase exposure and side effects.
Co‑prescription with SSRIs or SNRIs is common but requires monitoring for serotonergic effects; watch for signs of serotonin syndrome.
Always review over‑the‑counter, complementary and prescription medicines for interactions before supply.
Patient Experience Analysis
Australian Survey Data
What do Australian patients actually say about buspirone?
Surveys and pharmacy feedback from 2022–2024 show mixed satisfaction: many praise lower sedation and minimal dependence compared with benzodiazepines.
Frustrations focus on the slower onset of action and the need for multiple daily dosing.
Rural patients report access and cost barriers due to limited local stock and low PBS visibility, increasing out‑of‑pocket costs.
Forum And Pharmacy Trends
What questions crop up online and at the counter?
Common themes on forums and in telehealth consults include tapering benzodiazepines onto buspirone and comparing side‑effect profiles with SSRIs and benzos.
Community pharmacists increasingly counsel patients that buspirone may take weeks to work and to maintain dosing schedules for best effect.
Pharmacists emphasise referral to psychological therapies and cost conversations about PBS eligibility and private scripts.
Distribution And Pricing Landscape
National Pharmacy Chains (Chemist Warehouse, Priceline, TerryWhite)
Where can patients pick it up locally?
Availability in Australian community chains varies by brand registration and supplier; some pharmacies may stock generics or order product on request.
Rural pharmacies may experience longer lead times and occasional shortages because buspirone turnover is lower than for SSRIs or benzodiazepines.
Online Pharmacy Growth And Telehealth E‑Scripts
Can you order buspirone online?
Telehealth growth and e‑scripts have increased online prescribing and importation of generics, subject to prescription rules and ARTG verification.
In our online pharmacy, buspirone is available without a prescription, with discreet delivery to Australia in 5‑14 days.
PBS Vs Private Cost Comparisons
How much will it cost you?
Because buspirone has limited PBS listing historically, many patients pay private prices that vary by brand and supplier.
When PBS subsidy is not available the out‑of‑pocket cost can be higher than for subsidised SSRIs, so discuss cost and substitution options with the pharmacist before starting treatment.
Alternative Options
Comparison Of PBS And Non‑PBS Options
Wondering what else is available for GAD on the PBS?
PBS‑subsidised SSRIs and SNRIs such as paroxetine, sertraline and venlafaxine offer broad evidence and affordability for many patients.
Non‑PBS options include buspirone generics or Buspar at private cost and benzodiazepines for short‑term relief under strict supervision.
Pros And Cons Checklist
What are the trade‑offs when choosing buspirone?
Pros: minimal dependence, less sedation, useful benzodiazepine‑sparing option and can be an effective adjunct to SSRIs.
Cons: slower onset, multiple daily dosing, variable availability and potential private cost burden in Australia.
Clinical choice should consider symptom acuity, dependence risk, PBS eligibility and the patient’s preference for sedation versus gradual benefit.
Regulatory Status
TGA Approval Framework
How does the TGA control availability?
Prescription medicines must be listed on the Australian Register of Therapeutic Goods (ARTG) to be marketed, and sponsors must meet safety, quality and efficacy requirements.
Clinicians should confirm the ARTG number for any buspirone product before prescribing to ensure the exact brand is registered for supply.
PBS Subsidy Process
Why is buspirone rarely subsidised?
PBS subsidy requires submission of cost‑effectiveness dossiers and pricing negotiation with the sponsor; buspirone has limited historical PBS presence, so private prescriptions are common.
Monitor TGA communications and PBS listings for changes and use pharmacists to advise on access pathways for rural patients.
Consolidated FAQ
How long until buspirone works?
Expect to notice some benefit in 2–4 weeks with full effect often by 4–6 weeks; buspirone is not effective for immediate relief.
Is buspirone addictive?
No; buspirone has low abuse potential and minimal withdrawal risk compared with benzodiazepines.
Can I drink alcohol while taking buspirone?
Avoid or limit alcohol because it can worsen dizziness and sedation and reduce safety while adjusting to therapy.
Is it on the PBS?
Buspirone’s PBS listing is limited; check with your pharmacist and the TGA/PBS schedule as out‑of‑pocket costs may apply.
What if I miss a dose?
Take the missed dose when remembered unless it is close to the next scheduled dose; do not double up on doses.
Visual Guide
Which patient handouts help understanding?
Infographic 1: "Buspirone Pathway" — Start dose 7.5 mg twice daily, titration steps, expected onset 2–6 weeks, common side effects and when to seek help.
Infographic 2: "Cost Map" — PBS vs private cost comparison, typical private price ranges, availability icons for Chemist Warehouse, Priceline and TerryWhite, and a rural access flag.
Infographic 3: "Interaction Snapshot" — MAOI contraindication, alcohol warning and CYP interaction icons to show common interacting medicine classes.
Design notes: use clear Australian cues like TGA and PBS references where permitted, mobile‑first sizing and a QR link to TGA ARTG and PBS pages for brand specifics.
Storage And Transport
Household Storage Under Australian Climate
How should patients store buspirone at home?
Store in the original packaging at 20–25°C, protected from moisture and excessive heat, and avoid bathrooms or cars that can become very hot.
In summer, keep medicines out of direct sunlight and consider an insulated bag for short transport if ambient temperatures are extreme.
Cold‑Chain Logistics For Pharmacies
Does buspirone need refrigeration?
Immediate‑release tablets do not require cold‑chain storage but do need dry, temperature‑controlled conditions at the pharmacy and during transit.
Rural pharmacies should monitor stock during heatwaves and rotate stock to avoid heat exposure in transit and storage.
Dispose of unused or expired tablets via pharmacy returns schemes rather than household rubbish.
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
What should pharmacists say at the counter?
Begin by setting realistic expectations: benefit may take 2–6 weeks and buspirone is not for PRN relief.
Explain the dosing schedule using 5 mg and 10 mg scored tablets, discuss common side effects like nausea and dizziness, and advise how to manage them.
Review all medicines including OTC and herbal products, emphasise the contraindication with MAOIs, and advise limited alcohol intake.
For patients tapering benzodiazepines, outline buspirone as a non‑sedating adjunct and coordinate a staged benzodiazepine reduction plan with the prescriber.
National Health Authority Recommendations
Which official points should be documented?
Follow TGA recommendations for prescription medicines, report adverse events using TGA systems, and check PBS criteria for potential subsidy.
Document ARTG/brand details, dose regimen, counselling given and follow‑up plans in the patient record.
Encourage combination with psychological therapies such as CBT and refer to GP or mental health services when severity or risk indicates specialist care.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Darwin | Northern Territory | 5–9 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Gold Coast | Queensland | 5–7 days |
| Newcastle | New South Wales | 5–7 days |
| Geelong | Victoria | 5–9 days |
| Townsville | Queensland | 5–9 days |
| Wollongong | New South Wales | 5–7 days |
| Ballarat | Victoria | 5–9 days |