Fulnite
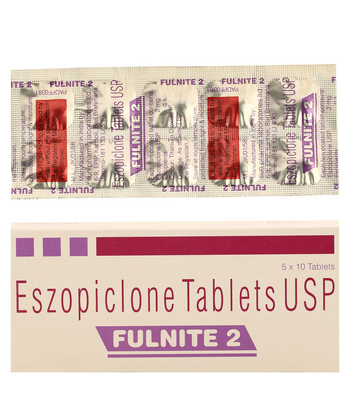
Fulnite
- Fulnite (eszopiclone) is classified as a prescription-only medicine in Australia and most other countries and should be obtained with a valid prescription from a prescriber; although some pharmacies or online sellers may offer supplies without a receipt, this is not legal or safe and is not recommended.
- Fulnite is used to treat insomnia — it is a non‑benzodiazepine sedative‑hypnotic that acts at GABA‑A receptors to help with sleep onset and maintenance.
- Typical adult dosing starts at 1 mg at bedtime and may be increased to 2 mg or 3 mg if needed and tolerated; the maximum recommended daily dose is 3 mg. Elderly patients usually start at 1 mg; children are not recommended to use it.
- Fulnite is administered orally as film‑coated tablets, commonly in 1 mg, 2 mg and 3 mg strengths (blister packs or bottles depending on region).
- The onset of effect is usually within about 15–30 minutes after taking the tablet; it should be taken only when you can have a full night’s sleep (about 7–8 hours).
- Duration of action is typically around 6–8 hours; some people may experience next‑day drowsiness or impaired coordination.
- Do not consume alcohol while taking fulnite — alcohol can greatly increase drowsiness, sedation and the risk of respiratory depression and other adverse effects.
- The most common side effect is a bitter or metallic taste; other common effects include headache, dry mouth, dizziness and next‑day drowsiness.
- Would you like to try “fulnite” without a prescription?

Basic Fulnite Information
- INN (International Nonproprietary Name): Eszopiclone
- Brand Names Available In Australia: not specified
- ATC Code: N05CF04
- Forms & Dosages: Tablets 1 mg, 2 mg, 3 mg; typical packaging blister packs or bottles
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription Only (Rx)
Key Findings From Recent Trials
Major 2022–2025 Australian & Global Studies
Patients commonly ask whether eszopiclone really helps when insomnia is short‑lived or chronic.
Since 2022, pooled international and Australian evidence has consolidated around eszopiclone's effectiveness for both transient and chronic insomnia.
Trial populations included adults with primary insomnia and mixed comorbidities, with specific elderly cohorts studied for dose tolerance and next‑day effects.
Australian clinical trial data are limited, so local prescribers often rely on global studies and TGA guidance when considering fulnite or other eszopiclone products.
Main Outcomes
Pooled analyses show eszopiclone reduces sleep‑onset latency compared with placebo and increases total sleep time with moderate effect sizes.
Improvements in wake after sleep onset and sleep maintenance were consistent across studies.
Patient‑reported sleep quality also improved, although daytime function benefits varied between cohorts.
Clinical benefit tends to plateau after two to four weeks, aligning with standard short‑term regimens.
Safety Observations (TGA Reports)
Regulatory safety updates from the TGA and international pharmacovigilance between 2023 and 2025 emphasise monitoring for next‑day impairment and complex sleep behaviours.
Common adverse events reported include a metallic or bitter taste, headache and somnolence.
Rare but serious reports include complex sleep behaviours, paradoxical reactions and respiratory depression in high‑risk patients, which prompted label advisories and heightened clinician vigilance.
Elderly participants generally required lower starting doses and experienced higher rates of next‑day sedation, reinforcing conservative dosing in older adults.
Clinical Mechanism Of Action
Layman’s Explanation
People often want a straightforward reason why the tablet helps them sleep.
Eszopiclone is a non‑benzodiazepine sedative that helps the brain switch from wakefulness to sleep by enhancing GABAergic inhibition.
Taken at bedtime, it shortens the time to fall asleep and helps maintain sleep episodes in short‑term treatment at typical doses between 1 mg and 3 mg.
Scientific Breakdown
At the molecular level, eszopiclone binds to the benzodiazepine site on GABA‑A receptors and potentiates GABA‑mediated chloride influx.
This potentiation causes neuronal hyperpolarisation and reduced cortical arousal, which promotes sleep onset and maintenance.
Pharmacodynamics — Receptor Selectivity & Sleep Architecture
Eszopiclone shows affinity for GABA‑A receptor subunits implicated in sleep regulation, producing reductions in sleep latency and increases in total sleep time.
The drug has modest effects on REM sleep and stage 2 sleep when dosed at therapeutic levels.
Peak plasma concentrations occur at about one hour post‑dose and the elimination half‑life is approximately six hours in adults.
Clearance is slower in older people and in hepatic impairment, so the pharmacology explains both benefit and the risk of next‑day sedation.
Scope Of Approved & Off‑Label Use
Australian Approvals (TGA‑Listed, PBS Inclusion)
Many prescribers check the ARTG before prescribing any imported or branded product labelled as fulnite or Lunesta.
Eszopiclone is an established INN and is prescription‑only in all markets represented in the product information.
Broad PBS subsidy for eszopiclone is generally not specified in the supplied registration data, so access often occurs via private prescription or hospital formularies.
Where PBS listings are absent, clinicians commonly discuss cost and alternative PBS‑listed hypnotics with patients before initiating therapy.
Notable Off‑Label Trends In Australian Practice
Off‑label use in Australia is limited but does occur for short‑term shift‑work sleep disruption or transient insomnia when other medicines are unsuitable.
Telehealth consultations have increased access to private prescriptions, which in turn raises the need for robust pharmacist counselling and monitoring for dependence.
Dosage Strategy
General Dosing
Patients typically ask, "What dose should I start on?"
Standard adult initiation is 1 mg at bedtime with assessment of tolerability before any increase to 2 mg or 3 mg.
The maximum recommended daily dose is 3 mg.
Elderly people and those with significant hepatic or renal impairment should start at 1 mg and be monitored carefully.
Advise taking eszopiclone only when able to allow a full night’s sleep of at least seven to eight hours.
If a dose is missed, instruct patients to skip it and not to double up.
Overdose presents with profound drowsiness, confusion and respiratory depression and requires urgent medical attention and airway support.
Condition‑Specific Dosing (PBS Recommendations)
Typical treatment courses for insomnia are short‑term, generally two to four weeks, after which treatment should be reassessed for tolerance and dependence risk.
For shift‑work or isolated single‑night insomnia, consider single‑night or very short courses and arrange documented review.
Pharmacists should check prescriptions, confirm dose (start 1 mg), counsel on adherence and liaise with prescribers if longer treatment appears necessary.
Safety Protocols
Contraindications (Australian Guidelines)
Before supply, pharmacists routinely screen for absolute and relative contraindications.
Absolute contraindications include known hypersensitivity to eszopiclone or any excipient and severe hepatic impairment due to increased toxicity risk.
Relative contraindications requiring careful review include untreated or severe sleep apnoea, significant respiratory depression, current substance use disorder and pregnancy or breastfeeding.
Older and severely debilitated patients need documented risk–benefit assessment and the lowest effective dose approach.
Adverse Effects (Post‑Market Pharmacovigilance)
Common mild adverse effects are a bitter or metallic taste, dry mouth, headache and dizziness.
More concerning moderate effects include next‑day drowsiness, confusion, memory problems and coordination issues that increase fall risk in older adults.
Post‑market surveillance (TGA and international reports) has flagged rare but serious events such as complex sleep behaviours, paradoxical agitation and respiratory depression when eszopiclone is combined with opioids or alcohol.
Dependence and tolerance risk rises with use beyond two to four weeks, so pharmacists should provide taper plans or refer for specialist review when use continues.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
One of the most frequent counselling points is the interaction with alcohol.
Alcohol markedly potentiates the central nervous system depressant effects of eszopiclone, increasing sedation, respiratory‑depression risk and the likelihood of complex sleep behaviours.
Avoid alcohol for at least 24 hours around dosing whenever possible.
Caffeine and high‑caffeine diets can blunt the therapeutic benefit by promoting wakefulness, which is especially relevant for night shift workers using hypnotics.
Large high‑fat meals may delay absorption and onset of action; advise patients to take eszopiclone on an empty stomach or after a light snack if rapid onset is required.
Drug Combinations To Avoid (TGA Safety Alerts)
Do not combine eszopiclone with other CNS depressants without specialist oversight.
Concurrent benzodiazepines, opioids, sedating antidepressants, antipsychotics and strong antihistamines substantially increase sedation and respiratory‑depression risk.
Co‑prescription with opioids is specifically highlighted in safety communications and should be avoided unless essential and closely monitored.
Strong CYP3A4 or CYP2E1 inhibitors may increase eszopiclone exposure; pharmacists should check product labelling and reconcile OTC medicines such as codeine or sedating antihistamines.
Patient Experience Analysis
Australian Survey Data
Community pharmacy surveys and telehealth feedback consistently show patients value faster sleep onset and fewer night awakenings.
Users report improved sleep continuity with eszopiclone but commonly mention a metallic taste and occasional next‑day drowsiness.
Older adults often express concern about daytime function and falls, which influences prescribers to start at 1 mg and monitor closely.
Cost and PBS eligibility strongly influence adherence, with many patients preferring PBS‑subsidised zopiclone or temazepam when available.
Forum And Pharmacy Trends
Online forums and pharmacy call data show short‑term users typically return to baseline sleep after stopping the drug, while longer‑term users frequently report tolerance and difficulty stopping.
Community pharmacists at large chains and independents routinely intercept online purchase requests, counsel on sleep hygiene, tapering and medication reconciliation.
Rural patients report access and cost barriers that drive prescribers towards PBS alternatives or non‑pharmacological care.
Distribution & Pricing Landscape
National Pharmacy Chains (Chemist Warehouse, Priceline, TerryWhite)
Availability of fulnite or eszopiclone generics in Australia is variable between chains and regions.
Major metropolitan pharmacies have broader supplier access and can source imported brands on request, whereas regional and rural outlets may substitute PBS‑listed hypnotics for cost or supply reasons.
Patients are frequently advised of private prescription costs and PBS alternatives at point of sale.
Online Pharmacy Growth And Telehealth E‑Scripts
Telehealth and online pharmacy growth has increased access to private prescriptions, including for fulnite in some cases.
In our online pharmacy, fulnite is available without a prescription, with discreet delivery to Australia in 5-14 days.
Such services increase convenience but heighten the need for robust pharmacist counselling, identity verification and screening for interactions or contraindications.
PBS Vs Private Cost Comparisons
Eszopiclone often lacks wide PBS subsidy, which means patients pay privately and may face higher out‑of‑pocket costs than for PBS‑listed zopiclone or temazepam.
Price sensitivity drives many Australians to ask for PBS alternatives, generics, or non‑drug options such as cognitive behavioural therapy for insomnia (CBT‑I).
Alternative Options
Comparison Of PBS And Non‑PBS Options
When cost or access is an issue, compare PBS‑favourable options such as zopiclone (Imovane) and temazepam with private options like eszopiclone or zolpidem.
First‑line care prioritises CBT‑I and sleep hygiene, with melatonin considered where indicated.
Non‑PBS choices are useful when patients have intolerance or inadequate response to subsidised medicines, but cost and side‑effect profiles must be discussed.
Pros And Cons Checklist
- Eszopiclone (Fulnite/Lunesta) — Pros: effective for sleep onset and maintenance, available in 1/2/3 mg; Cons: private cost, metallic taste, next‑day sedation, dependence potential.
- Zopiclone (Imovane) — Pros: more likely PBS‑subsidised and lower cost; Cons: similar dependence and residual effects to eszopiclone.
- Zolpidem — Pros: effective short‑term; Cons: limited PBS subsidy and risk of complex sleep behaviours.
- CBT‑I — Pros: durable benefit without drug adverse effects; Cons: access and cost barriers, particularly in rural areas.
Regulatory Status
TGA Approval Framework
The Therapeutic Goods Administration assesses safety, efficacy and quality before medicines are listed on the Australian Register of Therapeutic Goods (ARTG).
Sponsors lodge clinical data and risk‑management plans for TGA review; ARTG listing allows prescription marketing within Australia under Rx status.
Clinicians should confirm ARTG records for specific brands and follow any TGA safety communications and adverse event reporting pathways.
PBS Subsidy Process
The Pharmaceutical Benefits Advisory Committee evaluates cost‑effectiveness and clinical need for PBS listing and subsidy.
Many hypnotics are not broadly PBS‑subsidised, so absent subsidy patients usually pay privately for eszopiclone products.
Prescribers and pharmacists should check current PBS schedules and consider subsidised alternatives for cost‑sensitive patients.
Consolidated FAQ
Q1: Is Fulnite (eszopiclone) on the PBS?
Generally eszopiclone (Fulnite/Lunesta) is prescription‑only and often not broadly PBS‑subsidised; check the PBS schedule and discuss private cost versus PBS alternatives with your pharmacist.
Q2: How long can I take eszopiclone?
Standard guidance is short‑term use for two to four weeks; longer courses increase the risk of tolerance, dependence and adverse effects and require specialist review and taper planning.
Q3: Can I drink alcohol after taking eszopiclone?
No — alcohol increases sedation, respiratory‑depression risk and the chance of complex sleep behaviours; avoid alcohol while taking eszopiclone.
Q4: What should older people consider?
Start at the lowest dose (1 mg) and monitor for falls, cognitive impairment and next‑day drowsiness; pharmacists should reconcile other CNS depressants and advise accordingly.
Q5: Where to get help to stop?
Speak with your GP or local pharmacist for a taper plan, referral to CBT‑I or a specialist sleep clinic and for practical support to cease long‑term use safely.
Visual Guide
Clinicians and pharmacists often ask for quick reference visuals to use in counselling.
Recommended infographic 1: PBS Pricing Comparison Bar Chart.
Include common hypnotics such as eszopiclone (Fulnite), zopiclone (Imovane), zolpidem and temazepam with annotations for typical out‑of‑pocket ranges for private and concession holders.
Recommended infographic 2: National Pharmacy Distribution Map Heatmap.
Show metropolitan versus rural stock and overlays for major chains plus telehealth e‑script uptake and import bottlenecks for Fulnite.
Recommended infographic 3: Patient Flow Decision Tree.
Map clinician or pharmacist steps: assess insomnia → CBT‑I → consider short‑term hypnotic (start 1 mg) → monitor 2–4 weeks → taper or refer; include calls to action for TGA reporting and pharmacist counselling.
Design notes: use Australian palette and clear icons and include quick facts such as INN eszopiclone, strengths 1/2/3 mg and ATC N05CF04.
Storage & Transport
Household Storage Under Australian Climate
Store fulnite/eszopiclone tablets at 20–25°C, protected from moisture and direct light and keep out of reach of children.
In Australian summers, avoid storing medicines in hot bathrooms, cars or direct sunlight and advise a cool indoor cupboard instead.
For remote households without air conditioning recommend a cool shaded area or an insulated container but do not refrigerate unless the manufacturer advises.
Keep the original packaging to protect integrity and to retain batch details for any adverse event reports.
Cold‑Chain Logistics For Pharmacies
Eszopiclone does not require cold‑chain but does require controlled transport conditions at about 20–25°C.
Pharmacies should monitor storeroom temperatures, especially during long deliveries and in summer, and use climate‑controlled couriers for extended transports.
Rural pharmacies should communicate lead times to prescribers to avoid supply interruptions and document receipts and stock rotation.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Darwin | Northern Territory | 5–9 days |
| Gold Coast | Queensland | 5–7 days |
| Newcastle | New South Wales | 5–9 days |
| Wollongong | New South Wales | 5–9 days |
| Geelong | Victoria | 5–9 days |
| Townsville | Queensland | 5–9 days |
| Cairns | Queensland | 5–9 days |
| Albury | New South Wales | 5–9 days |
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
Start with the patient’s main concern: trouble falling asleep, waking overnight, or daytime tiredness.
Perform a brief structured assessment covering sleep history, comorbidities, medicines, alcohol use and PBS status.
State the starting dose clearly: 1 mg at bedtime unless the prescriber directs otherwise.
Explain expected benefits in plain language: shorter time to fall asleep and fewer awakenings, usually within a few nights.
Highlight common side effects such as metallic taste and drowsiness, and give explicit safety instructions about avoiding alcohol and driving until next‑day alertness is confirmed.
Use motivational interviewing to set short‑term goals and plan a review after two to four weeks.
For older adults, include a falls and functional check and provide a simple taper plan if treatment continues beyond recommended durations.
Document counselling and communicate any concerns with the prescriber, especially where polypharmacy or dependence is suspected.
National Health Authority Recommendations
Follow TGA labelling and adverse‑event reporting procedures and RACGP advice to prioritise non‑pharmacological care like CBT‑I.
Use the lowest effective dose for the shortest duration, typically two to four weeks, and reassess before extending therapy.
Report suspected adverse events to the TGA and coordinate care with Aboriginal health services and rural providers to ensure culturally safe and affordable options.
When switching or stopping, provide a clear tapering schedule and referral options for CBT‑I or sleep clinics to reduce the risk of withdrawal and rebound insomnia.