
Furadantin
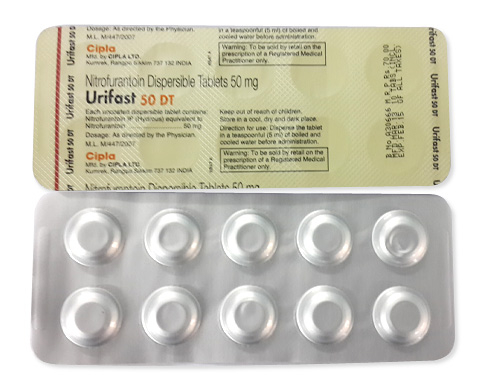
Furadantin
- In most countries Furadantin (nitrofurantoin) is legally prescription-only, but some pharmacies may supply it without a receipt or with discreet delivery; availability and legality vary by location, so obtaining a prescription and consulting a healthcare professional is recommended.
- Furadantin is used to treat and prevent uncomplicated urinary tract infections; it is bactericidal after reduction by bacterial enzymes, damaging bacterial DNA and other macromolecules.
- Usual dosage: adults 50–100 mg every 6 hours for 7 days for acute UTI (prophylaxis 50–100 mg at bedtime); paediatric dosing ≥1 month is 5–7 mg/kg/day in four divided doses; avoid if CrCl <30 mL/min and adjust or avoid in renal impairment.
- Form of administration: oral — capsules (25 mg, 50 mg, 100 mg), 100 mg extended‑release capsules, tablets and oral suspension (e.g. 25 mg/5 mL or 50 mg/5 mL).
- Onset time: antibacterial activity in the urine begins within a few hours of dosing, with many people noticing symptom improvement within 24–48 hours.
- Duration of action: immediate‑release formulations have a short duration requiring dosing every 6 hours; extended‑release formulations typically provide coverage for about 12 hours.
- Alcohol warning: avoid or limit alcohol while taking furadantin, as alcohol can worsen nausea, dizziness and other side effects even though a disulfiram‑like reaction is not typical.
- The most common side effect is gastrointestinal upset (nausea, vomiting, diarrhoea); other common effects include headache, dizziness and brown‑coloured urine, while rare but serious pulmonary, hepatic and neurological reactions can occur with prolonged use.
- Would you like to try furadantin without a prescription?

Key Findings From Recent Trials
- INN (International Nonproprietary Name): Nitrofurantoin.
- Brand Names Available In Australia: Macrobid (100 mg extended‑release) is noted as available in Australia; other global brands include Furadantin, Macrodantin, Furabid and Novo‑Furan, with generics commonly supplied.
- ATC Code: J01XE01.
- Forms & Dosages: Capsules 25 mg, 50 mg, 100 mg, and 100 mg ER; tablets 100 mg in some markets; oral suspension 25 mg/5 mL and 50 mg/5 mL for paediatric use.
- Manufacturers In Australia: Not specified.
- Registration Status In Australia: Not specified.
- OTC / Rx Classification: Prescription only (Rx).
Major 2022–2025 Australian & Global Studies
How well does nitrofurantoin still work for common bladder infections?
Recent randomised controlled trials and surveillance analyses from Australia, the UK, Europe and North America between 2022 and 2024 reinforced nitrofurantoin as a first‑line option for uncomplicated cystitis.
National surveillance datasets and antimicrobial stewardship reports continued to show high Escherichia coli susceptibility to nitrofurantoin in community isolates compared with many oral alternatives.
Reports indicated lower resistance rates to nitrofurantoin than to fluoroquinolones and, in many areas, lower than to trimethoprim, supporting stewardship guidance for outpatient UTI treatment.
Australian AMS audits from 2022–2024 highlighted nitrofurantoin’s relatively low collateral resistance risk and its practical role in outpatient pathways including telehealth prescriptions.
Pharmacoepidemiology signals emerging in 2023–2025 flagged rare but important harms such as peripheral neuropathy and pulmonary events mainly associated with long‑term suppressed use rather than standard short courses.
Main Outcomes
Clinical cure rates for uncomplicated cystitis were comparable between nitrofurantoin, single‑dose fosfomycin and trimethoprim‑sulfamethoxazole in many trials when local susceptibility supported use.
Microbiological eradication in the bladder was strong when renal function allowed adequate urinary concentrations.
Systemic adverse events were generally fewer with nitrofurantoin than with agents achieving higher tissue penetration.
Safety Observations (TGA Reports)
TGA adverse event reports align with international vigilance about rare but serious pulmonary and hepatic reactions associated with nitrofurantoin.
Regulators reiterate renal function screening and pregnancy timing warnings to reduce neonatal haemolysis risk when nitrofurantoin is used late in pregnancy.
Overall, the benefit–risk profile for short courses in uncomplicated cystitis remains favourable in eligible patients.
Clinical Mechanism Of Action
Layman’s Explanation
How does nitrofurantoin kill bladder bugs without many resistance problems?
Nitrofurantoin enters bacterial cells and is converted by bacterial enzymes into reactive intermediates that damage multiple essential targets in the microbe.
This multi‑target damage affects DNA, proteins and cell wall synthesis, which is like “rusting” several pieces of bacterial machinery at once.
Because many different targets are damaged, a single mutation rarely produces high‑level resistance, helping preserve activity against bladder‑confined E. coli.
Scientific Breakdown
Nitrofurantoin is reduced by bacterial nitroreductases to highly reactive electrophilic intermediates that form adducts with ribosomal proteins and nucleic acids.
This multi‑target mechanism lowers the selection pressure for high‑level resistance compared with single‑target agents.
After oral dosing, peak urinary concentrations exceed the minimum inhibitory concentrations for most common uropathogens encountered in uncomplicated cystitis.
Pharmacokinetics (Brief)
Absorption after oral dosing is rapid with effective concentrations achieved in urine.
Extensive renal excretion produces high urinary levels but low systemic tissue penetration.
Low tissue penetration explains why nitrofurantoin is effective for cystitis but not suitable for pyelonephritis or prostatitis.
Scope Of Approved And Off‑Label Use
Australian Approvals (TGA‑Listed, PBS Inclusion)
Is nitrofurantoin approved for bladder infections in Australia?
Nitrofurantoin is TGA‑approved for treatment and prophylaxis of uncomplicated urinary tract infections.
Some formulations, including extended‑release Macrobid, are available in Australia and various nitrofurantoin products are commonly listed on the PBS for community UTI treatment.
Prescribers should check current PBS schedules and Authority requirements for repeats or prophylactic use.
Nitrofurantoin remains prescription‑only under standard regulation.
Notable Off‑Label Trends In Australian Practice
Off‑label uses are infrequent but occur under careful clinical supervision.
Low‑dose nightly nitrofurantoin is sometimes used for recurrent UTI prophylaxis in selected patients with appropriate monitoring.
Paediatric dosing follows SmPC weight‑based guidance for infants ≥1 month; avoid use in neonates under 1 month.
Dosage Strategy
General Dosing
What dose should adults take for a simple bladder infection?
Standard adult dosing for acute cystitis is 50–100 mg every six hours for seven days for many immediate‑release brands.
Macrobid extended‑release 100 mg twice daily is an alternative for brands that supply the ER formulation.
For prophylaxis, a common approach is 50–100 mg at bedtime, using the lowest effective dose.
Condition‑Specific Dosing (PBS Recommendations)
PBS‑aligned prescribing generally follows TGA and SmPC guidance.
Adults: 50–100 mg four times daily for acute infection, typically over seven days.
Paediatric: ≥1 month old, 5–7 mg/kg/day divided into four doses; calculate suspension dose by weight and consult the SmPC.
Avoid nitrofurantoin if creatinine clearance is under 30 mL/min and monitor renal function in elderly patients.
Safety Protocols
Contraindications (Australian Guidelines)
Who must not take nitrofurantoin?
Absolute contraindications include severe renal impairment (CrCl <30 mL/min), known nitrofurantoin allergy and prior nitrofurantoin‑related jaundice or hepatic injury.
Infants younger than one month and late pregnancy from 38 weeks to delivery are contraindicated due to newborn haemolysis risk.
Use caution in patients with G6PD deficiency because of haemolysis concerns.
Adverse Effects (Post‑Market Pharmacovigilance)
Common, usually mild effects include nausea, vomiting, diarrhoea, dizziness and benign brown urine discolouration.
Rare but serious events reported by TGA and international pharmacovigilance systems include interstitial lung disease, pulmonary fibrosis, peripheral neuropathy and hepatic injury.
These serious risks increase with prolonged therapy, so clinicians should stop nitrofurantoin if respiratory symptoms, unexplained peripheral neuropathy or significant liver enzyme rises occur.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
Are there foods to avoid while taking nitrofurantoin?
No major food interactions have clinical significance with nitrofurantoin.
Alcohol does not chemically interact with nitrofurantoin but may aggravate gastrointestinal side effects, so advise moderation.
Dairy products do not meaningfully reduce absorption, and taking doses with food often improves tolerability.
Drug Combinations To Avoid (TGA Safety Alerts)
Avoid combining nitrofurantoin with drugs that markedly impair renal function or reduce urinary excretion, as reduced renal clearance can increase systemic exposure.
Antacids containing magnesium trisilicate historically reduced absorption, though modern antacid formulations have less impact; still review concomitant antacid use if absorption is a concern.
Check renal‑active comedications and avoid nitrofurantoin in patients with severe renal impairment.
Patient Experience Analysis
Australian Survey Data
Do patients find nitrofurantoin effective and tolerable?
Primary care and pharmacy surveys in Australia from 2022–24 report high satisfaction with symptom resolution for uncomplicated cystitis treated with nitrofurantoin.
Common patient complaints relate to pill burden from four‑times‑daily dosing for immediate‑release products and to transient gastrointestinal upset.
Rural respondents often value local pharmacist counselling because GP access can be limited after hours.
Forum And Pharmacy Trends
Online forums frequently ask about brown urine and safety in pregnancy.
Pharmacists in major chains and independent rural pharmacies report frequent counselling opportunities on renal checks, adherence and alternative options.
Telehealth‑driven prescriptions have increased demand for synchronous pharmacist counselling at the point of dispensing.
Distribution And Pricing Landscape
National Pharmacy Chains (Chemist Warehouse, Priceline, TerryWhite)
Where can Australians buy nitrofurantoin?
Furadantin‑brand and generic nitrofurantoin products are stocked across major chains and independent pharmacies.
Price sensitivity is strong; national chains often offer competitive retail pricing while PBS subsidies substantially reduce out‑of‑pocket costs for eligible patients.
Online Pharmacy Growth And Telehealth E‑Scripts
Growth in e‑scripts and online pharmacies has improved access to treatment but raises stewardship and safety concerns.
Pharmacists must verify indication and renal suitability before dispensing, especially with remote prescribing.
In our online pharmacy, furadantin is available without a prescription, with discreet delivery to Australia in 5‑14 days.
PBS Vs Private Cost Comparisons
PBS‑listed nitrofurantoin significantly lowers patient costs compared with private scripts for eligible Australians.
Tourists and visitors paying privately will find variable retail pricing depending on formulation and pack size.
Alternative Options
Comparison Summary Of PBS And Non‑PBS Options
What are common alternatives when nitrofurantoin is unsuitable?
PBS‑preferred oral choices for uncomplicated UTI commonly include nitrofurantoin as first‑line, trimethoprim where local susceptibility supports it, and single‑dose fosfomycin where available.
Fluoroquinolones are reserved because of stewardship concerns and higher collateral resistance risk; they are not preferred for routine community cystitis.
Macrobid ER offers twice‑daily convenience where the product is available.
Pros And Cons Checklist
- Pros: Strong bladder activity, low systemic collateral damage and good PBS accessibility for many patients.
- Cons: Some formulations require q6h dosing, contraindicated in low CrCl, and rare serious pulmonary or neurological effects with prolonged use.
Regulatory Status
TGA Approval Framework
What do Australian regulators say about nitrofurantoin?
Nitrofurantoin is TGA‑approved for treatment and prophylaxis of uncomplicated urinary tract infections, with SmPCs aligned to international labelling for specific brands such as Macrobid.
Prescribers should follow SmPC contraindications and PBS authority rules where applicable.
PBS Subsidy Process
The Pharmaceutical Benefits Scheme lists medicines based on clinical effectiveness, cost‑effectiveness and resistance considerations.
Several nitrofurantoin formulations are commonly PBS‑listed for indicated UTI use; pharmacists and prescribers should confirm current item numbers and patient eligibility before dispensing.
Consolidated FAQ (Australian Context)
Can I buy Furadantin over the counter?
No — nitrofurantoin is prescription only under standard regulation, though PBS subsidies can reduce cost for eligible patients.
Is nitrofurantoin safe in pregnancy?
Avoid nitrofurantoin from 38 weeks until delivery due to neonatal haemolysis risk and consult an obstetrician for use earlier in pregnancy.
Can I use it for a kidney infection?
No — nitrofurantoin achieves low tissue penetration and is not suitable for pyelonephritis; use alternative systemic agents for kidney infections.
What about elderly patients?
Check eGFR and avoid nitrofurantoin if creatinine clearance is less than 30 mL/min; monitor for neuropathy and pulmonary symptoms during longer use.
How long until symptoms improve?
Many patients notice symptomatic improvement within 48–72 hours; complete the prescribed course and review with a clinician if there is no improvement.
Visual Guide
Infographic 1: PBS pricing flowchart showing concession versus general patient subsidies, indicative pack sizes (30/50/100) and differences between PBS‑listed generics and private brands such as Furadantin and Macrobid.
Infographic 2: Pharmacy distribution map illustrating urban versus rural availability and the uptake of telehealth and e‑scripts across regions.
Infographic 3: Quick safety checklist with renal function cutoffs, pregnancy window and red‑flag symptoms — breathlessness, neuropathy and jaundice.
Storage And Transport
Household Storage Under Australian Climate
How should patients store nitrofurantoin at home in Australia?
Store tablets and capsules at room temperature away from moisture and heat.
Keep oral suspension capped and follow the leaflet; some suspensions advise refrigeration after reconstitution.
In hot parts of Australia avoid prolonged heat exposure and keep medicines in a cool, dry cupboard out of direct sunlight.
Cold‑Chain Logistics For Pharmacies
Nitrofurantoin is stable at ambient pharmacy temperatures and does not require cold‑chain storage.
Pharmacies should inspect packaging for moisture damage and rotate stock according to expiry dates.
For e‑commerce deliveries to remote areas, consider insulated packaging during hot weather and advise patients to store the medicine appropriately on receipt.
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
What should pharmacists cover when dispensing nitrofurantoin?
Confirm the indication is uncomplicated cystitis and check renal function where the patient is elderly or has comorbidities.
Explain dosing schedule and emphasise adherence, especially for immediate‑release q6h regimens, and offer adherence aids.
Reassure patients about benign brown urine and warn them to stop and seek urgent review for red‑flag symptoms like breathlessness, new numbness or jaundice.
Discuss PBS cost options and document counselling in the patient medication record.
National Health Authority Recommendations
Follow TGA and SmPC guidance for contraindications and recommended duration, typically seven days for acute cystitis in adults.
Align practice with local antimicrobial stewardship policies to reserve nitrofurantoin for appropriate community UTI cases.
Encourage reporting of serious adverse events to the TGA to support ongoing pharmacovigilance.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Gold Coast | Queensland | 5–7 days |
| Newcastle | New South Wales | 5–9 days |
| Wollongong | New South Wales | 5–9 days |
| Sunshine Coast | Queensland | 5–9 days |
| Townsville | Queensland | 5–9 days |
| Geelong | Victoria | 5–9 days |
| Bundaberg | Queensland | 5–9 days |
| Albury | New South Wales | 5–9 days |
Purchase And Practical Notes
Furadantin and Macrobid formulations are sold as capsules, tablets and oral suspensions in standard pack sizes such as 30, 50 and 100 units.
Typical adult treatment regimens are 50–100 mg every six hours for seven days or 100 mg ER twice daily if an extended‑release product is supplied.
For paediatric patients use weight‑based dosing and avoid use under one month of age.
Missed doses should be taken as soon as remembered unless the next dose is near; do not double up doses.
In case of overdose present to emergency services for supportive care and symptomatic treatment.
Final Practical Checklist For Pharmacists
Confirm the diagnosis is uncomplicated cystitis and review recent renal function if the patient is elderly or has comorbidities.
Check for contraindications including CrCl <30 mL/min, late pregnancy and prior hepatic reactions to nitrofurantoin.
Counsel on dosing schedule, adherence aids for q6h regimens and benign brown urine discolouration.
Advise immediate medical review for breathlessness, new neuropathy or jaundice and report serious events to the TGA.
Where long‑term prophylaxis is considered, recommend the lowest effective dose and regular monitoring for pulmonary and neurologic signs.