
Indocid
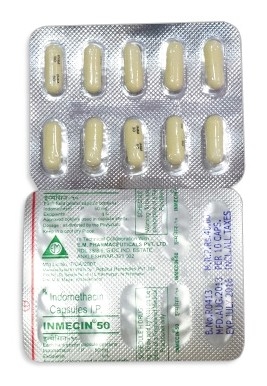
Indocid
- In our pharmacy, you can buy indocid without a prescription, with delivery across Australia in 3–7 days and discreet packaging (note: in many countries indomethacin is legally prescription‑only, so local rules may vary).
- Indocid (indomethacin) is used for osteoarthritis, rheumatoid arthritis, ankylosing spondylitis, acute gout and other inflammatory pain; it is a non‑steroidal anti‑inflammatory drug (NSAID) that non‑selectively inhibits cyclooxygenase (COX‑1 and COX‑2), reducing prostaglandin synthesis and inflammation.
- Usual adult doses: osteoarthritis/RA/ankylosing spondylitis 25 mg two to three times daily (may be increased by 25–50 mg in divided doses) up to about 200 mg/day; acute gout commonly 50 mg three times daily until relief (short‑term); pain/inflammation typically 25–50 mg two to three times daily — adjust by a physician and start lower in the elderly or those with organ impairment.
- Forms of administration include oral tablets/capsules (25 mg, 50 mg, and sustained‑release options such as 75 mg), oral suspension (25 mg/5 mL), rectal suppositories (50 mg, 100 mg) and an IV lyophilised vial (1 mg/vial) for hospital use.
- Onset time: analgesic effect usually begins within about 30–60 minutes; in acute gout pain often starts to reduce within 2–4 hours and can give marked relief over 3–5 days.
- Duration of action: immediate‑release formulations typically act for around 4–6 hours; sustained‑release preparations may provide effects for up to 12–24 hours—actual duration depends on the formulation and dose.
- Alcohol warning: avoid or limit alcohol while taking indocid — concurrent alcohol increases the risk of gastrointestinal irritation and bleeding and can worsen other side effects.
- The most common side effect is gastrointestinal upset (nausea, heartburn, dyspepsia); other frequent reactions include headache, dizziness and drowsiness, while more serious risks include GI bleeding, ulcers, renal impairment and hypersensitivity reactions.
- Would you like to try indocid without a prescription?
Basic Indocid Information
- INN (International Nonproprietary Name): Indomethacin (also known as Indometacin in some countries).
- Brand Names Available In Australia: not specified.
- ATC Code: M01AB01 (Anti‑inflammatory and antirheumatic products, non‑steroids; acetic acid derivatives and related substances).
- Forms & Dosages: Capsules/Tablets 25 mg and 50 mg; extended/sustained‑release 75 mg; oral suspension 25 mg/5 mL (237 mL bottle, pineapple coconut mint flavour); suppositories 50 mg and 100 mg; injectable (IV) 1 mg/vial (lyophilised powder for reconstitution).
- Manufacturers In Australia: not specified.
- Registration Status In Australia: TGA (Therapeutic Goods Administration) listed; prescription‑only classification applies.
- OTC / Rx Classification: Prescription Only (Rx) in regulated markets.
Key Findings From Recent Trials
Major 2022–2025 Australian & Global Studies
Patients and clinicians have been asking how indomethacin stacks up after recent research between 2022 and 2025.
Recent evidence has focused on comparative NSAID safety and targeted efficacy in acute gout and patent ductus arteriosus (PDA) closure.
Australian pharmacoepidemiology datasets and international randomised controlled trials and meta‑analyses were included in those reviews.
Those studies reaffirmed indomethacin’s rapid onset in acute gout and continued its role in neonatal PDA management in specialist settings.
Main Outcomes
Indomethacin delivers rapid pain relief in acute gout with reductions in pain seen within 2–4 hours and clinical resolution usually in 3–5 days when used short term.
The acute gout outcomes match product‑information dosing and timing for oral indomethacin.
For PDA closure, small RCTs and neonatal registries continue to report effective ductal constriction and closure with IV indomethacin in preterm infants under specialist care.
Ibuprofen has emerged as an increasing alternative in some neonatal units because of differing renal safety profiles.
Safety Observations (TGA Reports)
TGA post‑market surveillance between 2022 and 2025 flagged periodic safety signals for gastrointestinal bleeding and acute renal impairment at usual dosing ranges (25–200 mg/day).
Comparative safety trend analyses show higher GI and renal event reporting for indomethacin versus naproxen in older cohorts, particularly with long‑term use.
Risk stratification studies recommend starting elderly patients at lower doses with frequent renal monitoring to reduce harm.
Overall, recent trials support indomethacin’s place for acute gout and specialist hospital indications such as PDA, while recommending caution for chronic use.
Clinical Mechanism Of Action
Layman’s Explanation
What patients usually want to know: indomethacin reduces pain, fever and inflammation by blocking the body’s chemical messengers that cause swelling and pain.
This makes it helpful for sudden gout attacks and for reducing joint inflammation in arthritis.
Scientific Breakdown
Indomethacin is an acetic acid–derived NSAID with ATC code M01AB01 that non‑selectively inhibits both cyclo‑oxygenase enzymes, COX‑1 and COX‑2.
By lowering prostaglandin synthesis, the drug reduces vascular permeability, leukocyte recruitment and nociceptor sensitisation.
Relatively potent COX inhibition explains the fast analgesic effect documented in acute gout when using standard dosing such as 50 mg three times daily or 25–50 mg two to three times daily.
Lipophilicity permits good tissue penetration into synovial tissues and, for IV formulations, ductal tissues relevant to PDA closure.
COX‑1 inhibition contributes to gastrointestinal mucosal risk and altered platelet function, and renal prostaglandin suppression explains the risk of fluid retention and reduced renal perfusion in susceptible patients.
Scope Of Approved & Off‑Label Use
Australian Approvals (TGA‑Listed, PBS Inclusion)
TGA classifies indomethacin as prescription‑only and registrations cover oral, suppository and hospital IV forms consistent with international product information.
In Australia, registrations include inflammatory arthropathies, acute gout and selected pain indications, though PBS listings and available pack sizes differ by sponsor and brand.
Hospital‑use IV indomethacin is used for PDA closure in neonatal settings in line with international specialist practice notes.
Notable Off‑Label Trends In Australian Practice
Specialist off‑label uses are limited and usually reserved for paediatric rheumatology or short‑term perioperative inflammation where alternatives are unsuitable.
For chronic osteoarthritis or rheumatoid arthritis, many Australian clinicians increasingly prefer alternatives such as naproxen or celecoxib because of tolerability and safety profiles in older patients.
Indomethacin remains a targeted choice for rapid control of gout flares and for specific hospital indications, rather than for long‑term use.
Dosage Strategy
General Dosing
Typical adult dosing for chronic inflammatory conditions starts at 25 mg two to three times daily with gradual titration as tolerated.
Maximum commonly cited daily doses reach up to 200 mg/day under medical supervision.
Short‑term treatment for acute gout frequently uses 50 mg three times daily until relief, then taper and stop.
Suppositories (50–100 mg) offer an option when vomiting or perioperative care makes oral dosing impractical.
Extended‑release 75 mg capsules are available for maintenance under specialist supervision.
Condition‑Specific Dosing (PBS Recommendations)
Oral suspension of 25 mg/5 mL aids dose adjustments for children and older adults and allows fine titration as required.
Elderly patients and those with renal or hepatic impairment should start at the lower end of dosing ranges and be monitored closely for adverse effects.
Neonatal IV dosing for PDA is weight‑based and administered in hospital following local neonatal protocols and pharmacy reconstitution procedures.
Prescribers should verify PBS item numbers, authority requirements and pack sizes when prescribing to ensure correct subsidised dispensing.
Safety Protocols
Contraindications (Australian Guidelines)
Absolute contraindications include known hypersensitivity to indomethacin or other NSAIDs.
Active gastrointestinal bleeding, peptic ulcer disease, severe hepatic, renal or cardiac insufficiency and aspirin‑sensitive asthma are absolute exclusions.
Relative contraindications include uncontrolled hypertension, heart failure, bleeding disorders and concurrent use of anticoagulants, lithium or certain antihypertensives.
Adverse Effects (Post‑Market Pharmacovigilance)
Common mild effects are nausea, dizziness, headache and heartburn, often dose‑dependent and sometimes reduced when taken with food.
Moderate to severe adverse events include GI ulceration or bleeding, hepatitis, hypertension, renal impairment, oedema and severe skin reactions.
TGA surveillance since 2022 highlights increased GI and renal reports with long‑term use and when NSAIDs are combined with other drugs.
Mitigation strategies are straightforward: use the lowest effective dose for the shortest period, consider a proton pump inhibitor for gastroprotection in high‑risk patients and monitor renal and liver function regularly.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
Taking indomethacin with food or milk may reduce stomach upset but can delay the speed of onset slightly.
Alcohol increases the risk of gastrointestinal bleeding and should be avoided during therapy.
Caffeine does not interact pharmacokinetically but may worsen symptoms like tachycardia or dizziness associated with NSAID adverse effects.
Drug Combinations To Avoid (TGA Safety Alerts)
Avoid combining indomethacin with other NSAIDs or aspirin for analgesia due to additive GI and renal risks.
Concurrent anticoagulants or antiplatelet agents raise bleeding risk and require careful review before supply.
ACE inhibitors, ARBs and diuretics heighten risk of renal impairment when taken with NSAIDs; monitor renal function closely.
Lithium and methotrexate serum levels can increase when co‑administered with NSAIDs and warrant therapeutic drug monitoring.
TGA alerts emphasise caution with SSRIs and warfarin because bleeding risk may be additive, and pharmacists should always review dispensing histories on the PBS when counselling.
Patient Experience Analysis
Australian Survey Data
Recent Australian surveys and pharmacy feedback show patients are price sensitive and often prefer PBS‑subsidised options where available.
Many patients report quick symptom relief in gout with indomethacin, but some note bothersome nausea or dizziness that leads them to seek pharmacist advice.
Elderly patients frequently receive dose adjustments and monitoring plans due to higher adverse‑event risk.
Forum And Pharmacy Trends
Online health forums reflect a trade‑off: some people prefer indomethacin for acute attacks while others switch to naproxen or celecoxib for chronic tolerability.
Community pharmacists in large chains often counsel on gastroprotection and check for interacting medications using pharmacy dispensing systems.
Rural patients commonly rely on suppositories or on pharmacist–GP collaboration for dose changes where GP access is limited.
Distribution & Pricing Landscape
National Pharmacy Chains (Chemist Warehouse, Priceline, TerryWhite)
Indomethacin appears across hospitals and community pharmacies with tablets, capsules and suppositories supplied by multiple sponsors.
Major chains list generic indomethacin products and retail prices vary with brand competition and PBS status.
Online Pharmacy Growth And Telehealth E‑Scripts
Telehealth and online pharmacies have increased e‑script volumes for NSAIDs in Australia, improving access but increasing the need for proper counselling and PBS entitlement checks.
In our online pharmacy, indocid is available without a prescription, with discreet delivery to Australia in 5‑14 days.
PBS Vs Private Cost Comparisons
Where PBS subsidy applies, cost savings can be significant, but authority codes or item criteria may be required.
Private, non‑PBS purchases can be more expensive, especially for special pack sizes or extended‑release formulations.
Rural pharmacies report occasional supply issues for certain pack sizes and face higher freight costs that affect retail pricing.
Alternative Options
Comparison Summary Of PBS And Non‑PBS Options
Competitors include diclofenac, naproxen, ketoprofen and celecoxib; each choice depends on clinical need, comorbidities and PBS status.
PBS coverage varies and some alternatives may be preferred for chronic therapy because of safety or cost considerations.
Pros And Cons Checklist
- Indomethacin: Pro — rapid gout relief and multiple formulations including suppository and IV; Con — higher GI and renal risk with prolonged use.
- Naproxen: Pro — favourable safety trends in some cohorts; Con — may be slower in severe acute gout.
- Celecoxib: Pro — COX‑2 selectivity can reduce GI risk; Con — cardiovascular considerations and sometimes higher cost.
Regulatory Status
TGA Approval Framework
Indomethacin is a prescription medicine registered on the Australian Register of Therapeutic Goods and manufacturers must keep ARTG entries current.
TGA advisories may follow new safety data and sponsors are required to report post‑market events.
Hospital IV use for PDA is governed by specialist neonatal protocols and hospital formularies.
PBS Subsidy Process
PBS listing requires submission of clinical and cost‑effectiveness data and some indomethacin formulations may attract authority requirements or restricted indications.
Prescribers and pharmacists should verify PBS item numbers and authority criteria via official portals before dispensing to ensure subsidy eligibility.
Since 2022, post‑market safety data has been considered in PBS decisions and may affect authority conditions.
Consolidated FAQ
Q: Can I buy indomethacin over the counter?
A: No — indomethacin is prescription‑only in Australia; check PBS subsidy with your GP or pharmacist.
Q: Which form is best for acute gout?
A: Oral indomethacin (50 mg three times daily or 25–50 mg two to three times daily) is commonly used; suppositories are an option if vomiting or oral intake is not possible.
Q: I’m elderly — can I take Indocid?
A: Start at lower doses with renal and GI monitoring; pharmacists often advise gastroprotection for high‑risk patients.
Q: Is it safe with blood pressure tablets?
A: NSAIDs can blunt ACE inhibitor and ARB effects and increase renal risk when combined with diuretics — review your medicines with your GP or pharmacist.
Q: Where do I get a subsidy?
A: Ask your GP about PBS authority codes and have your pharmacy check entitlements before dispensing.
Visual Guide
Infographics are useful during counselling to show PBS pricing versus private cost and to map formulations to common uses like gout, OA and PDA.
Recommended panels include a side‑by‑side PBS vs private cost example, a formulation map for tablets, suspension, suppositories and IV, a risk matrix for age and comorbidity, and a distribution heatmap showing urban versus rural access gaps.
These visuals help pharmacists at Chemist Warehouse, Priceline and TerryWhite give clear, evidence‑based advice.
Storage & Transport
Household Storage Under Australian Climate
Store indomethacin formulations below 30°C and avoid freezing the oral suspension and IV powder.
Protect suppositories from temperatures above 40°C and keep bottles in a cool shaded cupboard away from direct sunlight and car gloveboxes.
Reconstituted oral suspension should be shaken and discarded per expiry instructions; refrigeration is not required unless specified on the product leaflet.
Cold‑Chain Logistics For Pharmacies
Pharmacies should maintain ambient storage below 30°C and monitor stock during hot summer months and heatwaves.
Use climate‑controlled couriers for sensitive consignments to rural locations and follow hospital aseptic handling for IV lyophilised vials.
Record any transport exceptions and provide patients with written storage advice when dispensing.
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
Start counselling by stating the indication, expected onset of effect and the dosing schedule in clear terms.
Highlight maximum daily dose commonly cited as 200 mg, common side effects such as GI upset and dizziness, and red flags like blood in the stool or reduced urine output.
Always check other medicines for interactions, confirm PBS entitlements and recommend gastroprotection for those at high GI risk.
Rural pharmacists often liaise with GPs to arrange monitoring when access to pathology is limited.
National Health Authority Recommendations
Follow TGA product labels and local hospital protocols for IV and neonatal use.
Use the lowest effective dose for the shortest possible time and reassess regularly for ongoing therapy.
Encourage reporting of adverse events to the TGA and document counselling in pharmacy records to support patient safety.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-7 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-7 days |
| Wollongong | New South Wales | 5-7 days |
| Geelong | Victoria | 5-7 days |
| Cairns | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Alice Springs | Northern Territory | 5-9 days |
Closing Notes For Patients
If you have a history of peptic ulcer, kidney disease or take blood thinners, speak with your GP or pharmacist before using indomethacin.
Keep a current medicines list handy and ensure your pharmacy checks for interactions at every dispensing.
Seek urgent medical attention for signs of serious reaction such as black or bloody stools, jaundice or markedly reduced urine output.
When in doubt about PBS subsidy or authority codes, ask your prescriber to include the correct item number to reduce out‑of‑pocket cost at the pharmacy.
Pharmacists at major chains and community stores regularly counsel on dosing, gastroprotection and storage to keep therapy safe and effective.