
Medroxyprogesterone
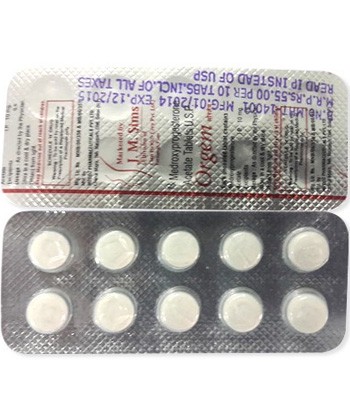
Medroxyprogesterone
- Medroxyprogesterone can be purchased through pharmacies in Australia and many other countries, usually as a prescription-only medicine (S4 in Australia). However, some online pharmacies may offer it without a prescription; use caution and follow local regulations.
- Medroxyprogesterone is used for contraception, menstrual and uterine bleeding problems, endometriosis, secondary amenorrhoea, and certain hormone-sensitive cancers. It is a progestogen that works by mimicking progesterone, suppressing ovulation, thinning the endometrium, and altering cervical mucus to reduce the chance of pregnancy.
- The usual dose depends on the indication: 150 mg by intramuscular injection every 12–13 weeks for contraception, 104 mg by subcutaneous injection every 12–13 weeks, or 5–10 mg orally daily for 5–10 days for some gynaecological conditions. Cancer treatment doses are higher and individually adjusted by a doctor.
- The form of administration is an oral tablet, intramuscular injection, or subcutaneous injection.
- It does not work immediately for all uses. When used for contraception, protection is generally maintained after the injection is given as directed; for oral treatment of bleeding or endometriosis, improvement is often seen within a few days of starting the course.
- The duration of action is long for injectable forms, usually about 12–13 weeks per dose. Oral courses act for the prescribed treatment period, typically 5–10 days per cycle, depending on the condition.
- Alcohol is not known to cause a major direct interaction, but drinking may worsen dizziness, mood changes, or stomach upset. It is best to limit alcohol, especially if you feel unwell.
- The most common side effects are menstrual changes or amenorrhoea, weight gain, headache, abdominal bloating or pain, dizziness, mood changes, acne, hair loss, and reduced libido.
- Would you like to try medroxyprogesterone without a prescription?

Basic Medroxyprogesterone Information
- INN (International Nonproprietary Name): Medroxyprogesterone
- Brand names available in Australia: Provera tablets, Depo-Provera injection
- ATC code: G03AC06, L02AB02, G03DA02
- Forms & dosages: Oral tablets 2.5 mg, 5 mg, 10 mg; IM suspension 150 mg/mL; SC injection 104 mg/0.65 mL
- Manufacturers in Australia: Pfizer; local generic supply may vary
- Registration status in Australia: Prescription medicine, subject to TGA registration and local supply
- OTC / Rx classification: Prescription Only (S4)
Recent Trial Findings And What They Mean
Thinking about how well medroxyprogesterone actually works, and whether the side effects are as common as people say?
Recent evidence from 2022 to 2025 has continued to support medroxyprogesterone as a reliable progestogen for contraception and selected gynaecological problems.
For contraception, both Depo-Provera 150 mg/mL IM every 3 months and Depo-SubQ Provera 104 remain highly effective, with low user-dependent failure because there is no daily pill-taking to get wrong.
That matters in Australian contraception evidence, especially for people who want something simple and low maintenance.
Studies and post-market reviews have kept the focus on continuation, bleeding patterns, bone health and mood effects, because those are the issues patients notice most in real life.
Bleeding changes remain common early on, and amenorrhoea often develops with ongoing use, which some patients welcome and others find unsettling.
Long-term DMPA safety has also stayed under the microscope, particularly around bone mineral density loss in higher-risk patients and the need for follow-up if use continues for years.
For oral Provera 2.5 mg, Provera 5 mg and Provera 10 mg, the evidence base still supports its use for abnormal uterine bleeding, secondary amenorrhoea and endometriosis symptom control when prescribed appropriately.
Australian pharmacovigilance continues to reflect the same practical warnings seen globally: mood changes, weight gain, irregular bleeding and bone density concerns need to be discussed before treatment and monitored over time.
How Medroxyprogesterone Works
Ever wondered why a single injection can prevent pregnancy for months at a time?
Medroxyprogesterone acetate is a synthetic progestogen that thickens cervical mucus, suppresses ovulation and stabilises the endometrium.
In plain terms, it makes it harder for sperm to get through, stops an egg from being released, and helps the lining of the uterus behave more predictably.
In ATC terms, it sits under G03AC06 for systemic progestogens and L02AB02 for endocrine therapy in cancer.
That distinction matters because contraceptive doses and oncology doses are not used for the same purpose or at the same intensity.
At higher doses in selected hormone-responsive cancers, medroxyprogesterone may reduce gonadotrophin-driven tumour growth, which is why it appears in palliative and specialist regimens.
Route-Specific Pharmacology
The IM 150 mg/mL and SC 104 mg/0.65 mL formulations are long-acting depot products that release medicine slowly over time.
Oral tablets work more quickly, but they rely on day-to-day adherence, which is why Provera tablets are used differently from the injection.
Approved And Off-Label Use In Australia
Want to know whether this medicine is actually approved here, or whether it is something doctors only use in special cases?
In Australia, medroxyprogesterone is prescription only and access depends on TGA registration and PBS subsidy status for the relevant indication.
The main local products are Provera tablets and Depo-Provera injection where stocked.
Common approved indications include contraception, secondary amenorrhoea, abnormal uterine bleeding, endometriosis symptoms and selected cancer indications.
Specialist-prescribed regimens can also be used for menstrual suppression, perimenopause symptom management and other hormonal plans, but these need clinician oversight rather than trial-and-error use.
That is especially important because supply can vary between urban chain pharmacies and rural areas, where stock delays are more common.
In our online pharmacy, medroxyprogesterone is available without a prescription, with discreet delivery to Australia in 5-14 days, which can help patients who are waiting on local supply or using telehealth follow-up.
Even so, the medicine itself remains a prescription medicine in Australian clinical practice, so it should be used with proper medical guidance.
Dosage Strategy And Missed Dose Rules
People often ask if the injection timing is strict, and the short answer is yes.
The usual contraception schedule is 150 mg IM every 3 months or 104 mg SC every 3 months.
For oral cycle-based use, the common pattern is 5–10 mg daily for 5–10 days, often timed within the menstrual cycle as prescribed.
For contraception, injections should not drift far beyond about 12 to 13 weeks.
If more than 14 weeks have passed, pregnancy should be assessed and backup contraception is needed.
Form-Specific Administration
The IM suspension is given as a deep injection from a single-use vial or pre-filled syringe.
The SC prefilled syringe is often easier for self-administration when that has been prescribed and taught properly.
Tablets are simpler to dispense and store, but they only work well when taken exactly as directed.
Condition-specific dosing should be individualised for endometriosis, uterine bleeding, secondary amenorrhoea and cancer regimens.
For endometrial or renal carcinoma, specialist dosing may be 200–400 mg IM weekly, with the exact plan adjusted to the patient.
Safety Checks And Adverse Effects
Before starting medroxyprogesterone, what conditions make it unsafe?
The main contraindications are pregnancy, active thromboembolic disease, unexplained vaginal bleeding, known or suspected breast or genital cancer, severe liver disease and hypersensitivity to the medicine or its excipients.
People with depression history, diabetes, hypertension, migraine, hyperlipidaemia or osteoporosis risk need closer monitoring.
That is especially important with long-term DMPA use, where bone health becomes part of the conversation rather than an afterthought.
Common side effects include amenorrhoea, irregular bleeding, weight gain, headache, bloating, dizziness, mood changes, acne, hair loss and reduced libido.
These are not rare “internet stories”; they are the same post-market effects pharmacists hear about at the counter every week.
Long-term bone density concerns are why pharmacists should often mention calcium and vitamin D discussion, especially when the patient already has low bone mass risk.
If mood changes become significant, or bleeding is heavy or persistent, review is needed rather than simply waiting it out.
Interactions And Co-Medication Checks
Are there food rules, alcohol limits or coffee restrictions with medroxyprogesterone?
There are no major food interactions, and coffee or everyday diet are not direct interaction problems.
Alcohol can still make dizziness or mood symptoms feel worse, so that is worth mentioning during counselling.
Weight-control concerns also come up often, especially for patients who notice the scales creeping up after starting the injection.
The more important checks are drug interactions and co-medications that may affect liver metabolism or complicate bleeding assessment.
Pharmacists should review all hormonal therapy, including combined packs such as Prempro or Premphase where relevant, and any medicines that may alter clot risk or bleeding symptoms.
When the picture is unclear, it is better to pause and check the full medication list than to assume a symptom is “just the injection”.
What Patients Say About It In Australia
Why do some patients love quarterly injections while others stop after the first few months?
Australian patient experience tends to split into two broad groups.
Some appreciate the convenience of not thinking about contraception every day, while others struggle with bleeding changes, weight gain and mood effects.
Price sensitivity matters too, and PBS reliance strongly influences whether patients stay on treatment long term.
Rural patients may have fewer appointment slots, delayed stock and longer travel for repeat injections, which can make a simple treatment feel harder than it should.
Urban patients usually have more pharmacy choice, but they still ask the same questions about delayed periods, fertility return and whether the injection “wears off” on time.
That is where pharmacists in Chemist Warehouse, Priceline and TerryWhite-style settings often do the heavy lifting: calming anxiety, explaining timelines and checking whether a review is needed.
Distribution And Pricing In The Australian Market
Where can patients actually get medroxyprogesterone, and what will it cost?
Stock access varies by state, suburb and pharmacy banner group, so a medicine that is easy to find in one area may be harder to source in another.
Tablets such as Provera 2.5 mg, 5 mg and 10 mg are usually simpler to dispense than injectable depot products, which may need ordering or clinic coordination.
National chains such as Chemist Warehouse, Priceline and TerryWhite can differ in local availability depending on demand and supplier stock.
Online pharmacy growth and e-prescribing have improved access, but injectables still often need in-person administration or local pharmacist coordination.
PBS pricing can substantially reduce out-of-pocket cost, while private pricing varies widely between products and suppliers.
That private-versus-PBS comparison is especially important for long-term contraception, where small monthly differences add up over time.
Patients often ring on a Friday afternoon asking whether a depot injection can be sourced before Monday, and the answer depends on local stock plus prescription status.
How It Compares With Other Options
Wondering whether Depo-Provera is the best fit, or whether another progestogen would be easier to live with?
Alternatives include norethisterone, levonorgestrel, desogestrel, dienogest and combined estrogen/progestin contraceptives.
These come in different routes, including oral tablets, implants, rings, patches and long-acting devices.
Medroxyprogesterone is often chosen for convenience and low-maintenance contraception, while oral options give more day-to-day control and quicker stopping if side effects occur.
The trade-off is that oral medicines depend on adherence, which can be a problem if routines are unpredictable.
DMPA is convenient and long-acting, but amenorrhoea and bone health concerns need more discussion than with some alternatives.
It is also less ideal for people who are already worried about mood sensitivity or have a strong osteoporosis risk.
For endometriosis, dienogest or other options may be discussed by a specialist depending on symptom pattern and prior treatment response.
Regulatory Status And Australian Compliance
Is this medicine actually regulated the same way as other prescription hormones in Australia?
Yes.
Medroxyprogesterone is prescription only in Australia and is regulated through TGA listings and local product information.
The INN is medroxyprogesterone, with brand names such as Provera and Depo-Provera used internationally and in Australian contexts where supplied.
PBS subsidy depends on the indication and item status, so some uses may be subsidised while others are private.
That is why a pharmacy can have one patient on a subsidised supply while another is comparing private pricing for the same medicine.
Local supply can change, so registry and brand availability checks still matter before promising a specific product.
Common Questions From Patients
How long does Depo-Provera last?
About 12 to 13 weeks.
Can medroxyprogesterone stop periods?
Yes, amenorrhoea is common.
Does it affect fertility?
Fertility usually returns after stopping, but the timing varies from person to person.
What if an injection is missed?
Get it as soon as possible, and if more than 14 weeks have passed, use backup contraception.
Is it available in Australia?
Yes, subject to Australian registration and local supply.
Visual Guide For Patients And Carers
Simple visuals make this medicine easier to use correctly, especially when patients are juggling timing, side effects and follow-up appointments.
An injection timetable is helpful for quarterly dosing, and a PBS versus private cost chart can help patients plan ahead.
A pharmacy access map showing metro and regional areas can also explain why supply feels easier in some postcodes than others.
Provera tablets versus Depo-Provera injection works well as a side-by-side comparison for counselling.
Colour-coding side effects, missed-dose steps and storage rules keeps the information practical rather than overwhelming.
Good patient education should answer the questions people are already asking, not just the questions clinicians think they should ask.
Delivery Across Australia
| City | Region | Delivery time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-7 days |
| Gold Coast | Queensland | 5-9 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Ballarat | Victoria | 5-9 days |
Storage And Transport
Storing medroxyprogesterone properly matters more than people realise, especially in Australian heat.
Keep it at 15–25°C and protect it from light and freezing.
Never leave packs in a hot car or near a sunny window for long periods.
If the suspension looks clumped or discoloured, it should not be used.
Although it is not usually a cold-chain medicine, pharmacies still need solid stock handling discipline, particularly in regional Australia where transport delays can happen.
That applies to both the injection and the tablets.
How Pharmacists Should Counsel Patients
The best counselling is practical, respectful and specific to the person in front of you.
Explain the injection timetable clearly, including what to do if a dose is late.
Talk through bleeding changes, mood monitoring and the reasons to seek medical review rather than quietly stopping treatment.
Check pregnancy status, clot risk, liver disease, depression history and bone-health history before the medicine is used.
Remind patients that medroxyprogesterone tablets and injections are prescription-only and are not suitable for unsupervised use.
Pharmacists also play a useful role in PBS navigation, rural supply coordination and referral to GPs or women’s health clinicians when treatment needs adjusting.
That support can make the difference between a treatment that is abandoned and one that fits real life.