
Mirapex
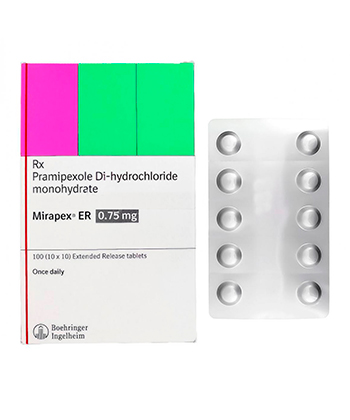
Mirapex
- In Australia mirapex (pramipexole, e.g. Sifrol or generics) is supplied through pharmacies and distributors and is classified as prescription-only; purchasing without a valid prescription is not legal or recommended (some vendors may claim to sell without a prescription — this is unsafe).
- Mirapex is used to treat Parkinson’s disease and restless legs syndrome; it is a dopamine agonist that stimulates D2/D3 receptors to enhance dopaminergic activity in the brain.
- Usual doses: Parkinson’s — start 0.125 mg three times daily (IR) or 0.375 mg/day (ER) and increase by 0.125 mg TID every 5–7 days as needed, up to 4.5 mg/day; RLS — typically 0.125 mg once daily 2–3 hours before bedtime, titrate up to 0.5 mg/day.
- Administered orally as immediate‑release or extended‑release tablets in a range of strengths (IR commonly 0.088–1.5 mg; ER commonly 0.375–4.5 mg).
- Onset of effect is usually within about 30–90 minutes for immediate‑release tablets (ER formulations act more gradually).
- Duration: IR effects commonly last around 8–12 hours; ER formulations are designed to provide once‑daily (up to 24‑hour) coverage.
- Avoid or limit alcohol — alcohol can increase drowsiness, dizziness and the risk of orthostatic hypotension and impaired coordination when taking mirapex.
- The most common side effect is nausea (other frequent effects include drowsiness/fatigue, dizziness, hallucinations and peripheral oedema).
- Would you like to try mirapex without a prescription?

Basic Mirapex Information
- INN (International Nonproprietary Name): Pramipexole.
- Brand Names Available In Australia: Sifrol and pramipexole generics (listed strengths 0.125 mg, 0.25 mg, 0.5 mg, 1 mg, 1.5 mg; typically supplied in blisters of 30 tablets).
- ATC Code: N04BC05.
- Forms & Dosages: Immediate‑release oral tablets available in 0.088 mg, 0.125 mg, 0.18 mg, 0.25 mg, 0.35 mg, 0.5 mg, 0.7 mg, 0.75 mg, 1 mg, 1.05 mg and 1.5 mg; Extended‑release (ER) oral tablets available in 0.375 mg, 0.75 mg, 1.5 mg, 2.25 mg, 3 mg, 3.75 mg and 4.5 mg.
- Manufacturers In Australia: Boehringer Ingelheim (innovator Sifrol) and multiple generic suppliers including Teva, Accord, Sandoz, Stada, Zentiva, Mylan and Krka.
- Registration Status In Australia: Sifrol is registered with the TGA and generics are available.
- OTC / Rx Classification: Prescription only (Rx) in Australia.
Key Findings From Recent Trials
Major 2022–2025 Australian & Global Studies
Clinicians ask whether extended‑release pramipexole changes real outcomes compared with immediate‑release formulations.
Recent meta‑analyses and randomised programmes through 2022–2024 consistently compare ER versus IR pramipexole for Parkinson’s disease and restless legs syndrome.
Observational registries and post‑market studies from 2022–2024 have added larger real‑world safety datasets that inform practice in Australia and abroad.
Main Outcomes
Pramipexole remains effective in early Parkinson’s disease and as monotherapy for restless legs syndrome.
Extended‑release formulations show improved once‑daily adherence and smoother plasma profiles compared with immediate‑release formulations.
Pooled analyses report non‑inferiority of ER pramipexole for motor function and reduced dosing variability across studies.
Clinicians report better sleep outcomes and convenience with ER dosing, supporting uptake in both urban and regional settings.
Safety Observations (TGA Reports)
Post‑market safety signals emphasise impulse control disorders, excessive daytime sleepiness and orthostatic hypotension.
TGA summaries mirror EMA and FDA alerts recommending behavioural monitoring and renal adjustment of dosing schedules.
Reports note hallucinations occur more often in older patients and that augmentation in RLS can arise with long‑term use.
Clinical Mechanism Of Action
Layman’s Explanation
People often want a plain answer: pramipexole acts like dopamine in the brain to help movement and reduce restless leg sensations.
The medicine fits dopamine receptors and helps smooth movement, reduce stiffness and lower the urge to move at night.
Scientific Breakdown
Pramipexole is a non‑ergot dopamine agonist with high affinity for D2 and D3 receptor subtypes, classified under ATC N04BC05.
It stimulates postsynaptic dopamine receptors to reduce bradykinesia and rigidity in Parkinson’s disease.
The higher D3 affinity is thought to contribute to benefits in restless legs syndrome while also explaining reward‑pathway effects linked to impulse control disorders.
Pharmacokinetics show renal excretion as the main elimination route so dose adjustment is required in renal impairment.
Extended‑release tablets provide a smoother plasma profile and support once‑daily dosing compared with immediate‑release tablets, which are usually dosed multiple times per day.
Available tablet strengths range across a wide spectrum for titration and conversion between IR and ER forms is based on total daily dose.
Scope Of Approved & Off‑Label Use
Australian Approvals (TGA‑Listed, PBS Inclusion)
Pramipexole is approved by the TGA for Parkinson’s disease and restless legs syndrome, marketed as Sifrol and as generics.
Product information lists both IR and ER tablets across multiple strengths and confirms prescription‑only status.
PBS listings have historically included pramipexole for Parkinson’s, but subsidy details and Authority requirements can vary by formulation and time.
Pharmacists should check current PBS schedules and Authority criteria when cost or subsidy affect patient uptake.
Notable Off‑Label Trends In Australian Practice
Australian neurologists occasionally consider pramipexole for other dopaminergic‑responsive movement disorders in selected cases, but off‑label use is conservative.
Concerns about impulse control disorders and somnolence limit off‑label prescribing outside specialist settings.
Rural prescribers balance access via telehealth e‑scripts with the capacity for face‑to‑face behavioural monitoring, and community pharmacists play a key role in follow‑up.
Dosage Strategy
General Dosing
Start low and titrate slowly using the lowest effective dose, especially for elderly patients and those with renal impairment.
Immediate‑release tablet strengths allow small incremental increases, while ER tablets support once‑daily titration using defined dose steps.
Typical IR starting dose for Parkinson’s is 0.125 mg three times a day and ER start is commonly 0.375 mg once daily.
Condition‑Specific Dosing (PBS Recommendations)
Parkinson’s initiation commonly follows 0.125 mg TID (IR) or 0.375 mg once daily (ER), increasing by 0.125 mg TID every 5–7 days for IR up to a maximum of 4.5 mg/day.
For restless legs syndrome aim to start at 0.125 mg once nightly taken 2–3 hours before bed and titrate at 4–7 day intervals up to 0.5 mg/day.
In elderly patients or those with renal impairment start at lower doses and extend titration intervals, documenting renal function and falls risk in clinical notes when following PBS authority rules.
Safety Protocols
Contraindications (Australian Guidelines)
Absolute contraindication is hypersensitivity to pramipexole or any excipient listed in the product information.
Relative contraindications include severe renal impairment without dose adjustment, history of psychosis, marked orthostatic hypotension and prior compulsive behaviours.
Pregnancy and lactation are generally avoided unless potential benefits clearly outweigh risks.
Adverse Effects (Post‑Market Pharmacovigilance)
Common adverse effects include nausea, drowsiness or fatigue, insomnia, dry mouth, constipation, dizziness and peripheral oedema.
Post‑market data and TGA reports underline serious concerns such as impulse control disorders (gambling, hypersexuality, compulsive spending), sudden sleep episodes and augmentation in RLS.
Older patients have higher risk of hallucinations and orthostatic hypotension, so monitor blood pressure and fall risk at baseline and during titration.
Pharmacists in community chains often identify early side effects and should escalate to the prescriber when behavioural changes or dangerous somnolence arise.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
No major food‑drug interactions are described in the product information, but alcohol and other CNS depressants increase drowsiness and risk of sudden sleep episodes.
Caffeine does not reduce the motor benefit of pramipexole but may worsen insomnia if consumed late in the day.
Drug Combinations To Avoid (TGA Safety Alerts)
Dopamine antagonists such as certain antipsychotics and metoclopramide can antagonise pramipexole efficacy and should be reviewed prior to initiation.
Concomitant sedatives, opioid analgesics and benzodiazepines increase the risk of falls and marked somnolence when used with pramipexole.
Antihypertensives and nitrates can exacerbate orthostatic hypotension and warrant closer blood pressure monitoring after starting or increasing pramipexole.
Levodopa is commonly co‑prescribed and can improve off‑periods, but careful titration is required to manage dyskinesia risk when combining treatments.
Patient Experience Analysis
Australian Survey Data
Patients in Australia report that pramipexole often improves motor control in Parkinson’s and reduces discomfort from restless legs syndrome.
Surveys from 2020–2024 show ER formulations score higher for convenience and adherence compared with IR dosing in urban and regional cohorts.
Adverse behavioural effects and daytime sleepiness are common reasons for dose changes or switching therapies.
Forum And Pharmacy Trends
Online forums record variable experiences with impulse control disorders, prompting peer‑led advice to monitor banks and relationships closely when starting treatment.
Community pharmacists regularly handle queries about daytime sleepiness, driving safety and out‑of‑pocket costs, and often advise early GP review for behavioural symptoms.
Rural patients describe access and monitoring gaps where telehealth e‑scripts improve access but can limit in‑person behavioural screening; pharmacists often bridge this gap.
Distribution & Pricing Landscape
National Pharmacy Chains (Chemist Warehouse, Priceline, TerryWhite)
Pramipexole is distributed widely through major Australian chains such as Chemist Warehouse, Priceline and TerryWhite as well as independent rural pharmacies.
Generics are commonly supplied and patients frequently request lower‑cost options at the time of dispensing.
Online Pharmacy Growth And Telehealth E‑Scripts
Electronic prescriptions and online pharmacy models have accelerated since 2020 and assist regional patients to obtain pramipexole without multiple clinic visits.
In our online pharmacy, mirapex is available without a prescription, with discreet delivery to Australia in 5‑14 days.
Pharmacies must still counsel on behavioural monitoring and driving safety even when supply occurs via e‑script or mail delivery.
PBS Vs Private Cost Comparisons
PBS subsidy status materially affects patient cost and uptake, and Authority requirements may apply for subsidised supply of certain formulations.
Private prescriptions incur a full retail price and many patients opt for generics to reduce out‑of‑pocket expense.
Alternative Options
Comparison Overview
Pramipexole remains a strong first‑line option for early Parkinson’s and monotherapy in RLS, with ER forms aiding adherence.
Ropinirole is an alternative dopamine agonist with a similar efficacy and side‑effect profile and is often PBS‑subsidised.
Rotigotine transdermal patch provides steady delivery and is useful for swallowing difficulties but can cause skin reactions and has PBS restrictions.
Apomorphine injections or infusion systems are specialist rescue options for off‑periods and are not first‑line for routine PBS prescribing.
Pros And Cons Checklist
- Efficacy: Pramipexole effective for motor control and for restless legs syndrome.
- Safety: Monitor for impulse control disorders and somnolence across all dopamine agonists.
- Cost/Access: Generics are typically cheaper and PBS listing affects affordability and authority paperwork.
- Adherence: ER formulations favour once‑daily dosing and reduce dosing variability.
Regulatory Status
TGA Approval Framework
The Therapeutic Goods Administration registers pramipexole products such as Sifrol and requires sponsors to maintain safety dossiers and report signals.
TGA safety communications align with international regulators on key risks including impulse control disorders and somnolence.
PBS Subsidy Process
Pharmaceutical Benefits Advisory Committee submissions determine PBS listing, specifying indication, formulation and any Authority prerequisites for subsidy.
Prescribers must supply Authority numbers where required and pharmacists verify PBS criteria at dispensing to ensure correct subsidy application.
Consolidated FAQ
Q: Can I drive when taking pramipexole?
A: Caution is required because pramipexole can cause sudden sleep episodes and drowsiness; stop driving if you feel sleepy and discuss with the prescriber.
Q: Is pramipexole covered by PBS?
A: Some pramipexole formulations have been PBS‑subsidised; check the current PBS schedule and whether an Authority code is needed at the time of dispensing.
Q: What should family members watch for?
A: Look for compulsive behaviours such as gambling, increased spending or hypersexuality, and for hallucinations or marked confusion, and report these promptly to the prescriber.
Q: How do I store pramipexole at home?
A: Store at room temperature between 15–30°C in the original packaging and away from moisture and direct sunlight.
Q: What if I miss a dose?
A: Take the missed dose as soon as you remember unless it is close to the next dose, and do not double up; seek urgent help for suspected overdose symptoms such as severe hypotension or confusion.
Visual Guide
Clinicians and pharmacists often ask for quick visuals to support counselling and dispensing.
Suggested infographic panels include a PBS pricing panel comparing subsidised versus private costs with an Authority note, a formulation map listing IR and ER strengths, a distribution heatmap for major chains and rural pharmacies, a safety timeline for common adverse effects and monitoring windows, and a concise counselling checklist for pharmacists.
These visuals help patients understand dose forms such as immediate‑release and extended‑release pramipexole tablets and what monitoring to expect after starting therapy.
Storage & Transport
Household Storage Under Australian Climate
Store pramipexole tablets at room temperature 15–30°C, away from moisture and direct sunlight in a cool cupboard rather than a bathroom or car glovebox.
Advise patients to avoid leaving medicines in hot cars during summer and to return deliveries to a shaded area promptly.
Cold‑Chain Logistics For Pharmacies
No cold‑chain is required for pramipexole, but pharmacies should store stock in a temperature‑controlled dispensary and monitor storage during heatwaves.
For mailed deliveries consider insulated packaging during extreme heat and instruct patients to store tablets promptly on receipt.
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
Use an empathetic, structured approach: confirm the indication, verify PBS status, review renal function and current medications, and screen for impulsive or psychotic behaviours.
Provide clear practical advice on dose timing — IR for divided doses and ER once daily — and warn about drowsiness and driving risks.
Document counselling, use teach‑back to confirm understanding and schedule follow‑up within 2–6 weeks after initiation or dose changes.
National Health Authority Recommendations
Follow TGA product information for dosing and contraindications and report adverse events through TGA channels if suspected.
Adjust dosing for renal impairment, avoid use in pregnancy where possible and encourage patients to carry an up‑to‑date medicines list.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5‑7 days |
| Melbourne | Victoria | 5‑7 days |
| Brisbane | Queensland | 5‑7 days |
| Perth | Western Australia | 5‑7 days |
| Adelaide | South Australia | 5‑7 days |
| Canberra | Australian Capital Territory | 5‑7 days |
| Hobart | Tasmania | 5‑7 days |
| Darwin | Northern Territory | 5‑7 days |
| Gold Coast | Queensland | 5‑7 days |
| Newcastle | New South Wales | 5‑9 days |
| Wollongong | New South Wales | 5‑9 days |
| Geelong | Victoria | 5‑9 days |
| Cairns | Queensland | 5‑9 days |
Storage And Transport Practical Tips
Patients should keep pramipexole in the original blister or bottle to protect from humidity and light, and dispose of expired packs responsibly.
Pharmacies should maintain buffer stock for rural demand and document any temperature excursions in the dispensary area.
Guidance For Special Populations
Elderly patients require lower starting doses and slower titration due to increased sensitivity and the higher likelihood of renal impairment.
Renal impairment necessitates dose reductions and prolonged titration intervals in accordance with product information.
Children are not recommended to use pramipexole as standard dosing and safety data are not established for paediatric populations.
When To Seek Urgent Help
Urgent medical attention is required for suspected overdose, with symptoms such as extreme confusion, severe hypotension or marked hallucinations.
Escalate promptly to the prescriber or emergency services if a patient develops sudden sleep episodes while awake, dangerous impulsive behaviour or signs of severe allergic reaction.
References And Where To Get Help
Product information and TGA registration details for Sifrol and generic pramipexole remain the authoritative sources for dosing and safety information.
Community pharmacists and prescribing clinicians should be the first point of contact for counselling, PBS checks and reporting adverse events.
Final Practical Checklist For Pharmacists
- Confirm indication (Parkinson’s disease vs restless legs syndrome) and current medicines list before supply.
- Check renal function and adjust starting dose as required.
- Screen for past compulsive behaviours or psychosis and counsel family to watch for behavioural changes.
- Advise on drowsiness, driving safety and the need to report hallucinations or sudden sleep episodes.
- Document counselling and arrange early follow‑up within 2–6 weeks after initiation or dose change.