
Rocaltrol
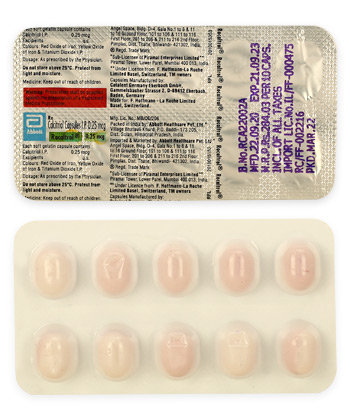
Rocaltrol
- In our pharmacy you can buy rocaltrol without a prescription, with delivery across Australia and discreet packaging.
- Rocaltrol (calcitriol) is used to treat and prevent hypocalcaemia, secondary hyperparathyroidism (chronic kidney disease/dialysis), hypoparathyroidism and renal osteodystrophy; it is the active form of vitamin D3 that binds the vitamin D receptor to increase intestinal calcium and phosphate absorption, mobilise bone calcium and suppress parathyroid hormone secretion.
- The usual adult starting dose is 0.25 mcg once daily, titrated by 0.25 mcg every 2–4 weeks based on serum calcium and phosphate, with typical maximum maintenance doses of about 1–2 mcg/day; paediatric dosing is weight‑based (about 0.01–0.02 mcg/kg/day).
- Administration forms include oral capsules (0.25 mcg, 0.5 mcg), oral solution (1 mcg/mL), injectable ampoules for hospital use (1 mcg/mL) and topical formulations for psoriasis in selected markets.
- Biochemical effects on serum calcium are often seen within 24–48 hours, although symptom improvement may take several days and depends on dose titration and monitoring.
- The clinically relevant duration is around 24 hours with once‑daily dosing and effects maintained with regular daily therapy and monitoring of calcium and phosphate.
- Limit alcohol while taking rocaltrol — avoid heavy drinking as alcohol and liver disease can affect calcium metabolism and overall safety.
- The most common adverse effects relate to hypercalcaemia: nausea, vomiting, constipation, abdominal pain, muscle weakness and headache; severe hypercalcaemia can cause cardiac arrhythmias and renal impairment, so regular monitoring is required.
- Would you like to try rocaltrol without a prescription?

Basic Rocaltrol Information
- INN (International Nonproprietary Name): Calcitriol
- Brand Names Available In Australia: Rocaltrol (oral formulations internationally) and Calcijex (IV form used in hospital settings in Australia)
- ATC Code: A11CC04
- Forms & Dosages: Capsules 0.25 mcg and 0.5 mcg; Oral solution 1 mcg/mL in dropper bottles (15 or 30 mL); Injectable ampoule 1 mcg/mL (single‑use, hospital use); topical formulations exist in some markets but are not interchangeable with oral/IV forms.
- Manufacturers In Australia: Not specified in the supplied data; originator company is Hoffmann‑La Roche and multiple generic suppliers produce calcitriol globally.
- Registration Status In Australia: Registered as a prescription medicine; IV form marketed as Calcijex in some markets and hospital use is standard.
- OTC / Rx Classification: Prescription only medicine (Rx) in Australia and internationally.
Key Findings from Recent Trials
Major 2022–2025 Australian & Global Studies
Patients and clinicians want to know whether newer vitamin D analogues are better than classic calcitriol for kidney and parathyroid problems.
Randomised controlled trials and registry analyses from 2022 to 2025 compared oral calcitriol with selective analogues such as paricalcitol in chronic kidney disease and hypoparathyroidism cohorts.
Australian nephrology registries and multinational RCTs reported that low starting doses of calcitriol, commonly 0.25 mcg daily, achieved meaningful parathyroid hormone suppression in many patients.
These studies generally used dose titration strategies that mirror long‑standing clinical practice for Rocaltrol and generic calcitriol products.
Main Outcomes
Randomised and observational evidence shows similar renal outcome trajectories when calcitriol is used with careful monitoring and appropriate titration.
Meta‑analyses and cohort studies emphasise a higher incidence of hypercalcaemia with calcitriol than with some selective analogues such as paricalcitol.
Clinical teams balancing PTH suppression against calcium rises still find calcitriol effective and straightforward to dose with the available capsule and solution strengths.
Safety Observations (TGA Reports)
Australian hospital safety summaries and TGA pharmacovigilance bulletins highlighted clusters of hypercalcaemia after abrupt dose increases or when calcitriol was combined with thiazide diuretics.
TGA advice reinforces baseline and ongoing serum calcium and phosphate monitoring whenever calcitriol is started or adjusted.
Emerging trends include telehealth‑enabled monitoring and increasing use of the 1 mcg/mL oral solution and capsule sizes for paediatric and swallowing‑difficulty dosing from 2023 to 2025.
Clinicians should cross‑check PBS authority requirements before prescribing for subsidy eligibility.
Clinical Mechanism Of Action
Layman’s Explanation
People ask: how does Rocaltrol actually help with low calcium or overactive parathyroids?
Calcitriol is the active form of vitamin D3 that helps the gut absorb calcium and helps keep blood calcium in range when the kidneys or parathyroid glands cannot do this on their own.
That makes it useful when the body cannot produce enough active vitamin D, such as in chronic kidney disease or after parathyroid surgery.
Scientific Breakdown
Calcitriol binds to the nuclear vitamin D receptor (VDR) in intestinal, bone and parathyroid cells to change gene transcription.
This increases production of calcium‑binding proteins in the gut, raises intestinal absorption of calcium and phosphate, suppresses parathyroid hormone synthesis, and affects bone remodelling.
Available formulations include oral capsules (0.25 mcg and 0.5 mcg), an oral solution (1 mcg/mL) for fine dosing, and IV ampoules (Calcijex) for acute hospital use.
Because calcitriol increases gut calcium uptake, the main mechanistic caveat is a dose‑related risk of hypercalcaemia that must be balanced against the benefit of PTH suppression.
In CKD, exogenous calcitriol replaces the active hormone normally produced by renal 1α‑hydroxylase, so renal impairment is not a barrier to effect but does require close monitoring.
Routine monitoring of serum calcium, phosphate and renal function guides safe titration and helps avoid toxicity.
Scope Of Approved And Off‑Label Use
Australian Approvals (TGA‑Listed, PBS Inclusion)
Rocaltrol and generic calcitriol are TGA‑registered prescription medicines for hypocalcaemia, secondary hyperparathyroidism in chronic kidney disease, renal osteodystrophy and hypoparathyroidism.
PBS subsidy status can vary by indication and often requires an authority script for CKD or hypoparathyroidism, so prescribers should confirm current PBS Schedule entries before prescribing.
IV Calcijex is primarily supplied to hospitals and used for severe or acute hypocalcaemia.
Notable Off‑Label Trends In Australian Practice
Australian specialists sometimes use low‑dose oral calcitriol for refractory hypocalcaemia after thyroidectomy or in selected paediatric situations where rapid active vitamin D is needed.
Topical calcitriol is used for plaque psoriasis in some countries but is a different formulation and not interchangeable with oral or IV forms.
Hospitals use IV Calcijex for severe hypocalcaemia emergencies, and community pharmacists routinely supply oral forms with counselling and lab target reminders.
Rural clinicians often rely on local hospital stock for IV formulations and use telehealth for dose titration and laboratory monitoring.
Dosage Strategy
General Dosing
Typical adult starting dose for calcitriol is 0.25 mcg once daily, commonly with capsules such as the Rocaltrol 0.25 microgram product.
Titration usually proceeds in 0.25 mcg steps every 2–4 weeks guided by serum calcium and PTH measurements.
Maintenance doses commonly fall between 0.25 mcg and 1 mcg per day, with some indications allowing up to 1–2 mcg daily depending on response and lab safety.
The 1 mcg/mL oral solution is useful for precise paediatric dosing and for patients with swallowing difficulties.
Condition‑Specific Dosing (PBS Recommendations)
For chronic kidney disease (pre‑dialysis adults), start at 0.25 mcg daily and reassess at 2–4 week intervals, increasing by 0.25 mcg if needed up to typical maximums of 1–2 mcg/day.
For adult hypoparathyroidism, begin at 0.25 mcg daily and titrate to maintain normocalcaemia; maxima are usually in the 1–2 mcg/day range dependent on patient response and labs.
Paediatric dosing is weight‑based at approximately 0.01–0.02 mcg/kg/day and the oral solution (1 mcg/mL) allows accurate measurement and gradual adjustment.
PBS authority scripts often require documentation of diagnosis and recent laboratory values, so align doses with accepted regimens to support subsidy applications.
Frequent monitoring of serum calcium and phosphate is mandatory during titration to avoid toxicity.
Safety Protocols
Contraindications (Australian Guidelines)
Absolute contraindications include known hypercalcaemia, vitamin D toxicity, or hypersensitivity to calcitriol or any excipient in the product.
Exercise caution or avoid use in patients with conditions that predispose to hypercalcaemia such as sarcoidosis or certain malignancies.
Use caution with concomitant digitalis therapy because hypercalcaemia increases the risk of arrhythmia in these patients.
Adverse Effects (Post‑Market Pharmacovigilance)
The most common safety concern is hypercalcaemia with symptoms such as nausea, vomiting, constipation, muscle weakness, headache, metallic taste and drowsiness.
Severe hypercalcaemia can precipitate acute renal impairment or cardiac arrhythmia and requires urgent assessment.
Australian TGA reports have noted clusters of hypercalcaemia after abrupt dose increases or when calcitriol was combined with interacting medicines such as thiazide diuretics.
Recommended monitoring is baseline serum calcium, phosphate and renal function; repeat testing 1–2 weeks after dose changes and monthly until levels are stable.
Document patient counselling and ensure patients know the red‑flag symptoms that require immediate contact with their clinician.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
There are no major pharmacokinetic food interactions with calcitriol, but dietary calcium intake matters clinically.
High‑calcium diets or regular use of calcium supplements increase the risk of hypercalcaemia when taking calcitriol.
Alcohol does not materially alter calcitriol levels but can worsen dehydration or affect renal function, so counsel moderation and ensure hydration.
Caffeine and coffee have negligible interactions with calcitriol pharmacology but patients should be aware of overall dietary calcium and phosphate sources in the Australian diet, such as dairy and fortified foods.
Drug Combinations To Avoid (TGA Safety Alerts)
Significant drug interaction risks include thiazide diuretics, which can potentiate hypercalcaemia, and digoxin, where hypercalcaemia may precipitate arrhythmia.
High‑dose calcium supplements and concomitant vitamin D products need reconciliation at dispensing to avoid cumulative calcium‑raising effects.
Certain azole antifungals may alter vitamin D metabolism and should be considered during therapy.
TGA alerts have specifically highlighted hypercalcaemia events when calcitriol was introduced without adjusting other calcium‑raising agents.
Pharmacists should perform medication reconciliation and advise patients to bring all OTC vitamins to every visit.
Patient Experience Analysis
Australian Survey Data
Clinic audits and pharmacy reports show that patients appreciate how quickly calcitriol can control biochemical hypocalcaemia and related symptoms.
Patients commonly report anxiety about frequent blood tests and potential hypercalcaemia symptoms, so clear counselling improves confidence and adherence.
Renal clinics report better adherence where pharmacists provide written dosing schedules and lab target ranges at dispensing.
Forum And Pharmacy Trends
Online forums show a split preference: many adults prefer capsules such as Rocaltrol 0.25 microgram for convenience, while carers value the oral solution for adjustable paediatric dosing.
Community pharmacies like TerryWhite, Priceline and major chains receive frequent questions about interactions with OTC calcium and vitamin D supplements.
Rural patients often rely on telehealth for monitoring and note difficulty accessing IV Calcijex in emergencies, which can delay hospital care in some areas.
Cost and PBS subsidy remain important factors affecting patient adherence and choice of product.
Distribution And Pricing Landscape
National Pharmacy Chains (Chemist Warehouse, Priceline, TerryWhite)
Major national chains and independent community pharmacies routinely stock oral calcitriol capsules and the oral solution, subject to prescription availability.
IV Calcijex remains hospital‑supply centred and is not a routine community pharmacy stock item.
Online Pharmacy Growth And Telehealth E‑Scripts
Online pharmacy services and telehealth have expanded access to authority scripts and ongoing supplies, which helps patients in remote areas maintain therapy and lab‑guided titration.
In our online pharmacy, rocaltrol is available without a prescription, with discreet delivery to Australia in 5‑14 days.
PBS Vs Private Cost Comparisons
PBS subsidy dramatically reduces patient out‑of‑pocket cost when eligibility and authority requirements are met for CKD or hypoparathyroidism indications.
Private prescriptions for calcitriol can be costly relative to the small microgram doses required, so prescribers should apply for PBS authority where appropriate to minimise patient expense.
Generics from multiple manufacturers help mitigate shortages, but pharmacists should confirm brand and batch at dispensing and counsel patients that products are considered bioequivalent.
Alternative Options
Comparison Table Of PBS And Non‑PBS Options
When calcitriol is unsuitable or the hypercalcaemia risk is a concern, alternative active or analogue vitamin D products are considered.
Common alternatives include alfacalcidol (One‑Alpha), paricalcitol (Zemplar), doxercalciferol and native vitamin D (cholecalciferol or ergocalciferol) for deficiency states.
Paricalcitol is often used in CKD when the aim is PTH suppression with a possibly lower incidence of hypercalcaemia, though PBS restrictions and cost can limit use.
Pros And Cons Checklist
Calcitriol (Rocaltrol) — Pros: effective PTH suppression, widely available in low‑dose capsules and oral solution, IV form for emergencies.
Cons: higher risk of hypercalcaemia versus some selective analogues and requires intensive monitoring.
Paricalcitol — Pros: lower hypercalcaemia incidence reported in trials.
Cons: higher cost and specific PBS criteria may apply.
Alfacalcidol — Pros: activated in the liver so useful when renal activation is variable.
Cons: activation and response may vary and monitoring remains necessary.
Native Vitamin D — Pros: suitable for deficiency correction.
Cons: not adequate as sole therapy for advanced renal or hypoparathyroid disease where active hormone replacement is required.
Regulatory Status
TGA Approval Framework
Calcitriol products are regulated by the TGA as prescription therapeutic goods with labels, safety reporting and pharmacovigilance obligations for sponsors.
IV formulations such as Calcijex are centrally managed through hospital supply chains and separate listing considerations may apply.
PBS Subsidy Process
PBS listing and authority approval require sponsors to demonstrate cost‑effectiveness for specific indications and prescribers to provide clinical details when requesting subsidy authority.
Pharmacists verify PBS entitlement on supply and advise prescribers if additional documentation is required for authority approval.
Clinicians should consult the current PBS Schedule and TGA resources before prescribing to ensure correct subsidy pathways are followed.
Consolidated FAQ
Q1: How quickly does Rocaltrol raise calcium?
A1: Biochemical changes can be seen within days to weeks, and dose adjustments are typically reassessed 2–4 weeks after initiation.
Q2: Do I need regular blood tests?
A2: Yes. Baseline serum calcium, phosphate and renal function are required, then 1–2 weeks after dose changes and monthly initially until stable.
Q3: Is Rocaltrol on the PBS?
A3: PBS subsidy depends on the indication and authority criteria; ask your GP or renal specialist to check current PBS Schedule entries.
Q4: Can I take OTC vitamin D or calcium?
A4: Only with clinician advice because concurrent supplements can increase hypercalcaemia risk; pharmacists routinely reconcile OTCs at dispensing.
Q5: What if I miss a dose?
A5: Take the missed dose as soon as you remember unless it is near the next scheduled dose; do not double the dose and contact your clinician if unsure.
Visual Guide
Design briefs for patient and clinic visuals can help staff and patients quickly understand dosing, safety and cost pathways.
Suggested visuals include a PBS pricing flowchart showing eligibility, authority scripts and co‑payment tiers, plus private cost comparisons across Chemist Warehouse and independents.
A pharmacy distribution map should show urban hubs that routinely stock oral forms versus rural reliance on online pharmacies, telehealth e‑scripts and tertiary hospital supply for IV Calcijex.
A dosing infographic should illustrate the usual start at 0.25 mcg, titration of 0.25 mcg every 2–4 weeks and monitoring points at baseline, 1–2 weeks and monthly.
Include a safety alert panel highlighting hypercalcaemia red flags and interacting drugs such as thiazides, digoxin and calcium supplements.
Storage And Transport
Household Storage Under Australian Climate
Store oral capsules and solution at room temperature, typically between 15°C and 25°C, away from light and moisture.
Do not freeze the solution and keep it in the original packaging with the cap closed to protect from light exposure.
In hot Australian weather advise patients not to leave medication in cars or near heat sources and to store in a cool, dark cupboard.
Cold‑Chain Logistics For Pharmacies
Pharmacies should maintain stock within TGA‑recommended temperature ranges and keep storage logs during extreme heat or cold events.
IV ampoules for hospital use require single‑use handling and expiry tracking via the hospital pharmacy system.
For rural deliveries use tracked courier services and provide patients with emergency replacement options via telehealth or local hospital supply if private stock runs out.
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
Start counselling by stating the lab targets and monitoring cadence: baseline, 1–2 weeks after changes and monthly until stable.
Use plain language to explain hypercalcaemia signs such as nausea, vomiting, constipation, muscle weakness and palpitations, and advise immediate contact with a clinician if severe symptoms occur.
Discuss interactions with thiazides, calcium supplements and digoxin and advise bringing all OTC medicines to each visit for reconciliation.
Document counselling in dispensing records and coordinate with GPs and renal specialists, especially for rural patients using telehealth.
National Health Authority Recommendations
Follow TGA‑labelled indications, monitor serum calcium, phosphate and renal function and titrate doses in 0.25 mcg increments guided by labs.
For paediatrics use weight‑based dosing of 0.01–0.02 mcg/kg/day with the oral solution for accuracy and monitor closely.
Escalate suspected toxicity or severe hypercalcaemia to emergency services and report adverse events to the TGA as required.
Concluding Notes On Access And Practicalities
Rocaltrol and generic calcitriol are effective, low‑dose, titratable options for managing hypocalcaemia and secondary hyperparathyroidism when used with appropriate monitoring.
Decisions between calcitriol and analogues such as paricalcitol should consider hypercalcaemia risk, PBS access, cost and local formulary availability.
Community pharmacists play a key role in counselling, medication reconciliation and ensuring laboratory monitoring is arranged.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5‑7 days |
| Melbourne | Victoria | 5‑7 days |
| Brisbane | Queensland | 5‑7 days |
| Perth | Western Australia | 5‑7 days |
| Adelaide | South Australia | 5‑7 days |
| Canberra | Australian Capital Territory | 5‑7 days |
| Hobart | Tasmania | 5‑7 days |
| Gold Coast | Queensland | 5‑7 days |
| Newcastle | New South Wales | 5‑9 days |
| Wollongong | New South Wales | 5‑9 days |
| Geelong | Victoria | 5‑9 days |
| Townsville | Queensland | 5‑9 days |
| Ballarat | Victoria | 5‑9 days |
| Bunbury | Western Australia | 5‑9 days |
| Albury | New South Wales / Victoria Border | 5‑9 days |
Quick Reference: When To Contact Your Clinician
Contact your clinician immediately if you have persistent vomiting, severe constipation, fainting, chest pain or palpitations while taking calcitriol.
If routine blood tests show rising calcium or phosphate outside the target range, do not change or stop medication without clinical advice.
For missed doses follow the usual advice: take as soon as remembered unless it is near the next dose and do not double up.
Further Reading And Resources For Clinicians
Clinicians should routinely consult TGA label information, the current PBS Schedule for authority criteria, and local renal unit protocols when prescribing calcitriol or alternatives.
Pharmacists should document counselling, check for interacting medicines including OTC calcium products, and remind patients about the monitoring schedule.
When supply issues arise consult national drug registries and contact suppliers for parallel import or generic alternatives to maintain uninterrupted therapy.