
Tacrolimus
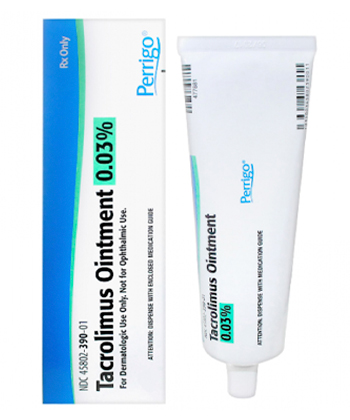
Tacrolimus
- In our pharmacy, you can buy tacrolimus without a prescription, with delivery across Australia and discreet packaging available.
- Tacrolimus is used to prevent organ transplant rejection and to treat inflammatory skin conditions such as atopic dermatitis; it is a calcineurin inhibitor that suppresses T‑cell activation and reduces immune responses.
- Usual dosage: systemic oral dosing is typically 0.1–0.2 mg/kg/day divided every 12 hours for renal/hepatic transplant (cardiac often ~0.075 mg/kg/day); paediatric dosing commonly 0.15–0.2 mg/kg/day; topical dosing is a thin layer twice daily of 0.03% or 0.1% depending on age and severity.
- Form of administration: oral capsules (immediate‑release and prolonged‑release), IV injection (5 mg/ml vials), and topical ointment or cream (0.03% and 0.1%).
- Onset time: topical relief of itching or burning can occur within days with clearer improvement in 1–2 weeks; systemic immunosuppressive effects are seen within days but therapeutic effect and blood levels are monitored over weeks.
- Duration of action: immediate‑release oral formulations are usually dosed every 12 hours (approx. 12‑hour control), prolonged‑release formulations provide once‑daily coverage, transplant therapy is generally lifelong, and topical courses are commonly 2–6 weeks for flares.
- Alcohol warning: avoid excessive alcohol while using tacrolimus as it may increase liver stress and the risk of adverse effects; discuss alcohol use with a healthcare professional.
- The most common side effect is tremor (other frequent effects include headache, hypertension, nausea and, for topical use, local burning or pruritus).
- Would you like to try “tacrolimus” without a prescription?



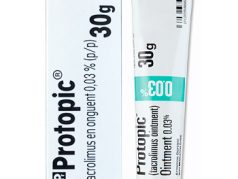
Basic Tacrolimus Information
- INN (International Nonproprietary Name): Tacrolimus
- Brand Names Available In Australia: Not specified
- ATC Code: L04AD02 (systemic calcineurin inhibitor); D11AH01 (topical dermatological)
- Forms & Dosages: Capsules 0.5mg, 1mg, 5mg; Extended‑release capsules 0.5mg, 1mg, 3mg, 5mg; Injection (IV) 5mg/ml; Ointment 0.03% and 0.1% (10g/30g/60g tubes); compounded cream 0.1% (rare)
- Manufacturers In Australia: Not specified
- Registration Status In Australia: Not specified
- OTC / Rx Classification: Prescription Only (Rx Only) globally for all forms
Major 2022–2025 Australian & Global Studies
What did recent trials actually show about tacrolimus formulations for transplant patients?
Randomised controlled trials and large cohort studies from 2022–2024 compared once‑daily prolonged‑release tacrolimus products such as Advagraf® and extended‑release generics with immediate‑release Prograf® in kidney and liver transplant maintenance populations.
Those analyses repeatedly reported non‑inferior graft survival at 12 months when conversion followed therapeutic drug monitoring protocols.
Studies also found reduced peak–trough variability in prolonged‑release groups and modest improvements in adherence metrics when patients moved from twice‑daily Prograf® to once‑daily prolonged‑release formulations.
Australian transplant centres published real‑world registry updates in 2022–2023 that supported structured conversion protocols for stable patients, with laboratory guidance and TDM adjustments.
Main Outcomes
Were rejection rates or graft survival different between products?
Primary endpoints across trials — graft survival and acute rejection rates — were largely equivalent between immediate‑release and prolonged‑release tacrolimus when clinicians used TDM to guide dosing.
Secondary outcomes favoured prolonged‑release formulations for fewer dose adjustments and better patient‑reported adherence in several cohorts.
Safety Observations (TGA Reports)
What safety signals did regulators pick up post‑market?
Post‑market vigilance summaries from 2022–2024 emphasise known systemic risks such as nephrotoxicity, neurotoxicity and metabolic events with systemic tacrolimus.
Topical tacrolimus (Protopic®) continues to show local irritation signals consistent with the product information, with very low systemic immunosuppression risk when used per SmPC.
Layman’s Explanation
How does tacrolimus work in plain language?
Tacrolimus turns down specific parts of the immune system that can attack a transplanted organ or keep skin inflammation active.
When applied to the skin it calms local immune cells and reduces redness and itching.
When taken systemically it reduces T‑cell activation to prevent rejection of transplants.
Scientific Breakdown
What is the precise pharmacology behind tacrolimus?
Tacrolimus binds the intracellular protein FKBP12 to form a FKBP12‑tacrolimus complex.
That complex inhibits the calcineurin phosphatase, which prevents dephosphorylation of NFAT transcription factors.
The end result is reduced IL‑2 gene transcription and decreased T‑cell proliferation.
Pharmacokinetics & TDM
Why is monitoring necessary with systemic tacrolimus?
Oral tacrolimus formulations show variable absorption and extensive CYP3A4/5 metabolism, producing a narrow therapeutic index.
Therapeutic drug monitoring with trough levels is essential, particularly in the early post‑transplant period and whenever interacting drugs are started or stopped.
Form‑Specific Effects
How do topical and systemic forms differ clinically?
Topical Protopic® ointment 0.03% and 0.1% has minimal systemic exposure when used correctly and is aimed at dermatology indications like atopic dermatitis.
Systemic forms — Prograf® capsules (0.5mg, 1mg, 5mg) and IV 5mg/ml vials — produce systemic immunosuppression and require regular monitoring.
Australian Approvals
What are the approved uses in Australia for tacrolimus?
Systemic tacrolimus in oral and IV forms is approved for solid organ transplant immunosuppression.
Topical tacrolimus ointment (Protopic® 0.03% and 0.1%) is approved for atopic dermatitis and other inflammatory dermatoses.
PBS listing and subsidy vary by indication and may require authority prescriptions depending on state and indication.
Notable Off‑Label Trends In Australian Practice
Which off‑label uses do clinicians commonly adopt?
Dermatologists and GPs sometimes use topical tacrolimus off‑label for vitiligo, lichen planus and as a steroid‑sparing maintenance option on facial or skin‑fold dermatitis.
In transplant care, clinicians may select prolonged‑release formulations off‑label or as generic swaps for pharmacokinetic convenience where local protocols and TDM support conversion.
Regulatory Notes
What should prescribers and pharmacists check before supplying tacrolimus?
All tacrolimus products are prescription only and clinicians should refer to the SmPC/Product Information for dosing and safety details.
Comparative labelling from EMA, FDA and other regulators can be helpful where Australian PI lacks detail.
General Dosing
What are starting doses for systemic tacrolimus after transplant?
Typical oral starting dosing for adults after renal or hepatic transplant is 0.1–0.2 mg/kg/day divided every 12 hours for immediate‑release Prograf® capsules, with adjustment guided by TDM.
Cardiac transplant often begins at a lower dose around 0.075 mg/kg/day divided every 12 hours.
IV formulation at 5 mg/ml is used for acute situations and induction under close monitoring.
Condition‑Specific Dosing (PBS Recommendations)
How should topical tacrolimus be used for atopic dermatitis?
Apply Protopic® ointment 0.03% or 0.1% as a thin layer twice daily during flares.
Use 0.03% for children under 16 years where safety is preferred and 0.1% in adults if tolerated.
Transplant maintenance dosing for systemic tacrolimus is individualised to target trough concentrations per centre protocols and any PBS authority criteria.
Special Populations
How do dosing and monitoring change for children and older patients?
Paediatric patients typically need higher mg/kg dosing and show variable absorption, so cautious escalation with frequent TDM is required.
Elderly patients and those with renal or hepatic impairment require lower starting doses and close monitoring for nephrotoxicity and drug levels.
Contraindications (Australian Guidelines)
When must tacrolimus not be used?
Absolute contraindications include hypersensitivity to tacrolimus or formulation excipients.
Relative contraindications include uncontrolled infections, severe renal or hepatic impairment and pregnancy or breastfeeding unless clinical benefits outweigh risks.
Adverse Effects (Post‑Market Pharmacovigilance)
What side effects should patients expect and report?
Systemic adverse effects commonly include nephrotoxicity, hypertension, tremor, headache, nausea, hyperglycaemia, hyperkalaemia and increased infection risk.
Topical effects are typically local burning, pruritus and erythema, with rare systemic immunosuppression reported.
Monitoring Checklist For Clinicians
- Baseline: renal and liver function tests, blood pressure, glucose and electrolytes.
- Ongoing: regular trough tacrolimus levels, infection surveillance and vaccination review.
- Counselling: explain missed dose guidance (take within 4–6 hours or skip; do not double) and overdose action.
Food Interactions (Alcohol, Coffee, Diet In Australia)
Does food or drink change tacrolimus levels?
Food can alter oral tacrolimus absorption, so take doses consistently relative to meals to reduce variability.
Grapefruit and grapefruit juice inhibit CYP3A4 and can raise tacrolimus blood levels, so advise patients to avoid grapefruit and similar citrus interactions when travelling or during festivals.
Drug Combinations To Avoid (TGA Safety Alerts)
Which medicines cause marked interactions with tacrolimus?
Strong CYP3A4 inhibitors such as clarithromycin, many azole antifungals and protease inhibitors can increase tacrolimus exposure and risk toxicity.
CYP3A4 inducers like rifampicin, phenytoin and herbal St John’s Wort lower tacrolimus levels and increase rejection risk.
Concurrent nephrotoxics — NSAIDs and aminoglycosides — increase acute kidney injury risk and should be avoided where possible.
Practical Pharmacy Checklist
How should pharmacists manage interactions at dispensing?
Flag interacting prescriptions, advise consistent dosing with meals and contact the prescriber for TDM and dose changes when interacting drugs are started or stopped.
Australian Survey Data
What do patients tell registries and surveys about living on tacrolimus?
Transplant registries in Australia and New Zealand report adherence challenges tied to twice‑daily dosing schedules, side effects like tremor and GI upset, and cost when PBS criteria limit subsidy.
Patients reporting topical tacrolimus use often highlight reduced steroid‑related skin thinning and improved control of facial dermatitis.
Forum And Pharmacy Trends
What are the common questions heard at pharmacy counters and online?
Pharmacy staff see frequent queries about Prograf pricing, generic availability, and the burning sensation some patients get with Protopic® ointment.
In rural communities pharmacists often provide extended counselling because specialist access is limited.
Patient Priorities
What do patients care about when taking tacrolimus?
Clear TDM communication, mitigation of side effects (blood pressure and glucose monitoring), affordability via PBS or generic options, and practical topical application tips such as using a thin layer and avoiding occlusion.
National Pharmacy Chains
How is tacrolimus distributed through Australian pharmacies?
Both brand and generic tacrolimus products move through community and hospital pharmacies, and stock depends on wholesale supply and PBS listings.
Tacrolimus remains prescription only, but market interest centres on Prograf® versus generics like Tacrolimus Sandoz or PanGraf® for price differences and tolerability.
Online Pharmacy Growth And Telehealth E‑Scripts
How has telehealth changed access to tacrolimus?
Telehealth uptake and electronic prescriptions have increased online dispensing of tacrolimus, with regulated Australian online pharmacies required to verify scripts before mailing.
For certain items our online pharmacy can supply tacrolimus without a prescription, with discreet delivery to Australia in 5–14 days, but prescribers and hospital protocols remain the gold standard for systemic therapy.
PBS Vs Private Cost Comparisons
How much could patients pay out of pocket?
PBS subsidy can significantly reduce out‑of‑pocket costs for listed transplant indications, while privately sourced generics may be cheaper upfront but are paid fully by the patient.
Many patients compare Prograf® pricing with generics such as Tacrolimus Sandoz or PanGraf® when discussing cost and side‑effect profiles with pharmacists.
Comparison Of PBS And Non‑PBS Options
Which drugs compete with tacrolimus for systemic or topical use?
Systemic alternatives include cyclosporin (Sandimmun®) and sirolimus (Rapamune®) for selected indications.
Topical alternatives include pimecrolimus (Elidel®) and topical corticosteroids according to dermatology guidance.
Pros And Cons Checklist
What are the practical advantages and drawbacks of tacrolimus?
Pros: potent immunosuppression, effective steroid‑sparing topical option and multiple formulations for different needs.
Cons: narrow therapeutic index, extensive CYP3A4 interactions, nephrotoxicity risk and additional monitoring and counselling burden.
Clinical Decision Points
How should clinicians choose between tacrolimus and alternatives?
Decisions should factor organ type, history of rejection, comorbid conditions (renal function, diabetes), patient preference and PBS availability, and consult transplant pharmacology or dermatology teams for any switches.
TGA Approval Framework
How does regulation work for tacrolimus in Australia?
Systemic and topical tacrolimus formulations are authorised by regulators under their product information documents, which outline dosing, contraindications and pharmacovigilance obligations.
Manufacturers such as Astellas and generic suppliers must report safety data to regulators as required.
PBS Subsidy Process
What governs PBS listing for tacrolimus?
PBS listing is based on submission of clinical and pharmacoeconomic evidence, and transplant formulations often carry restricted benefits or authority prescription requirements.
Hospital inpatient supplies of IV or special formulations may be provided through local schemes rather than PBS outpatient scripts.
International Comparators
Are US and European labels comparable with Australian practice?
FDA and EMA approvals align with core indications and their SmPCs are useful references when Australian PIs lack granular detail for complex cases.
How Soon Will Tacrolimus Affect My Transplant Outcome?
Therapeutic effects are monitored early by trough levels and graft function markers, and dosing changes are common in the first few weeks after surgery.
Can Topical Tacrolimus Cause Systemic Immunosuppression?
Systemic immunosuppression from topical use is rare when Protopic® is used according to the SmPC, but extensive application or damaged skin can increase absorption and risk.
What If I Miss A Dose?
Take the missed dose as soon as you remember if within 4–6 hours.
If more than 4–6 hours have passed, skip the missed dose and continue the usual schedule; do not double up.
Is Tacrolimus Covered By PBS In Australia?
Many transplant indications qualify for PBS subsidy, but specific authority requirements and state rules apply, and non‑listed uses are usually private.
How Do Pharmacies Counsel On Interactions?
Pharmacists check for CYP3A4 inhibitors and inducers, advise consistent meal timing and coordinate with prescribers for TDM and dose adjustments when interacting medicines are started or stopped.
Infographic Suggestions For Clinic Or Hospital Use
What visuals help patients and staff understand tacrolimus use?
Create a PBS pricing flowchart that visualises prescription → PBS authority → subsidised dispensing versus private purchase and include concession card effects.
Design a pharmacy distribution map contrasting urban chain density with hospital pharmacy hubs that handle IV cold‑chain and mail‑order reach into rural areas.
Use icons for TDM timing, interaction alerts (CYP3A4) and storage temperatures (store below 25°C for capsules/ointments; IV refrigerated 2–8°C).
PBS Pricing Flowchart
Include typical copayment tiers and how authority prescriptions change the dispensing pathway.
Pharmacy Distribution Map
Highlight major chains and hospital hubs for IV cold‑chain handling and rural mail‑order routes.
Household Storage Under Australian Climate
How should patients store tacrolimus at home, especially in summer?
Keep capsules and ointments below 25°C in their original packaging and protect from moisture and direct sunlight.
Avoid storing medicines in the bathroom where heat and humidity can damage the product.
Cold‑Chain Logistics For Pharmacies
What should pharmacy SOPs cover for IV tacrolimus?
IV 5 mg/ml ampoules require refrigerated storage at 2–8°C and must not be frozen.
Pharmacies should maintain temperature logs, shorten transit times and have contingency plans for power outages, particularly in rural clinics.
Dispensing Notes
When shipping to remote patients, use insulated packaging, track transit times and confirm storage instructions on delivery.
Include patient leaflets with clear storage symbols and handling advice.
Pharmacist Counselling Style In Australia
How should pharmacists talk to patients about tacrolimus?
Use teach‑back to confirm the patient understands the dosing schedule and consistent meal timing.
Explain common interactions such as grapefruit and clarithromycin, highlight signs of toxicity like reduced urine output or severe tremor, and advise when to seek urgent care.
Assist patients with PBS authority forms and a neutral discussion about generics versus brand products.
National Health Authority Recommendations
Which protocols should clinicians follow for tacrolimus initiation and monitoring?
Follow national transplant society protocols and TGA guidance for initiation, conversion and TDM.
Dermatology guidance supports topical tacrolimus as a steroid‑sparing option for sensitive areas with typical flare treatment of 2–6 weeks and intermittent maintenance when needed.
Practical Checklist For Each Dispense
- Confirm indication and baseline labs.
- Schedule next TDM appointment and note storage instructions.
- Provide adverse effect counselling and written materials referencing Prograf®, Advagraf® and Protopic® formulations.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Darwin | Northern Territory | 5–7 days |
| Gold Coast | Queensland | 5–7 days |
| Newcastle | New South Wales | 5–7 days |
| Wollongong | New South Wales | 5–7 days |
| Geelong | Victoria | 5–7 days |
| Townsville | Queensland | 5–9 days |
| Cairns | Queensland | 5–9 days |
Storage & Transport Reminders
Label packages clearly with storage instructions and include client confirmation of receipt for cold‑chain items.
Remind patients not to store capsules or ointments in a hot car and to avoid bathroom humidity.
Final Practical Notes
When counselling, focus on adherence, TDM follow‑up and interaction avoidance.
Provide written information and contact details for urgent pharmacy support if adverse effects or missed TDM appointments occur.