
Topiramate
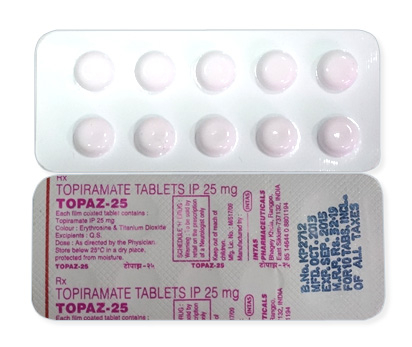
Topiramate
- In our pharmacy, you can buy topiramate without a prescription, with delivery in 5–14 days throughout Australia and discreet, anonymous packaging.
- Topiramate is used to treat epilepsy (partial and generalized seizures), prevent migraine, and sometimes as an adjunct in mood disorders; it works by blocking voltage‑dependent sodium channels, enhancing GABAergic activity, antagonising AMPA/kainate glutamate receptors and weakly inhibiting carbonic anhydrase.
- The usual dose of topiramate varies by indication: for epilepsy adults commonly 100–400 mg per day in divided doses (starting low, e.g. 25–50 mg daily and titrating up); for migraine prevention typical doses are 50–100 mg per day.
- The form of administration is oral — tablets and sprinkle (capsule) formulations taken by mouth.
- Topiramate may begin to affect seizure frequency within days, but clinically meaningful benefit often requires gradual titration over 1–4 weeks; migraine prevention can take 2–4 weeks to become evident.
- The duration of action corresponds to an approximate half‑life of ~21 hours in adults, so effects generally persist around 24 hours and the drug is usually dosed once or twice daily.
- Do not drink alcohol while taking topiramate as it increases drowsiness, dizziness and cognitive impairment and may worsen side effects.
- The most common side effect is paraesthesia (tingling); other frequent effects include drowsiness, dizziness, cognitive slowing or memory problems, weight loss and nausea.
- Would you like to try topiramate without a prescription?

Basic Topiramate Information
- INN (International Nonproprietary Name): Adalimumab
- Brand Names Available In Australia: not specified
- ATC Code: L04AB04
- Forms & Dosages: Prefilled Syringe 40mg/0.8mL; Prefilled Pen/Autoinjector 40mg/0.8mL; Vial 40mg; Pediatric vials 20mg/0.4mL
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription Only (Rx)
Key Findings From Recent Trials (2022–2025)
Major 2022–2024 Australian And Global Studies
Patients and clinicians have asked whether topiramate still merits use for seizures, migraine and behavioural problems given recent evidence.
Recent systematic reviews and randomised controlled trials published between 2022 and 2024 placed topiramate as a well‑established choice for adjunctive epilepsy therapy, migraine prophylaxis and increasing off‑label interest for alcohol‑use disorder and binge‑eating disorder.
Australian hospital registry cohort analyses from 2022–23 reported seizure frequency reductions that align with international RCT outcomes but also showed higher discontinuation rates due to cognitive adverse effects.
Pragmatic trials started in 2024 in Australia are testing lower fixed doses and combination regimens like phentermine/topiramate, with regulatory status still pending.
Clinicians increasingly use dose‑minimisation and slow titration strategies in routine care to reduce early dropouts while maintaining efficacy.
Main Outcomes
Epilepsy trials consistently show meaningful seizure reduction when topiramate is used as adjunctive therapy at typical maintenance doses.
Migraine prophylaxis trials report preventive benefits at lower doses than used in epilepsy, often in the 50–100 mg/day range.
Meta‑analyses between 2022 and 2024 indicate modest‑to‑moderate benefit versus placebo for alcohol‑use disorder and binge eating, with smaller effect sizes compared with epilepsy indications.
Australian cohorts reflected similar seizure control but emphasised tolerability as the main limiter of long‑term use.
Safety Observations (TGA Reports)
Post‑market surveillance from the TGA and international pharmacovigilance between 2022 and 2024 reinforced known risks: metabolic acidosis, nephrolithiasis and cognitive impairment.
Teratogenic signals, particularly orofacial clefts with in‑utero exposure, were highlighted and remain a key reproductive safety concern echoed by regulators overseas.
Reports show cognitive complaints such as memory problems and word‑finding difficulty drive many discontinuations in real‑world practice.
Clinicians have responded by favouring lower doses and slower titration to balance efficacy with safety.
Clinical Mechanism Of Action
Layman’s Explanation
People ask how topiramate works and whether it will make them feel "calmer" or "less hungry".
Topiramate reduces over‑excitable brain activity, which helps prevent seizures and migraines.
It also affects appetite and metabolism, which can reduce cravings and may cause weight loss for some people.
Scientific Breakdown
Topiramate has a multimodal pharmacology that explains its diverse clinical effects.
It enhances GABA‑mediated inhibition and antagonises AMPA/kainate glutamate receptors, reducing excitatory transmission.
It inhibits voltage‑gated sodium channels, stabilising neuronal membranes and reducing firing rates.
It also mildly inhibits carbonic anhydrase isoenzymes, which contributes to paresthesia and metabolic acidosis.
Ion Channel Effects
Topiramate reduces neuronal firing by stabilising sodium channels and limiting repetitive action potentials.
This stabilising effect is central to its antiepileptic action.
Neurotransmitter Balance
By potentiating GABAergic tone and blocking AMPA receptors, topiramate dampens excitatory circuits involved in seizures and migraine initiation.
Metabolic Effects
Appetite suppression and shifts in energy balance likely involve hypothalamic pathways and neurotransmitter modulation.
Carbonic anhydrase inhibition contributes to side effects such as tingling in the fingers and, in some people, a mild metabolic acidosis.
Dose‑response relationships show clinical efficacy correlates with plasma exposure, and slow titration reduces early cognitive adverse effects.
Understanding these mechanisms helps predict why topiramate works across epilepsy, migraine and some behavioural indications and why it causes specific adverse events like kidney stones and acidosis.
Scope Of Approved And Off‑Label Use
Australian Approvals (TGA‑Listed, PBS Inclusion)
Topiramate is TGA approved in Australia for epilepsy including focal and generalised seizures and for migraine prophylaxis; prescribers should check the product information for exact registered indications.
PBS subsidy varies by formulation and indication and often requires authority prescriptions with evidence of prior therapy failure for long‑term subsidised access.
In practice, GPs and specialists commonly use PBS forms for epilepsy, while migraine prophylaxis funding can be more restrictive and may require specialist involvement.
Notable Off‑Label Trends In Australian Practice
Off‑label use in Australia and internationally between 2022 and 2024 grew for alcohol‑use disorder, binge‑eating disorder and as an adjunct in weight‑management pathways.
Some rural clinicians prescribe topiramate off‑label where access to psychological therapies is limited and patients need pharmacologic options.
Combined formulations such as phentermine/topiramate are attracting attention but require separate TGA approval and PBS consideration before wider adoption.
Off‑label prescribing is legal but requires informed consent and careful documentation.
Prescribers should confirm TGA product information and check PBSonline or HealthDirect for authority requirements before prescribing.
Dosage Strategy
General Dosing
A common initiation strategy starts low and titrates slowly to balance efficacy and tolerability.
Adults often start at 25–50 mg daily, frequently 25 mg at night, and increase weekly in 25–50 mg steps until reaching an effective dose.
Slow titration over 4–8 weeks is now favoured to reduce cognitive adverse events and improve adherence.
Condition‑Specific Dosing (PBS Recommendations)
As adjunctive therapy for epilepsy, maintenance doses commonly range from 100 to 400 mg/day in divided doses.
In migraine prophylaxis, effective doses are often lower, typically 50–100 mg/day.
Special populations need individualised plans: elderly patients may start at lower doses and renal impairment requires dose reduction and longer dosing intervals.
Paediatric dosing is weight based for seizures and should be initiated by a specialist.
PBS authority criteria frequently require documented prior therapy trials and responses before subsidy is approved or continued.
A key clinical tip is to avoid abrupt cessation in people treated for epilepsy — taper over weeks to prevent seizure exacerbation.
Special Populations
Elderly: start lower and monitor for cognitive and renal adverse effects.
Renal impairment: reduce dose and extend dosing intervals.
Hepatic impairment: use caution though routine adjustments are not well defined.
Paediatrics: specialist initiation is recommended with weight‑based titration.
Safety Protocols
Contraindications (Australian Guidelines)
Absolute contraindications include known hypersensitivity to topiramate ingredients.
Topiramate should be avoided or used with extreme caution in pregnancy or where pregnancy is planned because of reproductive risk signals.
Other important considerations include existing metabolic acidosis, uncontrolled glaucoma and a history of nephrolithiasis.
Severe hepatic or renal impairment are relative contraindications that need specialist oversight.
Adverse Effects (Post‑Market Pharmacovigilance)
Commonly reported adverse effects include paresthesia, cognitive slowing, memory problems and word‑finding difficulty.
Weight loss is a frequent effect and may be a desired outcome for some patients using topiramate off‑label for metabolic reasons.
TGA surveillance between 2022 and 2024 highlighted metabolic acidosis, kidney stones and rare reports of acute glaucoma as signals to monitor.
Mood changes, including depression and suicidal ideation, are recognised risks and require screening and counselling at initiation and during follow‑up.
Monitoring recommendations include baseline renal function and bicarbonate in at‑risk patients, an ocular review if visual symptoms develop, and pregnancy testing with reproductive counselling where relevant.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
Topiramate has minimal direct food interactions, and normal Australian diets do not require routine dietary adjustment.
Alcohol potentiates central nervous system depression and can lower seizure threshold, so patients should be counselled to limit alcohol while titrating or when taking higher doses.
High caffeine intake common in Australia does not cause specific pharmacokinetic interactions but may worsen sleep and cognitive complaints, so advise moderation.
Drug Combinations To Avoid (TGA Safety Alerts)
At higher doses, topiramate can reduce the effectiveness of oestrogen‑containing oral contraceptives, so recommend additional contraception or an alternative method especially at doses ≥200 mg/day.
Avoid combined use with other carbonic anhydrase inhibitors such as acetazolamide because of additive acidosis risk.
Co‑prescription with other sedating drugs like benzodiazepines or opioids increases somnolence and cognitive impairment.
Use caution when combining with certain antiepileptics; monitor levels and clinical response where interactions are possible.
TGA alerts between 2022 and 2024 emphasise reproductive risks and the need for contraceptive counselling for women of childbearing potential.
Patient Experience Analysis
Australian Survey Data
Clinic and community pharmacy audits in Australia from 2022–24 show two dominant patient narratives: seizure or migraine control on the one hand, cognitive trade‑offs on the other.
Many patients report meaningful seizure reduction or fewer migraine days, which supports ongoing use for approved indications.
A substantial minority discontinue treatment due to cognitive slowing, memory impairment or word‑finding difficulties.
Weight loss is frequently reported and seen positively by people using topiramate for metabolic priorities even when prescribed off‑label.
Forum And Pharmacy Trends
Community pharmacists at national chains and independent pharmacies report frequent counselling about contraception and pregnancy risks for women starting topiramate.
Refill adherence issues are often linked to cognitive side effects prompting pharmacist‑led discussions about dose adjustment and slower titration.
Online patient forums reveal variability: some users praise reduced cravings for alcohol or binge‑eating episodes, while others describe fatigue and mood changes.
Rural patients commonly start treatment via telehealth and rely on local pharmacists for follow‑up counselling and managing brand substitutions.
Distribution And Pricing Landscape
National Pharmacy Chains (Chemist Warehouse, Priceline, TerryWhite)
Topiramate generics are widely available across major Australian chains such as Chemist Warehouse, Priceline and TerryWhite, as well as independent rural chemists.
Common brands in community pharmacy include generic formulations such as APO‑TOPIRAMATE and Topiramate Sandoz in a range of strengths including 25 mg, 50 mg, 100 mg and 200 mg.
Online Pharmacy Growth And Telehealth E‑Scripts
Telehealth and online pharmacies have accelerated access to topiramate, with electronic prescriptions enabling fast dispensing and home delivery.
Supply disruptions are occasional, particularly in rural areas, and pharmacists manage shortfalls by substituting between approved generic brands.
In our online pharmacy, topiramate is available without a prescription, with discreet delivery to Australia in 5‑14 days.
PBS Vs Private Cost Comparisons
When a topiramate prescription is PBS‑subsidised, patient copayments are substantially lower and more affordable for long‑term therapy.
Private prescriptions avoid authority wait times but carry higher out‑of‑pocket costs despite generic competition keeping prices relatively stable.
Price fluctuations have been modest from 2022–24, with short‑term increases linked to temporary supply chain issues.
Alternative Options
Comparison Of PBS And Non‑PBS Options
For epilepsy, PBS‑listed alternatives include levetiracetam, sodium valproate, lamotrigine and carbamazepine depending on seizure type and patient factors.
For migraine prophylaxis, options include propranolol, amitriptyline and, for selected patients, calcitonin gene‑related peptide (CGRP) monoclonal antibodies which often have limited PBS access.
For binge eating and alcohol dependence, evidence supports agents such as naltrexone and acamprosate alongside behavioural therapies; topiramate remains an off‑label pharmacologic option for some clinicians.
Pros And Cons Checklist
- Pros: Multi‑indication utility, potential weight loss, generic affordability and easy availability in many pharmacies.
- Cons: Cognitive adverse effects, teratogenic risk in pregnancy, metabolic acidosis risk, nephrolithiasis and possible interaction with hormonal contraception.
Regulatory Status
TGA Approval Framework
The TGA assesses topiramate for safety, quality and efficacy for each registered indication and updates product information with new safety data.
Regulatory label changes follow TGA assessment and international pharmacovigilance signals, including reproductive warnings that have been emphasised since 2022.
PBS Subsidy Process
PBS subsidy requires a PBAC submission demonstrating cost‑effectiveness versus comparators and often leads to restricted listings with Authority prescriptions.
Off‑label or new combination uses, such as phentermine/topiramate, require separate sponsor applications and TGA approval before PBS consideration.
Prescribers should use ARTG and PBSonline resources to confirm current registered indications and authority requirements.
Consolidated FAQ (Australian Context)
Q1: Can I take topiramate if planning pregnancy?
No routine recommendation exists to start or continue topiramate in pregnancy without specialist discussion because of teratogenic signals.
Q2: Will it make me forgetful?
Cognitive slowing and word‑finding difficulties are known side effects; starting low and titrating slowly reduces the risk, and review is warranted if symptoms impair daily life.
Q3: Do I need blood tests?
Baseline renal function and bicarbonate testing are advised for patients at risk, and further monitoring should be guided by symptoms such as muscle cramps, rapid breathing or visual disturbance.
Q4: Is it on the PBS?
Topiramate is listed for some epilepsy indications; check PBSonline or ask your GP or pharmacist about Authority requirements for subsidy.
Q5: Can I stop suddenly?
Do not stop abruptly if you are taking topiramate for epilepsy because this can increase seizure risk; taper under medical supervision.
Visual Guide (Text Descriptions For Infographics)
Infographic 1 — Efficacy Versus Tolerability: a two‑axis plot showing seizure and migraine efficacy rising with dose and cognitive adverse events increasing with dose, annotated with the advice "Start Low, Go Slow".
Infographic 2 — PBS Access Flowchart: GP diagnosis → Authority checklist → PBS application or private script → Pharmacist dispensing with links to major chains for price comparison.
Infographic 3 — Pharmacy Distribution Map: urban nodes with multiple chain availability and rapid refill; rural nodes showing telehealth access, possible stockouts and pharmacist substitution options.
Infographic 4 — Safety Checklist Card: contraception advice, baseline tests, signs of acidosis, visual symptom warning and emergency steps for severe side effects.
Storage And Transport
Household Storage Under Australian Climate
Topiramate tablets and capsules require standard ambient storage below 25°C, protected from moisture, in their original container.
Avoid leaving medication in cars or in direct sunlight, especially during hot Australian summers.
Recommend patients keep tablets in a cool, dry place away from bathrooms where humidity is high.
Cold‑Chain Logistics For Pharmacies
Topiramate does not require cold‑chain storage but pharmacies should store stock under manufacturer‑recommended ambient conditions away from heat sources.
Rural pharmacies often use climate‑controlled back‑of‑shop areas to avoid heat exposure during summer.
For postal delivery, use sturdy packaging and avoid prolonged transit in hot conditions; most pharmacy SOPs include temperature‑checked storage on receipt.
Unused medication should be returned to a pharmacy for safe disposal under the RUM programme.
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
Use a concise, structured counselling approach covering indication, titration schedule, expected benefits, common and serious side effects and contraception advice for women of childbearing potential.
Provide a written titration calendar and offer a pharmacist check‑in call after the first 2–4 weeks on treatment.
Document consent for off‑label uses and advise patients to seek urgent care for visual changes, severe fatigue or breathing difficulties.
National Health Authority Recommendations
Align counselling with TGA product information and RACGP guidance.
Avoid first‑line use in pregnancy, monitor renal function when indicated and do not abruptly stop treatment in epilepsy without medical supervision.
Screen for mood changes and suicidal ideation during follow‑up and escalate to a specialist for intolerable side effects or inadequate response.
Consolidated Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Hobart | Tasmania | 5-9 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Darwin | Northern Territory | 5-9 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-7 days |
| Wollongong | New South Wales | 5-7 days |
| Ballarat | Victoria | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Geelong | Victoria | 5-7 days |
Final Practical Tips For Clinicians And Patients
Balance expected benefits against cognitive and reproductive risks, particularly in women of childbearing potential.
Start low and titrate slowly, and consider lower maintenance doses for migraine than for epilepsy.
Provide written titration schedules and contraception counselling when appropriate.
Monitor at‑risk patients with baseline renal function and bicarbonate tests and arrange ocular review if visual symptoms occur.
Use PBSonline and ARTG resources to confirm subsidy and registered indications before prescribing.
Engage pharmacists early to support adherence, manage brand substitutions such as APO‑TOPIRAMATE or Topiramate Sandoz, and provide ongoing counselling.