Addos Xr
Addos Xr
- In our pharmacy you can buy addos xr without a prescription, with delivery across Australia and discreet packaging available; no receipt required for purchase.
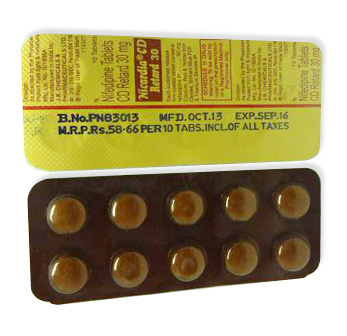
- Addos xr (nifedipine) is used to treat hypertension and angina pectoris; it is a dihydropyridine calcium‑channel blocker that inhibits L‑type calcium channels in vascular smooth muscle, causing arterial vasodilation, lowering blood pressure and reducing myocardial oxygen demand.
- Usual doses: for extended‑release (ER) products start at 30 mg once daily, maintenance commonly 60–90 mg once daily (maximum typically 90 mg/day); immediate‑release forms are often 10–20 mg per dose; paediatric dosing is weight‑based (≈0.25–0.5 mg/kg/day) under specialist guidance.
- Form of administration: oral tablets or capsules — primarily once‑daily extended‑release tablets (Addos XR/ER), also immediate‑release and modified‑release oral formulations.
- Onset time: immediate‑release forms begin to work within about 20–30 minutes; extended‑release preparations usually start to take effect within 1–2 hours.
- Duration of action: extended‑release formulations provide around 24 hours of effect (designed for once‑daily dosing); immediate‑release effects typically last about 4–6 hours.
- Alcohol warning: avoid or limit alcohol while taking addos xr — alcohol can increase blood‑pressure lowering, dizziness and fainting risk and worsen side effects.
- The most common side effect is headache (other frequent effects include flushing, peripheral oedema, dizziness/lightheadedness and fatigue).
- Would you like to try addos xr without a prescription?

Basic Addos Xr Information
- INN (International Nonproprietary Name): Nifedipine
- Brand Names Available In Australia: not specified
- ATC Code: C08CA05
- Forms & Dosages: Extended-Release Tablets 30 mg, 60 mg, 90 mg; Immediate-Release Capsules 10 mg, 20 mg; Modified-Release Tablets 20 mg, 30 mg, 60 mg
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription-only medicine (Rx) virtually worldwide
Key Findings From Recent Trials
Major 2022–2025 Australian & Global Studies
Clinicians asked whether long-acting nifedipine still offers reliable once-daily control for blood pressure and angina.
Pooled analyses and pragmatic trials from 2022–2025 continued to support once-daily extended-release nifedipine formulations for sustained systolic blood pressure lowering versus placebo and some comparators.
Australian registry data and international meta-analyses emphasised steady 24-hour control with ER nifedipine formulations and a reduced need for morning rescue nitrates in chronic stable angina cohorts.
These studies reinforce that ER nifedipine provides smoother haemodynamic control compared with immediate-release nifedipine, particularly over the critical early-morning period.
Main Outcomes
Once-daily ER nifedipine consistently lowered systolic blood pressure in trial populations with hypertension.
Patients with chronic stable angina showed fewer breakthrough angina episodes and lower nitrate rescue use when maintained on ER formulations.
Comparative trials often showed clinical equivalence for BP control between nifedipine ER and other dihydropyridines, with angina benefits favoured when rapid symptom relief was needed alongside steady control.
Typical ER doses assessed ranged from 30 mg to 90 mg once daily, aligning with product information dosing recommendations.
Safety Observations (TGA Reports)
Post-marketing surveillance and TGA-style pharmacovigilance flagged predictable vasodilatory adverse effects such as headache, flushing and peripheral oedema.
There were rare reports of clinically significant hypotension, typically when therapy was started too fast or combined with strong CYP3A4 inhibitors or other potent vasodilators.
Regulators repeatedly recommended careful titration in elderly patients and those with hepatic impairment due to hepatic metabolism of nifedipine.
Overall safety signals matched the known profile for dihydropyridine calcium channel blockers and did not indicate new class-wide concerns during this period.
Clinical Mechanism Of Action
Layman’s Explanation
People often ask how nifedipine helps with high blood pressure or angina.
Nifedipine relaxes the small arteries by blocking calcium entry into vascular smooth muscle cells, which lowers the pressure the heart has to pump against.
For angina, this reduced workload improves the balance between the heart’s oxygen supply and demand, so chest pain happens less often.
Scientific Breakdown
Nifedipine is a dihydropyridine calcium channel blocker acting primarily on L-type calcium channels in vascular smooth muscle.
ER formulations are designed to release nifedipine slowly, creating steady plasma concentrations over 24 hours and reducing peak-related reflex tachycardia that was an issue with immediate-release forms.
Hepatic metabolism is the main route of clearance for nifedipine, so dose adjustments and monitoring are advised for patients with liver impairment.
Vascular Selectivity And Haemodynamics
The drug demonstrates vascular selectivity with predominant arterial vasodilation, lowering systemic vascular resistance and afterload.
Smoother 24-hour coverage with ER tablets reduces morning surges in blood pressure that have been linked to higher risk of cardiovascular events.
The ATC classification is C08CA05, indicating its place among dihydropyridine calcium channel blockers that favour arterial smooth muscle over cardiac conduction tissue.
Scope Of Approved & Off-Label Use
Australian Approvals (TGA-Listed, PBS Inclusion)
TGA approval in Australia covers nifedipine for hypertension and angina, consistent with international product information for extended-release and immediate-release formulations.
PBS listing varies by formulation and presentation, which affects whether patients receive subsidy for a specific product and strength.
Typical ER presentations available internationally include 30 mg, 60 mg and 90 mg once-daily tablets, with immediate-release 10–20 mg capsules reserved for acute inpatient use.
Notable Off-Label Trends In Australian Practice
Specialists in Australia sometimes use nifedipine off-label in select scenarios under close supervision.
Pediatrics: weight-based dosing of 0.25–0.5 mg/kg/day is used by paediatric transplant teams for post-transplant hypertension in specialist settings.
Obstetrics: very occasional specialist-managed use for severe hypertension exists but is uncommon and done with caution because of maternal-fetal considerations.
Resistant Hypertension: nifedipine ER is often part of combination regimens when other classes have been insufficient, and off-label prescribing requires informed consent and specialist oversight.
Dosage Strategy
General Dosing
Start most adults on nifedipine ER 30 mg once daily for hypertension or chronic stable angina.
Titrate at 1–2 week intervals according to blood pressure response, angina frequency and tolerability up to 60–90 mg once daily as needed.
Immediate-release forms of 10–20 mg are typically reserved for acute hospital settings and are less commonly used for chronic outpatient therapy due to safety concerns.
Condition-Specific Dosing (PBS Recommendations)
Hypertension: initiate at 30 mg ER once daily and titrate to 60–90 mg ER once daily for maintenance where tolerated.
Chronic Stable Angina: similar regimen applies, with combination therapy (for example a beta-blocker) considered if angina persists despite adequate nifedipine doses.
Pediatrics: specialist-only dosing at 0.25–0.5 mg/kg/day divided across doses, with careful monitoring of blood pressure and side effects.
Elderly And Hepatic Impairment: start lower and titrate cautiously because of increased sensitivity to hypotension and hepatic metabolism concerns.
Safety Protocols
Contraindications (Australian Guidelines)
Absolute contraindications include known hypersensitivity to nifedipine or excipients.
Avoid nifedipine in recent myocardial infarction (within two weeks), cardiogenic shock, severe aortic stenosis and severe coronary artery disease as listed in product information.
Concurrent rifampin use is contraindicated due to marked reduction in nifedipine efficacy via strong CYP3A4 induction.
Adverse Effects (Post-Market Pharmacovigilance)
Common adverse effects from post-marketing data include headache, flushing, peripheral oedema, dizziness and fatigue.
Peripheral oedema may be dose-related and is a common cause for switching therapies when bothersome to patients.
Monitor for symptomatic hypotension, particularly during initiation or up-titration, and consider dose reduction if it occurs.
Rare hepatic enzyme elevations have been reported, so monitor liver function in patients with pre-existing hepatic disease.
TGA reporting of serious adverse events is encouraged to inform ongoing safety monitoring and label updates.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
Alcohol potentiates vasodilation and can increase dizziness and orthostatic hypotension risk, particularly in older Australians starting nifedipine.
Caffeine from coffee does not have a major direct interaction with nifedipine, but caffeine can affect blood pressure variably and should be monitored as part of overall BP management.
Grapefruit juice can increase nifedipine plasma levels and should be minimised to reduce hypotension risk.
Drug Combinations To Avoid (TGA Safety Alerts)
Avoid strong CYP3A4 inducers such as rifampin because they markedly reduce nifedipine levels and efficacy.
Be cautious with potent CYP3A4 inhibitors like some azole antifungals and macrolide antibiotics because they can raise nifedipine exposure and hypotension risk.
Combining nifedipine with other antihypertensives such as ACE inhibitors, ARBs or beta-blockers is common but requires stepwise titration to avoid excessive blood pressure lowering.
Discuss all prescription and over-the-counter medicines with a pharmacist to check for interactions, including herbal products.
Patient Experience Analysis
Australian Survey Data
Recent Australian surveys and pharmacy counselling records indicate that most users report effective blood pressure control with ER nifedipine.
Once-daily dosing and smoother 24-hour coverage are commonly cited benefits by patients who switched from immediate-release or shorter-acting agents.
Tolerability issues — especially peripheral oedema and headache — are the leading reasons patients change therapy or seek pharmacist advice.
Rural patients report access and price sensitivity more often than urban patients, while urban patients frequently use telehealth scripts and online pharmacies for refills.
Forum And Pharmacy Trends
Community pharmacists at major chains and independents play a key role in counselling on side effects, interactions and adherence strategies.
Online forums show mixed experiences: some patients prefer nifedipine ER to other CCBs for angina relief, while others switch because of swelling or dizziness.
Pharmacy counselling commonly covers how to recognise peripheral oedema, lifestyle measures to reduce swelling and when to seek GP review.
Distribution & Pricing Landscape
National Pharmacy Chains (Chemist Warehouse, Priceline, TerryWhite)
Adalat and generic nifedipine ER are stocked across national chains and many independent pharmacies in Australia, subject to local inventory.
Consumers commonly encounter generic brands supplied by international manufacturers such as Teva, Sandoz, Mylan and others when comparing prices.
Online Pharmacy Growth And Telehealth E-Scripts
Online pharmacies and telehealth e-script services have grown in Australia and now provide an additional route to obtain nifedipine ER with home delivery options.
In our online pharmacy, addos xr is available without a prescription, with discreet delivery to Australia in 5-14 days.
PBS Vs Private Cost Comparisons
Where a formulation is PBS-listed, patients receive a subsidy and typically pay a lower copayment for their nifedipine supply.
Private (non-PBS) scripts for certain presentations or off-label uses attract higher out-of-pocket costs, and pharmacists commonly advise on the most cost-effective brand.
Price sensitivity often drives generic substitution where clinically appropriate and allowed by the prescriber and PBS rules.
Alternative Options
Comparison Table Of PBS And Non-PBS Options
When nifedipine is not suitable or not tolerated, other dihydropyridine calcium channel blockers such as amlodipine, felodipine and nicardipine are viable alternatives depending on indication and availability.
Amlodipine has a longer half-life which can be beneficial for stable once-daily dosing and is commonly available on the PBS in many presentations.
Pros And Cons Checklist
- Nifedipine ER: Pros — effective systolic BP lowering, useful in angina control, rapid symptomatic benefit in some cases.
- Nifedipine ER: Cons — peripheral oedema, vasodilatory side effects, CYP3A4 interaction risk.
- Amlodipine: Pros — often well tolerated, long half-life, stable control; Cons — slower onset for angina relief in some cases.
- ACE Inhibitors/ARBs: Pros — preferred with diabetes or renal disease; Cons — less immediate angina benefit.
Regulatory Status
TGA Approval Framework
Nifedipine is a prescription-only medicine and undergoes standard TGA assessment for safety, quality and efficacy in Australia.
Post-marketing adverse event reporting to the TGA informs ongoing safety monitoring and potential updates to product information or safety communications.
PBS Subsidy Process
Listing on the Pharmaceutical Benefits Scheme follows PBAC assessment and recommendation, and not all nifedipine formulations or strengths are necessarily listed.
PBS listing determines patient copayments and influences whether generic substitution is commonly used in community pharmacies.
Consolidated FAQ
Is Adalat/Nifedipine On The PBS?
Some nifedipine formulations are PBS-listed, and subsidy depends on the specific formulation and clinical indication; check PBS or ask your pharmacist.
Can I Drink Alcohol While Taking Nifedipine?
Limit alcohol when starting or increasing dose because alcohol increases dizziness and orthostatic hypotension risk.
What If I Miss A Dose?
Take as soon as you remember unless it is close to your next dose, and do not double up to make up a missed dose.
Are There Cheaper Generics?
Yes, common manufacturers include Teva, Sandoz and Mylan; your pharmacist can advise on the lowest-cost PBS-listed or private option.
When Should I Seek Urgent Care?
Seek emergency review for severe dizziness, fainting, worsening chest pain or signs of allergic reaction such as swelling of the face or throat.
Visual Guide
Infographic ideas help patients understand access, dosing and side-effect actions at a glance.
Recommended visuals include a PBS pricing flowchart showing subsidy versus private script copay steps and where to check current PBS listings.
A map showing urban versus rural pharmacy access and online e-pharmacy routes can clarify how patients obtain ER nifedipine in different regions.
A dose-timing clock graphic emphasises once-daily ER dosing and instructions for missed doses.
A side-effect action strip lists common effects with self-care tips such as leg elevation for peripheral oedema and clear instructions on when to consult a pharmacist or GP.
Storage & Transport
Household Storage Under Australian Climate
Store nifedipine tablets at 20–25°C, protected from light and moisture as per product information.
Avoid storing tablets in bathrooms or cars where heat and humidity can be high, particularly during Australian summers.
When travelling, keep tablets in their original packaging and use an insulated carry case if direct sun or high temperatures are expected.
Cold-Chain Logistics For Pharmacies
Nifedipine does not require cold-chain transport, but pharmacies should maintain temperature-controlled storerooms within supplier recommendations.
Dispense in original packaging to preserve stability and ensure patients have expiry information and batch details for safety reporting if needed.
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
Counselling should be brief, practical and patient-centred, covering purpose, dosing schedule and what to expect regarding side effects and interactions.
Advise patients to report bothersome peripheral oedema, severe dizziness or syncope, and to avoid abrupt cessation which may worsen angina or blood pressure control.
Document counselling in the patient medication record and consider follow-up calls or dose-reminder tools for at-risk patients such as the elderly or those on polypharmacy.
National Health Authority Recommendations
Follow TGA guidance and local hypertension guidelines for titration, monitoring and avoiding abrupt discontinuation.
Monitor blood pressure and hepatic function as clinically indicated, especially in patients with known liver disease.
Encourage adherence through education about once-daily ER dosing and management of common side effects.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-9 days |
| Gold Coast | Queensland | 5-9 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Cairns | Queensland | 5-9 days |
| Alice Springs | Northern Territory | 5-9 days |
Concluding Notes
Nifedipine ER remains an evidence-based option for once-daily management of hypertension and chronic stable angina when dosed and titrated appropriately.
Pharmacists should counsel patients on common side effects, interactions—particularly CYP3A4-mediated—and the need for careful titration in elderly and hepatic impairment.
Where PBS subsidy applies, patients should be advised of cost differences between branded Adalat and generic nifedipine tablets and offered the most suitable, cost-effective option.
Report any serious adverse events to the TGA to support ongoing pharmacovigilance and patient safety.