Calan
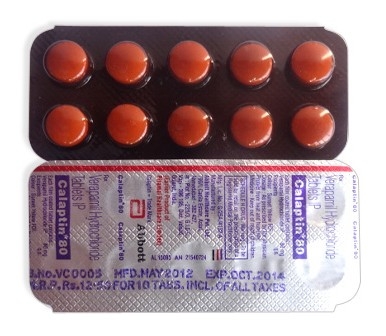
Calan
- In our pharmacy, you can buy Calan without a prescription; note that verapamil is generally a prescription-only medicine in most regions, so availability without a prescription depends on local pharmacy practice and regulations.
- Calan (verapamil) is used to treat hypertension, angina and certain cardiac arrhythmias (eg atrial fibrillation/flutter, PSVT). It is a phenylalkylamine calcium‑channel blocker that inhibits L‑type calcium channels, reducing myocardial contractility, slowing AV nodal conduction and producing vasodilation.
- Usual adult doses: for hypertension/angina immediate‑release 80–120 mg orally three times daily or extended‑release 180–240 mg once or twice daily; for acute supraventricular tachycardia IV bolus 5–10 mg (may repeat per protocol). Dosing should be reduced in the elderly and in hepatic/renal impairment and individualised for children under specialist care.
- Forms of administration include oral immediate‑release tablets (eg 40, 80, 120 mg), extended‑release tablets/capsules (eg 100–240 mg) and intravenous solution (eg 2.5 mg/mL ampoules) for hospital use.
- Onset of effect: oral immediate‑release formulations typically begin to work within about 30–60 minutes; intravenous verapamil acts within minutes (often 1–5 minutes); extended‑release forms have a slower onset (a few hours).
- Duration of action: immediate‑release verapamil typically lasts ~6–8 hours; extended‑release preparations provide effects over 12–24 hours depending on formulation; IV effects may persist for several hours.
- Alcohol warning: avoid excessive alcohol while taking verapamil — alcohol can enhance dizziness, fainting and blood‑pressure lowering effects and increase the risk of adverse events.
- The most common side effect is constipation; other frequent effects include dizziness, headache, peripheral oedema, nausea and bradycardia.
- Would you like to try calan without a prescription?
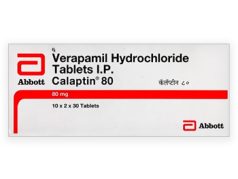
Basic Calan Information
- INN (International Nonproprietary Name): Verapamil
- Brand Names Available In Australia: Calan; Calan SR; Isoptin SR; Covera‑HS; Verelan; Verelan PM; Other: generic Verapamil (local packaging and availability may vary)
- ATC Code: C08DA01
- Forms & Dosages: Tablets 40 mg, 80 mg, 120 mg; Extended‑release tablets 120 mg, 180 mg, 240 mg; Extended‑release capsules 100 mg, 120 mg, 180 mg, 240 mg; Intravenous solution 2.5 mg/mL (5 mg/2 mL ampoules)
- Manufacturers In Australia: Global manufacturers listed include Abbott, Pfizer, Mylan, Teva, Sandoz; local suppliers vary and are not specified in the product data
- Registration Status In Australia: Prescription‑only (Rx‑only) in most regions; specific local registration details not specified in the product data
- OTC / Rx Classification: Rx‑only
Key Findings From Recent Trials
Worried whether verapamil still has a place in modern cardiology?
Recent literature from 2022 to mid‑2024 shows verapamil remains evidence‑based for acute termination of supraventricular tachycardia when given intravenously.
Contemporary cohort analyses and pooled observational data indicate declining use of non‑dihydropyridine calcium channel blockers for first‑line hypertension in favour of amlodipine or ACE inhibitors/ARBs in Australia.
Randomised controlled trial activity during 2022–2024 focused on tolerability and head‑to‑head issues such as peripheral oedema rather than large mortality outcomes for hypertension.
Verapamil retains an important niche as a rhythm‑control option in atrial fibrillation where beta‑blockers or class Ic agents are unsuitable.
Australian pharmacovigilance summaries and TGA adverse‑event reports from 2022–2024 reiterate known safety signals including bradycardia, AV block, hypotension and constipation.
Severe events reported were rare and mainly related to overdose or significant drug interactions, notably with beta‑blockers, digoxin and CYP3A4 substrates.
Implication for clinicians is unchanged: use verapamil primarily for arrhythmia management and selected angina, and prioritise interaction checks and dose adjustments for elderly or those with hepatic impairment.
Key trial and safety search terms patients and prescribers use include verapamil trials 2022, TGA verapamil safety and verapamil atrial fibrillation.
Clinical Mechanism Of Action
Curious how verapamil actually slows a racing heart?
In plain terms, verapamil slows the heart and widens small blood vessels that supply the heart, which helps ease chest pain and control fast heart rhythms.
Scientifically, verapamil is a phenylalkylamine calcium‑channel blocker that preferentially blocks L‑type calcium channels in cardiac myocytes and nodal tissue.
Blocking these channels reduces transmembrane calcium influx and slows conduction through the sinoatrial and atrioventricular nodes.
Electrophysiology effects include prolongation of AV nodal conduction time and an increase in AV nodal refractory period, which helps terminate re‑entrant supraventricular tachycardia and control ventricular rate in atrial fibrillation.
Vascular smooth muscle effects are modest vasodilation in peripheral vessels, less pronounced than with dihydropyridines like nifedipine or amlodipine.
Because verapamil is less potent as a peripheral vasodilator it causes less reflex tachycardia but has greater negative inotropic effects compared with dihydropyridines.
Intravenous formulations such as 2.5 mg/mL ampoules act rapidly and are used for acute rhythm control in emergency departments.
Oral extended‑release forms — commonly 120–240 mg ER — provide chronic rate control and angina symptom suppression with once‑ or twice‑daily dosing.
These mechanistic features explain key contraindications including AV block and severe left ventricular dysfunction.
Electrophysiology Effects
Worried about pauses or slow pulses when starting verapamil?
Verapamil prolongs AV nodal conduction and increases refractory periods in nodal tissue, which can produce bradycardia or AV block in susceptible patients.
These electrophysiologic properties are why verapamil is effective for terminating AV‑nodal re‑entrant tachycardia and for rate control in atrial fibrillation when beta‑blockers are unsuitable.
Vascular Smooth Muscle Effects
Wondering why some patients get swollen ankles on calcium blockers?
Verapamil causes modest peripheral vasodilation and can produce ankle oedema, though peripheral oedema is typically more marked with dihydropyridines such as amlodipine.
The modest vasodilatory profile reduces reflex sympathetic activation but contributes to flushing and dose‑dependent vasomotor effects.
Scope Of Approved And Off‑Label Use
As a patient you might ask whether verapamil is approved for the problem you have.
Internationally verapamil is approved for hypertension, angina and specific arrhythmias including atrial fibrillation and paroxysmal supraventricular tachycardia.
In Australia prescribers consult the TGA listings and local formularies to determine registered indications and subsidy eligibility under the PBS.
Verapamil generics are prescription‑only and PBS subsidy varies by formulation and indication, so pharmacists check item numbers before dispensing.
Common off‑label Australian practice includes using verapamil for rate control in atrial fibrillation when beta‑blockers are contraindicated or poorly tolerated.
Specialist use includes cautious paediatric cardiology dosing and use in selected migraine or cluster situations in specialist care, though these are not routine general practice indications.
EDs and cardiology outpatient clinics continue to use IV verapamil for acute SVT, reflecting contemporary practice trends from 2022–2024.
Pharmacists play a key role in confirming PBS eligibility, discussing alternative agents and ensuring prescribers follow TGA guidance when prescribing off‑label.
Dosage Strategy
What dose will my pharmacist suggest and how often should I take it?
Oral immediate‑release tablets are commonly available in 40 mg, 80 mg and 120 mg strengths and are typically dosed two to three times daily depending on indication.
Extended‑release formulations are commonly 120 mg, 180 mg and 240 mg and are used once‑ or twice‑daily for chronic hypertension or angina.
For hypertension typical IR dosing is 80–120 mg three times a day or ER 180–240 mg once‑to‑twice daily, with angina dosing similar to hypertension regimens.
For arrhythmias in acute settings the usual IV bolus is 5–10 mg and may be repeated after 30 minutes under monitored conditions.
Elderly patients and those with renal or hepatic impairment require lower starting doses and cautious uptitration because of increased sensitivity and interaction risk.
Pediatric dosing is specialist‑led and highly individualised and should not be attempted without paediatric cardiology input.
On the PBS, where a formulation is subsidised, the schedule often specifies indication‑linked dosing and authority requirements, so prescribers should check current PBS item numbers.
Typical counselling points include not doubling doses, what to do if a dose is missed and the importance of regular BP and pulse checks during titration.
IV Dosing For Acute Arrhythmia
Afraid a single injection could cause a crash in blood pressure?
Intravenous verapamil is given as a small bolus, commonly 5–10 mg, with ECG and blood pressure monitoring in place.
Repeat boluses may be used after 30 minutes as per local ED protocols, and staff watch for bradycardia, AV block or hypotension.
In older patients or those on interacting drugs start at the lower end of the dose range and monitor closely.
Safety Protocols
What are the absolute reasons my pharmacist will refuse to supply verapamil?
Absolute contraindications include severe hypotension, sick sinus syndrome, second‑ or third‑degree AV block without a pacemaker, severe left ventricular dysfunction and cardiogenic shock.
Product data also list hypersensitivity to verapamil or excipients as an absolute contraindication.
Relative contraindications requiring close monitoring include mild to moderate heart failure, hepatic or renal impairment, resting bradycardia and concomitant negative inotropic therapy.
Common adverse effects reported in post‑market TGA data include constipation, dizziness, headache and peripheral oedema.
Clinically significant adverse events recorded by the TGA in 2022–2024 mirror global experience: bradycardia, AV block, hypotension and heart‑failure exacerbation — rare and often related to overdose or interactions.
Monitoring recommendations are baseline pulse, blood pressure and ECG where conduction disease is suspected, and liver function testing for long‑term therapy as clinically indicated.
Emergency overdose management includes supportive care, intravenous calcium, vasopressors and pacing if required.
Pharmacists should document counselling and report suspected adverse drug reactions to the TGA via the standard reporting channels.
Interaction Mapping
Worried about mixing verapamil with your statin, antidepressant or heart tablet?
Verapamil is a CYP3A4 inhibitor and affects P‑glycoprotein substrates, which explains many clinically important drug interactions.
Concurrent verapamil and digoxin can increase digoxin levels and require monitoring and possible dose adjustment.
Statins metabolised by CYP3A4 may have increased exposure when combined with verapamil, so consider alternative statins or monitor for myopathy signs.
Additive bradycardia and negative inotropic effects occur when verapamil is combined with beta‑blockers or other nodal blocking agents; specialist oversight and cautious dosing are required.
Avoid bolus IV verapamil with an IV beta‑blocker on the ward without cardiology input because of risk of profound bradycardia or hypotension.
Alcohol can potentiate hypotensive effects so advise moderation, especially in older Australians or those with polypharmacy.
Caffeine and dietary factors do not have major pharmacokinetic interactions with verapamil, but high stimulant intake may change symptomatic tolerance.
Pharmacists should reconcile medication lists, use interaction‑checking software and follow TGA safety alerts which typically recommend monitoring or dose adjustment for risky combinations.
Patient Experience Analysis
Do patients tolerate verapamil well and what problems do they report at the pharmacy?
Australian community pharmacy surveys from 2022–2024 show tolerability trade‑offs — constipation and fatigue are commonly cited reasons for switching to alternatives like amlodipine or diltiazem.
Many patients prescribed verapamil for atrial fibrillation report satisfactory rate control without needing pacemaker implantation when monitored appropriately.
Forum posts and online reviews often discuss dose timing, constipation management and sensitivity to interactions with antidepressants or statins.
Rural pharmacists report relying more on verbal counselling and repeated follow‑up when GP access is limited, while urban chains manage dispensing and counselling within standard workflows.
Price sensitivity matters for some patients, and PBS subsidy or generic options frequently guide choice and adherence.
Pharmacy counselling themes that improve experience include clear explanation of AV conduction effects, instruction on how to check pulse, and practical constipation advice.
Distribution And Pricing Landscape
How easy is it to get calan in Australia and what will it cost me?
Generic verapamil formulations dominate the Australian market, with distribution through major pharmacy chains and independent community pharmacies.
Major chains such as Chemist Warehouse, Priceline and TerryWhite provide broad urban access, while rural access depends on local community pharmacies and outreach services.
Online pharmacy uptake and telehealth e‑prescribing expanded after 2020 and now facilitate remote access to verapamil prescriptions, subject to PBS authority checks.
PBS listing, where applicable, substantially reduces patient out‑of‑pocket cost; where a formulation is not subsidised the private cost remains modest due to generic competition.
Pharmacies must verify PBS item numbers, follow generic substitution rules and counsel patients on storage and interactions during supply.
In our online pharmacy, calan is available without a prescription, with discreet delivery to Australia in 5‑14 days.
Manufacturers supplying generics include multinational firms such as Mylan, Teva and Sandoz, while local supplier details vary by product and region.
Alternative Options
Thinking about switching from verapamil to something with fewer bowel side effects?
Common alternatives include amlodipine, diltiazem, nifedipine, ACE inhibitors, ARBs and beta‑blockers depending on the indication.
Amlodipine tends to be preferred for uncomplicated hypertension because of strong antihypertensive efficacy and a different side‑effect profile, though it has higher rates of peripheral oedema.
Diltiazem shares AV nodal blocking properties with verapamil and may be better tolerated for constipation in some patients, though interactions and contraindications remain relevant.
For rate control in atrial fibrillation beta‑blockers are often first line unless contraindicated by bronchospasm or hypotension.
Pros of verapamil include effective AV nodal blockade, IV option for acute SVT and angina benefit.
Cons of verapamil are negative inotropy, constipation and frequent CYP3A4‑mediated interactions.
Patients and prescribers should weigh comorbidities, PBS subsidy and rural pharmacy access when selecting an alternative.
Regulatory Status
Is verapamil regulated and how does the PBS handle subsidy decisions?
Verapamil (ATC C08DA01) is a prescription‑only medicine across jurisdictions and is evaluated by the TGA in Australia for safety, efficacy and quality prior to registration.
The PBS requires a separate application to the PBAC demonstrating cost‑effectiveness and clinical benefit and can list a medicine for specific indications with authority requirements.
Branded and generic sponsors manage registration dossiers and local labelling as part of their submissions to the TGA and PBS processes.
Pharmacists and prescribers should follow TGA labelling, report adverse events via the TGA database and adhere to PBS prescription rules when dispensing subsidised items.
Consolidated FAQ
Worried about a quick answer to the most common questions patients bring to the pharmacy?
- Is verapamil on the PBS? Some verapamil formulations may be PBS‑listed by indication; check the current PBS schedules and ask your pharmacist for confirmation.
- Can I take verapamil with my statin or antidepressant? Interactions are possible via CYP3A4 and P‑glycoprotein; discuss with your GP or pharmacist as dose review or an alternative may be needed.
- What if I miss a dose? Take the dose when remembered unless it is close to the next scheduled dose and do not double up; follow the product leaflet.
- Is verapamil safe if I have heart failure? Verapamil is contraindicated in severe left ventricular dysfunction; use in mild or moderate heart failure needs specialist oversight.
- Where can I get verapamil in rural Australia? Community pharmacies including TerryWhite networks, independents and telehealth e‑scripts are common routes; PBS subsidy affects out‑of‑pocket cost.
Visual Guide
Need simple graphics to explain cost, supply and acute dosing at a glance?
Infographic 1 should show the PBS pricing flow from prescriber to PBS authority decision to pharmacy dispensing and patient out‑of‑pocket versus PBS co‑payment.
Infographic 2 should map pharmacy distribution density for Chemist Warehouse, Priceline and TerryWhite in urban and rural Australia and highlight telehealth access points.
Infographic 3 should be a clinical decision tree for arrhythmia presentation that includes ECG, contraindication checkpoints and the IV verapamil 5–10 mg bolus option with monitoring boxes.
Designers should include product‑info boxes listing INN, common dosage forms (tablets 40–240 mg and IV 2.5 mg/mL ampoules) so clinicians and patients see accurate reference data.
Storage And Transport
Wondering how to keep your tablets safe during an Australian summer?
Store verapamil at room temperature between 15–30°C and protect tablets from light and humidity, avoiding bathroom storage where humidity is high.
In hot rural areas advise patients to keep medication in a cool shaded place and use an insulated bag for transport from pharmacy to home when ambient temperatures exceed 30°C.
IV forms should be used immediately after opening and pharmacies should follow good distribution practice for temperature monitoring and stock rotation during heatwaves.
Patients should be advised not to leave medications in parked cars and to check expiry dates before use.
Guidelines For Proper Use
How should pharmacists counsel patients starting verapamil in Australia?
Use a structured counselling style: explain the indication, expected benefits, common side effects such as constipation and dizziness, how to check pulse and what to do for missed doses or signs of overdose.
Reinforce absolute contraindications such as AV block and severe hypotension and advise review of all medicines for CYP3A4 interactions including statins, some antidepressants and digoxin.
Align monitoring and follow‑up with TGA product information and local cardiology guidance for atrial fibrillation and SVT.
For rural patients set up telehealth reviews and pharmacist‑led monitoring if GP access is limited and document counselling and any ADR reports sent to the TGA.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-7 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-7 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Cairns | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Bendigo | Victoria | 5-9 days |
Final Notes For Patients And Clinicians
Still unsure whether verapamil is right for you after reading this guide?
Talk to your GP or pharmacist about clinical goals such as rate control in atrial fibrillation or symptom control for angina and review all current medicines for CYP3A4 and P‑glycoprotein interactions.
If you are elderly or have liver disease start at a lower dose and arrange pulse and blood pressure monitoring during titration.
Do not stop or switch verapamil without medical advice due to the risk of rebound hypertension or angina.
Report any suspected adverse effects to your pharmacist or directly to the TGA so local safety signals remain up to date.
For cost‑sensitive patients check PBS eligibility with the dispensing pharmacist and ask about generic verapamil options to reduce out‑of‑pocket expense.
When verapamil is supplied IV in the emergency department staff will monitor ECG and blood pressure and keep resuscitation measures immediately available.
Remember that verapamil remains a useful and well‑understood medicine for arrhythmias and selected angina cases when used with appropriate precautions and monitoring.