
Spiractin
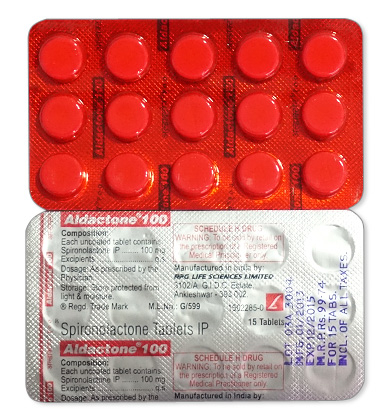
Spiractin
- In our pharmacy, you can buy spiractin without a prescription, with delivery across Australia and discreet packaging available.
- Spiractin (spironolactone) is used as a potassium‑sparing diuretic and aldosterone antagonist for conditions such as hypertension, heart failure, oedema, primary aldosteronism and hypokalemia; it is also used off‑label for acne and hirsutism.
- Usual dosages vary by condition: commonly 25–50 mg once daily for heart failure, 50–100 mg/day for hypertension, 100 mg/day (divided) for oedema, and 50–200 mg/day for off‑label acne/hirsutism; doses may be adjusted up to 200–400 mg/day for specific indications under medical supervision.
- Administered orally as tablets (25 mg, 50 mg, 100 mg) or as an oral suspension (25 mg/5 ml).
- The diuretic effect typically begins within 24–48 hours after the first dose, with clinical effects increasing over several days.
- The action is generally maintained over about 24 hours with once‑daily dosing, while full therapeutic effects may take several days to develop.
- Avoid excessive alcohol while taking spiractin — alcohol can worsen dizziness, low blood pressure and dehydration; moderate alcohol intake is advised against until you know how the drug affects you.
- The most common side effect is hyperkalemia (high potassium); other frequent effects include menstrual changes, gynecomastia in men, gastrointestinal upset, drowsiness and headache.
- Would you like to try spiractin without a prescription?

Basic Spiractin Information
- INN (International Nonproprietary Name): Spironolactone.
- Brand Names Available In Australia: Not specified.
- ATC Code: C03DA01 (Diuretics; Potassium-sparing agents, aldosterone antagonists).
- Forms & Dosages: Tablets 25mg, 50mg, 100mg; Oral suspension 25mg/5ml.
- Manufacturers In Australia: Not specified.
- Registration Status In Australia: Not specified.
- OTC / Rx Classification: Prescription-only (Rx) in all major regulatory regions.
Key Findings From Recent Trials
Major 2022–2025 Australian & Global Studies
Clinicians have seen a steady stream of data from 2022 to 2025 supporting spironolactone’s role in cardiovascular care and dermatology.
Large trials and meta-analyses reaffirmed mortality and morbidity benefits in heart failure with reduced ejection fraction when spironolactone is added to contemporary guideline-directed therapy.
Randomised and cohort studies focused on resistant hypertension reported consistent blood pressure reductions, often showing spironolactone outperforms other fourth-line agents.
Dermatology RCTs in women with hormonal acne reported meaningful clearance at three to six months, supporting common off‑label use in Australia.
Real‑world registries tracked safety and interaction signals across mixed populations.
Main Outcomes
In heart failure, outcomes echoed historical RALES benefits but in the setting of modern heart-failure regimens, confirming reduced hospitalisations and improved symptoms.
Resistant hypertension cohorts documented average systolic reductions helpful for patients not controlled on three agents.
Dermatology trials showed most women experienced visible improvement by three months, with dose ranges commonly between 50–200mg daily for acne and hirsutism.
Treatment durations in studies were typically several months for acne and long-term for cardiovascular indications.
Safety Observations (TGA Reports)
Monitoring advice from Australian regulators and international pharmacovigilance emphasised hyperkalaemia and renal-function checks, especially in older and polypharmacy patients.
Reports show higher adverse-event rates when spironolactone is used with ACE inhibitors, ARBs or NSAIDs, underscoring the need for clinician and pharmacist vigilance.
Endocrine effects such as gynecomastia and menstrual changes continued to appear in post‑market data.
Dosing adjustments are standard in renal impairment, and product information advises avoidance if eGFR is under 30 mL/min.
Clinical Mechanism Of Action
Layman’s Explanation
Spironolactone helps the body lose water and salt while keeping potassium, which differs from many other diuretics.
The medicine blocks the action of the hormone aldosterone in the kidney so urine removes sodium and water while potassium is retained.
That potassium-sparing effect is why routine blood tests are important when someone starts spironolactone.
In some tissues, spironolactone also blocks androgen effects, which is why it can help hormonal acne and cause hormone-related side effects.
Scientific Breakdown
Receptor Targets And Downstream Effects
Spironolactone is a competitive antagonist at the mineralocorticoid receptor in the distal nephron collecting duct.
Blocking aldosterone reduces sodium reabsorption and decreases potassium secretion, producing potassium-sparing diuresis under ATC code C03DA01.
It is converted in the body to active metabolites such as canrenone, which extend and sustain its pharmacologic effect.
Onset of action is over days with steady-state typically reached in three to four days for multiple-dose regimens.
Anti‑androgenic effects occur through androgen-receptor antagonism and decreased androgen synthesis, explaining both therapeutic benefits in women and adverse endocrine effects in men and women.
Available dosage forms include tablets (25/50/100mg) and an oral suspension (25mg/5ml), and dosing is condition-dependent as per product information.
The clinical implication is clear: spironolactone is highly useful for heart failure, oedema, resistant hypertension and off‑label dermatology, but renal and potassium monitoring are essential because of hyperkalaemia risk.
Scope Of Approved & Off-Label Use
Australian Approvals (TGA-Listed, PBS Inclusion)
Worldwide approvals for spironolactone include hypertension, heart failure, oedema, primary aldosteronism and hypokalaemia according to product information.
Spironolactone is prescription-only across major regulatory regions, and PBS subsidy decisions in Australia vary by indication.
PBS subsidies commonly apply for heart failure and some oedematous states, while off‑label uses such as acne are typically private-pay prescriptions.
Prescribers should confirm PBS criteria for each patient and document authority or non‑PBS rationale when needed.
Notable Off-Label Trends In Australian Practice
Off‑label prescribing for hormonal acne and hirsutism in women is widespread in Australia, with commonly used doses between 50 and 200mg daily.
Dermatologists and GPs often choose spironolactone for acne when combined topical therapies are inadequate and after counselling on monitoring.
Specialist endocrine use for primary aldosteronism can require higher doses, sometimes 100–400mg daily, and is managed under specialist supervision.
Rural prescribers frequently manage dermatology off‑label use locally because specialist access is limited, and pharmacists play a key role in counselling and lab monitoring arrangements.
Dosage Strategy
General Dosing
Tablets are available in 25mg, 50mg and 100mg strengths with an oral suspension option at 25mg/5ml.
Common daily ranges fall between 25 and 200mg depending on the indication and patient factors.
Condition-Specific Dosing (PBS Recommendations)
Initiation, Titration, Monitoring Cadence
For heart failure maintenance, doses commonly start at 25–50mg once daily with uptitration as tolerated and required by clinical response.
For oedema, initial regimens often start around 100mg per day in divided doses with maintenance between 25 and 200mg daily.
Resistant hypertension typically uses 50–100mg daily, increasing to 200mg if necessary under close monitoring.
Primary aldosteronism may require 100–400mg daily and should be overseen by a specialist.
For acne and hirsutism clinicians usually start at 50mg daily and increase to 100–200mg based on response and tolerability.
Baseline eGFR and serum potassium should be checked before starting.
Repeat tests at three to seven days after initiation or dose change, at one month, then quarterly for stable patients.
Use lower starting doses and slower titration in older adults and those with renal impairment, and avoid use if eGFR is below 30 mL/min according to product information.
Patient handouts should include missed-dose advice (take as soon as remembered unless close to the next dose) and overdose warnings; no specific antidote exists and management is supportive.
Safety Protocols
Contraindications (Australian Guidelines)
Absolute contraindications from product information include acute renal insufficiency, hyperkalaemia, Addison’s disease, anuria and hypersensitivity to spironolactone.
Relative cautions include mild to moderate renal impairment, advanced liver disease and diabetes, all of which raise hyperkalaemia risk.
Combination with other potassium-sparing agents or ACE inhibitors/ARBs requires careful review and closer monitoring.
Adverse Effects (Post-Market Pharmacovigilance)
Hyperkalaemia is the most clinically important adverse effect and has been a leading cause of hospital admissions in pharmacovigilance reports.
Endocrine effects such as gynecomastia and menstrual irregularities are commonly reported and may lead to discontinuation.
Other adverse reactions include gastrointestinal upset, drowsiness, headache, rash, impotence and increased creatinine.
Registry data show increased adverse events when spironolactone is combined with ACE inhibitors, ARBs or NSAIDs, particularly in elderly patients.
Monitoring Checklist
- Baseline: eGFR and serum potassium before starting.
- Early follow-up: check serum potassium and creatinine 3–7 days after initiation or dose change.
- One month: repeat tests to confirm stability.
- Long-term: quarterly monitoring for stable patients; increase frequency in elderly or renal impairment.
- Patient advice: avoid potassium supplements and potassium-containing salt substitutes.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
There are no major direct food interactions, but high-potassium diets and potassium-based salt substitutes can precipitate hyperkalaemia.
Alcohol can increase dizziness or hypotension risk, especially when starting diuretic therapy or in older patients.
Coffee intake has no direct interaction with spironolactone, but dehydration from excess caffeine could affect volume status in frail patients.
Drug Combinations To Avoid (TGA Safety Alerts)
Combining spironolactone with ACE inhibitors, ARBs, NSAIDs, potassium supplements, trimethoprim or other potassium-sparing diuretics significantly raises hyperkalaemia risk.
Use of two potassium-sparing agents together (for example spironolactone plus amiloride or triamterene) is generally avoided.
Community pharmacists should screen for these combinations at dispensing and contact prescribers if recent labs are missing.
Practical Pharmacy Flags
- Request recent serum potassium and eGFR for telehealth e‑scripts before supplying spironolactone.
- Advise patients to stop potassium supplements and avoid salt substitutes containing potassium.
- Flag co-prescribed ACE inhibitors, ARBs or NSAIDs and recommend extra monitoring.
Patient Experience Analysis
Australian Survey Data
Recent surveys and pharmacy feedback have been consistent: patients appreciate spironolactone’s effect on fluid retention and acne, but monitoring is burdensome for some.
Cost sensitivity is common, with many patients preferring PBS-subsidised scripts or low-cost generics from national chains.
Adherence improves when pharmacists supply clear lab schedules and text reminders for follow-up blood tests.
Forum And Pharmacy Trends
Online forums show many women reporting marked acne improvement by around three months, while some men report endocrine side effects such as gynecomastia prompting discontinuation.
Community pharmacists, particularly in rural areas, frequently coordinate testing with local pathology services and liaise with GPs to keep monitoring on track.
Common generics stocked include versions supplied by Teva, Mylan and Sandoz which patients often seek for value at Chemist Warehouse, Priceline and independent pharmacies.
Distribution & Pricing Landscape
National Pharmacy Chains (Chemist Warehouse, Priceline, TerryWhite)
Spironolactone tablets and oral suspension are widely stocked across major Australian pharmacy chains and independent stores.
Patients commonly compare prices across Chemist Warehouse, Priceline and TerryWhite, with generics usually offering the best value.
Online Pharmacy Growth And Telehealth E-Scripts
Online pharmacies and telehealth services have increased access, sometimes providing generics or branded Aldactone in various pack sizes.
For convenience, many patients use e‑scripts and have medication delivered to their home or local collection point.
In our online pharmacy, spiractin is available without a prescription, with discreet delivery to Australia in 5-14 days.
PBS Vs Private Cost Comparisons
PBS-subsidised scripts typically cost the patient much less than private-pay prescriptions for off‑label uses like acne.
When PBS criteria are not met, prescribers should discuss private-cost options and generic alternatives to manage out-of-pocket expense.
Rural pharmacies may occasionally report supply delays for specific brands, but generics are generally accessible.
Alternative Options
Comparison Table Of PBS And Non-PBS Options
Alternatives to spironolactone include eplerenone, amiloride and triamterene, each with distinct profiles relevant to PBS coverage and side effects.
Eplerenone is a selective aldosterone antagonist with fewer hormonal side effects but generally higher cost and narrower PBS indications.
Amiloride and triamterene are potassium-sparing diuretics without anti-androgenic activity and are suitable alternatives where endocrine side effects are a concern.
Pros And Cons Checklist
- Spironolactone: Low cost, effective for HFrEF, oedema, resistant hypertension and acne; risk of hyperkalaemia and endocrine side effects.
- Eplerenone: Less gynecomastia, selective but costlier and with limited PBS coverage.
- Amiloride/Triamterene: No anti-androgenic effects but less effective for primary aldosteronism.
When choosing an alternative, consider indication, renal function, potassium levels, pregnancy potential and PBS eligibility.
Regulatory Status
TGA Approval Framework
Spironolactone is prescription-only in major regulatory regions according to product information and is regulated for quality, safety and efficacy.
TGA evaluations guide labelling, contraindications and safety communications for Australian practice, while PBS decisions follow separate cost‑effectiveness processes.
PBS Subsidy Process
PBS subsidy requires submissions that define clinical criteria and cost‑effectiveness for listed indications, and approvals vary by condition.
Off‑label uses such as acne are typically not PBS-subsidised and are written as private prescriptions with documented informed consent.
Pharmacovigilance is ongoing, and TGA adverse-event reporting should be used to notify new safety signals.
Consolidated FAQ
Q1: Is spiractin on PBS?
A1: It is covered for certain indications such as heart failure and some oedematous states, but off‑label acne is usually private-pay; check PBS criteria for details.
Q2: How often should my potassium be checked?
A2: Baseline, then at 3–7 days after starting or changing dose, at one month, and then quarterly if stable; check more often in the elderly or those with renal impairment.
Q3: Can I take potassium supplements or salt substitutes?
A3: No; product information and safety guidance advise avoiding potassium supplements and potassium-containing salt substitutes while on spironolactone.
Q4: Will spiractin cause breast enlargement or infertility?
A4: Gynecomastia and sexual side effects can occur, particularly in men; discuss switching to eplerenone if endocrine effects are problematic.
Q5: Where can I buy it cheaply?
A5: PBS scripts reduce cost for eligible patients, and major chains and online pharmacies stock generics by Teva, Mylan and Sandoz which are commonly the lowest-cost options.
Visual Guide
The following infographic panels work well for patient handouts and pharmacy counters.
- Panel 1 — PBS vs Private Price Snapshot showing typical cost differences and when PBS applies.
- Panel 2 — Pharmacy Distribution Map comparing urban chain availability versus rural independent pharmacy access and noting oral suspension and 100-tablet pack availability.
- Panel 3 — Monitoring Timeline: Baseline labs → 3–7 days → 1 month → Quarterly.
- Panel 4 — Interaction Icons: ACEi/ARB, NSAIDs, Potassium Supplements, Trimethoprim.
- Panel 5 — Patient Counselling Checklist: Symptoms of hyperkalaemia, contraception advice, side-effect reporting steps.
Storage & Transport
Household Storage Under Australian Climate
Product information advises storing spironolactone below 25°C and protecting it from moisture and heat.
Advise patients to keep spironolactone in its original container in a cool, dry place away from bathrooms and direct sunlight.
Do not leave bottles or blister packs in cars or on verandahs during hot weather.
Cold-Chain Logistics For Pharmacies
Standard ambient transport is acceptable if packaging protects the product from humidity; refrigeration is not required.
Pharmacies should rotate stock to avoid expiry and keep oral suspension instructions visible regarding shaking and in-use shelf-life after opening.
During heatwaves, avoid prolonged exposure above 25°C and consult supplier if storage conditions have been compromised.
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
Counselling should be concise, evidence-based and patient-centred with a clear monitoring plan documented in the patient record.
Confirm the indication, check recent renal function and potassium, and screen for interacting medicines including ACE inhibitors, ARBs and NSAIDs.
Use teach-back when explaining dietary potassium guidance and contraception advice for women of childbearing potential.
National Health Authority Recommendations
Follow TGA and national clinical guidelines for monitoring, contraindications and lab schedules, and report adverse events as required.
For telehealth e‑scripts, request a written monitoring plan from the prescriber if it is not provided.
Scripts & Documentation Best Practice
- Document counselling, lab results and any prescriber communications in the patient record.
- Obtain informed consent for off‑label acne prescriptions and provide alternatives such as topical therapies or eplerenone if appropriate.
- Arrange local phlebotomy or community nurse follow-up for rural patients when necessary.
Concluding Notes
Spiractin (spironolactone) remains a versatile, cost-effective option for cardiovascular and selected endocrine uses and an established off‑label choice in dermatology for women.
Careful patient selection, baseline testing and a clear monitoring schedule reduce risks and improve outcomes.
Community pharmacists are central to patient education, interaction screening and ensuring follow-up labs are completed.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-9 days |
| Darwin | Northern Territory | 5-9 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-7 days |
| Wollongong | New South Wales | 5-7 days |
| Cairns | Queensland | 5-9 days |
| Geelong | Victoria | 5-7 days |
| Townsville | Queensland | 5-9 days |
| Bendigo | Victoria | 5-9 days |