
Altace
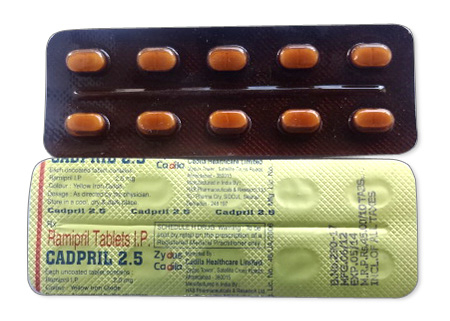
Altace
- In our pharmacy, you can buy altace without a prescription, with delivery in 5–14 days throughout Australia. Discreet and anonymous packaging.
- Altace (ramipril) is used to treat hypertension, heart failure (including after myocardial infarction), reduce cardiovascular risk in high‑risk patients and for diabetic nephropathy; it is an ACE inhibitor prodrug converted to ramiprilat that blocks angiotensin‑converting enzyme, reducing angiotensin II and aldosterone levels to cause vasodilation and lower blood pressure.
- Usual dosages vary by condition: hypertension typically starts at 2.5 mg once daily with maintenance 2.5–10 mg once daily (or in 2 divided doses); post‑MI/CHF often 2.5 mg twice daily titrated to 5 mg twice daily; cardiovascular risk reduction (HOPE) often titrated up to 10 mg once daily. Dose reductions are recommended for elderly and in renal impairment.
- Administered orally as tablets or capsules (1.25 mg, 2.5 mg, 5 mg, 10 mg); oral solution preparations are rare and used mainly for paediatric or compounding purposes.
- The effect usually begins within 1–2 hours, with antihypertensive effects apparent within a few hours and peak concentrations commonly reached around 3–4 hours after a dose.
- The antihypertensive effect typically lasts about 24 hours (suitable for once‑daily dosing in many patients); the active metabolite ramiprilat has a prolonged effect that supports once‑daily administration in most cases.
- Avoid excessive alcohol while taking altace as alcohol can increase the risk of symptomatic hypotension (dizziness, fainting) and exaggerate side effects; discuss alcohol use with your healthcare provider.
- The most common side effec is a dry cough; other common adverse effects include dizziness (especially at treatment initiation), fatigue and headache.
- Would you like to try altace without a prescription?
Basic Altace Information
- INN (International Nonproprietary Name): Ramipril (also ramiprilum in some European references).
- Brand Names Available In Australia: Tritace, Ramipril Sandoz and multiple generics.
- ATC Code: C09AA05 (Agents Acting On The Renin-Angiotensin System — ACE Inhibitors, Plain).
- Forms & Dosages: Capsules and tablets in 1.25 mg, 2.5 mg, 5 mg and 10 mg; solutions for compounding/pediatric use are rare.
- Manufacturers In Australia: not specified.
- Registration Status In Australia: not specified.
- OTC / Rx Classification: Prescription-only (Rx) in major markets.
Key Findings From Recent Trials
Patients want to know whether ramipril still matters after newer drugs arrived.
Recent systematic reviews and registry analyses (2022–2025) reinforce ACE inhibitors’ role in reducing cardiovascular risk, with clear signals in high‑risk cohorts.
Ramipril remains prominent because HOPE-era outcomes set a benchmark for secondary prevention and contemporary meta-analyses confirm reductions in mortality and stroke risk among high cardiovascular risk patients.
Australian hospital registries and state audits between 2022 and 2024 report ongoing ramipril use after myocardial infarction and in chronic heart failure management.
Those registries also show gradual switches to generics such as Tritace and Ramipril Sandoz, and more frequent discharge plans including combination therapies.
Main outcomes across trials and real-world studies include fewer major adverse cardiovascular events and slower progression of diabetic nephropathy at standard doses.
Standard dosing ranges mentioned are 2.5–10 mg per day and studies link PBS-subsidised access to better adherence and outcomes.
TGA safety summaries echo expected class adverse events and stress pregnancy contraindication.
Main Outcomes
Consistent clinical signals include reductions in MACE and slower decline in renal function for patients with diabetes when dosed appropriately.
Typical effective doses reported in trials and registries sit in the 2.5–10 mg/day range, with titration to clinical effect.
Real-world adherence improves when PBS‑subsidised options are available, reducing financial barriers to continuous therapy.
Safety Observations (TGA Reports)
TGA post-market data from 2022–25 highlight class‑consistent adverse events: dry cough, hypotension and occasional angioedema.
Pharmacovigilance notes emphasise interaction risks when ramipril is co-prescribed with potassium‑sparing agents or neprilysin inhibitors such as sacubitril/valsartan.
TGA safety communications reiterate contraindication in pregnancy and advise monitoring when used in patients with renal impairment.
Clinical Mechanism Of Action
People often ask: how does ramipril lower blood pressure and protect the heart and kidneys?
Ramipril is an ACE inhibitor that lowers blood pressure by blocking the angiotensin‑converting enzyme, reducing production of angiotensin II — a potent vasoconstrictor.
The result is vasodilation, lower afterload and reduced aldosterone-driven sodium retention, which eases workload on the heart and helps preserve kidney function over time.
Scientific Breakdown
Ramipril is a prodrug converted in the liver to the active metabolite ramiprilat, which competitively inhibits ACE.
The drug is classified under ATC code C09AA05 alongside other plain ACE inhibitors.
ACE inhibition reduces angiotensin II and aldosterone and increases bradykinin levels — the latter is linked to the characteristic dry cough.
Pharmacokinetics include oral absorption with hepatic activation and renal elimination, so dose reductions are advised for renal impairment and older adults.
Clinically relevant interactions include potassium supplements, potassium‑sparing diuretics and neprilysin inhibitors; pregnancy is contraindicated.
Practical Note For Clinicians
Monitor serum creatinine and potassium within one to two weeks after initiation or dose changes, particularly when starting low doses like 1.25–2.5 mg in vulnerable patients.
Scope Of Approved & Off-Label Use
Patients ask whether ramipril is suitable for hypertension, heart failure, diabetes and beyond.
Ramipril (marketed as Tritace, Ramipril Sandoz and generics; Altace internationally) is TGA‑registered as a prescription medicine for hypertension, heart failure and post‑MI management.
Many formulations are listed on the PBS in single agents or combinations, and clinicians often favour PBS‑subsidised generics to improve affordability and adherence.
Notable Off-Label Trends In Australian Practice
Australian clinicians sometimes use ramipril off‑label for nephroprotection in early diabetic kidney disease beyond narrow formal indications, tailoring doses to renal function.
In selected elderly patients, prescribers may retain low‑dose ramipril for vascular protection when the benefits outweigh risks, with careful monitoring.
Pediatric use is uncommon and not standardised in Australia, and regional clinicians may prefer long‑acting ACE inhibitors or once‑daily regimens to aid adherence in rural populations.
Global Context
Worldwide brands include Altace (Pfizer), Tritace (Sanofi) and multiple generics with standardised dosages of 1.25–10 mg.
Dosage Strategy
One common worry is how to start and titrate ramipril safely.
Typical adult starting dose for hypertension is 2.5 mg once daily, with upward titration to a maintenance range of 2.5–10 mg once daily or divided doses as tolerated.
For high‑risk secondary prevention following the HOPE protocol, titration up to 10 mg daily is common where tolerated.
Elderly patients and those at risk of hypotension often start at 1.25–2.5 mg with slower up-titration and closer monitoring.
Condition-Specific Dosing (PBS Recommendations)
Hypertension: Begin at 2.5 mg daily; maintain at 2.5–10 mg/day depending on response.
Post‑MI/CHF: Frequent initiation is 2.5 mg twice daily with escalation to 5 mg twice daily as tolerated.
Diabetic nephropathy: Individualised dosing within 2.5–10 mg/day with regular renal monitoring.
Renal impairment: Moderate impairment often warrants a 1.25 mg start and slow titration; severe impairment (CrCl <30 mL/min) needs caution or avoidance.
Titration & Monitoring
Check blood pressure, electrolytes and creatinine within 1–2 weeks of starting or changing dose, and advise patients not to double up on missed doses.
Safety Protocols
Patients commonly ask which side effects to expect and what needs urgent attention.
Absolute contraindications include prior ACE‑inhibitor–related angioedema, pregnancy, concurrent sacubitril/valsartan within 36 hours and known hypersensitivity.
Use caution with bilateral renal artery stenosis and severe hepatic impairment, and consult TGA or PBS safety notices before initiating where relevant.
Adverse Effects (Post‑Market Pharmacovigilance)
Common side effects are dry cough (about 5–15%), dizziness on initiation, headache and fatigue.
Serious but rare events include angioedema, clinically significant hyperkalemia and acute renal failure; the TGA’s adverse event reporting reflects these class‑consistent findings.
Pharmacist counselling should focus on recognising facial or throat swelling, sudden breathlessness or fainting and on measures to reduce risk.
Risk Mitigation
Baseline eGFR, creatinine and potassium are recommended, with a follow-up check within 1–2 weeks, especially if the patient uses NSAIDs, MRAs or potassium supplements.
For elderly or volume‑depleted patients, start at a low dose and titrate slowly to reduce symptomatic hypotension.
Interaction Mapping
Patients often bring long medicine lists; mapping interactions is essential.
There are no major food interactions, but alcohol can increase the risk of symptomatic hypotension, so conservative alcohol use is wise, particularly in older or rural patients.
High‑salt diets may blunt antihypertensive response; advise sodium reduction where appropriate.
Drug Combinations To Avoid (TGA Safety Alerts)
Avoid giving ramipril within 36 hours of sacubitril/valsartan (Entresto) to reduce angioedema risk.
Avoid aliskiren in diabetics, and exercise caution with potassium‑sparing diuretics, potassium supplements and mineralocorticoid receptor antagonists due to hyperkalemia risk.
NSAIDs can reduce antihypertensive effect and increase renal risk when combined with ACE inhibitors.
Practical Pharmacy Checks
Pharmacists should check e‑scripts for concurrent MRAs, NSAIDs and potassium supplements, and flag any Entresto co‑prescriptions for appropriate timing and authority codes.
Patient Experience Analysis
What do Australians say about taking ramipril?
Survey data and pharmacy feedback from 2022–24 show patients place high value on PBS subsidy and low out‑of‑pocket cost, which strongly correlates with adherence.
Common patient‑reported issues include dry cough, lightheadedness during initiation and a preference for once‑daily dosing to simplify routines.
Rural respondents frequently mention travel distances to pick up scripts and stock availability as factors that influence consistency of use.
Forum And Pharmacy Trends
Online forums and local pharmacy teams report frequent brand switches among Tritace, Altace and Ramipril Sandoz with minimal clinical difference, although some patients note pill appearance changes.
Community chains such as Chemist Warehouse and TerryWhite routinely provide counselling on cough and dizziness, and many pharmacies use reminder services to boost adherence.
Cultural & Socioeconomic Notes
Price sensitivity and reliance on PBS are major drivers of brand choice, and migrant communities often reference EU or Indian brand names like Ramace or Ramipres, so pharmacists should confirm dose equivalence during counselling.
Distribution & Pricing Landscape
Where do patients get ramipril and how much will they pay?
Major national pharmacy chains stock ramipril generics widely; Chemist Warehouse often lists low‑price generics while Priceline and TerryWhite provide pharmacist counselling alongside PBS dispensing.
Specific brand pack availability (1.25–10 mg) varies with supplier and supply‑chain events, so stock rotation and communication help avoid patient disruption.
Online Pharmacy Growth And Telehealth E‑Scripts
The rise of telehealth and e‑scripts since 2020 continued through 2022–25, improving access for regional patients.
Online pharmacies can dispatch ramipril by post with no cold‑chain needs; our online pharmacy offers discreet delivery to Australia in 5–14 days.
PBS Vs Private Cost Comparisons
PBS‑subsidised ramipril dramatically reduces co‑payments compared with private scripts, although some PBS listings require authority items and temporary private costs may apply.
Pharmacists should discuss price transparency tools and substitution options to help patients manage expense and maintain adherence.
Alternative Options
Many patients ask what to use if ramipril isn’t suitable.
PBS lists generics such as Ramipril Sandoz and Tritace which are generally the least expensive options for concession patients.
Non‑PBS alternatives include brand Altace or imported generics, which carry higher out‑of‑pocket costs and variable packaging.
Pros And Cons Checklist
Pros: strong evidence base from HOPE and meta‑analyses, renoprotective effects in diabetics, once‑daily regimens possible and wide generic availability.
Cons: cough incidence, contraindication in pregnancy, interaction profile (neprilysin inhibitors, potassium agents) and monitoring needs for renal impairment.
Alternatives: if ACE‑intolerance occurs, switch to an ARB such as perindopril alternatives; ARBs have lower cough rates but different PBS positions and cost implications.
Clinical Decision Factors
Choice should consider prior intolerance (cough -> ARB), renal function, PBS access and patient preference around dosing and tolerability.
Regulatory Status
Clinicians sometimes ask whether ramipril approvals differ between countries.
Ramipril is TGA‑registered as a prescription medicine for hypertension, heart failure and post‑MI management in Australia.
The TGA evaluates safety, efficacy and quality, and post‑market surveillance informs safety communications and updates to product information.
PBS Subsidy Process
PBS listing depends on cost‑effectiveness and clinical evidence, and once accepted medicines are subsidised under specified items or authority requirements.
Listings evolve, so clinicians should consult the current PBS schedule for authority codes or combination pack entries such as ramipril plus hydrochlorothiazide.
International Regulatory Harmonisation
Ramipril has global approvals and consistent prescribing information through regulators like the FDA and EMA, and Australian practice maps those data onto local TGA and PBS frameworks.
Consolidated FAQ
Q1 — Can I get ramipril on the PBS and how much will it cost?
A1: Many ramipril generics are PBS‑listed; cost depends on concession status and current PBS co‑payment thresholds, and pharmacists can check eligibility and suitable substitutes.
Q2 — What if I develop a cough?
A2: Cough occurs in approximately 5–15% of users; report it to your GP and do not stop without consulting — switching to an ARB is a common strategy if cough is persistent.
Q3 — Is it safe in pregnancy?
A3: No — ramipril is contraindicated in pregnancy (Category D). Women of childbearing potential should use contraception and stop ramipril if pregnancy is planned or suspected.
Q4 — How soon will my blood pressure drop and what monitoring is needed?
A4: Blood pressure usually falls within days; check BP and labs (eGFR, K+) within 1–2 weeks of starting or changing dose.
Q5 — Can I take ramipril with other common medicines?
A5: Avoid close timing with neprilysin inhibitors (36‑hour window) and use caution with NSAIDs, MRAs and potassium supplements; ask your pharmacist for a medicines‑check.
Visual Guide
What should clinics and pharmacies display to help patients understand ramipril access and dosing?
Infographic concept: a clear PBS pricing and co‑payment visual showing concession versus general patient bands, common dosages (1.25, 2.5, 5, 10 mg) and typical pack types (blister and bottle).
Another infographic: a map of Australia showing metropolitan stock abundance at Chemist Warehouse, Priceline and TerryWhite, and rural gaps where telehealth and mail order support continuity of supply.
Packaging visuals: label examples for Tritace, Altace and Ramipril Sandoz with ATC code C09AA05 and a storage icon indicating 20–25°C.
Implementation Notes
Provide downloadable PDFs for clinics and community pharmacies, use accessible fonts and consider translations or brand synonyms for migrant communities who may know local brand names such as Ramace or Ramipres.
Storage & Transport
People often keep medicines in the bathroom — that’s not ideal for ramipril.
Store ramipril at room temperature, ideally between 20°C and 25°C, and protect tablets from moisture and direct sunlight.
Avoid leaving packs on hot car dashboards or in humid bathrooms; recommend original packaging and tightly closed containers.
Cold‑Chain Logistics For Pharmacies
Ramipril does not require cold chain and can be stored at ambient pharmacy temperatures away from heat and humidity.
Pharmacies should rotate stock by expiry date and protect supplies from prolonged exposure to extreme temperatures during transport, especially in summer.
Online pharmacies should use insulated packaging when postal transit across hot regions is likely, although short postal delays are generally safe for ramipril.
Disposal & Returns
Advise patients to return unused medication to a pharmacy for safe disposal rather than throwing tablets in household rubbish.
Guidelines For Proper Use
What should a pharmacist say in three minutes when handing out ramipril?
Confirm the indication — hypertension, post‑MI or heart failure — then explain briefly that ramipril is an ACE inhibitor that reduces blood pressure and provides heart and kidney benefits.
Cover dose range (1.25–10 mg), expected timeline for effect, common side effects such as cough and dizziness and when to seek urgent care for angioedema or fainting.
National Health Authority Recommendations
Counselling should follow TGA advisories and Australian guideline practice: check baseline eGFR and potassium before initiation and repeat labs 1–2 weeks after start or titration.
Advise women of childbearing potential about pregnancy risks and contraception, and plan to switch to an ARB if ACE‑related cough or angioedema occurs.
Rural Practice Adjustments
In regional settings, arrange early telehealth follow‑up, organise local pathology access and favour once‑daily dosing or dispensing larger supplies to reduce travel burden where clinically appropriate.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-9 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Cairns | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |
Final Notes And Practical Tips
When counselling, use teach‑back to confirm the patient understands dosing, possible cough and the need to check blood tests after starting.
Match prescribing decisions to renal function, pregnancy status and previous ACE‑inhibitor intolerance, and document reason for choice in the record.
Be transparent about PBS entitlements and likely out‑of‑pocket costs, and offer substitution to Tritace or Ramipril Sandoz where clinically appropriate.
For patients travelling or living rurally, co‑ordinate supply ahead of time and consider pharmacy reminder services or dose blistering to improve adherence.
Report suspected adverse events to the TGA and encourage patients to return unused tablets for safe disposal at the pharmacy.