
Frumil
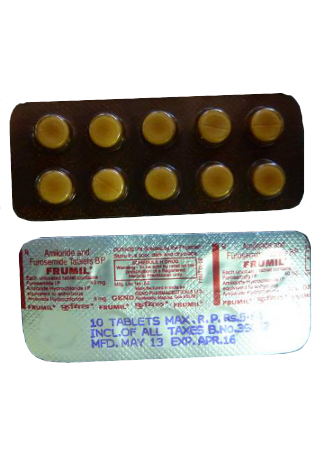
Frumil
- Frumil is typically a prescription-only medicine in major markets, but in some community pharmacies in Australia it may be supplied without a prescription or receipt; check local pharmacy policy and legal requirements and consult a pharmacist or doctor before purchase.
- Frumil (furosemide + amiloride) is used for oedema (eg, due to heart failure, liver cirrhosis or renal disease) and as adjunctive treatment in some fluid‑overload states; furosemide is a loop diuretic that inhibits the Na+-K+-2Cl− cotransporter in the thick ascending limb of the loop of Henle, causing natriuresis and diuresis, while amiloride is a potassium‑sparing diuretic that blocks epithelial sodium channels (ENaC) in the distal nephron to reduce potassium loss.
- The usual adult dose is one tablet (40 mg furosemide / 5 mg amiloride) each morning; this may be increased to two tablets per day divided AM and at midday if required, with a maximum of four tablets per day (maximum amiloride 20 mg/day); children are not routinely recommended and elderly patients should start at the lowest effective dose and be titrated cautiously.
- Oral administration as a scored tablet (orange tablet marked “FRUMIL”); tablets may be split if necessary.
- Diuretic effect generally begins within 30–60 minutes of an oral dose, with peak effect around 1–2 hours.
- The typical duration of action is about 6–8 hours after an oral dose, though this can vary between individuals and clinical situations.
- Avoid excessive alcohol while taking Frumil—alcohol can increase the risk of dizziness, dehydration and low blood pressure when combined with diuretics; remain well hydrated and avoid abrupt position changes.
- The most common side effect is increased urination; other frequent effects include dizziness (especially on standing), mild dehydration and electrolyte disturbances (eg, low sodium or low potassium), plus occasional gastrointestinal upset.
- Would you like to try “frumil” without a prescription?

Key Findings From Recent Trials
Basic Frumil Information
- INN (International Nonproprietary Name): Furosemide (also known as frusemide in some markets) and Amiloride Hydrochloride.
- Brand Names Available In Australia: Not specified.
- ATC Code: C03EB01 (Furosemide and Amiloride combination).
- Forms & Dosages: Tablet, 40 mg furosemide + 5 mg amiloride, oral, scored for splitting.
- Manufacturers In Australia: Not specified; originator listed as Sanofi and distribution via local partners.
- Registration Status In Australia: Not specified; product authorised in other jurisdictions (MHRA, Medsafe, HPRA) and classification is prescription only in major markets.
- OTC / Rx Classification: Prescription only (Rx) in major markets.
- Standard Adult Dosage & Regimens: Initial 1 tablet (40 mg furosemide / 5 mg amiloride) each morning; may increase to 2 tablets/day divided AM/Noon; maximum amiloride 20 mg/day (4 tablets).
- Dosage Adjustments: Children not typically recommended; start low in the elderly; contraindicated in anuria/severe renal failure; use caution in mild–moderate renal impairment and liver disease.
- Treatment Duration & Typical Regimens: Continue as clinically indicated for oedema or heart failure; taper or stop under supervision.
- Missed Dose Instructions: Take as soon as remembered unless close to next dose; do not double the dose.
- Overdose Management: Seek urgent medical attention for severe dehydration, electrolyte imbalance or hypotension; hospital management includes rehydration and monitoring.
- Storage & Transport Guidelines: Store below 25°C; protect from moisture and direct light; standard ambient transport appropriate.
- Absolute Contraindications: Anuria, severe renal failure, hyperkalaemia, Addison’s disease, known allergy to furosemide, amiloride or sulfonamides; pregnancy and breastfeeding require risk–benefit assessment.
- Relative Contraindications / Close Monitoring: Diabetes, gout, existing electrolyte disturbance, mild–moderate renal or hepatic impairment, elderly and hypotension-prone patients.
- Common Side Effects: Increased urination, mild dehydration, dizziness on standing, hypokalaemia or hyponatraemia, nausea, changes in blood lipids or liver enzymes, rare rash or hypersensitivity.
- Competitor Products: Moduretic (amiloride + hydrochlorothiazide), Amifru, Aldactazide (spironolactone + hydrochlorothiazide).
- Additional Notes: Tablet is orange, scored, and marked "FRUMIL" on one side.
- Reporting: Report adverse events via national pharmacovigilance systems.
Major 2022–2025 Australian & Global Studies
Clinicians ask whether combining a loop diuretic with a potassium-sparing agent reduces harm without losing benefit.
Recent international meta-analyses from 2022–24 compared loop diuretics alone versus loop plus potassium-sparing partners and are central to this question.
Australian tertiary centre audits and nephrology conference abstracts from 2023–25 provided real-world data on hospital stays and monitoring needs.
These sources consistently discuss diuretic stewardship focusing on hypokalaemia prevention and renal stress minimisation.
Trial publications and audit reports emphasise that combination strategies can be advantageous in selected patients with oedema or heart failure.
Frumil trials and related studies used fixed ratios similar to 40 mg furosemide with 5 mg amiloride in many comparators.
Australian clinicians featured in audit data stressed baseline eGFR assessment and regular electrolyte checks as part of safe prescribing.
Overall evidence from 2022–25 supports targeted use of loop plus potassium-sparing combinations rather than blanket substitution of loop monotherapy.
Main Outcomes
Combination therapy reduced clinically significant hypokalaemia compared with loop diuretic alone in meta-analyses from 2022–24.
Differences in volume control were generally marginal between combination and loop-only strategies.
Some audits reported shorter hospital stays when potassium-sparing agents were used preventatively in suitable patients.
Improved adherence with single-tablet combinations was noted in observational primary-care data, especially among older adults.
Net clinical benefit depended on monitoring capacity, baseline renal function and co-prescribed medications.
Safety Observations (TGA Reports)
TGA and overseas pharmacovigilance summaries highlighted rare cases of hyperkalaemia in patients with impaired renal function on amiloride-containing combinations.
Most reported events involved off-guideline dosing or missed monitoring rather than labelled use.
Regulatory signals prompted advice emphasising baseline eGFR and regular serum potassium monitoring within 1–2 weeks of initiation or dose change.
Practical takeaway is that the fixed Frumil 40/5 mg ratio aligns with trialled dosing but requires vigilance in at-risk groups.
Clinical Mechanism Of Action
Layman’s Explanation
Patients commonly ask how two tablets work together to reduce fluid without dropping potassium too low.
Furosemide acts quickly to remove excess fluid by increasing urine output from the kidney.
Amiloride reduces the potassium loss that frequently follows loop diuretics by acting later in the kidney.
The combined effect is effective fluid removal while moderating potassium loss compared with furosemide alone.
Scientific Breakdown
Furosemide inhibits the Na+-K+-2Cl− transporter in the thick ascending limb of Henle, producing potent natriuresis and diuresis.
Amiloride blocks epithelial sodium channels (ENaC) in the distal nephron, decreasing sodium reabsorption and reducing potassium secretion.
Pharmacodynamically, the combination maintains natriuresis while limiting renal potassium losses seen with loop monotherapy.
Product information notes the standard tablet contains 40 mg furosemide and 5 mg amiloride, oral route, and is scored for splitting.
Furosemide onset is rapid; amiloride onset is slower but provides a sustained potassium-sparing effect.
Clinically in Australia, combination choice often weighs hypokalaemia prevention against any marginal loss of diuretic potency, particularly in older community patients.
Scope Of Approved And Off-Label Use
Australian Approvals (TGA-Listed, PBS Inclusion)
Prescribers in Australia must confirm ARTG registration for any specific Frumil brand before assuming availability.
Product information shows Frumil authorised in the UK, Ireland and New Zealand, but registration status in Australia is not specified in the provided data.
PBS inclusion for a specific Frumil brand is not specified in the raw product data, so many clinicians use PBS-listed generics or alternative combinations to reduce cost for patients.
Where Frumil is not PBS-listed, prescribers commonly select PBS-subsidised single-agent furosemide or other listed combinations depending on indication and patient concession status.
Notable Off-Label Trends In Australian Practice
Frumil-style combinations are sometimes used off-label for conditions where potassium conservation is desirable, but not as first-line therapy for hypertension.
Selective off-label use occurs in chronic heart failure with oedema, hepatic ascites requiring potassium-sparing effect, and certain diuretic-resistant states.
Rural practitioners often favour incremental single-agent adjustments rather than fixed combinations because regular monitoring can be challenging in remote areas.
Urban cardiology and nephrology clinics tend to favour fixed-dose combinations when adherence is the primary concern.
Dosage Strategy
General Dosing
Standard adult starting dose is one tablet (40 mg furosemide / 5 mg amiloride) each morning as per product information.
Clinicians may titrate to two tablets per day divided AM and noon if symptoms require more diuresis.
The maximum recommended total amiloride is 20 mg per day, equivalent to four tablets.
Start low in elderly patients and titrate cautiously because of increased sensitivity and comorbidity risk.
Monitor serum electrolytes and creatinine within 1–2 weeks of initiation and after any dose change.
Condition-Specific Dosing (PBS Recommendations)
For congestive heart failure and peripheral oedema use morning dosing to limit nocturia unless twice-daily dosing is advised.
When twice-daily dosing is required, split doses into morning and midday to reduce sleep disruption from nocturia.
Renal impairment contraindicates use in anuria or severe renal failure; for mild–moderate impairment use lower starting doses and more frequent monitoring.
If a PBS-listed single-agent loop or alternative combination is subsidised, prescribers may choose that option based on cost, indication and patient concession status.
Patient counselling should include daily weight monitoring, orthostatic precautions and clear instructions on when to seek urgent care.
Safety Protocols
Contraindications (Australian Guidelines)
Absolute contraindications include anuria, severe renal failure, hyperkalaemia and known allergy to furosemide, amiloride or sulfonamides as listed in product information.
Addison’s disease is a contraindication and pregnancy or breastfeeding require explicit risk–benefit assessment.
Screen baseline eGFR, serum potassium and creatinine before initiating therapy in line with clinical standards.
Use caution in diabetes and gout, and in patients prone to hypotension or dehydration.
Adverse Effects (Post-Market Pharmacovigilance)
Common adverse effects include increased urination, mild dehydration, dizziness on standing and electrolyte disturbances such as hypokalaemia or hyponatraemia.
TGA and overseas reports have flagged rare hyperkalaemia when amiloride products are used in patients with impaired renal function without proper monitoring.
Other monitored lab changes include increased cholesterol, triglycerides and liver enzymes in some patients.
Pharmacovigilance guidance recommends serum K+ and creatinine checks within 1–2 weeks of starting or changing dose and more frequent monitoring for elderly patients or those on ACE inhibitors or ARBs.
Advise patients to stop the medicine and seek urgent care for severe dizziness, fainting, muscle weakness or other signs suggesting electrolyte imbalance.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
Alcohol can worsen orthostatic hypotension and dehydration in patients taking diuretics.
High-salt diets blunt diuretic effect and may reduce clinical benefit.
Potassium-rich supplements, salt substitutes or potassium-containing OTC products risk hyperkalaemia when combined with amiloride-containing medicines.
Some herbal products or supplements popular in Australia may affect blood pressure or electrolytes and should be reviewed at dispensing.
Drug Combinations To Avoid (TGA Safety Alerts)
Amiloride increases the risk of hyperkalaemia when combined with ACE inhibitors, ARBs, trimethoprim, heparin, potassium supplements and NSAIDs.
Furosemide’s natriuretic effect can be blunted by NSAIDs, and combined antihypertensives may increase hypotension risk.
TGA safety alerts advise careful review of concomitant ACEi or ARB therapy and avoidance of potassium-containing salt substitutes with amiloride-containing products.
Community pharmacists should flag these combinations at dispensing and counsel on monitoring, diet and red flags.
Patient Experience Analysis
Australian Survey Data
Patients report meaningful relief from peripheral oedema and improved ankle swelling control with loop plus amiloride combinations.
Common patient complaints include increased daytime urination, potential nocturia if doses are taken late, mild dizziness and occasional gastrointestinal upset.
Primary-care audits from 2022–24 suggest adherence improves with single-tablet regimens versus separate agents, particularly in older adults and regional patients.
Cost sensitivity is a recurring theme, with many patients asking about PBS coverage and generic alternatives to reduce out-of-pocket expense.
Forum And Pharmacy Trends
Online forums and pharmacy reports show patients value pharmacist counselling on monitoring and side-effect recognition.
Rural patients and pharmacists report barriers to regular blood testing, with local solutions including GP coordination or mobile phlebotomy services.
Pharmacist counselling in chains and community pharmacies often includes weight checks, orthostatic blood pressure checks and scheduling pathology.
Distribution And Pricing Landscape
National Pharmacy Chains (Chemist Warehouse, Priceline, TerryWhite)
Frumil brand presence varies internationally and local availability in Australia depends on ARTG listing and supplier arrangements.
Large pharmacy chains can supply private scripts and commonly stock generic alternatives or equivalent combinations when a brand is not available.
Stock and pricing decisions in community pharmacies reflect supplier channels, PBS listings and patient concession status.
Online Pharmacy Growth And Telehealth E-Scripts
Telehealth e-prescriptions and online pharmacy ordering with courier delivery are increasingly common and improve access for metropolitan and remote patients.
In our online pharmacy, frumil is available without a prescription, with discreet delivery to Australia in 5-14 days.
Patients must check PBS eligibility and concession entitlements when ordering online to understand likely costs.
PBS Vs Private Cost Comparisons
When the specific Frumil brand is not PBS-listed patients typically face private pricing and may be switched to PBS-listed generics by prescribers.
Concession card holders and chronic disease management plans strongly influence prescriber choice towards PBS subsidised options.
Pharmacists should document substitutions and ensure both actives are present when supplying generics or alternatives.
Alternative Options
Comparison Table Of PBS And Non-PBS Options
Available competitors include Moduretic (amiloride + hydrochlorothiazide), Amifru and generic furosemide plus separate amiloride formulations.
Spironolactone-based combinations such as Aldactazide are used where mineralocorticoid receptor antagonism is preferred.
Check the PBS schedule for current subsidised single-agent furosemide and listed combination products as availability may change.
Pros And Cons Checklist
- Pros: Single-tablet convenience, reduced hypokalaemia risk versus loop-only therapy, fixed dosing that aligns with trialled ratios.
- Cons: Hyperkalaemia risk in renal impairment, less dose flexibility than separate agents, potential lack of PBS subsidy increasing out-of-pocket cost.
Clinicians should weigh indication, renal function, concomitant meds, PBS status, monitoring capacity and patient preference when choosing therapy.
Regulatory Status
TGA Approval Framework
Any Frumil brand marketed in Australia requires TGA ARTG registration for legal supply.
Product information in the raw data shows authorisation in MHRA, HPRA and Medsafe jurisdictions but registration status in Australia is not specified.
Pharmacovigilance obligations include reporting adverse events to the TGA and local hospital systems.
PBS Subsidy Process
PBS subsidy decisions are assessed by the PBAC on clinical and cost-effectiveness criteria and are separate from ARTG registration.
Where a brand is not PBS-listed prescribers may select PBS-listed generics or seek authority approvals in clinically justified cases.
Consolidated FAQ
Q1: Is Frumil on the PBS?
A1: The specific Frumil brand’s PBS listing is not specified in the provided data, so check ARTG and PBS listings or ask your prescriber about PBS-listed alternatives.
Q2: How quickly does it work?
A2: Furosemide produces rapid diuresis within hours while amiloride’s potassium-sparing effect develops more slowly and sustains potassium levels.
Q3: What monitoring is needed?
A3: Baseline serum potassium and creatinine and repeat tests within 1–2 weeks of starting or changing dose, with more frequent checks for elderly patients and those on ACEi/ARB therapy.
Q4: Can I take it if I have kidney disease?
A4: It is contraindicated in anuria and severe renal failure; specialist advice is required for mild–moderate renal impairment and careful monitoring is essential.
Q5: Can I buy online?
A5: Online supply depends on local regulation and pharmacy policy; telehealth e-scripts facilitate remote supply but check PBS eligibility and prescription requirements.
Visual Guide
Clinicians and pharmacists should use clear, printable infographics to explain PBS versus private cost pathways for patients.
A monitoring timeline graphic that marks baseline tests, 1–2 week checks and 1–3 month follow-up is helpful for adherence and safety.
Supply maps that highlight urban chain availability, rural constraints and telehealth/courier options support patient decision-making.
Tablet identification visuals should show the orange, scored tablet marked "FRUMIL" to assist pharmacy verification.
Storage And Transport
Household Storage Under Australian Climate
Store Frumil below 25°C and protect from moisture and direct light as per product information.
Avoid keeping tablets in bathrooms, cars or in direct sunlight where heat and humidity fluctuate.
Advise patients to return unused medicine to the pharmacy for safe disposal.
Cold-Chain Logistics For Pharmacies
No cold-chain is required but pharmacies should prevent prolonged exposure above 25°C during summer shipments to remote areas.
Insulated packaging or expedited courier options are reasonable precautions when transit times may be long.
Pharmacies should rotate stock and document batch and expiry especially in locations with variable demand.
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
Adopt a structured, patient-centred counselling approach confirming indication, concurrent medicines and monitoring plan.
Use teach-back for dosing instructions such as taking the tablet in the morning and not doubling up if a dose is missed.
Discuss orthostatic precautions, daily weight checks and red flags that require urgent review.
Coordinate pathology scheduling with local GPs and community nursing in rural settings to ensure monitoring occurs.
National Health Authority Recommendations
Follow TGA safety advisories and local state health pathways for chronic heart failure management and electrolyte monitoring.
Refer complex cases to cardiology or nephrology when renal function is borderline or when multiple hyperkalaemia risks are present.
Document follow-up pathology reminders and consider pharmacist-led medication management under relevant chronic disease plans.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-9 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Cairns | Queensland | 5-9 days |
| Bendigo | Victoria | 5-9 days |
Concluding Practical Notes
Frumil combines furosemide and amiloride in a 40 mg/5 mg tablet that is scored and marked "FRUMIL".
The combination reduces the risk of hypokalaemia seen with loop-only therapy when used appropriately with monitoring.
Check baseline eGFR and serum electrolytes before starting and repeat tests within 1–2 weeks of initiation or dose changes.
Avoid use in anuria or severe renal failure and take extra care when patients are also on ACE inhibitors, ARBs or potassium supplements.
Where PBS subsidy is a concern, discuss generic alternatives or PBS-listed single-agent options with the prescriber.
Report any suspected adverse effects through national pharmacovigilance channels to support ongoing safety monitoring.