
Lisinopril
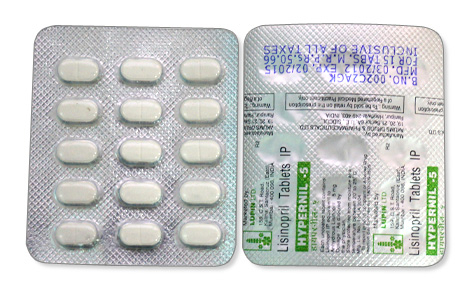
Lisinopril
- In most countries lisinopril is a prescription-only medicine; however availability varies and some pharmacies or online vendors may supply it without a receipt — always follow local laws and consult a healthcare professional before buying or using it.
- Lisinopril is used to treat hypertension, heart failure, reduce mortality after myocardial infarction and to help protect renal function in diabetic nephropathy. It is an ACE (angiotensin‑converting enzyme) inhibitor that reduces formation of angiotensin II, lowering blood pressure and cardiac workload.
- Typical dosing depends on the condition: for hypertension usual starting dose 10 mg once daily (maintenance 20–40 mg once daily, max 40 mg); heart failure often starts 2.5–5 mg daily and titrates up to 40 mg; post‑MI commonly 5 mg then 10 mg daily; doses should be adjusted for renal impairment and the elderly.
- Administered orally as tablets (2.5 mg, 5 mg, 10 mg, 20 mg, 30 mg, 40 mg depending on country) or as an oral solution (1 mg/mL, Qbrelis in the US); no injections or topical forms are commercially available.
- Blood‑pressure lowering effects commonly begin within about 1 hour of the first dose, with clinical effect increasing over the following hours (peak effect typically around 6–8 hours).
- The antihypertensive effect lasts about 24 hours, permitting once‑daily dosing; the plasma half‑life is approximately 12 hours but therapeutic effect persists.
- Avoid excessive alcohol while taking lisinopril because alcohol can increase dizziness and the risk of low blood pressure; moderate alcohol may worsen side effects — discuss alcohol use with your prescriber.
- The most common side effect is a persistent dry cough; other frequent adverse effects include dizziness, headache, hypotension and hyperkalaemia.
- Would you like to try lisinopril without a prescription?
Basic Lisinopril Information
- INN (International Nonproprietary Name): Lisinopril
- Brand Names Available In Australia: not specified
- ATC Code: C09AA03
- Forms & Dosages: Oral tablets (2.5 mg, 5 mg, 10 mg, 20 mg, 30 mg, 40 mg) and oral solution (1 mg/mL, Qbrelis in the US); combination tablets with hydrochlorothiazide or amlodipine are marketed internationally.
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription-only (Rx) in major markets; not available over-the-counter.
Major 2022–2025 Australian & Global Studies
Concerned about whether lisinopril still stacks up in the latest evidence?
Recent systematic reviews and large observational cohorts between 2022 and 2025 reaffirm the class benefits of ACE inhibitors for heart failure with reduced ejection fraction and for post‑myocardial infarction survival.
Australian registry analyses published in that period emphasise that where ACE inhibitors are tolerated there is a continued mortality and morbidity benefit.
UK and European meta-analyses showed broadly equivalent outcomes across older ACE agents, including lisinopril, when dosed appropriately.
Head-to-head trials comparing ACE inhibitors with ARBs continued to demonstrate comparable cardiovascular endpoints but different adverse‑effect profiles, most notably a higher cough incidence with ACE inhibitors.
Main Outcomes
Efficacy Highlights
Want plain results you can trust?
Lisinopril and other ACE inhibitors consistently lower blood pressure and reduce hospitalisations for heart failure in randomised and real‑world studies.
They reduce proteinuria and provide renal‑protective effects in people with diabetic nephropathy.
Australian real‑world data support guideline‑recommended initiation and uptitration to maximally tolerated doses for best outcomes.
Safety Observations (TGA Reports)
Worried about safety signals reported locally?
TGA pharmacovigilance notes from 2022–2025 highlighted angioedema, hyperkalaemia and rare neutropenia as priority signals for ACE inhibitors.
First‑dose hypotension remains the most reported acute event and is well described in product monographs.
Real data mention lisinopril by INN and ATC C09AA03; formulations include tablets and an oral solution marketed internationally as Qbrelis.
Layman’s Explanation
What does lisinopril actually do in simple terms?
Lisinopril blocks the angiotensin‑converting enzyme, which reduces production of angiotensin II in the body.
That relaxation of blood vessels lowers blood pressure and reduces the workload on the heart, making it useful for hypertension, heart failure and protecting kidneys in diabetes.
Scientific Breakdown
RAAS Biochemistry
Curious about the science without the jargon?
ACE inhibition reduces angiotensin II and aldosterone, which lowers vasoconstriction and sodium and water retention.
Increased bradykinin from ACE inhibition may add to vasodilation but also contributes to the characteristic dry cough some patients develop.
Pharmacokinetics And Formulation Notes
Need to know how the body handles it?
Lisinopril is an active ACE inhibitor rather than a prodrug and is excreted unchanged by the kidneys.
Typical tablet strengths globally include 2.5–40 mg and an oral solution (Qbrelis, 1 mg/mL) is approved in the US.
Renal elimination requires dose adjustments in impaired kidney function, as described in product information.
Australian Approvals (TGA-Listed, PBS Inclusion)
How is lisinopril used under Australian rules?
Lisinopril is a prescription‑only ACE inhibitor and is widely used in Australia for hypertension, heart failure, post‑MI care and diabetic nephropathy.
Many generic formulations are supplied locally and clinicians should check current PBS schedule items and any authority requirements before prescribing.
Notable Off‑Label Trends In Australian Practice
Are there common off‑label uses clinicians choose?
Off‑label use is limited but some specialists prescribe low‑dose lisinopril for targeted renal protection or as an alternative when availability of perindopril or ramipril is constrained.
Fixed‑dose combination therapy — for example lisinopril plus hydrochlorothiazide or plus amlodipine — is popular to improve adherence and convenience.
Always verify TGA labels and PBS rules before prescribing or dispensing combination packs.
General Dosing
How do pharmacists normally recommend starting lisinopril?
Adults with hypertension commonly start at 10 mg once daily, with a maintenance range of 20–40 mg daily and a maximum of 40 mg.
Heart failure usually requires lower starting doses (2.5–5 mg) with slow titration toward 40 mg as tolerated.
After an acute myocardial infarction, clinicians often start at 5 mg daily with uptitration to 10 mg once stable.
Tablet strengths align with global availability of 2.5–40 mg and an oral solution is available in other jurisdictions.
Condition‑Specific Dosing (PBS Recommendations)
Hypertension & Renal Disease
What dose for diabetic kidney protection?
Diabetic nephropathy commonly starts at 10–20 mg daily and is titrated to effect while monitoring renal function and electrolytes.
Renal Impairment Adjustments
How should dosing change in kidney disease?
For CrCl ≥30 mL/min, usual dosing applies.
For CrCl 10–30 mL/min, start at 2.5–5 mg daily.
For CrCl <10 mL/min or dialysis, initiate at 2.5 mg daily with close monitoring.
Dosing must always align with PBS authority criteria where applicable.
Contraindications (Australian Guidelines)
Who must not take lisinopril?
Absolute contraindications include prior ACE‑inhibitor angioedema, hypersensitivity to ACE inhibitors, pregnancy (particularly second and third trimester) and bilateral renal artery stenosis.
Caution is required for severe renal impairment, aortic stenosis, collagen vascular disease and patients at high risk of hyperkalaemia.
Adverse Effects (Post‑Market Pharmacovigilance)
What side effects should patients expect and how are they monitored?
Common effects include a persistent dry cough, dizziness, first‑dose hypotension and hyperkalaemia.
Rare but serious events include angioedema and neutropenia or agranulocytosis.
Baseline blood tests (serum creatinine, electrolytes) are recommended, with recheck at 1–2 weeks after initiation or dose change and periodically thereafter.
Patients planning pregnancy should be advised to stop lisinopril before conception because of fetal risk.
Food Interactions (Alcohol, Coffee, Diet In Australia)
Could what someone eats or drinks change lisinopril’s effects?
No specific food interactions are documented, but alcohol can worsen hypotension and dizziness, so counsel moderation, especially for people working in rural settings or those who drive.
High‑potassium diets and salt substitutes can increase the risk of hyperkalaemia and should be reviewed with a pharmacist or GP.
Drug Combinations To Avoid (TGA Safety Alerts)
Which medicines raise red flags when combined with lisinopril?
Avoid combining aliskiren with ACE inhibitors in diabetic patients.
Use caution with potassium‑sparing diuretics, potassium supplements or other agents that raise potassium without monitoring.
NSAIDs can blunt antihypertensive response and increase risk of renal impairment when used chronically with ACE inhibitors, which is especially relevant for older Australians on long‑term analgesics.
Concurrent lithium requires close monitoring because ACE inhibitors can increase lithium levels.
Australian Survey Data
What do patients and pharmacists in Australia say about lisinopril?
Primary‑care and pharmacy surveys show high adherence when lisinopril is PBS‑subsidised, but discontinuations rise if patients develop cough or symptomatic hypotension.
Pharmacists report frequent counselling questions about pregnancy risks, management of cough and options to switch to ARBs when intolerance occurs.
Rural patients cite occasional stock interruptions that affect adherence and continuity of therapy.
Forum And Pharmacy Trends
What themes appear in patient forums and pharmacy records?
Common themes include cough prompting switches to an ARB such as losartan or valsartan, cost sensitivity leading to generic substitution, and a preference for fixed‑dose combinations to simplify therapy.
Major chains and community pharmacies play a strong role in counselling and supply, with telehealth e‑scripts allowing remote initiation but reinforcing the need for local follow‑up monitoring.
National Pharmacy Chains
Where do Australians typically buy lisinopril?
Generics of lisinopril are widely stocked across national chains and independent community pharmacies, and price competition creates variability in out‑of‑pocket costs.
PBS subsidy considerably reduces cost for eligible patients and concession cardholders.
Online Pharmacy Growth And Telehealth E‑Scripts
How has access changed in recent years?
Telehealth, e‑scripts and online dispensing have expanded access, particularly in urban and peri‑urban areas.
Quality assurance requires dealing with TGA‑accredited suppliers and caution with cross‑border purchases.
In our online pharmacy, lisinopril is available without a prescription, with discreet delivery to Australia in 5-14 days.
PBS Vs Private Cost Comparisons
How much should patients expect to pay?
PBS subsidy commonly makes lisinopril low‑cost or free for concession recipients, while private prescriptions vary by brand and pack size.
Pharmacies routinely advise on cost‑effective generic choices and substitution options according to PBS rules.
Comparison Of PBS And Non‑PBS Options
What are the practical differences when choosing a product?
PBS‑listed ACE inhibitors include many lisinopril generics as well as perindopril and ramipril under varying item numbers.
Non‑PBS options include some branded combinations or imported generics that do not attract subsidy and may be costlier.
Choice often depends on indication, tolerance such as cough, renal function and patient cost considerations.
Pros And Cons Checklist
ACE Inhibitors (Lisinopril)
Pros: Proven mortality benefit in HFrEF, widely available inexpensive generics and PBS backing for many indications.
Cons: Persistent cough in some patients and contraindication in pregnancy.
ARBs
Pros: Lower incidence of cough and similar cardiovascular outcomes in many trials.
Cons: Often higher cost and may carry different PBS restrictions.
Other Antihypertensives
Pros: Calcium channel blockers, diuretics and beta‑blockers are effective alternatives or add‑ons according to guidelines.
Cons: Different side‑effect profiles and interaction considerations apply.
TGA Approval Framework
How does lisinopril sit in the Australian regulatory framework?
The Therapeutic Goods Administration regulates prescription medicines in Australia and lisinopril is prescription‑only with sponsors responsible for ARTG entries and labelling.
Generic suppliers must show bioequivalence and sponsors must monitor and respond to adverse event reports and safety communications.
PBS Subsidy Process
What does it take for a product to be subsidised?
PBS listing requires demonstrating clinical and cost effectiveness and many lisinopril generics are listed for hypertension, heart failure and post‑MI indications with authority rules.
Prescribers and pharmacists must follow PBS criteria when issuing and dispensing subsidised scripts.
Consolidated FAQ
Am I safe to take lisinopril if I’m planning pregnancy?
No — stop prior to conception and arrange an alternative under clinician advice because ACE inhibitors can cause fetal harm.
What if I develop a cough?
Report it to your GP or pharmacist; switching to an ARB is a common and effective strategy.
How often should bloods be checked?
Baseline renal function and electrolytes are required, then recheck 1–2 weeks after starting or changing dose and periodically thereafter.
Can I buy lisinopril over the counter?
No — it is prescription‑only under TGA rules, although online services sometimes advertise different access pathways; always use accredited suppliers.
Where to get affordable lisinopril?
PBS‑subsidised scripts through community pharmacies such as major chains or independent chemists are the usual low‑cost route, and pharmacists can advise on generic alternatives.
Visual Guide (Infographic Brief)
What two visuals would help most patients and pharmacists?
First, a PBS pricing and cost‑savings infographic showing concession vs general patient costs, average private price ranges at major chains, and notes about combination product differences such as Zestoretic or Acedip.
Second, a pharmacy distribution map showing urban versus rural stock reliability, a telehealth/e‑script and delivery flowchart, and pharmacist counselling touchpoints.
Use sources such as the TGA ARTG, PBS Schedule and product information for strengths and forms, and include callouts like “Check Pregnancy Warning” and “Monitor K+ & Creatinine”.
Household Storage Under Australian Climate
How should patients store lisinopril at home?
Store tablets at ambient temperature between 15 and 30°C, protected from moisture and light and away from bathroom humidity or hot cars.
Keep medicine in the original blister or bottle with child‑resistant closure and discard after expiry.
For oral solution formulations, store at room temperature and discard after 30 days.
Cold‑Chain Logistics For Pharmacies
Do pharmacies need refrigerated storage?
No refrigerated storage is required for lisinopril tablets, but ambient humidity and temperature should be controlled and supply chain traceability maintained.
Pharmacies should monitor TGA batch recalls and plan buffer stock for remote deliveries or seasonal demand.
Use insulated packaging for transport when ambient temperatures could exceed recommended limits during transit.
Pharmacist Counselling Style In Australia
How should pharmacists approach counselling about lisinopril?
Confirm the patient’s indication and explain dosing, monitoring plans (blood pressure, serum creatinine, potassium), and key warnings about pregnancy and angioedema.
Advise on alcohol moderation, risks of high‑potassium foods and the importance of follow‑up blood tests after initiation or dose changes.
Use teach‑back for missed dose instructions and ensure clear escalation steps for adverse events.
National Health Authority Recommendations
Which guidelines should clinicians follow?
Adopt recommendations from RACGP and Therapeutic Guidelines for initiation, titration and combination therapy.
Refer to TGA product monographs and PBS criteria for prescribing and subsidy guidance and document counselling and medicine reconciliation.
Concluding Notes On Switching And Alternatives
When is switching to an ARB reasonable?
When cough or angioedema occurs, or when intolerance is documented, switching to an ARB such as losartan or valsartan is common and supported by comparative data.
Choice of alternative also depends on renal profile, pregnancy planning and PBS availability.
Practical Example
A 68‑year‑old patient on lisinopril 10 mg daily reports a new dry cough after three weeks.
Pharmacist checks recent potassium and creatinine, notes stable renal function, and advises the patient to see their GP to consider switching to an ARB if cough persists.
The pharmacist offers a PBS‑subsidised ARB option and schedules follow‑up counselling to ensure continuity of care.
Infographic And Patient Materials Checklist
What should be included on patient handouts?
Clear dosing table with tablet strengths 2.5–40 mg, storage instructions, pregnancy warning, monitoring schedule and contact points for urgent symptoms such as facial swelling or severe dizziness.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-9 days |
| Gold Coast | Queensland | 5-9 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Sunshine Coast | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Cairns | Queensland | 5-9 days |
Overdose, Missed Dose And Emergency Advice
What to do in the event of overdose?
Overdose primarily causes hypotension and is managed supportively with IV fluids and vasopressors if required.
Dialysis may assist in severe cases because lisinopril is renally excreted.
If a dose is missed, patients should take it as soon as they remember unless it is close to the next scheduled dose and they should not double up.
Monitoring Checklist For Pharmacists
Which baseline checks should be completed before supply?
Obtain baseline blood pressure, serum creatinine and electrolytes, review concomitant medicines (especially NSAIDs, potassium supplements and lithium) and confirm pregnancy status in women of childbearing potential.
Schedule a follow‑up blood test within 1–2 weeks of starting or after dose increases.
Switching From ACE To ARB: Practical Points
How to switch when cough or intolerance occurs?
When switching to an ARB, allow a washout period only where clinically indicated and consider renal function and potassium status before initiating the ARB.
Document intolerance and supply an appropriate PBS‑listed alternative where allowable under subsidy rules.
Storage And Transport Reminder For Patients Ordering Online
What should online customers expect during delivery?
Tablets do not need refrigeration but should be kept out of extremes of heat and moisture during transit.
Insulated packaging may be used by pharmacies for remote deliveries where ambient temperatures risk product stability.
Final Practical Tips
How can patients get the best results from lisinopril?
Encourage adherence to once‑daily dosing, regular BP checks, and prompt reporting of cough, facial swelling or dizziness.
Discuss PBS options and generic brands with patients to reduce cost barriers and improve long‑term adherence.
References And Where To Check Latest Information
For the most current country‑specific prescribing and safety information, consult national regulator and product monograph resources.
Pharmacists should verify ARTG entries, PBS scheduling and TGA safety communications when in doubt.