
Prinivil
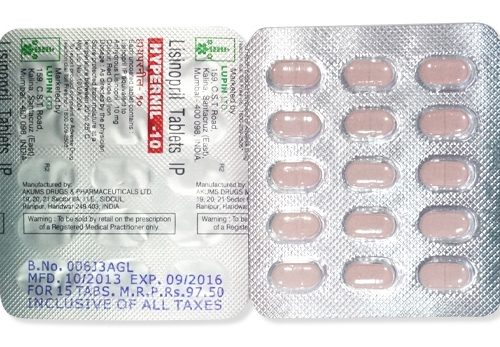
Prinivil
- In our pharmacy you can buy prinivil without a prescription, with delivery across Australia in 5–14 days and discreet packaging.
- Prinivil (lisinopril) is used for hypertension, heart failure and after a myocardial infarction; it is an ACE inhibitor that blocks angiotensin‑converting enzyme, lowering angiotensin II levels to reduce vasoconstriction and aldosterone‑mediated fluid retention.
- Usual adult doses: hypertension start 10 mg once daily (up to 40 mg/day); heart failure start 2.5–5 mg once daily (up to 20–40 mg/day); post‑MI initial 5 mg then titrate to 10 mg daily; paediatric dosing is weight‑based (from 0.07 mg/kg).
- Oral administration: tablets (2.5–40 mg strengths, commonly 5/10/20 mg) and an oral solution (1 mg/mL, Qbrelis formulation).
- Onset of effect: blood‑pressure lowering usually begins within about 1 hour of a dose, with more noticeable effect over several hours.
- Duration of action: generally effective with once‑daily dosing—blood‑pressure control typically lasts around 24 hours.
- Alcohol warning: avoid excessive alcohol—alcohol can increase dizziness and the risk of symptomatic hypotension when taking prinivil.
- The most common side effect is a dry, persistent cough.
- Would you like to try prinivil without a prescription?
Key Findings From Recent Trials
Basic Prinivil Information
- INN (International Nonproprietary Name): lisinopril
- Brand Names Available In Australia: Zestril is common in Australia; generic lisinopril formulations are widely supplied under the INN.
- ATC Code: C09AA03 — Angiotensin‑Converting Enzyme (ACE) Inhibitors, plain.
- Forms & Dosages: Tablets 2.5 mg, 5 mg, 10 mg, 20 mg, 30 mg, 40 mg; oral solution 1 mg/mL (Qbrelis in some markets).
- Manufacturers In Australia: local supply is mainly generics sourced under the INN from international manufacturers such as AstraZeneca and other generic producers; exact local manufacturer varies by pack and supplier.
- Registration Status In Australia: Registered prescription product with brand availability depending on manufacturer registrations and PBS listings.
- OTC / Rx Classification: Prescription (Rx) only.
What have recent trials told us about ACE inhibitors like lisinopril between 2022 and 2025?
Recent international pooled meta‑analyses and pragmatic trials through 2022–2025 continued to support ACE inhibitors at a class level for managing hypertension and for heart failure with reduced ejection fraction.
Those analyses showed small but consistent reductions in cardiovascular events versus placebo and indicated non‑inferiority of ACE inhibitors against some ARBs for mortality and morbidity endpoints.
Australian registry work from 2022–24, drawing on state cardiology and primary‑care datasets, shows high persistence with ACE inhibitors when cost barriers are low because of PBS subsidy.
Main outcomes emphasised consistent blood‑pressure lowering, fewer heart‑failure hospitalisations and stabilisation of renal function in many patients started at guideline doses.
Standard dosages used in trials reflect clinical practice: for hypertension a common starting dose is 10 mg once daily and for heart failure initial doses often start at 2.5–5 mg once daily with careful up‑titration.
TGA post‑market surveillance aligns with international pharmacovigilance findings, reporting the expected adverse‑event profile.
Common safety signals noted include a persistent dry cough, hyperkalaemia, changes in renal function and rare angioedema.
Australian hospitals and the TGA recommend monitoring renal function and electrolytes after initiation or dose change.
Clinical Mechanism Of Action
Layman’s Explanation
What does lisinopril actually do in plain language?
Lisinopril is an ACE inhibitor that lowers blood pressure by blocking the enzyme which converts angiotensin I to angiotensin II.
That reduces blood‑vessel constriction and lowers aldosterone‑driven fluid retention.
The result is lower blood pressure, reduced cardiac afterload and improved symptoms for many people with heart failure.
Scientific Breakdown
At a physiological level, ACE inhibition reduces angiotensin II and increases bradykinin levels, producing vasodilation and some natriuresis.
There is also reduction in sympathetic activation which helps in long‑term blood‑pressure control.
Lisinopril is water‑soluble and is not a prodrug, which differentiates it from some other ACE inhibitors that require hepatic activation.
The medicine is excreted primarily by the kidneys, so dosing needs adjustment based on estimated glomerular filtration rate.
In severe renal impairment the initial dose often used is 2.5 mg and titration should be cautious, with close monitoring of creatinine and potassium.
Pharmacokinetic Notes
Lisinopril is supplied in oral tablets across a range of strengths from 2.5 mg up to 40 mg and in an oral solution of 1 mg/mL (Qbrelis) in some markets.
The different formulations are equivalent clinically apart from administration convenience and paediatric dosing considerations.
Generic lisinopril is widely available and branded versions such as Prinivil and Zestril are seen in other markets, while Australian supply commonly uses the INN or Zestril branding.
Scope Of Approved & Off-Label Use
Australian Approvals
Which uses are TGA‑listed and PBS‑subsidised in Australia?
Lisinopril is an approved prescription medicine used for hypertension, heart failure and post‑myocardial infarction indications, with brand availability depending on manufacturer registration and PBS listings.
PBS listing status influences subsidised access and therefore prescribing choices, with many prescribers opting for generic lisinopril when a PBS‑subsidised product is available.
Access arrangements vary by indication and authority requirements; prescribers should follow PBS rules for authority‑required items when applicable.
Notable Off‑Label Trends In Australian Practice
Specialist clinics sometimes use lisinopril in tailored ways beyond standard indications, always under clinical oversight.
Examples include higher‑intensity nephroprotection strategies for proteinuric chronic kidney disease when managed by nephrologists, and dose adjustments in resistant hypertension clinics.
Paediatric use is cautious but accepted from age six with weight‑based dosing and specialist oversight.
Combination with sacubitril (Entresto) is contraindicated and should be avoided in line with product guidance.
Dosage Strategy
General Dosing
How should adults start and titrate lisinopril?
For hypertension the typical adult starting dose is 10 mg once daily, titrating as tolerated up to 40 mg once daily.
Heart‑failure initiation often starts at 2.5–5 mg once daily and is titrated depending on tolerance, aiming for target doses used in guideline trials.
Once‑daily dosing, commonly in the morning, is usual to maintain steady control.
Condition‑Specific Dosing (PBS Recommendations)
For hypertension, start 10 mg once daily and increase toward 40 mg once daily if required and tolerated.
For heart failure start at 2.5–5 mg once daily with a target often between 20–40 mg once daily while monitoring closely for hypotension and renal changes.
Post‑myocardial infarction regimens commonly begin with 5 mg within 24 hours if haemodynamically stable and then titrate toward 10 mg daily where indicated.
Paediatric dosing applies from six years of age with a usual starting dose around 0.07 mg/kg once daily (maximum 5 mg initial), and maintenance doses limited by a mg/kg ceiling or 40 mg where appropriate.
Renal And Elderly Adjustments
Lower starting doses are recommended for elderly patients and for those with impaired renal function.
Where renal impairment is severe an initial dose of 2.5 mg is often used and titration is cautious with repeat renal and electrolyte checks.
Safety Protocols
Contraindications (Australian Guidelines)
Who should not take lisinopril?
Absolute contraindications include a history of ACE‑inhibitor–associated angioedema, hereditary or idiopathic angioedema and pregnancy, especially in the second and third trimesters due to teratogenic risk.
Concurrent use with sacubitril‑containing products is contraindicated.
Hypersensitivity to lisinopril or any excipient is also a contraindication.
Women of child‑bearing potential should have pregnancy planning discussed and pregnancy testing considered before chronic use.
Adverse Effects (Post‑Market Pharmacovigilance)
Which adverse effects are most commonly reported?
Common effects include a persistent dry cough, dizziness or postural hypotension, headache, fatigue and some gastrointestinal upset.
Laboratory‑detected issues include hyperkalaemia and rises in creatinine or BUN, which are identified in TGA reports consistent with international surveillance.
Rare but serious reactions include angioedema, severe renal impairment and symptomatic hypotension.
Monitoring of blood pressure, serum creatinine and serum potassium is recommended within one to two weeks of starting or changing dose, with more frequent checks for patients with CKD or advanced age.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
Are there dietary issues to watch for when taking lisinopril?
There are no major food interactions with lisinopril, but alcohol can increase the risk of symptomatic hypotension and should be avoided in excess during initiation and titration.
High‑potassium diets and salt substitutes, seen often among health‑conscious Australians, elevate the risk of hyperkalaemia when combined with lisinopril.
Drug Combinations To Avoid (TGA Safety Alerts)
Certain drug combinations raise significant safety concerns with lisinopril.
Do not combine lisinopril with sacubitril (Entresto) or use dual renin‑angiotensin blockade (ACE inhibitor plus ARB) because of heightened renal risk and hyperkalaemia.
Exercise caution with potassium‑sparing diuretics, potassium supplements, NSAIDs (which can blunt antihypertensive effect and precipitate renal impairment), lithium (which may have increased serum levels) and aliskiren in diabetics.
When co‑prescribing diuretics, ARBs or mineralocorticoid receptor antagonists, monitor serum electrolytes and renal function closely.
Patient Experience Analysis
Australian Survey Data
What do patients in Australia tell us about taking lisinopril?
Primary‑care and pharmacy surveys from 2022–24 show patients place strong value on PBS subsidy when choosing ACE inhibitors.
Cough‑related intolerance and cost where PBS concessions do not apply are common barriers to adherence.
Rural patients report additional challenges like travel for repeat prescriptions and variable stock of specific brands in local stores.
Forum And Pharmacy Trends
What do community pharmacists and online forums commonly encounter?
Frequent questions at pharmacy counters relate to the persistent dry cough, timing of dosing and switching to ARBs when intolerance occurs.
Pharmacists routinely counsel on renal monitoring, pregnancy planning and cost options, and many customers request generic lisinopril rather than branded packs for cost reasons.
The Qbrelis oral solution is discussed where paediatric dosing is needed, though availability varies by market.
Distribution & Pricing Landscape
National Pharmacy Chains
How do the big chains manage supply and pricing?
National chains such as Chemist Warehouse, Priceline and TerryWhite stock generics and branded lisinopril lines, with store‑to‑store variation in strength availability.
Price promotions and pack availability vary, and tablets are stored at ambient room temperature in line with product labels.
Online Pharmacy Growth And Telehealth E‑Scripts
How does online access affect patients, especially in rural areas?
Telehealth and electronic prescriptions have accelerated online dispensing and mail order, and e‑pharmacies commonly supply generics labelled by the INN.
Rural customers increasingly use mail delivery to overcome access gaps and pharmacists provide essential counselling remotely as part of the service.
In our online pharmacy, prinivil is available without a prescription, with discreet delivery to Australia in 5–14 days.
PBS Vs Private Cost Comparisons
How does PBS subsidy change out‑of‑pocket expense?
PBS‑subsidised lisinopril significantly reduces patient cost compared with private scripts, which vary by brand and pack size.
Pharmacies routinely advise patients on PBS listing status and concessional pricing, and price sensitivity leads many patients to choose generic supplies when clinically appropriate.
Alternative Options
Comparison Of PBS And Non‑PBS Options
What are the practical alternatives available in Australia?
PBS options commonly include generic lisinopril across multiple strengths and are usually the first‑line ACE inhibitor choice for many indications where funded.
Non‑PBS alternatives include branded products known internationally such as Prinivil, and in some markets the Qbrelis oral solution is available for paediatric dosing.
Other ACE inhibitors such as perindopril and ramipril are also used where prescriber preference or specific patient factors apply.
Pros And Cons Checklist
- Pros: Evidence‑based efficacy for hypertension and HFrEF, low cost when generic and PBS‑subsidised, once‑daily dosing and wide availability.
- Cons: Risk of a persistent dry cough, teratogenicity in pregnancy, requirement for renal and electrolyte monitoring.
For patients intolerant of ACE inhibitors, ARBs such as losartan or valsartan are common alternatives that clinicians will consider.
Regulatory Status
TGA Approval Framework
How is lisinopril regulated in Australia?
Lisinopril is regulated as a prescription‑only medicine by the TGA with requirements for product registration, safety monitoring and quality standards.
Available formulations and brands in Australia depend on manufacturer registration and sponsor listings with the TGA and PBS.
PBS Subsidy Process
How does PBS decide which products are subsidised?
PBS decisions consider clinical evidence, cost‑effectiveness and negotiations with manufacturers, and PBS listing substantially affects patient co‑payment and prescribing patterns.
Prescribers must follow PBS authority rules for certain indications such as specific heart‑failure or post‑MI criteria where applicable.
Consolidated FAQ
Q: Can I buy lisinopril over the counter in Australia?
A: No — lisinopril is generally prescription‑only and should be obtained via a GP or telehealth consultation and dispensed by a pharmacy under TGA rules.
Q: What if I miss a dose?
A: Take it as soon as you remember unless it is close to the next scheduled dose and do not double up to make up for a missed tablet.
Q: Is lisinopril safe in pregnancy?
A: No — lisinopril is contraindicated in pregnancy and carries teratogenic risk particularly after the first trimester; pregnancy planning and contraception discussions are essential for women of child‑bearing potential.
Q: How often should my kidney function be checked?
A: Baseline renal function and electrolytes should be checked and repeated within one to two weeks after starting or changing dose, with more frequent monitoring for CKD or elderly patients.
Q: Can I switch to an ARB if I get a cough?
A: Yes — clinicians commonly switch to an ARB such as losartan when an ACE‑inhibitor cough is intolerable.
Visual Guide
What visual aids help patients and clinics use lisinopril safely?
Suggested infographic elements include a PBS pricing ladder showing typical out‑of‑pocket versus concessional costs for generic lisinopril compared with private brand pricing.
Another helpful visual is a pharmacy distribution map contrasting urban chain access with rural independent and mail‑order timelines.
A monitoring timeline graphic is useful: baseline labs, follow‑up at 1–2 weeks, then three‑monthly or as clinically indicated.
Design notes: use clear Australian icons and include the INN lisinopril alongside common brand names such as Zestril for recognition.
Make a printable A4 pharmacist counselling sheet emphasising pregnancy warnings, the cough side effect and when to seek urgent care for angioedema.
Storage & Transport
Household Storage Under Australian Climate
How should patients store lisinopril at home?
Store tablets at room temperature between 15–30°C and protect them from moisture and direct light.
Avoid leaving tablets in bathrooms or cars during hot Australian summers to prevent heat and humidity exposure.
Keep all medicines out of reach of children and check expiry dates before use.
Oral solutions should follow the manufacturer's label for storage and discard instructions.
Cold‑Chain Logistics For Pharmacies
Do lisinopril tablets need refrigeration during distribution?
Tablets do not require refrigeration but pharmacies should maintain ambient storage with humidity control to preserve product integrity.
Rural suppliers and mail‑order services should package stock to avoid prolonged heat exposure in transit, especially in summer postal conditions.
Pharmacies must follow Therapeutic Goods storage guidance when handling and dispatching products.
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
How should pharmacists discuss lisinopril with patients?
Use patient‑centred, evidence‑based counselling that explains INN and brand names, the dosing schedule and likely side effects such as cough and dizziness.
Cover the monitoring plan including blood pressure checks and baseline and follow‑up blood tests for creatinine and potassium.
Highlight the pregnancy warning, advise on missed doses and outline when to seek urgent care for allergic reactions or angioedema.
Discuss PBS options and cost considerations to support adherence.
National Health Authority Recommendations
Which national recommendations apply to prescribing and monitoring?
Australian guideline positions and TGA/PBS frameworks support ACE inhibitors as first‑line therapy for many patients with hypertension and heart failure with reduced ejection fraction.
Avoid combination with sacubitril and ensure contraception and pregnancy planning are addressed prior to long‑term therapy.
Document monitoring results and communicate with the prescribing GP or specialist during titration and when adverse events occur.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-9 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-7 days |
| Wollongong | New South Wales | 5-7 days |
| Sunshine Coast | Queensland | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Cairns | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |
Conclusion And Practical Takeaways
Many patients with hypertension and heart failure benefit from ACE inhibitors such as lisinopril when used at guideline‑recommended doses and monitored appropriately.
Prescribers should start conservatively in the elderly and those with renal impairment and arrange early follow‑up blood tests to check creatinine and potassium.
Persistent dry cough is a common reason for switching to an ARB, and rare but serious risks such as angioedema and severe renal dysfunction require urgent attention.
Cost and PBS listing strongly influence persistence in Australia, so discuss subsidised generic options where clinically appropriate to improve adherence.
Pharmacists are central to counselling on dosing, monitoring and storage, and can support telehealth and mail‑order services for patients in rural and regional areas.