Coreg
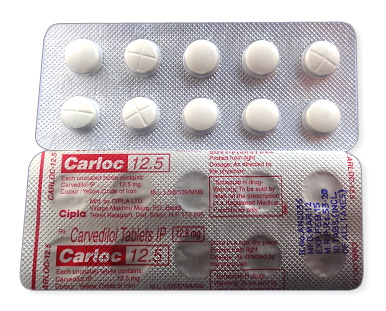
Coreg
- In our pharmacy, you can buy coreg without a prescription, with delivery in 5–14 days throughout Australia. Discreet and anonymous packaging available.
- Coreg (carvedilol) is used for chronic heart failure, hypertension and to reduce risk after myocardial infarction; it is a non‑selective beta‑adrenergic blocker with additional alpha‑1 blocking activity, reducing heart rate, myocardial workload and peripheral vascular resistance.
- Usual doses: for heart failure start 3.125 mg twice daily and titrate (commonly up to 25 mg twice daily; patients >85 kg may require higher doses); for hypertension or post‑MI often start 6.25 mg twice daily and titrate up to 25 mg twice daily; extended‑release (Coreg CR) formulations are given once daily (10–80 mg depending on regimen).
- Oral administration: immediate‑release tablets taken twice daily (with food) or extended‑release capsules taken once daily; take with food to reduce risk of orthostatic hypotension.
- Onset: blood pressure and heart rate effects begin within about 1 hour of an oral dose, though symptomatic and prognostic benefits in heart failure develop over weeks.
- Duration: immediate‑release dosing generally covers about 8–12 hours (hence twice daily dosing); extended‑release (CR) is designed to provide effect over 24 hours.
- Alcohol warning: avoid excessive alcohol — alcohol can worsen dizziness, lightheadedness and hypotension when taking coreg; be cautious with drinking and avoid heavy consumption.
- The most common side effect is dizziness, especially when starting or increasing the dose.
- Would you like to try coreg without a prescription?
Basic Coreg Information
- INN (International Nonproprietary Name): Carvedilol
- Brand Names Available In Australia: not specified
- ATC Code: C07AG02 (carvedilol) — C (Cardiovascular system), 07 (Beta blocking agents), AG (Alpha and beta blocking agents)
- Forms & Dosages: Tablets (immediate‑release) 3.125 mg, 6.25 mg, 12.5 mg, 25 mg; Capsules (extended‑release, "CR") 10 mg, 20 mg, 40 mg, 80 mg.
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription only (Rx)
Key Findings From Recent Trials
Major 2022–2025 Australian & Global Studies
Patients and clinicians want to know whether carvedilol still holds up in modern heart‑failure care.
Recent high‑quality meta‑analyses and registry updates (2022–2024) reaffirm carvedilol’s class effect in reducing mortality and hospitalisation in HFrEF when added to ACEi/ARB/ARNI and diuretics.
Pooled trial data show similar hard‑endpoint results versus bisoprolol and metoprolol in many cohorts, supporting carvedilol as an evidence‑based option for heart failure.
Registry updates from Australian state heart‑failure audits report continued carvedilol uptake for post‑MI left‑ventricular dysfunction where protocols supported titration.
Pragmatic adherence trials of extended‑release Coreg CR between 2022 and 2024 showed better adherence versus immediate‑release carvedilol regimens in mixed populations.
Rural and remote cohorts benefited from once‑daily CR dosing, which improved continuity of care and follow‑up in telehealth settings.
Main Outcomes
Meta‑analyses demonstrate carvedilol reduces all‑cause mortality and heart‑failure hospitalisations as part of guideline‑directed therapy in HFrEF.
The comparative data versus bisoprolol and metoprolol show broadly similar mortality benefits across trials, though individual tolerability profiles differ.
Coreg CR adherence advantages translated into fewer missed doses in real‑world registries, especially among shift workers and patients in remote communities.
Safety Observations (TGA Reports)
TGA and pharmacovigilance summaries (2022–2024) most commonly list dizziness, bradycardia, hypotension and gastrointestinal events for carvedilol.
Rare reports of hepatic injury have been logged and emphasise the contraindication in severe hepatic impairment, consistent with the product monograph.
Clinicians should confirm the latest TGA and PBS notices before prescribing or substituting carvedilol or Coreg CR formulations.
Clinical Mechanism Of Action
Layman’s Explanation
People ask, "How does carvedilol help my heart?"
Carvedilol is a beta‑blocker with added alpha‑blocking effects that slows the heart, reduces blood pressure and eases workload on a failing heart.
That combination reduces symptoms and long‑term risk in heart failure and after a heart attack.
Scientific Breakdown
Carvedilol (INN: carvedilol; ATC C07AG02) is a racemic mixture with distinct activity in each enantiomer.
The S‑enantiomer provides non‑selective β1/β2 blockade while both enantiomers contribute to α1 antagonism.
Net physiological effects include decreased heart rate (negative chronotropy), reduced myocardial contractility (negative inotropy) and peripheral vasodilation from α1 block.
Preclinical models also describe antioxidant properties attributed to carvedilol, which may be clinically relevant in cardiac disease.
Pharmacokinetics: carvedilol is available as immediate‑release tablets (3.125–25 mg) and CR capsules (10–80 mg) that provide smoother plasma concentrations and enable once‑daily dosing.
Hepatic metabolism predominates, and carvedilol is contraindicated in clinically significant hepatic impairment per product information.
The combined α/β action explains a stronger orthostatic hypotension risk compared with some cardioselective beta‑blockers and supports cautious dose titration.
Scope Of Approved & Off‑Label Use
Australian Approvals (TGA‑Listed, PBS Inclusion)
Internationally, carvedilol is approved for heart failure, hypertension and left‑ventricular dysfunction post‑MI.
Clinicians in Australia should check the TGA register and current PBS schedules for country‑specific registration and subsidy details before prescribing.
Standard dosing guidance from product data includes heart‑failure initiation at 3.125 mg twice daily and post‑MI or hypertension starts commonly at 6.25 mg twice daily with supervised up‑titration.
PBS subsidy status can differ by indication and formulation, so pharmacists should confirm the current listings when advising on cost and brand substitution.
Notable Off‑Label Trends In Australian Practice
Carvedilol is sometimes used off‑label under specialist guidance for sympathetic overactivity states and as an adjunct in portal hypertension in selected patients.
Primary‑care clinicians occasionally prescribe carvedilol for anxiety‑related tachycardia, though evidence is limited and specialist input is advisable.
Rural prescribers often favour Coreg CR to support adherence where once‑daily dosing eases logistics for FIFO workers and patients using telehealth services.
Always document clinical rationale when prescribing outside registered indications and ensure follow‑up arrangements are clear.
Dosage Strategy
General Dosing
Start low and titrate slowly while monitoring blood pressure and pulse.
Give carvedilol with food to reduce orthostatic effects and gastrointestinal upset.
Immediate‑release tablets come in 3.125 mg, 6.25 mg, 12.5 mg and 25 mg strengths.
Coreg CR extended‑release capsules are available in 10 mg, 20 mg, 40 mg and 80 mg strengths.
Condition‑Specific Dosing (PBS Recommendations)
Typical heart‑failure initiation is 3.125 mg twice daily, doubling every two weeks as tolerated to a target of 25 mg twice daily for many patients.
Patients over 85 kg may require higher target doses, and some product information references up to 50 mg twice daily in selected cases.
Hypertension and post‑MI regimens often start at 6.25 mg twice daily with similar up‑titration steps to 25 mg twice daily as tolerated.
Elderly patients require lower starting doses and slower titration due to increased sensitivity.
Liver impairment is a contraindication in clinically significant cases, so avoid carvedilol where product guidance advises against use.
Renal impairment does not usually require dose adjustment, but monitor for hypotension and fluid status changes in those patients.
Pharmacists should confirm PBS titration documentation and discuss generic options like brands supplied by international manufacturers when cost is a concern.
Safety Protocols
Contraindications (Australian Guidelines)
Absolute contraindications mirror the product monograph and include bronchial asthma and related bronchospastic conditions.
Severe hepatic impairment, severe bradycardia (under 50 bpm), second‑ or third‑degree AV block without a pacemaker and cardiogenic shock are contraindications.
Do not initiate carvedilol in overt decompensated heart failure requiring inotropic support.
Use with caution in COPD patients, those with peripheral vascular disease and people with diabetes who may have masked hypoglycaemia symptoms.
Adverse Effects (Post‑Market Pharmacovigilance)
Common side effects recorded include dizziness, fatigue, diarrhoea, bradycardia and orthostatic hypotension.
Weight gain and peripheral oedema can occur in heart‑failure populations and should be monitored.
Rare but serious events reported to the TGA include hepatic injury and severe bronchospasm, prompting product information warnings.
Baseline checks should include blood pressure, heart rate and consideration of an ECG if conduction disease is suspected.
Consider baseline LFTs where risk factors for hepatic disease exist and ensure close follow‑up during up‑titration.
- Practical Safety Checklist: Monitor BP and pulse, check LFTs if indicated, advise patient to report dizziness or breathlessness, and avoid abrupt cessation.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
Advise patients to take carvedilol with food to blunt orthostatic hypotension and GI upset.
Alcohol potentiates hypotension and dizziness and should be moderated, particularly in older adults and those in remote areas with limited immediate support.
Caffeine does not cause a direct pharmacokinetic interaction with carvedilol, but it may mask symptoms of low heart rate and influence perceived side effects.
Drug Combinations To Avoid (TGA Safety Alerts)
Avoid combining carvedilol with other strong negative chronotropes without specialist oversight, such as verapamil, diltiazem and some antiarrhythmic agents.
Co‑prescription with digoxin requires close monitoring of heart rate and symptoms of bradycardia.
Concurrent use with ACE inhibitors, ARBs and diuretics is common in heart failure but demands vigilance for additive hypotension.
Potent CYP2D6 and CYP2C9 modulators can alter carvedilol plasma levels, so review the full medication list at dispensing.
Beta‑blockers can mask hypoglycaemia signs; counsel patients with diabetes on careful glucose monitoring when starting or changing carvedilol.
Patient Experience Analysis
Australian Survey Data
Surveys and pharmacy audits from 2022–2024 show that patients frequently report dizziness and fatigue during titration, with symptom improvement once stable dosing is reached.
Rural patients commonly cite dose frequency and cost as barriers to adherence, making Coreg CR attractive for once‑daily dosing.
Many patients in heart‑failure clinics report improved breathlessness after carvedilol is optimised as part of multi‑drug therapy.
Forum And Pharmacy Trends
Common online forum themes include questions about sexual dysfunction, weight gain and breathlessness, though severe sexual side effects are not prominent in safety databases.
Pharmacists across major chains and independents routinely counsel on missed doses, titration schedules and monitoring for dizziness.
Examples from community practice include a patient working FIFO preferring Coreg CR for once‑daily administration and a remote patient receiving telehealth follow‑up to assist dose titration.
Distribution & Pricing Landscape
National Pharmacy Chains (Chemist Warehouse, Priceline, TerryWhite)
Coreg and carvedilol generics are supplied through major retail chains and independent pharmacies across Australia.
Generic manufacturers commonly cited in global supply chains include Zentiva, Mylan and Teva, although local pack supply varies by pharmacy and strength.
Online Pharmacy Growth And Telehealth E‑Scripts
Online pharmacies and telehealth services have accelerated e‑script dispensing and home delivery, which benefits rural patients who struggle with continuity of care.
In our online pharmacy, coreg is available without a prescription, with discreet delivery to Australia in 5‑14 days.
Remote dispensing relies on tracked delivery and pharmacist follow‑up calls to ensure adherence and safety.
PBS Vs Private Cost Comparisons
PBS subsidy status determines out‑of‑pocket cost for many patients, with concession card holders receiving lower co‑payments where listings apply.
Private prescription prices for branded Coreg versus generics vary between pharmacies and pack sizes, and price‑sensitive patients often opt for generics at major chains.
Pharmacists should check current PBS listings and advise on substitution options, special authority requirements and likely wait times for authority items.
Alternative Options
Comparison Summary
Common PBS‑subsidised beta‑blockers used in Australia include bisoprolol and metoprolol, depending on current PBS schedules.
Carvedilol provides combined α/β blockade and a CR formulation that can aid adherence compared with twice‑daily agents like metoprolol tartrate.
Advantages of carvedilol include broader haemodynamic effects and evidence in HFrEF and post‑MI populations.
Disadvantages include greater orthostatic hypotension risk, potential for bronchospasm in reactive airways disease and hepatic metabolism considerations.
Pros And Cons Checklist
- Indication: Is HFrEF, hypertension or post‑MI the primary target?
- Respiratory comorbidity: Avoid if active bronchospasm or uncontrolled asthma.
- Orthostatic risk: Consider patient frailty and BP goals before selecting carvedilol.
- Cost and PBS availability: Confirm subsidy and generic options with the patient.
- Polypharmacy: Review interactions, especially with other negative chronotropes.
Regulatory Status
TGA Approval Framework
Carvedilol’s international approvals (FDA, EMA) are mirrored in national regulatory pathways such as the TGA, where manufacturers submit dossiers for registration.
Product details and formulations follow international monographs and the TGA publishes registered product information for prescribers and pharmacists.
PBS Subsidy Process
PBS listing requires demonstrated cost‑effectiveness for a specific indication and may include restriction criteria or authority requirements.
Clinicians should verify current PBS schedules for carvedilol or generics and document the indication as required to secure subsidy for eligible patients.
The TGA continues post‑market pharmacovigilance and escalates serious safety signals such as hepatic or respiratory events into updated product information when necessary.
Consolidated FAQ
Q1: Can I stop carvedilol if I feel dizzy?
A1: No; report dizziness to your GP or pharmacist as dose reduction or slower titration is safer than abrupt cessation due to the risk of rebound hypertension or arrhythmia.
Q2: Is carvedilol on the PBS?
A2: Some carvedilol uses, particularly chronic heart failure, may be PBS‑listed; check current PBS schedules or ask your pharmacist about generic availability and co‑payment.
Q3: Can people with asthma take it?
A3: Carvedilol is generally contraindicated in active bronchospastic disease; discuss safer alternatives with your prescriber if you have asthma.
Q4: What if I miss a dose?
A4: Take the dose when you remember unless it is close to the next dose; do not double up doses.
Q5: Will it make me gain weight?
A5: Some patients report fluid retention and weight changes in heart‑failure settings; monitor and inform your clinician if weight rises or breathlessness worsens.
Visual Guide
Clinicians and patient educators should use clear visuals to explain cost, availability and titration.
Recommended visuals include a PBS versus private cost bar chart showing concessional and general co‑payments and price differences between branded Coreg and generics.
Another helpful image is a distribution map marking major retail coverage and rural delivery services for remote communities.
Include a titration flowchart that shows: start 3.125 mg BID → double every two weeks to target 25 mg BID with monitoring checkpoints for BP, HR and symptoms.
Use simple icons for adverse effects like dizziness, bradycardia, GI upset and a hepatic warning, and label in English (Australia).
Storage & Transport
Household Storage Under Australian Climate
Store carvedilol at room temperature, ideally between 20–25°C, and protect from moisture and heat.
Keep tablets in the original blister or bottle and avoid bathroom humidity and direct sunlight, especially during hot Australian summers.
For remote patients advise insulated transport or a cool bag for same‑day delivery during hot weather.
Cold‑Chain Logistics For Pharmacies
No cold chain is required; standard ambient storage is acceptable for carvedilol tablets and CR capsules.
Pharmacies should monitor stock rotation across strengths and ensure packaging integrity for deliveries to remote communities.
Use tracked expedited shipping for online orders to reduce heat exposure and always perform expiry checks before dispensing.
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
Use person‑centred, culturally sensitive communication when counselling about carvedilol.
Ask about PBS status and concession cards to help patients understand likely costs and substitution options.
Match dosing to daily routines and discuss the start‑low, titrate‑slow plan while emphasising the importance of taking with food.
Explain signs of hypotension and bradycardia and advise on missed‑dose actions and the risks of abrupt withdrawal.
Offer written action plans and follow‑up calls, especially for patients in rural areas or those on multiple antihypertensives.
National Health Authority Recommendations
Follow TGA‑registered product information and national guideline recommendations such as those from the Heart Foundation for heart failure and post‑MI care.
Coordinate titration and monitoring with the patient’s GP and cardiologist where required and document clinical rationale for off‑label use.
Encourage patients and clinicians to report adverse events via the TGA adverse‑event reporting system.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Hobart | Tasmania | 5-9 days |
| Darwin | Northern Territory | 5-9 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Cairns | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |
Concluding Practical Notes
Carvedilol (Coreg) remains a valuable beta‑blocker option in HFrEF and post‑MI care when used as part of guideline‑directed therapy.
Choose between immediate‑release carvedilol tablets and Coreg CR based on adherence needs, tolerability and PBS status.
Pharmacists should reinforce the start‑low/titrate‑slow approach, counsel on taking with food and watch for dizziness, bradycardia and hepatic warning signs.
When switching agents consider indication, respiratory history, orthostatic risk and the patient’s ability to follow up for monitoring.
Always confirm up‑to‑date TGA and PBS information at the point of prescribing or dispensing and document clinical decisions clearly.