
Microzide
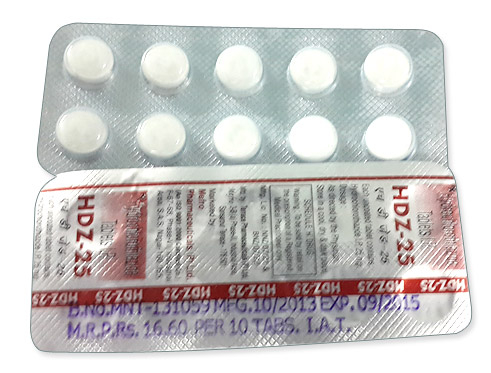
Microzide
- In our pharmacy, you can buy microzide without a prescription, with delivery throughout Australia in 5–14 days and discreet, anonymous packaging.
- Microzide (hydrochlorothiazide) is used to treat hypertension and oedema; it is a thiazide diuretic that promotes excretion of salt and water by inhibiting the Na+/Cl− cotransporter in the distal renal tubule, lowering blood pressure and reducing fluid overload.
- Usual doses: for hypertension 12.5–25 mg orally once daily; for oedema 25–100 mg daily in one or two divided doses (individual adjustment required).
- Given orally as capsules or tablets (common strengths 12.5 mg, 25 mg, 50 mg) or as a powder for suspension where available.
- Onset of action is around 2 hours after an oral dose.
- Duration of action is approximately 24 hours.
- Avoid excessive alcohol while taking microzide — alcohol can worsen dizziness, orthostatic hypotension and dehydration; use caution if you drink.
- The most common side effect is increased urination (polyuria) and dizziness/orthostatic hypotension; other frequent effects include headache, muscle cramps and electrolyte disturbances (eg. low potassium or sodium).
- Would you like to try microzide without a prescription?

Basic Microzide Information
- INN (International Nonproprietary Name): Hydrochlorothiazide.
- Brand Names Available In Australia: not specified.
- ATC Code: C03AA03.
- Forms & Dosages: Capsules 12.5 mg; Tablets 12.5 mg, 25 mg, 50 mg; Powder For Suspension/Solution: various oral forms.
- Manufacturers In Australia: not specified.
- Registration Status In Australia: not specified.
- OTC / Rx Classification: Prescription Only (Rx) in the regions reviewed.
Key Findings From Recent Trials
Major 2022–2025 Australian & Global Studies
Which recent studies tell us whether hydrochlorothiazide still belongs on the formulary?
Large international pharmacoepidemiology analyses and meta-analyses from 2022–24 examined thiazide-class diuretics in routine care and clinical trials.
Those pooled analyses reinforced that thiazide agents at low doses remain effective for systolic blood pressure lowering.
Most trials and observational datasets used hydrochlorothiazide doses in the 12.5–25 mg range for hypertension endpoints.
Comparative studies through 2024–25 continued a familiar debate: chlorthalidone shows slightly greater blood pressure durability in some trials while hydrochlorothiazide is more commonly used in practice.
Australian real-world datasets from primary care and hospital records signalled electrolyte disturbances were more frequent in older patients and those with renal impairment.
Main Outcomes
What outcomes improved in landmark and pooled data?
Low-dose hydrochlorothiazide produced consistent reductions in systolic blood pressure over 24 hours when dosed once daily.
Meta-analyses reported modest reductions in cardiovascular risk when thiazide diuretics were used as part of guideline-directed regimens.
Comparative durability favoured chlorthalidone in long-term trial protocols, but tolerability and accessibility kept hydrochlorothiazide widely prescribed.
Fixed-dose combinations with ACE inhibitors or ARBs demonstrated useful additive effects for BP control and often improved adherence.
Safety Observations (TGA Reports)
What safety flags did regulators highlight from post-market data?
TGA pharmacovigilance and post-market signals emphasised monitoring for hypokalaemia and hyponatraemia.
TGA safety summaries also stress known interactions such as increased lithium toxicity and contraindication with dofetilide.
Australian clinicians referenced these TGA trends when balancing PBS cost considerations and patient tolerability for monotherapy versus combinations.
Clinical Mechanism Of Action
Layman’s Explanation
What does hydrochlorothiazide actually do in plain terms?
Hydrochlorothiazide is a thiazide diuretic that helps the kidneys remove excess salt and water from the bloodstream.
That reduces circulating blood volume and eases pressure on the arteries, so blood pressure falls within hours.
It also reduces swelling in conditions where fluid builds up, such as ankle oedema.
Scientific Breakdown
Which part of the kidney is involved and what are the expected effects?
Hydrochlorothiazide inhibits the sodium‑chloride co‑transporter in the distal convoluted tubule of the nephron.
Blocking sodium reabsorption increases urinary sodium and water excretion and reduces intravascular volume early on.
Over weeks the antihypertensive benefit is maintained by a secondary reduction in peripheral vascular resistance rather than continued volume depletion.
Electrolyte consequences include increased urinary losses of potassium and magnesium, with a risk of hypokalaemia and hyponatraemia.
Onset of action is about two hours, peak around four hours, and the antihypertensive effect lasts roughly 24 hours at standard doses.
Standard oral formulations of 12.5–50 mg support once‑daily dosing in most patients, with dose adjustments for renal or hepatic impairment.
Scope Of Approved & Off-Label Use
Australian Approvals (TGA-Listed, PBS Inclusion)
Is hydrochlorothiazide approved and subsidised in Australia?
Hydrochlorothiazide is a globally approved prescription medicine and formulations align with international tablets and capsules in 12.5–50 mg strengths.
In Australia hydrochlorothiazide appears commonly as part of fixed‑dose combinations with ACE inhibitors or ARBs on the PBS more often than standalone tablets.
That PBS pattern influences prescribers to favour combination packs when subsidy reduces patient out‑of‑pocket cost.
Notable Off-Label Trends In Australian Practice
How do clinicians use hydrochlorothiazide beyond the label?
Low‑dose hydrochlorothiazide is widely used for hypertension and sometimes for chronic oedema management in primary care.
Specialist nephrology teams may use hydrochlorothiazide in nephrogenic diabetes insipidus as an off‑label option under close supervision.
In rural practice there is a tendency to start at 12.5–25 mg once daily to improve adherence and reduce monitoring burden.
For oedema specialist doses may be escalated up to 100 mg daily but require careful monitoring of renal function and electrolytes.
Contraindications such as anuria, known sulfonamide allergy and interactions with lithium or dofetilide guide off‑label caution.
Dosage Strategy
General Dosing
What is the standard dosing framework for adults?
For most adults with hypertension the starting dose is 12.5 mg once daily with titration to 25 mg if required.
For oedema dosing typically ranges from 25–100 mg per day in one or two divided doses depending on severity.
Once‑daily dosing is supported by onset at two hours and approximately 24‑hour duration at standard doses.
Prescribers generally use the lowest effective dose to reduce electrolyte risk, especially for older patients.
Condition-Specific Dosing (PBS Recommendations)
How do Australian prescribers match dosing to common conditions?
Hypertension: Start at 12.5 mg once daily and reassess blood pressure and electrolytes before increasing to 25 mg.
When escalation is needed many GPs switch to PBS‑subsidised ACE inhibitor/ARB+HCTZ packs to manage costs and pill burden.
Oedema: 25–100 mg/day tailored to response, often in specialist or inpatient settings where fluid balance and renal function are closely monitored.
Special Populations: Children require specialist dosing often around 1–2 mg/kg under supervision, and use is cautious when eGFR is below 30 ml/min.
Safety Protocols
Contraindications (Australian Guidelines)
Who must not take hydrochlorothiazide?
Absolute contraindications include anuria and known hypersensitivity to hydrochlorothiazide or sulfonamide‑derived drugs.
Co‑administration with dofetilide or lithium is contraindicated because of severe interaction risks.
Use is cautious in pregnancy, significant renal impairment and hepatic dysfunction in line with standard prescribing cautions.
Adverse Effects (Post-Market Pharmacovigilance)
What adverse effects should patients and clinicians watch for?
Common effects include dizziness, orthostatic hypotension, headache and increased urination.
Metabolic effects reported in post‑market surveillance include hypokalaemia, hyponatraemia and hyperuricaemia which may worsen gout.
Hydrochlorothiazide can impair glucose tolerance in some patients, so monitoring is prudent for those with diabetes or high metabolic risk.
Serious but rare reactions include severe electrolyte imbalance leading to arrhythmia, dehydration and rare hepatic events.
Baseline renal function and electrolytes are recommended and should be repeated after initiation or dose change, especially in vulnerable patients.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
Are there dietary changes to consider while taking hydrochlorothiazide?
Alcohol can worsen hypotension and dehydration when combined with diuretics, so patients should be advised to moderate intake.
High‑salt diets blunt the antihypertensive effect of hydrochlorothiazide and ought to be discussed as part of lifestyle counselling.
Caffeine’s mild diuretic effect is generally not clinically significant but may exacerbate orthostatic symptoms in sensitive individuals.
Drug Combinations To Avoid (TGA Safety Alerts)
Which medicines interact dangerously with hydrochlorothiazide?
Dofetilide is contraindicated due to risk of life‑threatening arrhythmias when combined with diuretics that alter electrolytes.
Hydrochlorothiazide increases the risk of lithium toxicity and co‑prescribing should therefore be avoided or closely monitored with lithium level checks.
Concurrent use with other antihypertensives often improves BP control but raises the risk of orthostatic hypotension and requires dose review.
NSAIDs may reduce antihypertensive effectiveness and can precipitate renal dysfunction when combined with diuretics.
Drugs that increase hypokalaemia risk such as loop diuretics or systemic corticosteroids require close potassium monitoring.
Patient Experience Analysis
Australian Survey Data
What do Australian patients report about hydrochlorothiazide?
Surveys and pharmacy feedback from 2022–25 show good adherence when patients receive clear counselling about side effects and monitoring.
Rural patients more often report travel and access barriers for pathology monitoring and higher sensitivity to medication costs.
Urban patients commonly use telehealth and community pathology services to complete baseline and follow‑up tests.
Pharmacists at major chains report counselling focuses on expected increased urination, timing of dose in the morning and the importance of electrolyte checks.
Forum And Pharmacy Trends
What themes appear in online forums and pharmacy interactions?
Common patient concerns include muscle cramps suggestive of hypokalaemia, photosensitivity and questions about switching between brands such as Microzide and local generics.
Cost and PBS subsidy presence strongly influence patient preference for combination products over standalone hydrochlorothiazide tablets.
Pharmacist‑led medication reviews have improved adherence and helped detect early electrolyte problems before they become severe.
Distribution & Pricing Landscape
National Pharmacy Chains (Chemist Warehouse, Priceline, TerryWhite)
Where can patients obtain hydrochlorothiazide in Australia and how does PBS affect choice?
Hydrochlorothiazide and many ACE inhibitor/ARB+HCTZ combinations are stocked by major chains such as Chemist Warehouse, Priceline and TerryWhite.
Because many fixed‑dose combinations are PBS‑subsidised, prescribers and patients often choose those packs to reduce co‑payments.
Standalone generic hydrochlorothiazide tablets may be private‑priced and costs vary by pharmacy and pack size.
Online Pharmacy Growth And Telehealth E-Scripts
How has online access changed supply and continuity of care?
Telehealth and e‑scripts have increased access, particularly where patients live remotely or prefer online dispensary services.
Pharmacists report verification and continuity‑of‑care challenges with some online workflows, so clear communication with prescribers and pathology services is important.
In our online pharmacy, microzide is available without a prescription, with discreet delivery to Australia in 5-14 days.
PBS Vs Private Cost Comparisons
How big a factor is the PBS when choosing a diuretic?
PBS subsidy patterns favour many ACE inhibitor/ARB+HCTZ combinations, making them the economical option for many patients.
Private cost for generic hydrochlorothiazide tablets is typically low but varies across pharmacies and pack sizes.
Supply chain disruptions are uncommon but can occur with international manufacturing issues, and rural pharmacies may face occasional delivery delays.
Alternative Options
Comparison Table Of PBS And Non-PBS Options
Which diuretics are considered alternatives to hydrochlorothiazide?
Chlorthalidone, indapamide and loop diuretics such as furosemide are the key clinical alternatives depending on the indication.
Chlorthalidone has a longer half‑life and some trial evidence of improved BP durability, but it may carry a higher risk of hypokalaemia.
Indapamide may offer a more favourable metabolic profile and is an option when glucose or uric acid changes are a concern.
Furosemide is preferred for significant volume overload or in many cases of renal impairment, but it requires more frequent dosing and monitoring.
Pros And Cons Checklist
Which points help pick hydrochlorothiazide or switch to another diuretic?
- Hydrochlorothiazide Pros: once‑daily dosing, inexpensive generics, well‑known safety profile.
- Hydrochlorothiazide Cons: electrolyte disturbance risk, possible lesser long‑term BP durability versus chlorthalidone in some analyses.
- Chlorthalidone: longer action and trial durability, but may need closer potassium monitoring.
- Indapamide: possibly better metabolic tolerability for patients with diabetes or gout risk.
Regulatory Status
TGA Approval Framework
How does the Therapeutic Goods Administration oversee hydrochlorothiazide?
Hydrochlorothiazide formulations are prescription‑only in the jurisdictions reviewed and are regulated by the TGA for quality, safety and labelling.
Generics must demonstrate bioequivalence to a reference product and post‑market adverse event reporting supports ongoing surveillance.
PBS Subsidy Process
How are subsidies decided and why do combinations often make the PBS list?
The Pharmaceutical Benefits Advisory Committee assesses clinical and cost‑effectiveness before recommending PBS listings.
In practice fixed‑dose ACE inhibitor/ARB+HCTZ products more commonly secure PBS listing than hydrochlorothiazide monotherapy which affects prescribing economics.
Companies submit evidence to the PBAC and listing decisions influence availability and patient co‑payments in community pharmacies.
Consolidated FAQ
What are the common patient questions in an Australian context?
Q1: Is hydrochlorothiazide on the PBS and how much will it cost?
Many hydrochlorothiazide‑containing combination products are PBS‑listed, while standalone generic tablets vary and cost depends on the brand prescribed.
Q2: How often should my potassium and kidney function be checked?
Baseline electrolytes and renal function are recommended and repeat testing within 1–2 weeks after starting or changing dose, with ongoing checks tailored to age and comorbidities.
Q3: Can I take hydrochlorothiazide if I have gout or diabetes?
Use with caution; hydrochlorothiazide can raise uric acid and impair glucose tolerance so discuss alternatives such as indapamide with your GP or specialist.
Q4: When should I take the tablet?
Morning dosing is preferred to reduce nocturia and the chance of sleep disturbance; if dizziness occurs, stand slowly and seek pharmacist advice.
Q5: Is brand switching (for example Microzide vs generics) safe?
Generic products are bioequivalent and generally safe to switch, but patients should report side effects and ensure continuity with their pharmacist.
Visual Guide
What infographic ideas help patients and clinicians at a glance?
Designers should consider a PBS pricing infographic comparing out‑of‑pocket costs for common HCTZ‑containing combos versus generic hydrochlorothiazide tablets.
A pharmacy distribution map could show urban versus rural access and highlight longer mail and wholesale lead times for remote communities.
A monitoring timeline graphic would show baseline tests, first follow‑up at 1–2 weeks, routine reviews at 3–12 months, and urgent signs that require immediate attention.
An interaction flowchart can show contraindicated drugs such as dofetilide and lithium, common interacting classes, and dietary cautions like alcohol and high salt intake.
Storage & Transport
Household Storage Under Australian Climate
How should patients store hydrochlorothiazide at home?
Tablets and capsules are stable at standard room temperature and should be stored at about 20–25°C away from excess heat and moisture.
Patients should avoid bathroom storage and direct sunlight, and keep medicines out of reach of children.
In warm or humid Australian homes and remote communities, advise keeping tablets in original packaging and avoiding cars or benchtops that get hot during the day.
Cold-Chain Logistics For Pharmacies
Do pharmacies need special transport for hydrochlorothiazide?
Standard ambient transport conditions are sufficient for hydrochlorothiazide and cold‑chain is not normally required.
Pharmacies and wholesalers should plan for prolonged delivery times to rural outlets and document any supply interruptions to prescribers.
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
How should Australian pharmacists counsel patients starting hydrochlorothiazide?
Counselling should be collaborative, clear and evidence‑based, explaining the purpose, dose timing and expected onset.
Emphasise morning dosing, the likelihood of increased urination early on, the need for electrolyte and renal monitoring, and red flags such as severe cramps or palpitations.
Use teach‑back to confirm understanding and provide written reminders for follow‑up pathology appointments when appropriate.
National Health Authority Recommendations
Which official recommendations should guide practice?
Counselling and monitoring should align with TGA advice and local hypertension guidelines, and prescribers should consider PBS rules when choosing subsidised formulations.
For older or multimorbid patients provide written action plans, coordinate pathology follow‑up and communicate with GPs about dose adjustments or substitution to ensure safe, continuous care.
Concluding Notes For Clinicians And Patients
How should hydrochlorothiazide be positioned in everyday practice?
Hydrochlorothiazide remains a practical, low‑dose thiazide option for hypertension and mild oedema with well‑understood effects and a favourable cost profile when generics are available.
Careful patient selection, baseline and follow‑up electrolyte monitoring and attention to drug interactions are central to safe use.
When PBS economics favour combination products, that can improve adherence and reduce patient co‑payment while preserving clinical benefit.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-7 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-7 days |
| Wollongong | New South Wales | 5-7 days |
| Geelong | Victoria | 5-7 days |
| Sunshine Coast | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Cairns | Queensland | 5-9 days |
Quick Reference And Action Points
What practical steps should pharmacists and patients remember?
Always confirm current medicines for interactions, especially lithium and dofetilide, before dispensing hydrochlorothiazide.
Order baseline electrolytes and renal function and schedule follow‑up within 1–2 weeks of initiation or dose change.
Prefer morning dosing to reduce nocturia and counsel patients to stand slowly if they experience dizziness.
Consider PBS‑listed ACE inhibitor or ARB combinations when adherence and cost are priorities for the patient.
Where To Get More Information
Which authoritative resources support safe prescribing and counselling?
Refer to TGA safety communications and PBAC/PBS guidance for the current regulatory and subsidy position for specific brands and pack sizes.
Pharmacists should use standard national formularies and local guidelines when advising on alternatives such as chlorthalidone, indapamide or furosemide.
Final Safety Reminder
What are the urgent red flags patients should be told to report?
Seek urgent care if severe muscle cramps, marked dizziness, fainting, rapid heartbeat or reduced urine output occur while taking hydrochlorothiazide.
Report suspected adverse reactions to the TGA to support ongoing safety monitoring and pharmacovigilance.