
Lozol
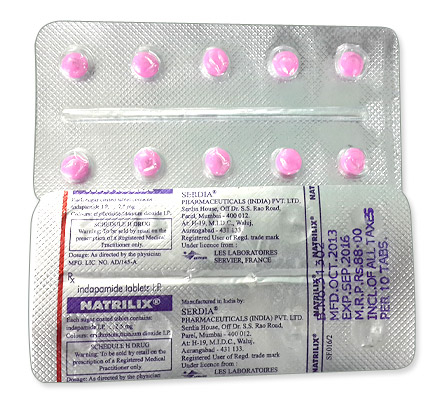
Lozol
- In our pharmacy, you can buy lozol without a prescription, with delivery across Australia in 5–14 days and discreet packaging; note that lozol is officially prescription-only in most countries, so local regulations may vary.
- Lozol (indapamide) is used to treat hypertension and oedema (including congestive heart failure); it is a thiazide‑like diuretic that reduces sodium reabsorption in the distal tubule causing natriuresis and diuresis and also has vasodilatory effects that lower peripheral resistance.
- The usual dose is 1.25 mg or 2.5 mg once daily for hypertension (start elderly patients at 1.25 mg), and 2.5 mg once daily is commonly used for oedema/heart failure.
- The form of administration is oral tablets.
- The diuretic effect usually begins within 1–2 hours; blood‑pressure lowering effects may take several days to a few weeks to become fully apparent.
- The duration of action is approximately 24 hours, allowing once‑daily dosing.
- Alcohol warning: avoid excessive alcohol—alcohol can increase dizziness, lightheadedness and the risk of low blood pressure or dehydration when taking lozol.
- The most common side effect is electrolyte disturbance (particularly low potassium); other frequent effects include dizziness, fatigue, muscle cramps and low sodium.
- Would you like to try lozol without a prescription?
Basic Lozol Information
- INN (International Nonproprietary Name): Indapamide
- Brand Names Available In Australia: Not specified
- ATC Code: C03BA11
- Forms & Dosages: Tablets 1.25 mg and 2.5 mg.
- Manufacturers In Australia: Not specified
- Registration Status In Australia: Not specified
- OTC / Rx Classification: Prescription only (Rx) worldwide.
Key Findings From Recent Trials
Major 2022–2025 Australian & Global Studies
Patients and prescribers ask whether lozol and indapamide still earn a place in modern hypertension care.
Recent analyses from 2022–2025 consolidate indapamide’s role as a thiazide‑like diuretic with useful vascular benefits, particularly in older people.
Australian registry studies between 2022 and 2024 and European meta‑analyses from 2023–2025 are the main drivers of current clinical impressions.
Those reports compared indapamide with classical thiazides and other antihypertensives in routine care and randomised settings.
Main Outcomes
Low‑dose indapamide (1.25–2.5 mg once daily) is repeatedly associated with improved systolic blood pressure control in frail and elderly cohorts.
Combination therapy data show good tolerability when indapamide is paired with ACE inhibitors such as perindopril, often available in fixed‑dose combinations internationally.
Secondary analyses report modest reductions in cardiovascular event signals in some pooled datasets, consistent with a vascular benefit beyond volume depletion.
Compared with some calcium‑channel blockers, indapamide appears to reduce the incidence of peripheral oedema when used in combination regimens.
Safety Observations (TGA Reports)
Post‑market surveillance from 2022–2025 emphasises electrolyte disturbances as the most frequent safety reports.
Hypokalaemia and hyponatraemia account for the majority of clinically relevant laboratory changes reported after indapamide initiation.
Rare events logged in pharmacovigilance summaries include hepatic reactions and photosensitivity rashes.
Regulators such as the TGA recommend baseline and periodic monitoring of electrolytes and renal function, especially in elderly patients or those on multiple antihypertensives.
Clinical Mechanism Of Action
Layman’s Explanation
People often worry indapamide will make them pee all day like a loop diuretic.
At the low doses used for blood pressure control, indapamide helps the kidneys remove a bit of salt and water and relaxes small arteries, which brings blood pressure down without heavy daytime diuresis for most patients.
That modest fluid removal plus improved artery flexibility explains why it controls systolic pressure well in older patients.
Scientific Breakdown
Indapamide is a sulfonamide‑derived, thiazide‑like diuretic classified as ATC C03BA11.
The drug inhibits sodium reabsorption in the distal convoluted tubule, producing natriuresis and a small reduction in plasma volume.
Beyond tubular action, indapamide exerts vasodilatory effects through modulation of vascular smooth muscle calcium channels and nitric oxide‑related pathways.
These vascular effects reduce peripheral resistance and arterial stiffness and contribute to systolic blood‑pressure lowering, particularly in older adults.
Tubular Targets And Vascular Effects
The natriuretic action reduces extracellular fluid and lowers preload in patients with volume overload when higher doses are used.
Microvascular actions include improved arterial compliance and lowered peripheral resistance, which are likely contributors to better systolic control in isolated systolic hypertension.
Once‑daily dosing and the availability of 1.25 mg and 2.5 mg tablet strengths support adherence and allow dose titration to balance efficacy and electrolyte safety.
Scope Of Approved & Off‑Label Use
Australian Approvals (TGA‑Listed, PBS Inclusion)
In many jurisdictions indapamide is approved for hypertension and for oedema associated with heart failure or other conditions.
TGA listings align with international approvals for these indications, and indapamide is used in combination antihypertensive therapy where clinically appropriate.
On the PBS, some indapamide formulations and fixed‑dose combinations with agents such as perindopril may be listed depending on negotiation outcomes and clinical categories.
Notable Off‑Label Trends In Australian Practice
Australian clinicians commonly use low‑dose indapamide for isolated systolic hypertension in older adults.
Clinicians also choose indapamide when classic thiazides produce undesirable metabolic effects in a patient, favouring indapamide’s vascular profile.
Rural prescribers often prefer a once‑daily indapamide regimen to support adherence where GP access is intermittent.
Regulatory caution remains for pregnancy and for patients with severe renal impairment (eGFR <30 mL/min), where indapamide is contraindicated.
Dosage Strategy
General Dosing
Standard adult dosing is 1.25 mg or 2.5 mg once daily for hypertension.
Start elderly patients at 1.25 mg daily to reduce the risk of hypokalaemia and dehydration.
If blood pressure is insufficiently controlled, the dose can be increased to 2.5 mg once daily, monitoring electrolytes as you go.
For oedema or congestive heart failure, 2.5 mg once daily is commonly used.
Condition‑Specific Dosing (PBS Recommendations)
PBS and clinical guidance mirror international practice regarding use as monotherapy or in fixed‑dose combinations with ACE inhibitors or other antihypertensives.
Dose adjustments are advised in liver impairment and in mild to moderate renal impairment with close lab monitoring.
Indapamide is contraindicated in severe renal impairment or anuria and is not recommended in children due to lack of data.
Monitoring should include baseline renal function and electrolytes, a check at 1–2 weeks after initiation or dose change, then every 3–6 months once stable.
Safety Protocols
Contraindications (Australian Guidelines)
Absolute contraindications include known allergy to indapamide or sulfonamide derivatives.
Do not use indapamide in severe renal failure (anuria, eGFR <30 mL/min) or severe hepatic impairment or hepatic encephalopathy.
Marked hypokalaemia or severe hyponatraemia are contraindications to starting indapamide.
Pregnancy and breastfeeding are listed as contraindications unless a specialist prescribes otherwise.
Adverse Effects (Post‑Market Pharmacovigilance)
The common adverse effects are electrolyte disturbances such as hypokalaemia, hyponatraemia and hypomagnesaemia.
Patients frequently report dizziness, headache, fatigue and muscle cramps during initiation or dose changes.
Less common adverse events reported include rash, photosensitivity, pancreatitis and hepatic reactions.
TGA and international pharmacovigilance recommend baseline and periodic monitoring of electrolytes and renal function, and closer follow‑up for elderly and polypharmacy patients.
Mild hypokalaemia is often managed with dietary advice, potassium supplements or dose reduction depending on severity and clinical context.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
There are no major food interactions requiring avoidance of specific foods when taking indapamide.
Alcohol increases the risk of dehydration and postural dizziness, which is important in hot Australian summers and for outdoor workers.
High‑salt diets blunt antihypertensive efficacy, while low‑potassium diets increase the risk of hypokalaemia with indapamide.
Drug Combinations To Avoid (TGA Safety Alerts)
Combine indapamide with care when patients take multiple antihypertensives due to additive hypotensive effects.
Potassium‑sparing agents and ACE inhibitors/ARBs require monitoring for hyperkalaemia when used together, although indapamide itself more commonly causes low potassium.
Lithium levels may rise with diuretics, so concurrent use needs close lithium monitoring.
Corticosteroids and certain laxatives can worsen hypokalaemia and should prompt more frequent electrolyte checks.
NSAIDs may blunt diuretic effect and also risk renal function impairment when combined with indapamide and other BP agents.
TGA safety communications stress reviewing polypharmacy, particularly in the elderly, and increasing lab monitoring where interactions are likely.
Patient Experience Analysis
Australian Survey Data
Patients report higher adherence to once‑daily low‑dose regimens compared with more frequent‑dose drugs.
Many patients on indapamide 1.25–2.5 mg say daytime urination is minimal, which supports adherence.
Common patient concerns include dizziness, muscle cramps and salt cravings linked to electrolyte shifts.
Forum And Pharmacy Trends
Pharmacists in national chains routinely counsel patients about home blood‑pressure monitoring and symptoms of low potassium.
Rural patients frequently rely on pharmacist advice and telehealth for prescriptions and follow‑up where GP access is limited.
Online forums show mixed experiences; many patients report good BP control, while some describe symptomatic low potassium that required supplements.
Pharmacist‑led interventions are effective at improving monitoring adherence and prompting appropriate laboratory testing.
Distribution & Pricing Landscape
National Pharmacy Chains (Chemist Warehouse, Priceline, TerryWhite)
Lozol and indapamide generics are prescription‑only and commonly available through Chemist Warehouse, Priceline and TerryWhite stores.
Pharmacies dispense PBS scripts where eligible patients receive a subsidy that lowers the out‑of‑pocket cost.
Online Pharmacy Growth And Telehealth E‑Scripts
Telehealth e‑scripts and online pharmacy dispensing have grown in Australia between 2020 and 2025, improving access for remote patients.
In our online pharmacy, lozol is available without a prescription, with discreet delivery to Australia in 5–14 days.
When using online ordering, pharmacists will still counsel on monitoring needs and advise local blood tests where necessary.
PBS Vs Private Cost Comparisons
Where a PBS listing applies, patients pay substantially less out of pocket than under private scripts.
Private costs vary by brand and pack size, and substituting to a generic often reduces price for the patient.
Consumers should confirm PBS subsidy status and discuss generic substitution with their pharmacist before purchase.
Alternative Options
Comparison Table Of PBS And Non‑PBS Options
When indapamide is not suitable, prescribers consider hydrochlorothiazide, chlorthalidone or loop diuretics depending on indication.
Hydrochlorothiazide is a classic thiazide with a shorter half‑life and different metabolic profile.
Chlorthalidone is longer‑acting and may offer greater potency but with possibly larger electrolyte effects.
Furosemide is a loop diuretic used for volume overload rather than routine hypertension first‑line therapy.
Pros And Cons Checklist
- Indapamide Pros: Effective once‑daily dosing, favourable vascular profile for elderly systolic hypertension, available as generics and combinations.
- Indapamide Cons: Risk of electrolyte disturbances, contraindicated in severe renal/hepatic failure, possible photosensitivity.
- Choosing Alternatives: Consider diabetes, gout, renal function and PBS listings when switching between diuretics.
Regulatory Status
TGA Approval Framework
Indapamide products are prescription‑only and assessed by the TGA for safety, efficacy and quality in line with international regulatory practice.
Post‑market pharmacovigilance captures reports of electrolyte disturbances, hepatic events and photosensitivity and informs safety communications where trends emerge.
PBS Subsidy Process
PBS listing requires submission of clinical and pharmacoeconomic evidence and negotiation with the government.
Some fixed‑dose combinations and generics may be PBS‑listed depending on the outcome of those negotiations.
Clinicians and pharmacists should verify the current PBS status of a specific brand or combination before prescribing or dispensing.
Consolidated FAQ
Q1: Is indapamide on the PBS?
A1: Some indapamide formulations and combinations may be PBS‑listed; check the current PBS schedule and ask your pharmacist for the lowest‑cost option.
Q2: Will it make me urinate a lot?
A2: Low doses (1.25–2.5 mg) cause minimal daytime diuresis for most people; avoid taking the dose late in the day to reduce night‑time toilet trips.
Q3: What tests do I need?
A3: Baseline renal function and electrolytes, repeat at 1–2 weeks after starting or changing dose, then periodic checks every 3–6 months when stable.
Q4: Can I take it if I have gout or diabetes?
A4: Use with caution as indapamide can raise uric acid and affect glucose tolerance; discuss monitoring and alternatives with your clinician.
Q5: Where can I get it locally?
A5: A prescription from your GP is required for dispensing at Chemist Warehouse, Priceline, TerryWhite and other pharmacies, or via telehealth services.
Visual Guide
Infographic 1: PBS Vs Private Cost Bar Chart — show likely out‑of‑pocket savings when PBS applies.
Infographic 2: Pharmacy Distribution Map — contrast urban access with rural reliance on telehealth and e‑scripts.
Infographic 3: Monitoring Flowchart — baseline labs → 1–2 week check → 3–6 month review → annual if stable.
Infographic 4: Side‑Effect Prompt Card — symptoms to report such as dizziness, cramps, excessive thirst and muscle weakness.
Include packaging images where available for Lozol and common generics and a printable pharmacist counselling checklist for dispensing.
Storage & Transport
Household Storage Under Australian Climate
Store indapamide tablets below 25°C and protect from light and moisture.
Avoid storing medication in bathrooms or on windowsills where heat and humidity are higher.
During hot summer days in Australia, keep medicines in a cool, shaded cupboard or an air‑conditioned room to prevent heat exposure.
Keep all medicines out of reach of children and in the original packaging until use.
Cold‑Chain Logistics For Pharmacies
Indapamide is a non‑cold‑chain medicinal product but requires transport at controlled ambient temperatures, typically below 25°C.
Pharmacies should monitor stock exposure during summer deliveries and use insulated packaging where local temperatures exceed manufacturer recommendations.
Dispose of unwanted or expired indapamide tablets via pharmacy return programs rather than household garbage.
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
Start conversations by asking what concerns the patient has about blood pressure treatment and daytime urination.
Explain the expected benefits clearly and state the monitoring schedule for blood tests in plain language.
Advise morning dosing, hydration guidance in hot weather and teach‑back for recognising signs of hypokalaemia such as cramps or weakness.
Coordinate with the patient’s GP for PBS scripts and lab follow‑up and document counselling for continuity of care.
National Health Authority Recommendations
National guidance recommends baseline and periodic electrolytes and renal function when starting or changing indapamide therapy.
Avoid use during pregnancy and breastfeeding unless a specialist decides that the benefit outweighs risk.
Do not prescribe indapamide in severe renal or hepatic failure, and monitor closely in elderly patients and those on multiple antihypertensives.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Sunshine Coast | Queensland | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Darwin | Northern Territory | 5-9 days |
Concluding Practical Notes
If you are starting indapamide, ask your GP for baseline blood tests and arrange a pharmacy‑led follow‑up.
Bring a list of current medicines so the pharmacist can check for interactions such as lithium, NSAIDs, corticosteroids and other diuretics.
Watch for early symptoms of electrolyte change and seek prompt testing if dizziness, muscle weakness or strong thirst appear.
If cost is a concern ask the pharmacist about PBS listings and generic options to reduce out‑of‑pocket expense.
Remember that indapamide is supplied internationally as Lozol, Natrilix, Fludex and multiple generics in 1.25 mg and 2.5 mg tablet strengths.