
Allopurinol
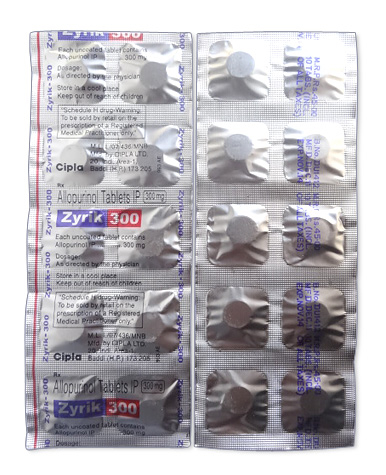
Allopurinol
- In our pharmacy, you can buy allopurinol without a prescription, with delivery in 5–14 days throughout Australia and discreet, anonymous packaging (note: allopurinol is typically prescription-only in many countries due to risk of serious side effects).
- Allopurinol is used to lower uric acid for gout (including prevention of flares and tophi), uric acid kidney stones and for tumour lysis syndrome prophylaxis; it is a xanthine oxidase inhibitor that blocks uric acid synthesis.
- The usual dose in adults is to start at 100 mg/day and titrate up based on serum uric acid; typical maintenance is 200–300 mg/day for mild disease or 400–600 mg/day for more severe cases, with doses up to 800 mg/day in specialist-managed cases; children are usually 10–20 mg/kg/day (max ~400 mg/day) and renal impairment requires dose reduction (e.g. if CrCl <20 mL/min consider max ~100 mg/day).
- The form of administration is oral, most commonly film‑coated tablets (100 mg and 300 mg); some regions may offer 200 mg/400 mg, suspensions or compounded forms — injectable forms are not typical.
- The onset of biochemical effect is over days (often detectable within 2–7 days), but clinical benefit can take weeks to months; it does not provide immediate relief for an acute gout attack.
- The duration of action is effectively covered by once‑daily dosing (the active metabolite oxypurinol has a long half‑life of roughly 18–30 hours); long‑term daily therapy is required to maintain lower uric acid levels.
- Alcohol warning: avoid excessive alcohol (especially beer and spirits) as alcohol raises uric acid and increases the risk of gout flares; discuss alcohol use with a healthcare professional while taking allopurinol.
- The most common side effect is skin rash (which may herald a serious hypersensitivity reaction and requires immediate stopping and medical review); other common effects include gastrointestinal upset (nausea, diarrhoea), liver enzyme elevations, headache and drowsiness.
- Would you like to try allopurinol without a prescription?
Basic Allopurinol Information
- INN (International Nonproprietary Name): Allopurinol (also referenced as Allopurinolum or Allopurinolum Ph. Eur.).
- Brand Names Available In Australia: Not specified; globally representative brands include Zyloric, Zyloprim and generics supplied by Teva, Sandoz, Mylan, Aspen and others.
- ATC Code: M04AA01.
- Forms & Dosages: Tablets are the standard oral forms, commonly 100 mg and 300 mg; some regions may supply 200 mg or 400 mg formulations, suspensions or compounded forms, but oral tablets 100 mg and 300 mg are most common.
- Manufacturers In Australia: Not specified; major global suppliers include Teva, Sandoz, Mylan, Accord, Zentiva, Aspen and Sanofi (Zyloric).
- Registration Status In Australia: Widely registered with national regulators including the TGA (Therapeutic Goods Administration).
- OTC / Rx Classification: Prescription-only (Rx) in all territories.
Key Findings From Recent Trials
Major 2022–2025 Australian & Global Studies
Worried whether allopurinol is still first choice for long-term gout control?
Recent high-quality systematic reviews and randomised controlled trials from 2022–2025 continued to position allopurinol as the established first-line xanthine oxidase inhibitor for chronic gout and urate-lowering therapy.
Australian pharmacoepidemiology reports up to 2024 show persistent high prescribing of allopurinol with 100 mg and 300 mg tablets dominant in dispensing data.
Trials across Australia and internationally reaffirmed serum urate lowering, tophi prevention and improved long-term outcomes with titrated allopurinol therapy.
Main Outcomes
Concerned about effectiveness compared with newer agents?
Key trial outcomes include effective and sustained reduction in serum urate levels when titrated to target and prevention of tophi progression over months to years.
Cost-effectiveness analyses in several studies favoured allopurinol versus newer agents for most patient groups, given widespread generic availability and PBS influence on price.
Clinical practice papers from 2023–2025 emphasise the success of a start-low, go-slow titration approach to reach targets such as serum urate under 0.36 mmol/L (6 mg/dL).
Safety Observations (TGA Reports)
Worried about serious skin reactions or rare harms?
Post-market surveillance, including TGA adverse-event reports, reiterate rare but severe cutaneous adverse reactions such as Stevens–Johnson syndrome and toxic epidermal necrolysis.
Reports continue to highlight the clinically important association between severe cutaneous reactions and HLA‑B*5801 in higher-risk ethnic groups.
Contemporary safety messaging in Australia stresses early recognition of rash and urgent cessation when progressive skin, mucosal or systemic signs appear.
Clinical Mechanism Of Action
Layman’s Explanation
Want to know how allopurinol actually helps gout?
Allopurinol lowers the body's production of uric acid so crystals that cause gout flares and tophi are less likely to form.
That means fewer painful attacks, reduced size of tophi and a lower chance of uric acid kidney stones over time.
Scientific Breakdown
Curious about the chemistry behind those benefits?
Allopurinol is a xanthine oxidase inhibitor that is metabolised to oxypurinol, its long-acting active metabolite.
Oxypurinol competitively inhibits xanthine oxidase and reduces conversion of hypoxanthine to xanthine and xanthine to uric acid.
The shift in purine metabolism increases more soluble intermediates and lowers serum urate.
Pharmacokinetics: oral tablets are well absorbed and oxypurinol is renally cleared, so dose adjustment is required in renal impairment.
In severe renal impairment such as CrCl below 20 mL/min, doses are typically limited (for example, around 100 mg/day) or individualised.
Clinical implication: titrate to serum urate targets rather than fixed dose alone and avoid starting during an acute flare unless there is prophylactic cover.
Scope Of Approved & Off-Label Use
Australian Approvals (TGA-Listed, PBS Inclusion)
Are you wondering what allopurinol is officially approved for here?
Approved indications focus on chronic gout and hyperuricaemia, prevention of uric acid nephrolithiasis, and short-term use for tumour lysis syndrome prophylaxis in oncology protocols.
Allopurinol is TGA-registered and prescription-only in Australia.
PBS listing and any applicable restrictions influence access and out-of-pocket cost for eligible patients.
Notable Off-Label Trends In Australian Practice
Thinking about how clinicians adapt treatment for complex patients?
Australian practice trends include careful dose adjustment in chronic kidney disease and selective HLA‑B*5801 testing in higher-risk ethnic groups at some specialist centres.
Shared-care models involving general practitioners and community pharmacists are common for routine monitoring of long-term therapy.
In oncology, rasburicase is preferred for patients at very high risk of tumour lysis, while allopurinol is commonly used for moderate-risk prophylaxis under hospital guidance.
Dosage Strategy
General Dosing
Worried about how to start and when to increase the dose?
Standard practice is to start low and titrate by serum urate response.
Typical adult initiation often begins at 100 mg once daily with stepwise increases every 2–4 weeks until target serum urate is reached.
Maintenance doses commonly fall in the 200–300 mg/day range for mild disease, while severe disease may require 400–600 mg/day and some patients up to 800 mg/day under specialist supervision.
Condition-Specific Dosing (PBS Recommendations)
Need examples tailored to different conditions?
Gout and hyperuricaemia: start at 100 mg/day, titrate every 2–4 weeks to target serum urate, with usual maintenance 200–300 mg/day for many patients.
Uric acid stone prevention follows similar dosing and monitoring principles.
Tumour lysis syndrome prophylaxis: oncology protocols may use higher short-term dosing around 600–800 mg/day in divided doses under hospital care.
Pediatric dosing is only for specific indications such as chemotherapy-related hyperuricaemia, typically 10–20 mg/kg/day up to 400 mg/day.
Renal impairment requires dose reductions; for CrCl below 20 mL/min a maximum around 100 mg/day is often considered unless specialist guidance suggests otherwise.
Safety Protocols
Contraindications (Australian Guidelines)
Worried you or a family member might be at risk?
Absolute contraindications include known hypersensitivity to allopurinol or any excipient and a history of severe cutaneous adverse reactions such as SJS or TEN.
Initiating allopurinol during an acute gout attack is generally avoided.
Relative caution is required in chronic kidney or liver disease and in people who test positive for HLA‑B*5801.
Adverse Effects (Post-Market Pharmacovigilance)
What side effects should patients watch for?
Common mild effects include skin rash, gastrointestinal upset, headache and transient liver enzyme elevations.
Initial gout flares can be provoked when starting therapy; colchicine or an NSAID for prophylaxis during the first 2–3 months reduces this risk.
TGA post-market surveillance continues to report rare but serious events including severe hepatic injury and SCARs such as SJS and TEN.
Mitigation strategies include starting at low dose, clear counselling on rash as an emergency red flag, baseline and periodic renal and liver function tests and selective HLA‑B*5801 risk assessment for people of higher-risk ancestry.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
Can diet affect how well allopurinol works?
Alcohol, particularly beer, increases uric acid production and can undermine gout control, so moderation and good hydration are recommended.
General advice on dietary purine reduction, weight management and reducing sugar-sweetened drinks remains sensible while on urate-lowering therapy.
Evidence for coffee is inconsistent, so no specific prescribing change is mandated by product information.
Drug Combinations To Avoid (TGA Safety Alerts)
Which medicines need special attention?
Co-administration of allopurinol with azathioprine or 6-mercaptopurine increases the risk of severe toxicity and requires dose reductions or alternative choices.
Warfarin potency may be affected; INR monitoring is advised if both are used.
Thiazide diuretics raise serum urate and can complicate control.
In oncology, interactions with chemotherapeutics and anticoagulants require hospital oversight where allopurinol is used for TLS prophylaxis.
Patient Experience Analysis
Australian Survey Data
What do Australian patients talk about most in clinics and surveys?
Recent patient surveys and pharmacy feedback from 2022–2024 highlight price sensitivity and reliance on PBS subsidies when filling allopurinol prescriptions.
Many patients report relief from recurrent gout attacks once maintenance serum urate is achieved, but frustration about initial flares during titration is common.
Questions to pharmacists often focus on side effects, rash risk, and how to safely titrate allopurinol tablets such as allopurinol 100mg and allopurinol 300mg.
Forum And Pharmacy Trends
How do online forums and community pharmacies influence care?
Community groups report confusion around titration schedules and alarm about rashes, making pharmacists a frequent first point of triage and education.
Chains and local pharmacies commonly advise on stock availability of generic allopurinol tablets and on PBS subsidy requirements.
Rural patients often rely more on local pharmacists for monitoring and may experience longer wait-times for GP reviews.
Distribution & Pricing Landscape
National Pharmacy Chains
Where do most Australians buy allopurinol?
Allopurinol is widely stocked across national chains such as Chemist Warehouse, Priceline and TerryWhite, and by community pharmacies nationwide.
Both branded (for example Zyloric) and multiple generics from suppliers like Teva and Sandoz are readily available in 100 mg and 300 mg tablet strengths.
Online Pharmacy Growth And Telehealth E-Scripts
Is it safe to order medication online?
Online pharmacies and telehealth e‑scripts have expanded access since 2020, but prescribers and pharmacists must ensure appropriate monitoring and verification.
In our online pharmacy, allopurinol can be ordered with discreet delivery to Australia in 5–14 days subject to prescription requirements.
PBS Vs Private Cost Comparisons
Which is cheaper: PBS or private scripts?
PBS listing substantially reduces patient co-payments for eligible Australians compared with private prescriptions, and generics have driven down private costs as well.
Pharmacists often advise on PBS authority steps and therapeutic substitution between brands to maintain supply continuity during shortages, especially in rural areas.
Alternative Options
Comparison Table Of PBS And Non-PBS Options
Thinking allopurinol might not be right for you?
Alternatives include febuxostat, uricosurics such as probenecid and agents used in TLS like rasburicase.
Febuxostat is an effective xanthine oxidase inhibitor and is commonly used when patients are intolerant to allopurinol, but PBS access may be restricted and require authority approval.
Rasburicase is reserved for hospital use in tumour lysis syndrome and is not a routine outpatient substitute.
Pros And Cons Checklist
Need a quick way to weigh options?
- Allopurinol: Low cost, strong evidence base, requires renal adjustment and has rare SCAR risk.
- Febuxostat: Useful alternative for intolerance; consider cardiovascular history and PBS restrictions.
- Probenecid: Uricosuric option but less effective in renal impairment and less commonly used.
- Rasburicase: Effective for TLS in hospital settings; not a community alternative.
Regulatory Status
TGA Approval Framework
How does the TGA oversee medicines like allopurinol?
Allopurinol is TGA-registered as a prescription-only xanthine oxidase inhibitor with ATC code M04AA01.
The TGA evaluates quality, safety and efficacy data and monitors post-market adverse-event reports from healthcare professionals and consumers.
PBS Subsidy Process
How does a medicine become subsidised on the PBS?
PBS listing requires evidence of clinical benefit and cost-effectiveness, and many allopurinol generic and branded permutations are PBS-listed or available under PBS authority rules.
PBS listing materially reduces out-of-pocket costs and shapes prescribing choices in Australia.
Consolidated FAQ
Here are common patient questions Australians ask about allopurinol.
-
Can I start allopurinol during a gout attack?
Generally avoid starting during an acute flare because it can worsen symptoms; if initiation is clinically necessary, prophylactic cover with colchicine or an NSAID is used under clinician guidance.
-
Do I need HLA‑B*5801 testing?
Testing is not universally required in Australia but should be considered for people of Han Chinese, Korean, Thai or other high-risk Asian ancestry or in those with previous severe cutaneous reactions.
-
How often do I monitor bloods?
Obtain baseline renal and liver tests and serum urate, repeat every 2–4 weeks during titration, then every 6–12 months once stable depending on comorbidity.
-
Is PBS cheaper than private scripts?
Yes, PBS subsidy typically lowers out-of-pocket costs substantially compared with private prescriptions; check local pharmacies for stock and exact pricing.
-
What if I develop a rash?
Stop allopurinol immediately and seek urgent medical review because a rash can herald a severe cutaneous adverse reaction.
Visual Guide
Want simple visuals to take home?
Recommended patient handouts include a PBS vs private cost flowchart, a pharmacy distribution map showing major chains and regional pharmacies, a titration timeline for dose increases and serum urate checkpoints, and a safety red-flag checklist highlighting rash or HLA‑B*5801 considerations.
Suggested data sources for infographics include TGA, PBS schedules and pharmacy pricing snapshots from 2024–2025.
Storage & Transport
Household Storage Under Australian Climate
Where should you keep your tablets at home?
Store allopurinol below 25°C, protected from light and moisture, and keep tablets in original packaging.
Avoid placing tablets in bathrooms where humidity is high and avoid exposure to direct sunlight or very hot conditions during Australian summers.
Cold-Chain Logistics For Pharmacies
How do pharmacies manage deliveries and stock?
Oral tablets do not require refrigeration, but pharmacies should maintain ambient temperature control during storage and delivery and plan buffer stock in remote areas to guard against short-dated returns and intermittent shortages.
Return expired medicines to a pharmacy for safe disposal.
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
What should patients hear at the pharmacy counter?
Counselling should be pragmatic and patient-centred: explain the start-low titration plan, the common early flare risk and the value of prophylactic colchicine or NSAID cover for the first 2–3 months.
Use teach-back to confirm dose, monitoring schedule and recognition of red-flag symptoms such as progressive rash or mucosal ulcers.
Advise hydration, alcohol moderation and the importance of follow-up blood tests.
National Health Authority Recommendations
What do national guidelines recommend?
Clinical guidance supports long-term urate-lowering therapy for recurrent gout and tophi, individualised dosing for renal impairment, HLA‑B*5801 risk assessment where relevant, and avoiding initiation during an acute flare unless required with prophylaxis.
Pharmacists in rural areas often coordinate local blood testing and telehealth specialist referrals when needed.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-9 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Cairns | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Alice Springs | Northern Territory | 5-9 days |
Storage And Transport Practical Tips
How can patients and pharmacies avoid damaged stock?
Keep tablets below 25°C and in original blister packs or bottles to protect from moisture and light.
Do not freeze tablets and avoid leaving them in hot cars during transport or delivery.
Online pharmacies and couriers should use ambient temperature control and monitor transit times to maintain medicine stability.
Pharmacy Counselling Checklist
What are the quick counselling points pharmacists should cover?
- Confirm indication and baseline bloods including renal and liver function and serum urate.
- Explain start-low dosing (e.g., 100 mg/day) and the plan to titrate to a serum urate target.
- Advise on prophylaxis for initial gout flares and signs of allergic reaction — stop if rash develops.
- Discuss PBS authority steps and likely refill timing for 100 mg and 300 mg tablet regimens.
Concluding Notes
Allopurinol remains a first-line, well-established urate-lowering agent with broad global and Australian use, commonly supplied as 100 mg and 300 mg tablets under ATC M04AA01.
Safe use requires start-low titration, monitoring of renal and liver function, counselling on rash recognition and consideration of HLA‑B*5801 testing in higher-risk groups.
When alternatives are needed, febuxostat, probenecid or hospital-based rasburicase are options, with PBS listing and access influencing practical prescribing choices in Australia.