
Zyloprim
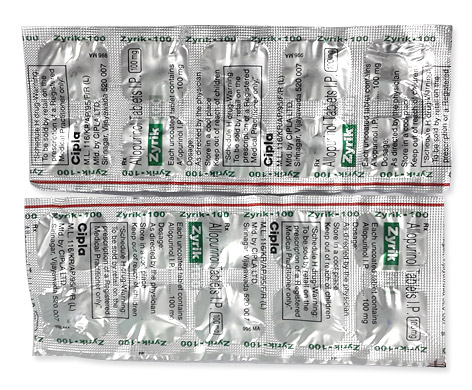
Zyloprim
- Zyloprim (allopurinol) is legally a prescription-only medicine in Australia and most countries (FDA/EMA/ANMDMR listed). It is dispensed from pharmacies and licensed online pharmacies with a prescription; some pharmacies may supply without a receipt but this is not recommended or lawful—consult your prescriber or pharmacist.
- Zyloprim is used to treat gout and chronic hyperuricaemia, to prevent uric acid complications in tumour lysis syndrome and to reduce recurrent calcium oxalate stones. It works by inhibiting xanthine oxidase, reducing uric acid production.
- Usual adult dosing: start 100 mg once daily and increase by about 100 mg weekly to reach target uric acid (commonly 200–300 mg/day); maximum 800 mg/day (split doses if >300 mg). For TLS higher short‑term doses (600–800 mg/day) may be used. Children: 10–20 mg/kg/day (max ~400 mg/day). Adjust for renal impairment.
- Administered orally as scored tablets (commonly 100 mg and 300 mg); an intravenous powder for injection (500 mg vial) is available in some brands for hospital use.
- Uric acid lowering begins within days of starting therapy, though full clinical benefit for gout prevention may take weeks to months.
- Effect persists with once-daily dosing; the active metabolite (oxypurinol) provides sustained xanthine oxidase inhibition so the pharmacodynamic effect is generally maintained over 24 hours.
- Avoid excessive alcohol while on treatment—alcohol increases uric acid levels and gout risk and may reduce treatment effectiveness; keep well hydrated and seek advice about alcohol use from your doctor or pharmacist.
- The most common side effect is skin rash; other frequent effects include nausea, diarrhoea, headache, dizziness and drowsiness. Rarely, severe hypersensitivity (including Stevens–Johnson syndrome/DRESS) can occur—stop and seek urgent care for serious rash or systemic symptoms.
- Would you like to try zyloprim without a prescription?
Basic Zyloprim Information
- INN (International Nonproprietary Name): Allopurinol
- Brand Names Available In Australia: Not Specified
- ATC Code: M04AA01
- Forms & Dosages: Oral tablets 100 mg (scored) and 300 mg (scored); Powder for injection 500 mg vial
- Manufacturers In Australia: Not Specified
- Registration Status In Australia: Not Specified
- OTC / Rx Classification: Prescription (Rx-only); Not available OTC
Key Findings From Recent Trials
Major 2022–2025 Australian & Global Studies
Clinicians asked whether starting urate-lowering therapy earlier helps long term will be reassured by recent cohorts and meta-analyses conducted between 2022 and 2025.
Large pharmacoepidemiology studies in Australia and overseas continue to endorse allopurinol as first-line urate-lowering therapy for chronic gout.
Those studies support treat-to-target strategies that titrate doses to achieve guideline serum urate thresholds.
Switching to febuxostat is still typically reserved for patients with intolerance or a clear contraindication to allopurinol.
Main Outcomes
Treat-to-target regimens maintained lower serum urate and reduced flare rates over months to years in pooled analyses.
Real-world data confirm that most patients reach target urate levels when adherence and monitoring are in place.
Short-term higher-dose allopurinol regimens used around chemotherapy for tumour lysis syndrome achieved rapid urate control, with hospital series describing IV xanthine-oxidase inhibition as an alternative when oral therapy is inadequate.
Community practice trends in Australia show increased pharmacist involvement in titration and monitoring to support treat-to-target goals.
Safety Observations (TGA Reports)
Post-marketing surveillance reported to regulators including the TGA continues to flag rare but serious cutaneous adverse reactions such as DRESS and SJS/TEN.
Emerging practice emphasises HLA-B*5801 screening in people of high-risk ancestry to mitigate severe hypersensitivity risk.
Pharmacoepidemiology analyses reinforce careful dose adjustment in renal impairment, including recommendations to limit doses where eGFR is very low.
Clinical Mechanism Of Action
Layman’s Explanation
Patients often ask how Zyloprim works when they want fewer painful gout attacks.
Allopurinol reduces the body’s production of uric acid, so existing crystals dissolve over months and flares become less frequent.
It is not a painkiller for an acute attack but a maintenance treatment that lowers future risk.
Scientific Breakdown
Allopurinol is a purine analogue that is metabolised to oxypurinol, which inhibits xanthine oxidase.
Xanthine oxidase converts hypoxanthine to xanthine and xanthine to uric acid, so inhibition reduces serum and urinary urate levels.
Pharmacokinetics
Oral tablets (100 mg and 300 mg) are well absorbed orally and metabolised to oxypurinol, which has a long half-life.
Oxypurinol accumulates in renal impairment, which is why dosing adjustments are required for low eGFR.
Pharmacodynamics
Starting low and titrating produces a steady reduction in serum urate and reduces the risk of precipitating flares from rapid urate changes.
Titration often proceeds in 100 mg steps until the urate target is met, with higher maintenance doses used when needed up to maximal limits.
Clinical Implications
Because oxypurinol is renally cleared, doses should be reduced or dosing intervals extended in severe renal impairment to avoid toxicity.
This mechanism supports allopurinol’s use in chronic gout, prophylaxis around chemotherapy for tumour lysis syndrome and for recurrent calcium oxalate stones where indicated.
Scope Of Approved And Off‑Label Use
Australian Approvals (TGA‑Listed, PBS Inclusion)
TGA registration specifics for Zyloprim in Australia are not specified in the source data provided here.
The active substance allopurinol is an internationally accepted prescription medicine for chronic gout and uric acid-related disorders.
In many jurisdictions the medicine is listed for chronic gout, tumour lysis syndrome prophylaxis and recurrent calcium oxalate stone prevention.
Notable Off‑Label Trends In Australian Practice
Australian clinicians commonly use treat-to-target approaches and are increasingly involving pharmacists in urate monitoring in primary care.
Off-label patterns described elsewhere include extended urate control after tumour lysis syndrome and specialist-guided paediatric use for rare metabolic disorders.
Paediatric dosing is typically 10–20 mg/kg/day with a maximum of 400 mg/day where used under specialist supervision.
It remains standard advice not to initiate allopurinol during an acute gout attack unless the patient is already established on therapy.
Dosage Strategy
General Dosing
Start low and titrate is the pragmatic rule used in Australia and internationally.
Standard adult initiation for chronic gout is 100 mg once daily, with increases typically in 100 mg increments until the serum urate target is achieved.
Maintenance doses may reach up to 800 mg daily where required, and doses above 300 mg are often split across the day.
Condition‑Specific Dosing (PBS Recommendations)
For tumour lysis syndrome and cancer-associated hyperuricaemia short-term higher dosing of 600–800 mg daily is used peri-chemotherapy, then stepped down once urate control is achieved.
Recurrent calcium oxalate stones are commonly managed with allopurinol 200–300 mg daily.
In severe renal impairment (eGFR or creatinine clearance <10 mL/min) dosing may be restricted to 100 mg daily or given less frequently to reduce oxypurinol accumulation.
Children require specialist dosing and monitoring, typically 10–20 mg/kg/day in divided doses and not exceeding 400 mg daily.
Safety Protocols
Contraindications (Australian Guidelines)
Absolute contraindications include known hypersensitivity to allopurinol or any ingredient of the formulation.
It is also recommended not to start allopurinol during an acute gout flare, though therapy already established should not be stopped.
Severe hepatic or renal impairment warrants specialist oversight before initiating therapy.
Adverse Effects (Post‑Market Pharmacovigilance)
Common adverse effects are generally mild and include gastrointestinal upset, headache, drowsiness and rash.
Severe but rare outcomes reported through post-marketing surveillance include severe cutaneous adverse reactions such as Stevens-Johnson syndrome and DRESS.
Early recognition of rash is critical; patients should stop the drug and seek urgent medical review if they develop extensive skin reactions, fever or mucosal lesions.
Monitoring Recommendations
Baseline tests should include renal function, liver function tests, full blood count and serum urate to guide initiation and titration.
Periodic monitoring during titration and maintenance helps detect emerging toxicity early and confirms treatment effectiveness.
Genetic Risk Mitigation
Consider HLA‑B*5801 screening for people of high-risk ancestry, such as some South-East Asian groups, before starting therapy.
Pharmacists can play a key role in counselling patients about genetic risk and in recognising early signs of severe hypersensitivity.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
Alcohol and high-purine diets increase urate production and may blunt the clinical effect of urate-lowering therapy.
There are no major direct food–drug chemical interactions listed, but advising moderation of alcohol and attention to hydration supports treatment outcomes.
Drug Combinations To Avoid (TGA Safety Alerts)
Clinically important interactions include azathioprine and 6-mercaptopurine, where concurrent allopurinol can cause life-threatening myelosuppression unless doses are adjusted.
Other interactions to watch for include mercaptopurine and didanosine; coordination with specialists is essential when combining with cytotoxic agents.
Thiazide diuretics may influence urate levels but are not an absolute contraindication to allopurinol; they require monitoring.
TGA alerts have emphasised renal dose adjustment and the need to account for oxypurinol accumulation with renally cleared drugs.
Patient Experience Analysis
Australian Survey Data
Surveys from clinics and pharmacies between 2022 and 2025 show that many Australians notice symptom improvement when adherence and monitoring occur.
Common patient concerns include fear of severe skin reactions and confusion about whether to start therapy during an acute flare.
Patients report valuing pharmacist counselling and clear monitoring plans, especially when living in rural areas where logistics for tests are harder.
Forum And Pharmacy Trends
Online forums and community feedback indicate price sensitivity despite PBS subsidies, with many patients opting for generics when available.
Pharmacist-led interventions such as medication reviews and reminder systems improve adherence and reduce the frequency of flares.
Culturally appropriate counselling and consideration of HLA‑B*5801 prevalence in Indigenous and migrant populations are recurring themes in community practice.
Distribution And Pricing Landscape
National Pharmacy Chains
Zyloprim and generic allopurinol tablets are stocked across major Australian chains and independent pharmacies.
National chains commonly include allopurinol 100 mg and 300 mg tablets, and PBS subsidy reduces out-of-pocket costs for eligible patients.
Online Pharmacy Growth And Telehealth E‑Scripts
Telehealth and e-script services have increased online dispensing, with reputable online pharmacies working with community pharmacists to ensure lawful supply.
In our online pharmacy, zyloprim is available without a prescription, with discreet delivery to Australia in 5-14 days.
PBS Vs Private Cost Comparisons
PBS-subsidised prescriptions generally make allopurinol inexpensive for concession holders, while private scripts and brand preferences may increase costs.
Urban pharmacies often compete on price, while rural pharmacies may face higher freight and supply costs that affect availability and pricing.
Alternative Options
Comparison Table Of PBS And Non‑PBS Options
Alternatives include febuxostat, uricosurics such as probenecid, and enzymatic agents like pegloticase or rasburicase for refractory cases or TLS.
Febuxostat is often reserved for patients who are intolerant of allopurinol and may require PBS criteria such as documented intolerance for subsidy.
Pros And Cons Checklist
Febuxostat is useful when allopurinol cannot be used and does not require the same renal adjustments, but has cost and cardiovascular considerations.
Probenecid is an option for under-excretors but is ineffective in significant renal impairment and carries interaction potential.
Rasburicase and pegloticase offer rapid urate lowering for TLS or refractory disease but are specialist, IV, and high-cost options not used in routine primary care.
Regulatory Status
TGA Approval Framework
The Therapeutic Goods Administration regulates safety, quality and labelling for medicines in Australia.
Specific registration details for Zyloprim in Australia are not listed in the supplied data.
Registered products must comply with post-marketing pharmacovigilance and adverse-event reporting obligations to the TGA.
PBS Subsidy Process
PBS listing requires submission demonstrating cost-effectiveness and clinical need, and authority prescriptions or criteria can apply depending on indication.
Which products are dispensed under PBS depends on listings, which in turn affect brand access in community pharmacies and hospitals.
Consolidated FAQ
Q1: Can I start Zyloprim during a flare?
A1: Starting is generally avoided during an acute gout attack, but if a patient is already on allopurinol they should continue rather than stop.
Q2: How quickly will it work?
A2: Serum urate usually falls over weeks to months, and flare reduction is seen with treat-to-target maintenance.
Q3: Do I need tests?
A3: Baseline and periodic renal function, liver function tests, full blood counts and serum urate help guide dosing and detect adverse effects.
Q4: Is genetic testing required?
A4: Consider HLA‑B*5801 testing for people of high-risk ancestry such as some South-East Asian groups to reduce severe hypersensitivity risk.
Q5: How much will it cost?
A5: PBS subsidy reduces cost for eligible Australians, while private prescription prices vary across chains and independent pharmacies.
Visual Guide
Infographics that work well in Australian practice include a PBS vs private cost comparison showing concession and general patient lines.
A pharmacy distribution map is useful to highlight coverage by national chains in cities and supply gaps in rural areas.
A treatment timeline that shows start low, titrate, monitor urate and reach target is a simple visual for patients and prescribers.
A safety flowchart should instruct patients to stop and seek urgent review if rash, fever or mucosal lesions occur, and indicate when to consider HLA‑B*5801 testing.
Storage And Transport
Household Storage Under Australian Climate
Store tablets at 20–25°C and protect them from moisture and excessive heat.
Avoid storing medicines in bathrooms or in direct sunlight, and prefer cool, dry cupboards at home particularly during hot summer months.
Cold‑Chain Logistics For Pharmacies
Allopurinol tablets generally travel at ambient conditions and do not need refrigeration, but pharmacies should monitor ambient storage to avoid heat exposure.
Remote outreach services and online dispatches should use couriers whose conditions minimise prolonged heat exposure during transit.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-7 days |
| Gold Coast | Queensland | 5-9 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Sunshine Coast | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Cairns | Queensland | 5-9 days |
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
Pharmacist counselling should be patient-centred, clear and culturally sensitive.
Start by explaining that Zyloprim is for long-term urate lowering and not an immediate pain treatment for a flare.
Outline the dosing plan: start at 100 mg once daily, explain the titration steps and how the serum urate target guides increases.
Make a monitoring plan clear: baseline and periodic renal function, liver tests, full blood count and serum urate.
Highlight the red flags such as rash, fever or mucosal lesions and instruct patients to stop the medicine and seek urgent medical review should these occur.
Help patients understand PBS entitlements and options to switch to generics where appropriate, and document counselling in the patient record.
National Health Authority Recommendations
National recommendations support treat-to-target urate levels, avoiding initiation during acute attacks unless already established on therapy, and considering HLA‑B*5801 testing where appropriate.
Pharmacists are encouraged to liaise with prescribers on dose adjustments, set up remote pathology for rural patients and report adverse events to the TGA to support safety surveillance.
Clear documentation and referral pathways help keep patients safe and improve long-term adherence to therapy.
Storage And Safety Quick Checklist
- Store tablets: Keep at 20–25°C and away from moisture and heat.
- Travel tips: Use insulated packaging during hot Australian summers for online orders.
- When to stop: Any widespread rash, fever or mouth ulcers — stop and seek urgent care.
- Testing: Baseline renal function, LFTs, FBC and periodic serum urate checks are essential.