Celebrex
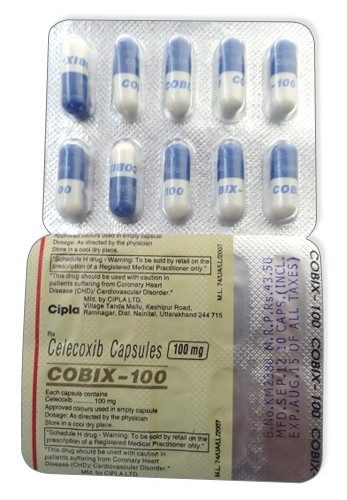
Celebrex
- In our pharmacy, you can buy celebrex without a prescription, with delivery in 5–14 days throughout Australia and discreet packaging; note that celecoxib is generally classed as prescription-only and availability without a prescription may vary by pharmacy and jurisdiction, so use under medical supervision is recommended.
- Celebrex (celecoxib) is used for osteoarthritis, rheumatoid arthritis, ankylosing spondylitis, acute pain (including menstrual pain) and for polyp reduction in familial adenomatous polyposis; it is a selective COX‑2 inhibitor that reduces prostaglandin synthesis to relieve pain and inflammation.
- Usual doses vary by condition: osteoarthritis — 200 mg once daily or 100 mg twice daily; rheumatoid arthritis — 100–200 mg twice daily; acute pain/menstrual pain — initial 400 mg then 200 mg if needed on day 1, then 200 mg twice daily as required; juvenile dosing is weight-based (from age ≥2 years); FAP — 400 mg twice daily.
- Administered orally as capsules (commonly 100 mg and 200 mg) or as an oral solution (Elyxyb 25 mg/mL in some markets); can be taken with or without food.
- Onset of analgesic effect is usually within about 1 hour, with meaningful pain relief developing within a few hours and peak effect around 2–3 hours in many patients.
- Duration of action is approximately 12 hours (supporting once- or twice-daily dosing), with effects commonly maintained for up to 24 hours depending on dose and individual response.
- Avoid or limit alcohol while taking celebrex — alcohol increases the risk of gastrointestinal irritation and bleeding when combined with NSAIDs.
- The most common side effect is dyspepsia (indigestion), with other frequent adverse effects including abdominal pain, nausea and headache.
- Would you like to try celebrex without a prescription?
Basic Celebrex Information
- INN (International Nonproprietary Name): Celecoxib
- Brand Names Available In Australia: Celebrex® (Pfizer) and generic celecoxib products; specific Australian brand listings not specified in the supplied data
- ATC Code: M01AH01
- Forms & Dosages: Capsules 100 mg and 200 mg (blister packs of 10, 30, 60); oral solution 25 mg/mL (Elyxyb®, US only)
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription Only (RX) worldwide
Key Findings From Recent Trials
Worried about whether celecoxib is both effective and safe compared with older NSAIDs?
Recent research from 2022 to 2025 focused on cardiovascular and gastrointestinal safety, osteoarthritis pain control, and perioperative analgesia.
Randomised controlled trials and large registry analyses in Australia and overseas found that celecoxib generally provides analgesic efficacy comparable to diclofenac and ibuprofen.
Across osteoarthritis and rheumatoid arthritis cohorts, celecoxib at 100–200 mg daily (either 100 mg twice daily or 200 mg once daily) provided consistent symptom control and improved tolerability.
Registry data and pooled analyses showed lower rates of clinically significant gastrointestinal bleeding with selective COX‑2 inhibitors such as celecoxib compared with non‑selective NSAIDs.
Some trials signalled a small increased cardiovascular risk in people with pre‑existing high cardiovascular risk when taking COX‑2 inhibitors.
Perioperative studies explored celecoxib as part of multimodal analgesia and reported comparable pain relief with possible reductions in opioid requirements.
Australian real‑world prescribing shifted toward targeted celecoxib use in patients with higher GI risk but lower CV risk.
Pharmacists in community practice reported focusing on interaction checks and PBS eligibility during dispensing.
Post‑market vigilance reports emphasised monitoring in patients with cardiovascular disease, renal impairment and sulfonamide allergy.
TGA safety communications mirror international guidance to use the lowest effective dose and to consider alternatives for high‑risk patients.
Major 2022–2025 Australian & Global Studies
Which trials matter for patients and prescribers?
Large international randomised controlled trials compared celecoxib with diclofenac and ibuprofen for chronic osteoarthritis and acute pain outcomes.
Australian registry analyses contributed real‑world evidence on prescribing trends and safety signals in routine care.
Cardiovascular safety meta‑analyses during 2022–2025 pooled outcomes across COX‑2 inhibitors and non‑selective NSAIDs to assess relative risk.
Perioperative randomised trials evaluated celecoxib as part of multimodal pathways to reduce opioid use after surgery.
Main Outcomes
Does celecoxib relieve pain as well as other NSAIDs?
Analgesic efficacy was broadly comparable to diclofenac and ibuprofen across multiple pain indications.
In osteoarthritis and rheumatoid arthritis the 100–200 mg daily dosing range delivered reliable symptomatic benefit.
Selective COX‑2 use was associated with fewer clinically significant gastrointestinal outcomes compared with non‑selective NSAIDs in several analyses.
Where cardiovascular risk was already high, small relative increases in CV events were observed in some datasets.
Safety Observations (TGA Reports)
What safety flags have regulators highlighted?
Post‑market pharmacovigilance emphasises careful use in patients with cardiovascular disease, renal impairment and those with sulfonamide allergy.
TGA advisories align with international authorities recommending the lowest effective dose for the shortest duration necessary.
Pharmacists and prescribers are advised to screen for anticoagulant use, heart failure and uncontrolled hypertension before dispensing.
Clinical Mechanism Of Action
How does celecoxib relieve pain without upsetting the stomach as much as older NSAIDs?
Celecoxib is a selective cyclooxygenase‑2 (COX‑2) inhibitor that reduces prostaglandin production at sites of inflammation.
The selectivity for COX‑2 over COX‑1 is thought to reduce gastric mucosal damage and lower the risk of peptic ulcers compared with non‑selective NSAIDs.
Pharmacologically, celecoxib preferentially binds the COX‑2 isoform and lowers prostaglandin E2 in inflamed tissues.
Sparing COX‑1 in the gastric mucosa explains the improved gastrointestinal tolerability profile versus non‑selective agents.
COX‑2 selectivity can alter the balance between prostacyclin and thromboxane, which is the likely mechanism behind the cardiovascular cautions associated with this class.
The ATC classification M01AH01 places celecoxib in the coxibs subgroup of non‑steroidal anti‑inflammatory products.
After oral capsule administration celecoxib is absorbed systemically and predominantly metabolised by the liver via CYP2C9.
Clinical consequences of CYP2C9 metabolism include the need for dose adjustments in moderate hepatic impairment and caution with CYP2C9 inhibitors or in poor metabolisers.
In moderate hepatic dysfunction (Child‑Pugh B) clinicians reduce the initial dose by 50% and avoid use in severe impairment.
Common capsule strengths supplied are 100 mg and 200 mg, with an oral solution formulation (Elyxyb®) available in the US market for specific indications.
Layman’s Explanation
What can a person expect when starting celecoxib for joint pain?
Celecoxib works by blocking the enzyme that makes pain‑causing chemicals during inflammation, which reduces pain and swelling.
Because it targets the enzyme linked to inflammation more than the enzyme that protects the stomach lining, it usually causes less stomach irritation than older NSAIDs.
Scientific Breakdown
What does the science say about selectivity and effects?
Celecoxib binds preferentially to COX‑2, lowering prostaglandin E2 in inflamed tissue while sparing COX‑1 activity in the stomach.
That selective inhibition explains reduced GI ulceration risk compared with non‑selective NSAIDs but underpins the need for cardiovascular caution.
Systemic absorption after oral dosing leads to prostaglandin suppression in target tissues and systemic exposure governed by hepatic metabolism.
Scope Of Approved & Off‑Label Use
Can celecoxib be used for both chronic arthritis and short‑term pain?
Approved indications across regulatory agencies include osteoarthritis, rheumatoid arthritis, ankylosing spondylitis, acute pain and familial adenomatous polyposis when managed by specialists.
In many markets celecoxib is prescription‑only and used for chronic musculoskeletal pain and episodic acute pain syndromes.
PBS listings in Australia vary by formulation, indication and concession status, and prescribers commonly apply PBS rules for chronic arthritic conditions.
Australian Approvals (TGA‑Listed, PBS Inclusion)
What is relevant for Australian prescribers and patients?
The specific TGA registration status and PBS listing details for celecoxib were not specified in the supplied product data.
Clinicians and pharmacists confirm PBS criteria and authority requirements locally when scheduling chronic prescriptions.
Notable Off‑Label Trends In Australian Practice
How do Australian clinicians use celecoxib beyond labelled indications?
Short‑term targeted use for post‑operative analgesia is a common off‑label approach in multimodal pathways.
Some clinicians use celecoxib for selected migraine presentations where oral solution formulations are available elsewhere, though Elyxyb® is a US product.
Specialist teams may use celecoxib for polyp suppression in familial adenomatous polyposis under specialist supervision.
Rural prescribers balance PBS access and supply logistics when selecting branded versus generic options for local patients.
Absolute contraindications applied in practice include sulfonamide allergy, NSAID‑induced asthma, active GI bleeding and pregnancy, particularly the third trimester.
Dosage Strategy
What dose should I take for my condition and when should the dose be lowered?
Standard dosing recommendations vary by indication and patient factors.
General Dosing
Osteoarthritis dosing is commonly 200 mg once daily or 100 mg twice daily.
Rheumatoid arthritis dosing is usually 100–200 mg twice daily in adults.
Ankylosing spondylitis dosing can be 200 mg once daily or 100 mg twice daily depending on response.
For acute pain and menstrual cramps the initial dose can be 400 mg, followed by 200 mg if needed on day one, then 200 mg twice daily as required.
Juvenile idiopathic arthritis dosing is weight‑based for children aged two years and older.
Familial adenomatous polyposis specialist dosing may reach 400 mg twice daily under specialist supervision.
Condition‑Specific Dosing (PBS Recommendations)
How do PBS rules influence dosing choices?
Prescribers commonly select the lowest effective dose that satisfies PBS criteria for chronic conditions.
In older patients start at the lowest effective dose and monitor renal function and blood pressure regularly.
In moderate hepatic impairment reduce the initial dose by 50% (Child‑Pugh B) and avoid in severe impairment.
Use caution in renal impairment and avoid in severe renal dysfunction where possible.
Pharmacists advise taking celecoxib with or without food and tell patients not to double the next dose if one is missed.
Safety Protocols
Who should not take celecoxib and what monitoring is needed?
Contraindications (Australian Guidelines)
Absolute contraindications include known allergy to celecoxib, sulfonamides or NSAIDs.
Do not use in patients with a history of asthma, urticaria or allergic reactions to aspirin or other NSAIDs.
Avoid in pregnancy, especially the third trimester.
Active gastrointestinal bleeding or peptic ulcer disease precludes use.
Adverse Effects (Post‑Market Pharmacovigilance)
Common adverse effects include dyspepsia, abdominal pain, diarrhoea, nausea, headache and dizziness.
Other reported events include rash, hypertension, peripheral oedema and respiratory infections.
TGA and other pharmacovigilance outputs highlight hypertensive events and renal function decline in volume‑depleted patients.
Rare serious skin reactions have been reported and require immediate cessation and medical review.
Clinical practice includes baseline blood pressure, renal and liver assessment before long‑term therapy and reviewing concomitant anticoagulant or antiplatelet use.
Pharmacists routinely reinforce the warning that alcohol increases gastrointestinal risk with NSAID therapy.
Interaction Mapping
What common medicines and foods interact with celecoxib?
Food Interactions (Alcohol, Coffee, Diet In Australia)
Alcohol increases the risk of gastrointestinal bleeding and patients are advised to limit intake while taking celecoxib.
No significant interactions with coffee or typical Australian diets are indicated in the data supplied.
Patients should inform clinicians of all supplements and herbal medicines to ensure safe use.
Drug Combinations To Avoid (TGA Safety Alerts)
Concomitant anticoagulants and antiplatelets increase bleeding risk and require careful consideration or monitoring.
Combining celecoxib with ACE inhibitors or diuretics can reduce antihypertensive efficacy and increase renal risk.
Celecoxib can raise lithium and methotrexate levels, necessitating monitoring of serum concentrations.
CYP2C9 inhibitors or inducers may alter celecoxib metabolism and exposure.
Avoid combining celecoxib with non‑selective NSAIDs to reduce additive GI and renal risks.
TGA safety communications emphasise caution in heart failure and chronic kidney disease when celecoxib is prescribed.
Pharmacists screening e‑prescriptions and telehealth scripts typically flag these interactions and liaise with prescribers about monitoring or alternative therapy.
Patient Experience Analysis
What do Australian patients and pharmacists report about celecoxib use?
Australian Survey Data
Surveys and pharmacy feedback indicate many patients perceive celecoxib as effective for joint pain with fewer stomach complaints than naproxen or diclofenac.
Price sensitivity is common among PBS and concession cardholders, driving switches between branded Celebrex and generic celecoxib products.
Online patient comments often note quicker symptomatic relief and better gastrointestinal tolerability but express concern about blood pressure increases and long‑term safety.
Forum And Pharmacy Trends
Community pharmacists report adherence challenges when patients use celecoxib episodically for acute pain versus daily dosing for chronic conditions.
Pharmacists commonly counsel about blood pressure monitoring, renal checks and signs of gastrointestinal bleeding.
Rural patients face supply variability and pharmacists play a key role arranging repeats, generics substitution and liaising with GPs regarding PBS authority paperwork.
Distribution & Pricing Landscape
How easy is it to get celecoxib in Australia and what does it cost?
Celecoxib in branded Celebrex form and generics is widely stocked by national chains and independent pharmacies.
Major pharmacy chains such as Chemist Warehouse, Priceline and TerryWhite generally list both branded and generic options with variable pricing.
PBS listings greatly influence out‑of‑pocket costs and dispensing patterns, and concession cardholders benefit from lower co‑payments.
Online pharmacies and telehealth e‑scripts have increased access, with pharmacists triaging contraindications and interactions at the point of dispensing.
Generics from manufacturers such as Teva, Sandoz and others commonly provide lower‑cost options that many patients choose.
Rural supply constraints and PBS authority paperwork can delay access, in which case pharmacists help maintain continuity through coordination with GPs.
In our online pharmacy, Celebrex and generic celecoxib are available with discreet delivery to Australia in 5‑14 days and pharmacists screen all orders for contraindications before dispatch.
Alternative Options
What are reasonable alternatives if celecoxib is unsuitable?
Comparison Table Of PBS And Non‑PBS Options
Compare alternatives by availability and risk profile when discussing choices with patients.
- Paracetamol – PBS‑accessible, lower GI/CV risk but less effective for inflammatory pain.
- Ibuprofen, Naproxen, Diclofenac – Traditional NSAIDs, widely available and effective but higher GI risk.
- Etoricoxib (Arcoxia®) – Another COX‑2 option with similar GI benefits and CV cautions; PBS status varies by indication.
Pros And Cons Checklist
Use a checklist to weigh options with patients.
- Celecoxib — Pro: reduced GI ulcer risk, effective for arthritis. Con: cardiovascular caution and prescription‑only status.
- Etoricoxib — Pro: COX‑2 benefits for GI tolerability. Con: variable PBS status and similar CV considerations.
- Non‑selective NSAIDs — Pro: lower cost and broad availability. Con: higher risk of GI complications.
- Paracetamol — Pro: low GI/CV risk and PBS‑accessible. Con: limited efficacy for inflammatory joint pain.
Regulatory Status
How are celecoxib products assessed and subsidised in Australia?
TGA Approval Framework
TGA assessment considers product quality, safety and efficacy for registration in Australia.
Post‑market surveillance contributes to periodic safety updates and advisories.
The supplied data did not specify the exact TGA registration details or dates for Australia.
PBS Subsidy Process
PBS listing requires a separate health economics evaluation of cost‑effectiveness and public benefit.
Not all indications or formulations are necessarily subsidised and some uses require PBS authority approvals.
Pharmacists verify PBS eligibility at dispensing and assist prescribers with authority criteria when needed.
Consolidated FAQ
What questions do patients ask most about celecoxib in Australia?
Q1: Can I get Celebrex on the PBS?
A1: PBS subsidy depends on the indication, concession status and current PBS listings; confirm eligibility with your GP or pharmacist.
Q2: Is celecoxib safer for my stomach?
A2: Compared with non‑selective NSAIDs, celecoxib tends to cause fewer clinically significant GI ulcers, but the risk is not zero and alcohol increases GI risk.
Q3: Can I take it with blood thinners?
A3: Concomitant anticoagulant or antiplatelet use increases bleeding risk and clinicians usually avoid combinations or monitor closely.
Q4: What about pregnancy and breastfeeding?
A4: Avoid celecoxib in pregnancy, especially the third trimester, and consult your obstetrician for alternatives.
Q5: Are generics equivalent?
A5: Generic celecoxib products meet regulatory standards and pharmacists can advise on interchangeability and cost‑saving options.
Visual Guide
Which visuals help patients and clinicians understand trade‑offs quickly?
Infographic suggestions include a PBS vs private cost flowchart showing eligibility and likely price ranges for branded Celebrex and generics at major chains.
A second visual could be a pain‑management algorithm from paracetamol through topical NSAID to celecoxib/etoricoxib and onward to specialist biologic therapy for severe rheumatoid arthritis.
A third infographic might display the dispensing workflow from GP e‑script through telehealth to pharmacist screening, highlighting contraindications, interactions and PBS authority checks.
Design notes: use clear icons for rural versus urban access, and colour coding for gastrointestinal risk versus cardiovascular risk to aid shared decision‑making.
Storage & Transport
How should celecoxib be stored at home and in pharmacy supply chains across Australian climates?
Household Storage Under Australian Climate
Store celecoxib capsules below 25°C in the original packaging and protect from moisture.
Avoid storing in bathrooms or humid places and choose a cool, dry cupboard away from direct sunlight, especially in hot northern climates.
Do not use tablets past their expiry date and keep medicines out of reach of children.
Cold‑Chain Logistics For Pharmacies
Celecoxib capsules are ambient‑stable and do not require cold‑chain transport.
Wholesalers and pharmacies should avoid prolonged exposure to temperatures above 25°C during summer or remote deliveries.
Check specific manufacturer guidance for any special storage instructions, particularly for non‑capsule formulations such as the US oral solution.
Guidelines For Proper Use
What should pharmacists cover when counselling patients starting celecoxib?
Pharmacist Counselling Style In Australia
Begin by confirming the indication and PBS eligibility.
Screen for allergies to sulfonamides, NSAID or aspirin sensitivity and document any history of asthma or GI ulceration.
Review cardiovascular, renal and hepatic history and discuss monitoring plans for blood pressure and renal function when therapy is long term.
Check the patient’s full medication list for anticoagulants, ACE inhibitors, lithium, methotrexate and CYP2C9 inhibitors.
Advise dosing expectations, missed‑dose rules and to avoid doubling up if a dose is missed.
Explain common side effects and when to seek urgent care for signs of GI bleeding or severe skin reactions.
Use plain language and shared decision‑making when weighing GI versus CV risk for chronic therapy.
National Health Authority Recommendations
TGA and RACGP–aligned recommendations stress the lowest effective dose for the shortest duration practicable and regular review of chronic use.
Report any suspected serious adverse events to the TGA as part of post‑market safety surveillance.
In rural settings emphasise access pathways such as telehealth e‑scripts and pharmacist coordination with local GPs for monitoring.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Darwin | Northern Territory | 5–9 days |
| Gold Coast | Queensland | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Newcastle | New South Wales | 5–9 days |
| Wollongong | New South Wales | 5–9 days |
| Townsville | Queensland | 5–9 days |
| Geelong | Victoria | 5–9 days |
| Bundaberg | Queensland | 5–9 days |
Concluding Practical Notes
What are the key takeaways for patients considering celecoxib?
Celecoxib is an effective COX‑2 selective anti‑inflammatory option for osteoarthritis, rheumatoid arthritis and certain acute pain syndromes when a prescription is appropriate.
It generally offers better gastrointestinal tolerability than non‑selective NSAIDs but requires cardiovascular risk consideration and renal monitoring.
Starting at the lowest effective dose and reviewing therapy periodically aligns with safety guidance from national and international authorities.
Pharmacists are a practical local resource for counselling about dosing, interactions with anticoagulants or blood pressure medicines, PBS eligibility and generic substitution.
For urgent concerns such as signs of GI bleeding, severe rash, or new‑onset breathlessness, advise immediate medical review.
Patients planning pregnancy or who are breastfeeding should consult their obstetrician or treating clinician before using celecoxib.
For cost or access questions contact your pharmacist to discuss PBS criteria, concession entitlements and brand versus generic options.