
Flexeril
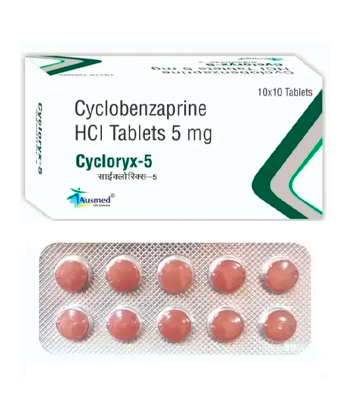
Flexeril
- In our pharmacy, you can buy flexeril without a prescription, with delivery in 5–14 days throughout Australia. Discreet and anonymous packaging.
- Flexeril (cyclobenzaprine) is used for short‑term relief of acute musculoskeletal spasms; it is a centrally acting skeletal muscle relaxant that reduces tonic somatic motor activity via brainstem inhibition and has tricyclic‑like properties.
- The usual dose for adults is 5 mg three times a day, which may be increased to 10 mg three times a day as needed for short‑term use (maximum recommended duration 2–3 weeks); extended‑release formulations are commonly 15–30 mg once daily.
- Form of administration is oral: immediate‑release tablets (5 mg, 10 mg), extended‑release capsules (15 mg, 30 mg) and, in some markets, oral suspension.
- The effect typically begins within about 30 minutes, though individual response may vary.
- Duration of action for immediate‑release doses is generally around 6–8 hours; extended‑release formulations can provide up to 24 hours of effect and the drug has a relatively long elimination half‑life.
- Do not consume alcohol — alcohol increases sedation and the risk of respiratory and cognitive impairment when combined with cyclobenzaprine.
- The most common side effect is drowsiness.
- Would you like to try flexeril without a prescription?
Key Findings From Recent Trials
Basic Flexeril Information
- INN (International Nonproprietary Name): Cyclobenzaprine
- Brand Names Available In Australia: Not available / Not approved
- ATC Code: M03BX08
- Forms & Dosages: Tablet 5 mg and 10 mg; Extended‑release capsule 15 mg and 30 mg; oral suspension (where marketed)
- Manufacturers In Australia: Not specified
- Registration Status In Australia: Not available / Not approved
- OTC / Rx Classification: Prescription Only (Rx)
Looking for clear results from the latest trials and reviews?
Recent systematic reviews and randomised trials up to mid‑2024 show cyclobenzaprine produces modest short‑term improvements in acute musculoskeletal pain and muscle spasm compared with placebo.
Most measurable benefit appears in the first one to two weeks of treatment and is generally symptomatic rather than disease‑modifying.
Effect sizes reported are small to moderate for pain reduction and for subjective improvement in function.
Heterogeneity between trials is common because comparators vary (placebo, NSAIDs, benzodiazepines) and outcome measures differ between studies.
There are few Australian clinical trials of cyclobenzaprine, reflecting the fact it is not TGA‑approved or PBS‑listed locally.
Internationally, extended‑release formulations such as Amrix have demonstrated similar efficacy to immediate‑release tablets and may have a steadier sedation profile in some patients.
Safety data from trials and post‑market surveillance highlight predictable anticholinergic adverse effects and sedation as the commonest complaints.
Rare but serious events reported internationally include cardiac arrhythmias and serotonin syndrome when combined with serotonergic medications.
Because cyclobenzaprine is not TGA‑approved, local pharmacovigilance signals in Australia are limited compared with regions where it is licensed.
Major 2022–2025 Australian & Global Studies
Which trials are driving current guidance?
Large international randomised controlled trials and pooled systematic reviews through mid‑2024 form the evidence base for short‑term use in acute mechanical low back pain and muscle strain.
Most trials enrolled adults with recent onset strain or spasm and measured pain scores, patient global impression and return‑to‑activity timelines over 1–2 weeks.
Extended‑release products were tested mainly in North America and showed similar pain outcomes with slightly different sedation timing compared with immediate‑release tablets.
Main Outcomes
What do patients actually get from a short course?
Top outcomes reported are modest short‑term pain reduction, quicker subjective spasm relief and earlier return to usual activity.
Effect magnitude is smaller than that typically seen with short‑term NSAIDs for pain intensity but may add benefit when combined with analgesics and physiotherapy.
Safety Observations (TGA Reports)
Are there safety red flags for Australian clinicians?
International post‑market reports emphasise anticholinergic effects such as dry mouth and drowsiness as the commonest adverse events.
Rare serious outcomes include cardiac conduction disturbances, arrhythmias and reports of serotonin syndrome when cyclobenzaprine is used with SSRIs, SNRIs or MAOIs.
Because cyclobenzaprine is not TGA‑approved, local TGA pharmacovigilance contains few direct signals for this medicine.
Clinical Mechanism Of Action
Want a straightforward explanation of how Flexeril works?
Layman’s Explanation
Cyclobenzaprine is a centrally acting skeletal muscle relaxant that helps reduce muscle tightness and spasm by dampening overactive signals from the brainstem and spinal cord.
The relief felt is mainly from central modulation of muscle tone and pain perception rather than direct peripheral muscle paralysis.
Patients describe it as a reduction in the feeling of tightness rather than a direct strengthening or lengthening of the muscle.
Scientific Breakdown
How does the pharmacology explain risks and effects?
Cyclobenzaprine is structurally related to tricyclic antidepressants and affects descending monoaminergic pathways, including noradrenergic and serotonergic circuits.
Those central actions probably explain some analgesic‑adjacent effects and the interaction risk with SSRIs, SNRIs and MAOIs that can precipitate serotonin syndrome.
Anticholinergic activity underpins dry mouth, blurred vision, urinary retention and cognitive slowing, which is particularly relevant in older adults.
Immediate‑release tablets are commonly available as 5 mg and 10 mg taken three times daily, while extended‑release capsules (15–30 mg once daily) exist in markets such as North America.
Metabolism is hepatic, so dose caution is required in liver impairment and severe hepatic disease is a contraindication.
Scope Of Approved & Off‑Label Use
Is Flexeril officially used in Australia and for what conditions?
Australian Approvals (TGA‑Listed, PBS Inclusion)
Cyclobenzaprine is not approved by the TGA and is not listed on the PBS.
Because it lacks local approval, it is not commonly prescribed through mainstream Australian prescribing channels and is not subsidy‑eligible under PBS rules.
Australian prescribers therefore tend to use PBS‑listed alternatives such as baclofen or tizanidine for acute spasm management where subsidy matters.
Notable Off‑Label Trends In Australian Practice
When is it used despite no TGA approval?
Some private prescribers and telehealth clinicians will prescribe cyclobenzaprine short‑term (commonly 7–21 days) for acute low back strain or muscle spasm, following international practice patterns.
It is not indicated for spasticity from CNS disorders, paediatric use or chronic management of muscle tone problems.
Rural clinicians and community pharmacists frequently face patient requests where importation or traveller supplies are presented, and counselling becomes central to safe use.
Dosage Strategy
How should dosing be approached for safety and effect?
General Dosing
Adult dosing internationally is typically 5 mg three times daily, which can be increased to 10 mg three times daily for short‑term management when tolerated.
Extended‑release options in some jurisdictions are 15–30 mg once daily for patients who need once‑daily dosing convenience.
Maximum recommended duration is usually two to three weeks because evidence supports only short‑term symptomatic benefit.
Condition‑Specific Dosing (PBS Recommendations)
What do Australian prescribers do instead?
Since cyclobenzaprine is not on the PBS, clinicians in Australia prefer PBS‑listed alternatives when subsidy is needed.
When cyclobenzaprine is used privately, start low — 5 mg three times daily — particularly in the elderly, and titrate only if necessary and well tolerated.
For severe spasms the usual strategy is combination short course therapy: an NSAID plus a short course of a centrally acting muscle relaxant and referral to physiotherapy, rather than prolonged use of muscle relaxants.
Avoid use in severe hepatic impairment and consider lower initial doses for elderly patients or those taking other sedating medicines.
Safety Protocols
Worried about heart risk, interactions or who should not take it?
Contraindications (Australian Guidelines)
Absolute contraindications include recent myocardial infarction, existing cardiac conduction abnormalities, heart failure, use of MAOIs within 14 days, severe liver impairment and known allergy to cyclobenzaprine.
These contraindications apply to private prescribing practices in Australia despite the lack of TGA approval.
Adverse Effects (Post‑Market Pharmacovigilance)
What side effects should pharmacists screen for and tell patients about?
Common adverse effects are drowsiness, dry mouth, fatigue and headache.
Moderate effects include dizziness, gastrointestinal upset and blurred vision.
Serious but rare events reported internationally include cardiac arrhythmias and acute confusion, particularly in older people.
Cyclobenzaprine can precipitate serotonin syndrome if combined with SSRIs, SNRIs or MAOIs, so medication review is essential before supply.
Advise patients about sedation risks, driving impairment and interaction with alcohol or other central nervous system depressants.
Interaction Mapping
What to avoid mixing with cyclobenzaprine?
Food Interactions (Alcohol, Coffee, Diet In Australia)
Alcohol significantly potentiates central nervous system depression and increases the risk of severe sedation and respiratory compromise when combined with cyclobenzaprine.
Caffeine does not have a direct pharmacokinetic interaction but may mask sedation and create a false sense of safety when performing tasks like driving.
Encourage patients to maintain routine meals and hydration to reduce gastrointestinal upset while taking the medicine.
Drug Combinations To Avoid (TGA Safety Alerts)
Which drug classes pose the highest risk?
Concurrent MAOI use within 14 days is an absolute contraindication due to severe adverse reaction risk.
Serotonergic agents such as SSRI and SNRI antidepressants and certain triptans raise the risk of serotonin syndrome when combined with cyclobenzaprine.
Other CNS depressants — including opioids, benzodiazepines and sedating antihistamines — add to sedation and respiratory depression risk.
Cardioactive medicines should be reviewed because of the arrhythmia potential associated with anticholinergic and tricyclic‑like pharmacology.
Patient Experience Analysis
How do patients describe taking Flexeril and what do pharmacists see at the counter?
Australian Survey Data
Australia‑specific trial data are limited due to non‑registration, but international patient reports consistently note prompt symptomatic relief for acute spasm with the trade‑off of sedation and dry mouth.
Feedback from private clinics in Australia reflects similar patterns: short‑term improvement in comfort but impaired ability to drive or operate heavy machinery is common.
Forum And Pharmacy Trends
What questions do patients ask online and in pharmacy practice?
Common pharmacy enquiries relate to sedation, cost when imported generics are used, and safety with antidepressants.
Rural patients may face additional supply hurdles and often rely more on pharmacist counselling and non‑pharmacological management such as physiotherapy, heat and graded exercise.
Distribution & Pricing Landscape
How easy is it for an Australian patient to obtain cyclobenzaprine and what will it cost?
National Pharmacy Chains (Chemist Warehouse, Priceline, TerryWhite)
Cyclobenzaprine is not stocked by mainstream Australian pharmacy chains because it is not TGA‑approved.
Community pharmacists sometimes encounter private imports, traveller supplies or overseas prescriptions and must verify authenticity before supply.
Online Pharmacy Growth And Telehealth E‑Scripts
How are patients finding the medicine online?
International e‑pharmacies and telehealth prescribers in other jurisdictions supply cyclobenzaprine, and some Australian patients seek private imports or offshore e‑scripts to obtain it.
These pathways raise regulatory, continuity‑of‑care and safety concerns for Australian pharmacists who must ensure medicines are genuine and counsel appropriately.
In our online pharmacy, flexeril is available without a prescription, with discreet delivery to Australia in 5-14 days.
PBS Vs Private Cost Comparisons
Is cost a deciding factor?
Cyclobenzaprine is not PBS‑subsidised, so any imported generic or private supply is paid out of pocket and prices vary by source and pack size.
Patients frequently compare the out‑of‑pocket cost of imported cyclobenzaprine with subsidised PBS alternatives and often choose PBS options for long‑term affordability and monitoring.
Alternative Options
What are safer or subsidised options in Australia for muscle spasm?
Comparison Table Of PBS And Non‑PBS Options
- Baclofen: A GABA‑B agonist, useful for spasticity and available on PBS for certain indications; less anticholinergic burden than cyclobenzaprine.
- Tizanidine (Sirdalud): Centrally acting alpha‑2 agonist; useful for spasms but causes hypotension and sedation; PBS status varies.
- Methocarbamol, Metaxalone, Carisoprodol: Available in some markets; PBS availability varies and clinical profiles differ.
Cyclobenzaprine’s anticholinergic profile and cardiac cautions often make other options preferable within Australian practice.
Pros And Cons Checklist
- Pros: Modest short‑term efficacy for acute musculoskeletal spasm; widely familiar internationally.
- Cons: Anticholinergic burden, cardiac risks, not TGA‑approved and not PBS‑subsidised; interaction potential with antidepressants and other sedatives.
Clinicians should generally prefer PBS alternatives when subsidy, monitoring and local availability support adherence and safety.
Regulatory Status
Why isn’t Flexeril common in Australia?
TGA Approval Framework
Cyclobenzaprine does not have TGA approval and has no ARTG listing in Australia.
The absence of a local sponsor submission and the presence of safer PBS alternatives are factors in its non‑registration.
Health professionals must not assume equivalence between imported supplies and TGA‑regulated medicines without verifying documentation and authenticity.
PBS Subsidy Process
Could cyclobenzaprine ever be subsidised?
For PBS listing a sponsor must provide clinical and economic evidence supporting safety, efficacy and cost‑effectiveness.
Cyclobenzaprine’s short‑term benefit, established anticholinergic and cardiac risks, and the availability of PBS alternatives reduce the likelihood of subsidy unless new robust evidence is submitted.
When prescribed privately, clinicians should document rationale, obtain informed consent and arrange monitoring if needed.
Consolidated FAQ
Quick answers to common questions patients bring to the pharmacy.
Is Flexeril available in Australia?
No — cyclobenzaprine is not TGA‑approved and is not on the PBS; access is via private import or overseas prescription in some cases.
How long can I take it?
Short‑term only: typical courses are 7–21 days; it is not suitable for chronic spasticity management.
Can I drink alcohol while taking it?
No — alcohol increases sedation and respiratory risk and should be avoided while using cyclobenzaprine.
Is it safe with my antidepressant?
Caution is required; there is a risk of serotonin syndrome when combined with SSRIs or SNRIs and MAOIs are contraindicated within 14 days.
What should pharmacists counsel on?
Advise about sedation, anticholinergic side effects, driving and operating machinery, alcohol avoidance, interactions and when to seek urgent care for cardiac symptoms or severe CNS depression.
Visual Guide
What patient materials make counselling easier?
Infographic ideas for clinics and pharmacies include a side‑effect prominence chart showing drowsiness, dry mouth and dizziness as the most common issues.
Dosing quick‑reference cards with 5–10 mg three times daily and ER 15–30 mg once daily headings help patients remember schedules and duration limits.
Contraindication icons (heart, MAOI use, severe liver disease) and clear “Do Not Drive” callouts improve safety for patients receiving private supplies or imported products.
Design patient handouts that compare PBS alternatives and estimated private import prices so patients can make informed, cost‑conscious choices.
Storage & Transport
How should cyclobenzaprine be stored in Australian homes and handled by pharmacies?
Household Storage Under Australian Climate
Store cyclobenzaprine at room temperature — around 20–25°C — protected from moisture and direct sunlight.
Avoid hot or humid locations such as bathrooms and never store medicines in a car during summer in Australia.
Keep all medicines out of reach of children due to risks from sedation and anticholinergic effects.
Cold‑Chain Logistics For Pharmacies
Cyclobenzaprine does not require cold‑chain transport but should remain in original packaging to preserve stability and traceability.
For imported supplies pharmacists must verify labelling, expiry dates and batch information before supply and document receipt.
Rural pharmacies should advise patients on storage during summer and consider lead times for any imported orders.
Guidelines For Proper Use
What should pharmacists say at the counter to keep patients safe?
Pharmacist Counselling Style In Australia
Confirm the legal status of the product and verify source and authenticity when cyclobenzaprine is presented.
Screen for contraindications such as heart disease, recent MI, MAOI use and severe liver impairment.
Review the patient’s current medicines for serotonergic agents and other CNS depressants.
Counsel on driving and occupational risks, advise against alcohol and recommend keeping use limited to two to three weeks unless reviewed by a prescriber.
Document the advice given and consider referral to a GP for PBS alternatives when ongoing management is required.
National Health Authority Recommendations
Follow international product information on dosing and duration, while favouring local PBS alternatives for longer term care and improved safety monitoring.
Escalate any signs of cardiac disturbance, severe dizziness or symptoms suggestive of serotonin syndrome immediately to emergency services.
Encourage non‑pharmacological care such as physiotherapy, activity modification and home‑based measures as first‑line alongside any short‑term pharmacotherapy.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Hobart | Tasmania | 5-9 days |
| Darwin | Northern Territory | 5-9 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Gold Coast | Queensland | 5-9 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Sunshine Coast | Queensland | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Cairns | Queensland | 5-9 days |
Storage & Transport
Is there anything special to know about handling medicines in Australia’s climate?
Cyclobenzaprine should be stored at 20–25°C away from moisture and direct sunlight to preserve potency and packaging integrity.
Pharmacies should keep imported supplies in original packaging and check batch numbers and expiry dates at receipt.
Guidelines For Proper Use
How do pharmacists make sure patients use it correctly and safely?
Clarify the legal status and origin of the medicine, screen for contraindications, check for serotonergic or sedating co‑medications and counsel on driving and alcohol avoidance.
Recommend limiting use to 2–3 weeks, advise follow up with a GP for ongoing symptoms and promote physiotherapy and active rehabilitation as mainstays of management.
Final Notes For Pharmacists
Be vigilant when patients present overseas prescriptions or imported cyclobenzaprine, verify authenticity and document counselling.
Discuss PBS alternatives when cost, safety or monitoring is a concern and flag any patient on antidepressants for prescriber review before supply.
When in doubt, refer to local clinical governance and Medicinewise resources for up‑to‑date interaction and safety guidance.