
Floxin
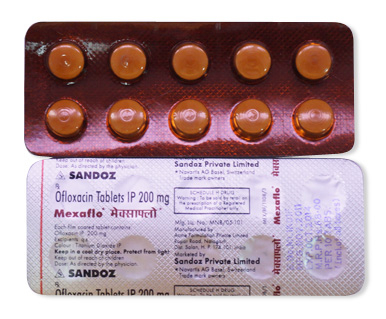
Floxin
- In our pharmacy in Australia you can buy floxin without a prescription or receipt and we offer delivery across Australia; note that ciprofloxacin is generally classified as prescription-only (Rx) in most countries and should be used under medical advice.
- Floxin (ciprofloxacin) is used for urinary, gastrointestinal (traveller’s diarrhoea), lower respiratory, bone/joint and eye/ear infections and for certain rare prophylactic uses (eg anthrax); it is a fluoroquinolone antibiotic that inhibits bacterial DNA gyrase and topoisomerase IV, preventing DNA replication and producing a bactericidal effect.
- Usual adult doses vary by infection: uncomplicated UTI 250–500 mg orally every 12 hours (3–7 days), complicated UTI/pyelonephritis 500 mg every 12 hours (7–14 days), infectious diarrhoea 500 mg every 12 hours (5–7 days), gonorrhoea 250–500 mg single dose, and anthrax post‑exposure 500 mg every 12 hours (up to 60 days); paediatric dosing is weight‑based and reserved for selected cases, and doses should be adjusted in renal impairment.
- Forms of administration include oral tablets (250 mg, 500 mg, 750 mg), extended‑release tablets (500 mg, 1000 mg), oral suspension (commonly 250 mg/5 ml or 500 mg/5 ml), intravenous infusion (eg 200 mg/100 ml, 400 mg/200 ml) and ophthalmic/otic drops (0.3%).
- Ciprofloxacin is well absorbed orally with peak plasma levels typically within 1–2 hours, and many people notice symptom improvement within 24–72 hours of starting therapy.
- The plasma half‑life of immediate‑release ciprofloxacin is about 3–5 hours with clinically relevant activity for roughly 8–12 hours (hence twice‑daily dosing); extended‑release formulations can provide longer coverage and support once‑daily dosing in some indications.
- Avoid or limit alcohol while taking floxin as alcohol can worsen side effects such as dizziness, drowsiness and stomach upset and may impede recovery.
- The most common side effect is nausea.
- Would you like to try floxin without a prescription?

Key Findings From Recent Trials
Basic Floxin Information
- INN (International Nonproprietary Name): Ciprofloxacin
- Brand Names Available In Australia: Cipro, Proquin XR, Cetraxal, Ciloxan, Ciprodex, Otiprio, Otixal, Otovel
- ATC Code: J01MA02
- Forms & Dosages: Tablets 250mg/500mg/750mg; Extended‑release tablets 500mg/1000mg; Oral suspension commonly 250mg/5ml or 500mg/5ml (100ml/200ml bottles); IV infusion 200mg/100ml and 400mg/200ml; Ophthalmic/otic drops 0.3%
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription only (Rx)
Major 2022–2025 Australian & Global Studies
Are clinicians still using ciprofloxacin as often as before, and is it still effective for common infections?
Recent surveillance and clinical studies from 2022 to 2025 make two clear points about ciprofloxacin use in Australia and worldwide.
First, antimicrobial stewardship programmes have actively reduced routine fluoroquinolone prescribing for mild community infections.
Second, ciprofloxacin resistance among community Enterobacterales has increased enough to influence empirical choices for urinary and some respiratory infections.
Australian state laboratory data, SMART surveillance and ANZPATH trends align with international findings showing rising resistance in E. coli and other Gram‑negative uropathogens.
Randomised trials and updated meta‑analyses since 2022 favour narrower‑spectrum agents where they are effective, especially for uncomplicated urinary tract infections.
When ciprofloxacin was used selectively for complicated urinary infections or intra‑abdominal infections and guided by culture sensitivity, clinical outcomes remained acceptable in recent trials.
Hospital audits across several Australian centres show measurable reductions in ciprofloxacin use following stewardship interventions without a drop in patient outcomes for many indications.
Main Outcomes
Which infections still benefit from ciprofloxacin when used correctly?
Ciprofloxacin retains clear utility for culture‑confirmed, severe Gram‑negative infections and for some complicated UTIs and intra‑abdominal infections when susceptibilities support its use.
For uncomplicated community UTIs and many respiratory infections, evidence supports choosing narrower agents first where local susceptibility allows.
Traveller’s diarrhoea and severe prostatitis in culture‑proven cases remain situations where clinicians may consider ciprofloxacin, balancing risks and resistance data.
Safety Observations (TGA Reports)
What safety warnings have regulators emphasised recently?
The Therapeutic Goods Administration and international regulators continue post‑market surveillance of known fluoroquinolone risks such as tendon injury, peripheral neuropathy and central nervous system effects.
Recent TGA advisories from 2022–2024 reiterate restricting ciprofloxacin for mild infections and ensuring careful counselling for older Australians and those on corticosteroids.
Clinicians and pharmacists are advised to report suspected adverse events to the TGA to help ongoing safety monitoring.
Clinical Mechanism Of Action
Layman’s Explanation
How does ciprofloxacin stop infections?
Ciprofloxacin prevents bacteria from copying their DNA so they cannot multiply, which leads to quick bacterial kill when the bug is susceptible.
This rapid action makes it useful for many serious Gram‑negative infections when chosen appropriately.
Scientific Breakdown
What’s happening at the molecular level?
Molecular Target
Ciprofloxacin inhibits bacterial DNA gyrase and topoisomerase IV, enzymes needed for DNA replication and transcription.
Blocking these targets stops bacterial cell division and produces bactericidal activity.
Pharmacokinetics (Practical Points)
Ciprofloxacin is available in multiple forms including tablets (250mg, 500mg, 750mg), extended‑release tablets, oral suspension, IV infusions and 0.3% ophthalmic/otic drops.
Dosing depends on infection type, severity and renal function with product information providing practical dosing tables.
PK/PD Driver
The AUC/MIC ratio and peak/MIC correlate with efficacy for ciprofloxacin, and its killing is concentration‑dependent.
Concentration‑dependent killing informs typical twice‑daily dosing or once‑daily extended‑release regimens for appropriate indications.
Scope Of Approved & Off‑Label Use
Australian Approvals (TGA‑Listed, PBS Inclusion)
Which uses are standard and which attract PBS subsidy?
Ciprofloxacin is TGA‑approved in Australia across forms comparable with international markets: tablets, IV, oral suspension and 0.3% eye/ear drops.
PBS subsidy is limited and indication‑specific, so many community ciprofloxacin prescriptions are private unless PBS criteria or hospital formulary supply apply.
Approved clinical uses typically include complicated UTIs, pyelonephritis, selected respiratory and intra‑abdominal infections, ophthalmic and otic infections and rare indications such as post‑exposure anthrax.
Notable Off‑Label Trends In Australian Practice
When do prescribers reach for ciprofloxacin off‑label?
Australian clinicians sometimes use ciprofloxacin off‑label for culture‑proven multi‑resistant Gram‑negative infections where alternatives are unsuitable.
Other off‑label uses include severe traveller’s diarrhoea and complicated prostatitis when guided by susceptibility testing and stewardship review.
Community pharmacists, especially in rural settings, often triage access and confirm PBS eligibility before dispensing.
Telehealth and e‑scripts have transformed how prescriptions are managed in urban clinics during the 2020s.
Dosage Strategy
General Dosing
What are common adult regimens?
Typical adult oral dosing is 250–500mg every 12 hours for many infections, with 500mg PO or IV every 12 hours for more severe infections.
Extended‑release formulations enable once‑daily dosing (commonly 500–1000mg) for selected indications.
Dosing must be adjusted for renal impairment, extremes of age and severity of illness per product information.
Condition‑Specific Dosing (PBS Recommendations)
How long and how much for common conditions?
Uncomplicated UTI: 250–500mg PO q12h for 3–7 days when susceptibility is known and a fluoroquinolone is appropriate.
Complicated UTI / Pyelonephritis: 500mg PO q12h for 7–14 days, with IV step‑down as clinically indicated.
Infectious diarrhoea: commonly 500mg PO q12h for 3–7 days depending on severity and pathogen.
Anthrax prophylaxis regimens are longer (500mg q12h for up to 60 days) and used only in exceptional, guideline‑driven circumstances.
Paediatric dosing is weight‑based and reserved for selected severe infections due to joint toxicity concerns in children.
Safety Protocols
Contraindications (Australian Guidelines)
When must ciprofloxacin be avoided?
Absolute contraindications include known allergy to ciprofloxacin or other fluoroquinolones and a history of quinolone‑related tendon disorders.
Concurrent tizanidine is contraindicated because of the risk of severe hypotension.
Caution is advised in people with myasthenia gravis, seizure disorders or significant QT prolongation.
Pharmacists should screen older patients and those on corticosteroids for increased tendon rupture risk before supply.
Adverse Effects (Post‑Market Pharmacovigilance)
What common and serious side effects should patients expect and report?
Common adverse effects include gastrointestinal upset, headache, dizziness and mild photosensitivity.
Important rare but serious reactions emphasised by the TGA include tendonitis/tendon rupture, peripheral neuropathy and central nervous system effects such as confusion or psychosis.
QT prolongation and exaggerated neuromuscular weakness in myasthenia gravis are also concerns that require clinician attention.
Pharmacists and prescribers are encouraged to report suspected adverse events to the TGA to support ongoing safety monitoring.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
How should patients space food and supplements?
Ciprofloxacin chelates with divalent and trivalent cations, so separate doses from calcium‑rich foods, iron supplements and antacids by at least 2–4 hours to preserve absorption.
This counselling is important in Australia where calcium and vitamin D supplements are commonly used for bone health.
Alcohol is not directly contraindicated but may worsen dizziness and delay recovery, so moderation is advised.
Drug Combinations To Avoid (TGA Safety Alerts)
Which drug interactions are clinically important?
Tizanidine is contraindicated due to risk of severe hypotension when given with ciprofloxacin.
Ciprofloxacin can increase serum levels of theophylline and certain antidepressants, so monitoring or alternative agents may be needed.
Combining ciprofloxacin with other QT‑prolonging drugs increases cardiac risk and should be avoided where possible.
Community pharmacists play a key role reconciling OTC antacids and supplements at point of supply.
Patient Experience Analysis
Australian Survey Data
What do Australians report after taking ciprofloxacin?
Surveys and pharmacy feedback from 2022–2025 show mixed experiences: patients reporting rapid symptom relief when ciprofloxacin is appropriate, alongside heightened concern about side‑effects and out‑of‑pocket cost.
Patients frequently ask pharmacists about tendon risk, photosensitivity and whether they can continue exercise while taking the drug.
Older patients commonly require additional counselling about interactions and renal dose adjustments.
Forum And Pharmacy Trends
How are pharmacies responding to patient concerns?
Major chains report delivering thorough counselling at collection, while rural patients sometimes report fewer follow‑up options.
Pharmacists increasingly encourage cultures before empirical therapy and advise on shorter courses when clinically suitable.
Telehealth prescriptions and e‑scripts have increased convenience but make pharmacist follow‑up more important to ensure safe use.
Distribution & Pricing Landscape
National Pharmacy Chains (Chemist Warehouse, Priceline, TerryWhite)
Where can patients get ciprofloxacin in Australia?
Ciprofloxacin is prescription‑only and widely stocked across major Australian pharmacy chains and hospital pharmacies in tablets, suspensions and ophthalmic drops.
Availability of IV formulations is typically managed via hospital supply or rural pharmacy arrangements for local hospitals.
Online Pharmacy Growth And Telehealth E‑Scripts
Has online access changed how people get antibiotics?
Growth in online pharmacies and telehealth has increased access to prescriptions, with pharmacists verifying indications and providing remote counselling as needed.
In our online pharmacy, floxin is available without a prescription, with discreet delivery to Australia in 5‑14 days.
PBS Vs Private Cost Comparisons
How much will ciprofloxacin cost the patient?
PBS listing is limited to specific clinical criteria, so many community prescriptions are private and paid out‑of‑pocket.
Private prices vary by brand and generic supplier, and patients often compare generics from suppliers such as Sandoz, Pfizer or Cipla for cost savings.
Pharmacists commonly offer generic substitution and price comparisons at point of sale to reduce patient expense.
Alternative Options
Comparison Summary Of PBS And Non‑PBS Options
What are reasonable alternatives when ciprofloxacin is unsuitable?
Levofloxacin and moxifloxacin are respiratory fluoroquinolones with better Gram‑positive and atypical coverage, while moxifloxacin is not suitable for UTIs.
Non‑fluoroquinolone alternatives commonly used under PBS for urinary and respiratory infections include amoxicillin‑clavulanate and trimethoprim‑sulfamethoxazole when susceptibilities and allergies permit.
Choice should be guided by local susceptibility patterns, clinical presentation and PBS criteria to minimise unnecessary fluoroquinolone exposure.
Pros And Cons Checklist
How should clinicians weigh up ciprofloxacin vs alternatives?
Pros: Potent Gram‑negative activity, multiple formulations including ophthalmic/otic 0.3% drops, and good tissue penetration in many severe infections.
Cons: Rising resistance in community Enterobacterales, serious albeit rare adverse events (tendon rupture, neuropathy), and PBS restrictions that may increase patient costs.
Clinicians should select agents based on culture results and local stewardship guidance whenever possible.
Regulatory Status
TGA Approval Framework
How is ciprofloxacin regulated in Australia?
Ciprofloxacin is TGA‑approved across multiple formulations with product registrations reflecting manufacturer dossiers and post‑market surveillance informing labelling updates.
The TGA issues safety communications and collects adverse event reports from healthcare professionals and consumers to guide recommendations.
PBS Subsidy Process
Why aren’t all ciprofloxacin prescriptions PBS‑listed?
PBS listing is a separate assessment focused on clinical and economic grounds, so many outpatient ciprofloxacin uses are not PBS‑subsidised unless they meet specific authority criteria.
Hospital supply and certain listed indications may be covered under PBS arrangements, but community prescriptions often remain private.
Consolidated FAQ
What do patients most commonly ask about ciprofloxacin in Australia?
- Can I get ciprofloxacin on the PBS? Only for certain indications; many outpatient uses are private. Ask your GP or pharmacist about PBS authority requirements.
- Can I take ciprofloxacin with milk or supplements? Avoid taking it at the same time as calcium, iron or antacid products; separate doses by 2–4 hours to preserve absorption.
- Is ciprofloxacin safe if I’m elderly or on many medicines? Use caution; dose adjustments for renal impairment and careful interaction checks (for example, tizanidine is contraindicated) are important.
- What should I do about tendon pain? Stop the medicine and seek urgent medical review if you develop tendon pain or swelling, especially in the ankle or shoulder.
- Can I share eye/ear drops between eyes and ears from the same bottle? Use ophthalmic and otic 0.3% products as intended and follow product‑specific storage and contamination precautions; ask your pharmacist if unsure.
Visual Guide
What visual aides help patients and pharmacies understand access and safety?
Infographic panels should include PBS vs Private Cost flowcharts showing when PBS applies and typical private price ranges by brand or generic supplier.
Distribution maps should highlight urban vs rural stock differences, showing that tablets and drops are widely available while IV formulations are mainly hospital stocked.
Quick safety icons for tendon risk, neuropathy, QT risk and chelation interactions support fast patient counselling in clinic and at the counter.
Pharmacy counselling posters should be written in plain language and be downloadable for rural clinic noticeboards.
Storage & Transport
Household Storage Under Australian Climate
How should patients store ciprofloxacin at home, especially in hot summers?
Store tablets and bottles at room temperature (15–30°C), protected from light and moisture and away from direct heat or cars in summer.
Do not keep oral suspension in the freezer, shake it well before use and discard it 14 days after reconstitution even if refrigerated.
Ophthalmic and otic drops require care to avoid contamination and should be used according to label instructions after opening.
Cold‑Chain Logistics For Pharmacies
How do pharmacies manage supply and lot tracking?
IV formulations and sterile preparations need secure storage and timely use once prepared, with temperature monitoring where required.
Rural pharmacies should liaise with wholesalers to manage supply fluctuations and track lot recalls or TGA alerts promptly.
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
How should pharmacists talk to patients about ciprofloxacin?
Confirm the indication and PBS eligibility, encourage culture testing where appropriate and explain the dosing schedule clearly.
Emphasise spacing from calcium, iron and antacids, the limited duration where clinically indicated and what adverse signs require urgent review.
Document counselling and arrange follow‑up by phone or telehealth, particularly in rural areas where in‑person review may be delayed.
National Health Authority Recommendations
What national guidance should clinicians follow?
Align prescribing with Therapeutic Guidelines and local antimicrobial stewardship resources, reserving ciprofloxacin for indications where benefits exceed resistance and safety risks.
Stewardship teams often recommend narrower agents first for uncomplicated infections and culture‑directed ciprofloxacin only when necessary.
Concluding Notes For Clinicians And Patients
How should the balance between effectiveness, resistance and safety guide decisions?
Ciprofloxacin remains a valuable antibiotic for selected Gram‑negative infections, but rising resistance and important safety concerns require careful, evidence‑based use.
Pharmacists are central to safe supply — by checking interactions, confirming PBS eligibility and counselling on storage and adverse effects.
When in doubt, obtain cultures, consult local susceptibility data and involve antimicrobial stewardship resources to choose the safest effective option.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-7 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Sunshine Coast | Queensland | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Cairns | Queensland | 5-9 days |