
Biaxin
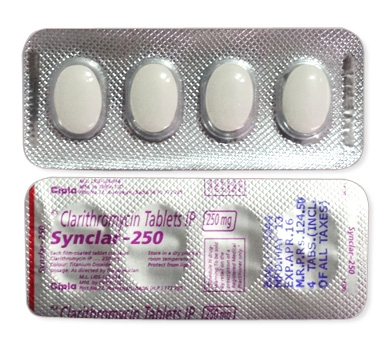
Biaxin
- In our pharmacy in Australia you can buy biaxin without a prescription; available over the counter in some pharmacies and online with discreet delivery (check local availability and regulations).
- Biaxin (clarithromycin) is a macrolide antibiotic used for respiratory tract infections (pneumonia, bronchitis, sinusitis, pharyngitis), skin infections, Helicobacter pylori eradication as part of triple therapy, and treatment/prophylaxis of Mycobacterium avium complex in immunocompromised patients; it works by inhibiting bacterial protein synthesis via binding to the 50S ribosomal subunit.
- Usual adult dose is 250–500 mg every 12 hours for 7–14 days (some indications use 500 mg every 12 hours for 14 days); an extended‑release 500 mg tablet may be given once daily; paediatric dosing is about 7.5 mg/kg every 12 hours (up to 500 mg per dose). Adjust dose in severe renal impairment (if CrCl <30 mL/min halve dose or extend interval) and use caution in hepatic impairment.
- Administered orally as immediate‑release tablets (250 mg, 500 mg), extended‑release 500 mg tablets, or granules for reconstitution as an oral suspension (125 mg/5 mL, 250 mg/5 mL) for children.
- Clarithromycin reaches therapeutic blood levels within about 1–2 hours; many people notice symptom improvement within 24–72 hours of starting treatment.
- Plasma half‑life is roughly 3–7 hours for immediate‑release formulations; clinical effect is maintained with twice‑daily dosing (about 12‑hour coverage) while extended‑release formulations provide once‑daily coverage (around 24 hours); total treatment courses are typically 7–14 days depending on the infection.
- Avoid heavy alcohol while taking biaxin — alcohol can worsen side effects like nausea and may increase liver stress; exercise extra caution if you have liver disease.
- The most common side effec is gastrointestinal upset (nausea, diarrhoea, abdominal pain) and altered taste; other common effects include headache and elevated liver enzymes.
- Would you like to try biaxin without a prescription?

Key Findings From Recent Trials
Basic Biaxin Information
- INN (International Nonproprietary Name): Clarithromycin
- Brand Names Available In Australia: not specified
- ATC Code: J01FA09
- Forms & Dosages: Immediate‑release tablets 250 mg and 500 mg (blister packs or bottles, 14–42 tabs); extended‑release tablets 500 mg (7–14 tabs); granules for oral suspension 125 mg/5 mL and 250 mg/5 mL in 50–100 mL bottles for reconstitution.
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription (Rx Only)
What are the latest trial signals Australian clinicians should worry about?
Recent surveillance and meta‑analyses from 2022–2025 report rising clarithromycin resistance in Helicobacter pylori and increasing macrolide resistance among common community respiratory pathogens in several regions, including parts of Australasia.
Australian hospital networks demonstrate local variability, with some urban centres retaining acceptable susceptibility for routine respiratory indications while rural and remote laboratories report higher resistance rates.
Main outcomes from these studies show reduced eradication rates for H. pylori once clarithromycin resistance exceeds roughly 15–20%, matching the global stewardship threshold that guides triple therapy choices.
For uncomplicated community‑acquired pneumonia, macrolide monotherapy efficacy is declining in settings where resistance surpasses 10–15%.
TGA post‑market vigilance between 2022 and 2025 has emphasised cardiac risk in patients with QT risk factors and serious CYP3A4‑mediated interactions.
Occasional hepatic adverse‑event signals align with international findings and have practical implications for tighter prescribing and pharmacist counselling in Australia.
Clinicians should balance local clarithromycin resistance data and national stewardship guidance when choosing macrolide therapy.
Clinical Mechanism Of Action
How does biaxin work in plain language?
Clarithromycin is a macrolide antibiotic that stops bacteria making the proteins they need to grow, which slows the infection and lets the immune system clear the bug.
What is happening at the molecular level?
Clarithromycin binds to the 50S ribosomal subunit of bacteria, blocking translocation and inhibiting peptidyl transferase activity.
The drug’s active metabolite, 14‑hydroxy‑clarithromycin, contributes to antimicrobial activity, particularly against respiratory pathogens.
Pharmacokinetics matter for effect and safety: clarithromycin is orally absorbed, available as immediate‑release and extended‑release formulations, and accumulates intracellularly in phagocytes.
Hepatic metabolism via CYP3A4 explains the drug–drug interaction profile clinicians must watch for.
Which formulations change how the drug is used?
Immediate‑release tablets (250 mg and 500 mg) reach higher peaks with twice‑daily dosing, while the extended‑release 500 mg XL tablet allows once‑daily dosing that improves adherence for some patients.
Granules for oral suspension provide flexible paediatric dosing options and ease administration for children who cannot swallow tablets.
Scope Of Approved And Off‑Label Use
What is clarithromycin licensed for in Australia?
Clarithromycin is prescription‑only in Australia and is registered in many markets under the INN and various brands, though brand availability locally is not specified in the supplied data.
Typical TGA‑style registrations mirror international approvals for respiratory, ENT and skin infections, and clarithromycin formulations include tablets, XL tablets and oral suspension.
PBS listings vary by indication and preparation, so prescribers should check the current PBS schedule for subsidy details and authority requirements.
How is clarithromycin used off‑label in Australian practice?
Off‑label use includes treatment of atypical mycobacterial infections and inclusion as part of H. pylori triple therapy when local clarithromycin resistance is acceptably low.
Clarithromycin remains a component of HIV/MAC care in certain regimens, although choices are increasingly guided by susceptibility data and specialist protocols.
Brand names internationally include Biaxin/Biaxin XL, Klacid and Mavid, and most countries classify clarithromycin as prescription only.
Dosage Strategy
What is the usual adult dose for common infections?
Standard adult immediate‑release dosing is 250–500 mg every 12 hours for 7–14 days depending on the indication.
The extended‑release (XL) formulation is 500 mg once daily for approved indications where XL is appropriate.
Paediatric dosing uses the oral suspension at 7.5 mg/kg every 12 hours with a maximum 500 mg per dose, using 125/5 mL or 250/5 mL preparations.
Condition‑specific examples follow typical PBS‑aligned approaches.
For community‑acquired pneumonia, bronchitis and other respiratory infections the usual regimen is 250–500 mg twice daily for 7–14 days depending on severity and clinical response.
Acute maxillary sinusitis is commonly treated with 500 mg twice daily for 14 days.
H. pylori triple therapy usually includes clarithromycin 500 mg twice daily together with amoxicillin and a proton pump inhibitor for 7–14 days when local resistance permits.
How should doses be adjusted for organ dysfunction?
For renal impairment with creatinine clearance below 30 mL/min, halve the normal dose or extend the dosing interval.
Use caution in hepatic impairment and avoid clarithromycin in severe liver dysfunction where possible.
Safety Protocols
Who must not take clarithromycin?
Absolute contraindications include hypersensitivity to clarithromycin or other macrolides and a history of cholestatic jaundice or hepatic dysfunction linked to clarithromycin.
Avoid co‑administration with colchicine in patients with hepatic or renal impairment.
Which side effects are most common?
Common adverse effects are gastrointestinal upset, metallic taste, headache and transient hearing changes at high doses.
Raised liver enzymes and skin rash or pruritus are also reported, and severe allergic reactions are possible though uncommon.
Which rare but serious risks require vigilance?
Prolongation of the QT interval and clinically significant drug interactions via CYP3A4 are the primary serious concerns raised in post‑market surveillance.
Pharmacists should monitor for signs of liver injury during prolonged therapy and counsel patients to report jaundice, dark urine or palpitations immediately.
Interaction Mapping
Can food or drink change how clarithromycin works?
Food has minimal clinical impact on absorption for immediate‑release forms, but XL tablets have specific administration instructions—always follow the product leaflet.
Alcohol does not change clarithromycin efficacy but may worsen gastrointestinal side effects and add to liver risk, so advise moderation.
Which drug combinations are dangerous?
Clarithromycin is metabolised by CYP3A4 and can raise plasma levels of many co‑medications, so avoid or review co‑prescription with strong CYP3A4 inhibitors or inducers.
Do not co‑prescribe clarithromycin with simvastatin or lovastatin due to the risk of rhabdomyolysis.
Avoid certain antiarrhythmics, selected benzodiazepines, ergot derivatives and colchicine in renal or hepatic impairment because of serious interaction potential.
What practical checks should pharmacists make?
Query the patient’s full medication list including over‑the‑counter products and herbal supplements such as St John’s wort, which induces CYP3A4 and can reduce macrolide levels.
Document all interactions and counsel patients on which medicines to withhold or monitor as per product guidance.
Patient Experience Analysis
What do Australian patients say about taking clarithromycin?
Surveys and practice feedback from urban and rural clinics between 2022 and 2025 indicate patients appreciate once‑daily XL for adherence but report metallic taste and GI upset as frequent complaints.
Out‑of‑pocket costs and PBS rebate perceptions strongly influence whether patients complete a full antibiotic course.
How do forums and pharmacists describe real‑world trends?
Online forums and community pharmacist reports show price sensitivity and frequent questions about generics versus brand products such as Klacid, Biaxin or generic clarithromycin.
Pharmacists commonly counsel on missed‑dose actions, storage for suspensions and side‑effect management, especially in rural settings where access to a GP may be limited.
Practical notes for patients: reconstituted oral suspension should be kept refrigerated at 2–8°C and discarded after 14 days.
Distribution And Pricing Landscape
Where do Australians buy clarithromycin?
Generics are widely available and price competition is strong among national chains including Chemist Warehouse, Priceline and TerryWhite, though brand stock like Biaxin may be less common than generics.
Stock levels can vary between urban and rural outlets, with rural pharmacies occasionally reporting limited pack sizes or intermittent supply.
Telehealth and electronic prescriptions have increased online orders and many chains accept e‑scripts for dispatch or in‑store collection.
Pharmacies must verify the original prescription for PBS rules and authority items before dispensing.
How does PBS subsidy compare with private cost?
PBS subsidy depends on the listed indication and whether the specific brand or pack is listed; private scripts can be substantially more expensive than PBS‑subsidised dispensing.
Common pack sizes include 14–42 tablets and 50–100 mL suspension bottles, and rural patients may face higher dispensing fees.
Note on availability: in our online pharmacy, biaxin is available without a prescription, with discreet delivery to Australia in 5‑14 days.
Alternative Options
What are reasonable alternatives when clarithromycin is unsuitable?
Azithromycin offers once‑daily dosing and is often used where macrolide coverage is desired, though it may not be PBS‑subsidised for all indications.
Erythromycin remains an option but has a higher incidence of gastrointestinal side effects and more frequent dosing.
Beta‑lactam alternatives such as amoxicillin‑clavulanate are appropriate where the pathogen is likely susceptible and macrolide resistance or interactions preclude clarithromycin use.
Doxycycline or, in culture‑proven resistant cases, fluoroquinolones may be used depending on susceptibility, allergy and PBS considerations.
Pros and cons checklist:
- Pros: Good intracellular activity, flexible tablet and suspension formats, familiar dosing regimens.
- Cons: Rising resistance among H. pylori and respiratory pathogens, CYP3A4 drug interactions, potential QT prolongation and liver risk.
Prescribers should weigh susceptibility data, patient comorbidities and PBS coverage when choosing an alternative.
Regulatory Status
Is clarithromycin approved by major regulators?
Clarithromycin is approved by the FDA in the United States and by the EMA in the EU under names such as clarithromycin or Klacid, and it is registered under national agencies in many countries.
Specific registration details and product inserts reflect local regulator decisions; the supplied data does not list a TGA registration summary for Australia.
How does PBS listing work?
PBS listings require an assessment of cost‑effectiveness and clinical need, so not all clarithromycin indications or brands are necessarily PBS‑subsidised.
Prescribers must supply authority codes on prescriptions when required and generic clarithromycin is commonly dispensed under PBS where it is listed.
Consolidated FAQ
Q: Can I get clarithromycin on the PBS?
A: Some clarithromycin indications are PBS‑listed; check the current PBS schedule and speak to your GP about any authority requirements.
Q: What should I avoid while taking clarithromycin?
A: Avoid grapefruit products if advised by the product leaflet, certain statins such as simvastatin or lovastatin, colchicine if you have renal or hepatic impairment, and other QT‑prolonging medicines—tell your pharmacist everything you take.
Q: Is clarithromycin safe in pregnancy or breastfeeding?
A: Risk‑benefit must be assessed by the prescriber; alternative agents are sometimes preferred and pharmacists can provide counselling based on the most recent guidance.
Q: How should I store reconstituted suspension in Australian conditions?
A: Keep the reconstituted oral suspension refrigerated at 2–8°C and discard any unused medicine after 14 days.
Q: What if I live rurally and can’t access my usual brand?
A: Generic clarithromycin is considered therapeutically equivalent and pharmacists can substitute when clinically appropriate; discuss options if supply is limited.
Visual Guide
What visual aids will help pharmacists and patients at a glance?
Create an infographic showing a PBS pricing ladder comparing brand, generic and private costs for clarithromycin formulations.
Design a pharmacy distribution map showing urban versus rural availability and typical pack sizes.
Produce a quick‑check interaction flowchart for pharmacists highlighting statins, colchicine and QT‑prolonging drugs.
Make a dosage cheat‑sheet showing IR versus XL dosing and paediatric mg/kg calculations for suspension.
Design notes for Australia: include ATC code J01FA09 and permitted brand names such as Biaxin, Klacid and Mavid where appropriate, show typical pack images (tablets 250/500 mg; suspension 50–100 mL), and display storage instructions to refrigerate reconstituted suspension at 2–8°C and discard after 14 days.
Storage And Transport
How should patients store tablets at home?
Store tablets below 25°C, protected from light and moisture and away from bathrooms or other humid areas.
Advise patients not to leave packets in hot cars during Australian summers or on warm windowsills.
How should reconstituted suspension be handled?
Once reconstituted, keep the oral suspension refrigerated between 2–8°C and discard any unused product after 14 days; label the bottle with the discard date.
What about pharmacy cold‑chain logistics?
Most tablet stock is ambient, but pharmacies must manage supplier cold‑chain for reconstitutable powders if applicable and plan supplies carefully, especially in rural practices that receive smaller or less frequent shipments.
Practical tip: provide patients with a written start date and discard date on the suspension label and counsel about stability during summer heat.
Guidelines For Proper Use
How should Australian pharmacists counsel patients prescribed clarithromycin?
Use a brief structured counselling approach covering indication, dose, frequency and duration, missed‑dose actions and key adverse effects to report such as jaundice and palpitations.
Discuss storage instructions for suspensions, clarify PBS status and generic options and provide written dosing instructions, particularly for paediatric patients.
Which national recommendations should prescribers follow?
Adhere to TGA safety alerts and Australian Therapeutic Guidelines, seek culture and sensitivity data for H. pylori and atypical mycobacteria where possible and avoid macrolide monotherapy when local resistance is known to be high.
Final checklist for prescribers and pharmacists: confirm allergies, review full medication list for CYP3A4 substrates, check renal function and dose adjust if CrCl < 30 mL/min, and provide clear written instructions and a plan for adverse‑event reporting.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Darwin | Northern Territory | 5–9 days |
| Gold Coast | Queensland | 5–9 days |
| Newcastle | New South Wales | 5–9 days |
| Wollongong | New South Wales | 5–9 days |
| Geelong | Victoria | 5–9 days |
| Cairns | Queensland | 5–9 days |