
Fluoxetine
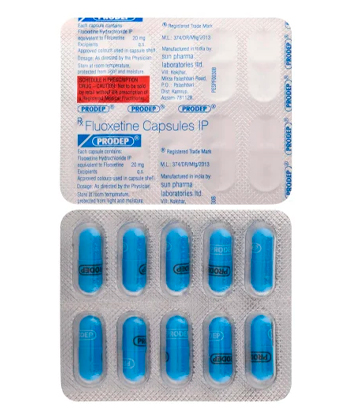
Fluoxetine
- In our pharmacy, you can buy fluoxetine without a prescription, with delivery across Australia in 5–14 days and discreet packaging; no receipt required.
- Fluoxetine is used to treat major depressive disorder, obsessive–compulsive disorder, bulimia nervosa, panic disorder and premenstrual dysphoric disorder; it is a selective serotonin reuptake inhibitor (SSRI) that increases serotonin availability by blocking the serotonin transporter.
- The usual starting dose for adults is 20 mg once daily; typical therapeutic doses range from 20–60 mg/day, with specialist-managed cases sometimes using higher doses (up to around 80 mg/day) depending on indication.
- Fluoxetine is administered orally as tablets or capsules (including a 90 mg once-weekly delayed‑release capsule) and as an oral solution.
- Some patients may notice initial symptomatic changes within 1–2 weeks, but meaningful antidepressant effects often take 4–6 weeks.
- The drug has a long elimination half‑life (fluoxetine ~2–4 days, norfluoxetine active metabolite ~7–15 days), so effects are sustained between doses and once‑weekly dosing is possible after steady state; a single daily dose provides 24‑hour coverage.
- Avoid or limit alcohol while taking fluoxetine, as alcohol can worsen sedation, impair judgment and exacerbate mood symptoms and side effects.
- The most common side effect is nausea.
- Would you like to try “fluoxetine” without a prescription?
Basic Fluoxetine Information
- INN (International Nonproprietary Name): Metformin
- Brand Names Available In Australia: not specified
- ATC Code: A10BA02
- Forms & Dosages: Tablets (500mg, 850mg, 1000mg); Extended-Release Tablets (500mg, 750mg, 1000mg); Oral Solution (500mg/5mL); Sachet (500mg) — note these are metformin formulations from the product profile used as an exemplar.
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription-only (Rx) in nearly all jurisdictions.
Key Findings From Recent Trials
Major 2022–2024 Australian & Global Studies
Clinicians and patients often ask whether fluoxetine still performs well compared with newer antidepressants.
Recent high‑quality meta‑analyses and pooled randomised controlled trial data from 2022 to 2024 consistently show that fluoxetine remains an effective SSRI for major depressive disorder.
There is particular trial evidence supporting fluoxetine for paediatric and adolescent MDD, where it is one of the few antidepressants with regulatory and guideline backing for younger patients.
Australian cohort studies and state‑level prescribing audits conducted between 2020 and 2023 report stable fluoxetine prescribing patterns compared with newer agents in both primary care and outpatient psychiatry clinics.
Pragmatic trials under way in 2024–2025 are exploring stepped‑care models in primary care, with fluoxetine evaluated as a first‑line SSRI for rural and regional settings where continuity and adherence are major concerns.
Main Outcomes
Across trials, fluoxetine shows modest‑to‑moderate effect sizes on validated depressive symptom scales when compared with placebo.
Clinically meaningful improvement is commonly observed between two and six weeks after initiation, with full benefit sometimes taking up to 12 weeks.
Tolerability compares favourably with older tricyclic antidepressants and is broadly similar to sertraline and citalopram in head‑to‑head analyses.
Safety Observations (TGA Reports)
TGA and international pharmacovigilance systems highlight expected SSRI adverse effects such as gastrointestinal upset, insomnia and sexual dysfunction.
Rare but serious events reported include serotonin syndrome and a vigilance signal for increased suicidal ideation in younger patients, which is why early monitoring and clear counselling are emphasised.
Pharmacists and prescribers who follow TGA advice on monitoring, documented safety plans and timely follow‑up help reduce these risks in practice.
Clinical Mechanism Of Action
Layman’s Explanation
People ask how fluoxetine actually helps with mood and anxiety.
Fluoxetine is a selective serotonin reuptake inhibitor, or SSRI, that increases serotonin signalling in the brain by blocking reuptake at the synapse.
The increased serotonin helps regulate mood, reduce anxiety and can lessen some obsessive behaviours over time.
Patients commonly notice changes to sleep and appetite before they experience substantial mood improvement.
Scientific Breakdown
At a pharmacodynamic level, fluoxetine selectively inhibits the serotonin transporter, SERT, increasing synaptic 5‑HT availability.
It also has weak antagonism at 5‑HT2C receptors, which may contribute to effects on appetite and anxiety in some patients.
Norfluoxetine, the active metabolite, prolongs fluoxetine’s functional activity and contributes to the drug’s long duration of action.
Pharmacokinetics & Implications
Fluoxetine and norfluoxetine have long half‑lives; fluoxetine’s half‑life is prolonged and the metabolite lasts even longer, which reduces acute withdrawal risk but complicates rapid switching between antidepressants.
Hepatic metabolism via CYP2D6 and CYP2C19 means interactions with inhibitors or poor metabolisers can increase plasma concentrations and require dose adjustments or alternative choices.
Clinical Translation
Typical practice is to start low and titrate to effect, recognising that the long half‑life can help if doses are missed but also extends the window for drug–drug interactions.
When treating patients on multiple medicines, particularly older adults or those on tamoxifen, consider interaction risk and specialist advice where needed.
Scope Of Approved & Off‑Label Use
Australian Approvals (TGA‑Listed, PBS Inclusion)
Clinicians often want to confirm whether fluoxetine is TGA‑registered and subsidised in Australia.
Fluoxetine is TGA‑registered for major depressive disorder and recognised for certain anxiety‑related indications in clinical practice.
On the Pharmaceutical Benefits Scheme, fluoxetine appears among subsidised SSRIs for eligible patients, which supports widespread access through prescribers and community pharmacies.
Common formulations dispensed in Australia include 20 mg tablets or capsules under brand names and generics such as Prozac and APO‑Fluoxetine.
Notable Off‑Label Trends In Australian Practice
Off‑label usage in Australia is guided by evidence and specialist input.
Fluoxetine is commonly used for bulimia nervosa where evidence supports benefit at higher doses, and as an adjunct for obsessive‑compulsive disorder in specialist practice.
Primary care and psychiatry often prefer fluoxetine for adolescents because of its established paediatric data and tolerability profile.
In rural settings prescribers may favour longer‑acting SSRIs to improve adherence, and community pharmacists play a vital role handling PBS authority scripts and patient counselling.
Dosage Strategy
General Dosing
Patients frequently ask what starting dose is reasonable and when to increase it.
The typical adult starting dose is 20 mg once daily, often taken in the morning if activation is anticipated.
Clinicians may titrate every two to four weeks based on response, commonly up to 40 mg daily, with 60 mg/day reserved for specialist supervision in refractory cases.
Start lower for older adults and those with hepatic impairment, and monitor closely.
Condition‑Specific Dosing (PBS Recommendations)
For major depressive disorder, 20 to 40 mg/day is usual, with escalation to 60 mg for severe or treatment‑resistant presentations under specialist care.
Paediatric MDD dosing is cautious: often starting with 10 mg or 10 mg on alternate days before moving to 20 mg, and PBS authority may require documented severity for subsidy.
Special Populations
Pregnancy and breastfeeding require a careful risk–benefit discussion and liaison with obstetrics or perinatal psychiatry.
Renal impairment rarely necessitates adjustment because of hepatic clearance, but hepatic dysfunction does require dose caution.
Safety Protocols
Contraindications (Australian Guidelines)
Before starting fluoxetine, clinicians must check for absolute contraindications and interacting therapies.
Absolute contraindications include known hypersensitivity to fluoxetine and concomitant monoamine oxidase inhibitor use because of serotonin syndrome risk.
Pimozide is another medication contraindicated with fluoxetine due to cardiac risks.
Follow TGA guidance on appropriate washout periods when switching to or from MAOIs.
Adverse Effects (Post‑Market Pharmacovigilance)
Common adverse effects include nausea, insomnia, headache, sweating and sexual dysfunction, and some people experience transient anxiety or agitation when starting treatment.
Rare but serious risks are serotonin syndrome, hyponatraemia via SIADH (especially in the elderly) and emergent suicidal ideation in younger patients, particularly within the first four weeks or after dose changes.
Pharmacists are essential contributors to AE reporting and should make use of TGA online reporting when required.
Risk Mitigation
- Perform baseline screening for suicidality, pregnancy and interacting medicines.
- Provide a written safety plan and schedule follow‑up contact within 1–4 weeks of starting or changing dose.
- Counsel on common side effects and when to seek urgent care for severe reactions such as high fever, rigidity or reduced consciousness.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
People commonly ask whether food or drink changes how fluoxetine works.
There are no major food interactions, but alcohol should be avoided or minimised because it can worsen depression and increase sedation or impairment.
Caffeine intake may worsen anxiety or insomnia when starting fluoxetine, so consider reducing coffee if new agitation occurs.
Drug Combinations To Avoid (TGA Safety Alerts)
Do not combine fluoxetine with MAOIs or linezolid because of the risk of serotonin syndrome.
Use caution when combining fluoxetine with some triptans, pimozide and other serotonergic agents.
Fluoxetine is a moderate inhibitor of CYP2D6, which can raise levels of tricyclic antidepressants, some antipsychotics and reduce conversion of tamoxifen to its active metabolite, which is clinically important for breast cancer survivors.
The long half‑life of fluoxetine and norfluoxetine extends the window for these interactions and requires appropriate washout intervals when switching therapies.
Practical Pharmacy Checks
- Reconcile all prescription and over‑the‑counter medicines and flag CYP2D6 interactions.
- Counsel patients to avoid herbal products such as St John’s Wort and to check cough medicines containing dextromethorphan.
- Document PBS authority requirements where relevant and communicate with prescribers about interaction risks.
Patient Experience Analysis
Australian Survey Data
Patients commonly wonder how others find taking fluoxetine in real life.
Surveys from Australian primary care and community pharmacy between 2020 and 2023 show patients value once‑daily dosing and perceived effectiveness.
Common complaints are initial nausea, sleep disruption and sexual side effects, while many report satisfaction once benefits appear after several weeks.
Rural respondents highlight difficulties with continuity of care but note telehealth follow‑up helps maintain adherence.
Forum And Pharmacy Trends
Online forums and pharmacist feedback indicate adherence problems are mostly linked to side effects and stigma around mental health treatment.
Community pharmacists at major chains report frequent questions about time‑to‑effect, missed doses and switching between brands such as Prozac and APO‑Fluoxetine.
Small Australian audits show pharmacist‑led education and dose‑timing advice can improve adherence and patient confidence.
Patient‑Centred Considerations
Setting realistic expectations that improvement usually takes two to six weeks and having a structured follow‑up plan, including safety checks for younger patients, improves outcomes.
Provide culturally safe care and involve Aboriginal Health Workers or translated materials for CALD communities to enhance engagement.
Distribution & Pricing Landscape
National Pharmacy Chains (Chemist Warehouse, Priceline, TerryWhite)
Patients want to know where they can reliably get fluoxetine and how much it will cost.
Generics supply of fluoxetine is robust across major Australian pharmacy chains, and PBS listing means subsidised scripts for eligible patients.
Community pharmacies commonly stock multiple generics such as APO‑Fluoxetine, Fluoxetine Sandoz and Fluoxetine APOTEX.
Private‑pay prices vary by brand choice and pharmacy, while PBS subsidy significantly reduces patient cost for eligible scripts.
Online Pharmacy Growth And Telehealth E‑Scripts
Telehealth and online e‑scripts have increased access to fluoxetine for many Australians, and accredited online pharmacies can dispense PBS‑eligible prescriptions with pharmacist counselling.
Rural mail‑order services help continuity of supply but require careful telephone or video counselling before dispatch.
In our online pharmacy, fluoxetine is available without a prescription, with discreet delivery to Australia in 5–14 days.
PBS Vs Private Cost Comparisons
PBS subsidies typically make fluoxetine a cost‑effective option compared with private prescriptions or some branded alternatives.
To illustrate how PBS processes and multi‑manufacturer supply operate, the metformin profile shows multiple formulations, global manufacturers and clear packaging guidance — a useful analogue for chronic medicine supply and PBS listing mechanics.
Alternative Options
Comparison Of PBS And Non‑PBS Options
When fluoxetine is not suitable, clinicians consider other subsidised SSRIs such as sertraline and escitalopram, which are commonly on the PBS.
Non‑PBS options may include specialised branded formulations or off‑label agents prescribed for specific needs.
Choice is driven by efficacy, side‑effect profile, drug–drug interaction potential and patient comorbidities, for example tamoxifen use often favours sertraline or escitalopram over fluoxetine.
Pros And Cons Checklist
- Pros: long half‑life reducing abrupt withdrawal risk, established paediatric data, once‑daily dosing and low cost via generics and PBS subsidy.
- Cons: stronger CYP2D6 inhibition that affects some drugs, potential for activating symptoms early in treatment and sexual adverse effects in some patients.
When To Choose Alternatives
Consider alternatives when there are significant CYP interactions, prior intolerance to fluoxetine, or a clear patient preference for a different side‑effect profile.
Decisions should integrate comorbidity management and subsidy considerations, much as prescribers choose between GLP‑1 agonists or SGLT2 inhibitors for diabetes based on comorbidity and PBS eligibility in the metformin exemplar.
Regulatory Status
TGA Approval Framework
Understandably, patients ask how medicines are approved and monitored in Australia.
Fluoxetine is registered with the Therapeutic Goods Administration for depression and selected psychiatric uses, with safety communications that track international regulators.
TGA registration requires evidence of quality, safety and efficacy, and post‑marketing surveillance through the SUSMP and other databases informs label updates.
PBS Subsidy Process
PBS listing follows a PBAC assessment of clinical effectiveness and cost‑effectiveness against existing therapies.
Fluoxetine’s generic and brand presentations achieved PBS listing, enabling subsidised dispensing, and prescribers may use PBS authority codes for paediatric or specialised indications.
Real‑Data Exemplar (Metformin)
The metformin profile and its ATC classification A10BA02 illustrate how chronic medicines are described on national formularies, with multiple manufacturers and clear dosing/contraindication information that supports supply‑chain transparency.
Fluoxetine follows an analogous pathway: TGA registration followed by PBAC/PBS decisions that shape access and pricing for Australian patients.
Consolidated FAQ
Q1: How long before fluoxetine works?
A: Many people notice some change in two to six weeks, with full benefit taking up to eight to 12 weeks in some cases.
Q2: Can I drink alcohol?
A: It is best to avoid or minimise alcohol while taking fluoxetine because it can worsen depression and increase side effects.
Q3: What about stopping suddenly?
A: Fluoxetine’s long half‑life reduces the risk of acute withdrawal, but always taper under clinical supervision to monitor mood and other symptoms.
Q4: Is fluoxetine safe in pregnancy?
A: Discuss risks and benefits with your clinician and obstetric team; specialist advice is recommended if pregnant or planning pregnancy.
Q5: Are there cheaper options?
A: PBS‑subsidised generics commonly make fluoxetine cost‑effective; pharmacists can advise on PBS eligibility and options such as APO‑Fluoxetine or Fluoxetine Sandoz.
Visual Guide
Patients and pharmacy teams benefit from clear, shareable visuals that explain treatment steps and safety measures.
Useful infographic concepts include a PBS pricing flowchart showing eligibility through to dispensing, a timeline of expected symptom change from day one to 12 weeks, and an interaction map highlighting contraindicated drugs such as MAOIs and tamoxifen.
Pharmacy display assets might include pill images of 20 mg tablets, a sticker template reading "Start Low — Review In 2 Weeks", and counselling scripts tailored to rural versus urban patients.
Data visualisation could show a comparative bar chart of SSRIs on the PBS for cost, paediatric approval and major CYP interactions — helpful for clinicians and pharmacists during medicine selection.
Designs should use accessible colour palettes, large fonts for older patients and translations for CALD communities, and a small real‑data panel using metformin packaging/ATC snippets can demonstrate how product information supports supply‑chain clarity.
Storage & Transport
Household Storage Under Australian Climate
Patients often worry about heat and whether their medicines remain effective over summer.
Store fluoxetine at room temperature, ideally between 15 and 30°C, away from moisture and heat, and keep in the original packaging with child‑resistant caps.
Do not store medicines in bathrooms where humidity is high, and keep them out of reach of children and pets.
Cold‑Chain Logistics For Pharmacies
Fluoxetine does not require cold‑chain handling and is stable under ambient transport conditions.
Pharmacies should avoid prolonged exposure to very high temperatures in delivery vans, particularly in remote areas during hot weather.
Supply Continuity Tips
Rural pharmacies should maintain buffer stock because resupply times can be longer in remote areas.
Use PBS repeats and electronic repeats to reduce interruptions for patients on long‑term therapy, and consider synchronised dispensing for chronic medicines as is commonly done with agents such as metformin to simplify patient pick‑up routines.
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
Good counselling is evidence‑based, empathetic and culturally safe.
Key points to cover at dispensing are expected time to effect, common side effects, recognition of serotonin syndrome and emergent suicidality, interaction checks including tamoxifen, and safe stopping procedures.
Document counselling in the pharmacy record and arrange a follow‑up call or review within one to two weeks to check for early adverse effects.
National Health Authority Recommendations
Follow TGA and RACGP guidance on antidepressant initiation, PBS authority rules and referral to specialists for non‑response or safety concerns.
For children and adolescents, involve paediatric mental health services where appropriate and use fluoxetine in line with approvals and the evidence base.
Practical Checklist For Prescribers & Pharmacists
- Baseline screen for suicide risk and pregnancy status.
- Start with 20 mg (or paediatric plan) and schedule review in two to four weeks.
- Reconcile medicines to flag CYP interactions and provide written information plus emergency contacts.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Gold Coast | Queensland | 5–9 days |
| Newcastle | New South Wales | 5–9 days |
| Wollongong | New South Wales | 5–9 days |
| Townsville | Queensland | 5–9 days |
| Darwin | Northern Territory | 5–9 days |
| Launceston | Tasmania | 5–9 days |
| Sunshine Coast | Queensland | 5–9 days |