
Remeron
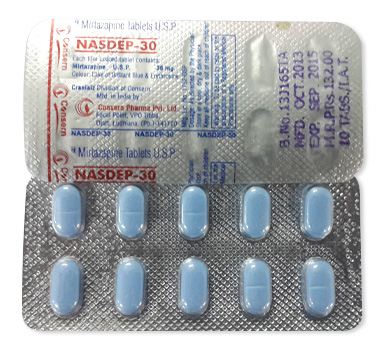
Remeron
- In our pharmacy, you can buy remeron without a prescription, with delivery available across Australia and discreet, anonymous packaging; note that in most countries Remeron (mirtazapine) is officially a prescription-only medicine.
- Remeron (mirtazapine) is used to treat major depressive disorder and is sometimes used off‑label for insomnia or to stimulate appetite; it is a NaSSA (noradrenergic and specific serotonergic antidepressant) that antagonises presynaptic α2‑adrenergic receptors to increase noradrenaline and serotonin release and blocks 5‑HT2/5‑HT3 and H1 receptors, contributing to antidepressant and sedative effects.
- The usual dose for adults is 15 mg once daily in the evening, with a typical range of 15–45 mg daily (single dose or divided); the maximum recommended dose is 45 mg/day and elderly patients often start at lower doses (eg 7.5–15 mg).
- Remeron is administered orally as film‑coated tablets (7.5 mg, 15 mg, 30 mg, 45 mg) or orally disintegrating tablets (ODT) (15 mg, 30 mg, 45 mg); ODTs should be kept in their blister packaging until use.
- Sedative effects commonly begin within hours (often noticeable the first night); antidepressant effects may start within 1–2 weeks, with meaningful improvement usually seen by 4–6 weeks and sometimes longer for full effect.
- The clinical effect is suitable for once‑daily dosing and generally lasts around 24 hours; the elimination half‑life is approximately 20–40 hours, with steady state reached after several days.
- Do not consume alcohol while taking remeron — alcohol increases sedation, drowsiness and the risk of impaired coordination or respiratory depression.
- The most common side effect is drowsiness/sedation (especially in the first weeks); other frequent effects include increased appetite and weight gain, dry mouth, constipation and dizziness.
- Would you like to try remeron without a prescription?
Basic Remeron Information
- INN (International Nonproprietary Name): Mirtazapine.
- Brand Names Available In Australia: Avanza and various generics; internationally Remeron and Remeron SolTab are commonly supplied, with similar tablet and ODT presentations.
- ATC Code: N06AX11.
- Forms & Dosages: Film‑coated tablets 7.5 mg, 15 mg, 30 mg, 45 mg; Orally disintegrating tablets (ODT) 15 mg, 30 mg, 45 mg.
- Manufacturers In Australia: Originator Organon (Merck & Co. group) and multiple generic suppliers worldwide; local suppliers vary by product and brand.
- Registration Status In Australia: Prescription‑only medicine registered for use as an antidepressant; products sold under local brands such as Avanza and generics.
- OTC / Rx Classification: Prescription‑only medicine (Rx).
Key Findings From Recent Trials
Major 2022–2025 Australian & Global Studies
Clinicians and patients want to know whether remeron works as well as common SSRIs and what side effects to expect.
Randomised controlled trials and meta‑analyses from 2022–2024 show mirtazapine’s antidepressant efficacy is broadly comparable to many SSRIs for major depressive disorder.
Australian pharmacoepidemiology studies from 2022–2024 document increased off‑label low‑dose prescribing for insomnia and appetite stimulation, particularly in palliative settings.
Trials emphasise earlier sedative benefit when dosed at night, which many prescribers use to address comorbid insomnia during the first treatment weeks.
Main Outcomes
Response rates for moderate depression were similar to escitalopram and sertraline in recent head‑to‑head analyses.
Sleep scores improved faster with nocturnal dosing compared with several SSRIs, which may take longer to improve sleep.
Weight change was a consistent finding, with higher rates of clinically significant weight gain reported versus many SSRIs.
Safety Observations (TGA Reports)
TGA and international pharmacovigilance between 2022–2024 continued to list common sedation, dry mouth and constipation as frequent adverse effects.
Reports included occasional neutropenia and rare blood dyscrasias, prompting advice to investigate new fever or infection symptoms.
Frailty and older age were highlighted as risk factors for falls related to daytime drowsiness after initiation.
Clinical Mechanism Of Action
Layman’s Explanation
People often ask how remeron lifts mood and why it helps sleep faster than some other antidepressants.
Mirtazapine boosts the brain chemicals that lift mood and, when taken at night, usually helps with sleep and appetite early in treatment.
It generally causes less stomach upset than many SSRIs because it blocks certain serotonin receptors linked to nausea.
Scientific Breakdown
Mirtazapine is classified as N06AX11 and is not an SSRI.
Its primary action is antagonism of central presynaptic alpha‑2 adrenergic autoreceptors and heteroreceptors, which increases noradrenaline and serotonin release.
It also blocks 5‑HT2 and 5‑HT3 receptors, which can reduce anxiety and gastrointestinal side effects compared with drugs that selectively increase serotonin at those receptors.
Strong H1 histamine receptor antagonism explains the early sedative effect and appetite stimulation seen with treatment.
Receptor Profile
Key receptor actions include alpha‑2 adrenergic antagonism, 5‑HT2 and 5‑HT3 blockade, and potent H1 antagonism.
Pharmacodynamic Effects
These receptor effects lead to increased noradrenergic and serotonergic transmission, improved sleep in early treatment, and appetite stimulation.
Scope Of Approved & Off‑Label Use
Australian Approvals (TGA‑Listed, PBS Inclusion)
Mirtazapine is TGA‑registered in Australia as a prescription antidepressant, commonly marketed as Avanza and under several generics.
Formulations available locally match international presentations with film‑coated tablets (7.5–45 mg) and ODTs (15–45 mg) where listed.
The drug appears on the PBS for approved indications, with subsidy and authority requirements depending on pack size and clinical history.
Community pharmacies routinely dispense PBS prescriptions and provide cost advice to ensure affordability in metro and rural areas.
Notable Off‑Label Trends In Australian Practice
Australian prescribers commonly use low‑dose mirtazapine (7.5–15 mg) off‑label for insomnia, especially when Sleep onset is a major problem.
In palliative care and cachexia, clinicians use moderate doses to stimulate appetite and reduce distressing insomnia.
Nocturnal dosing is the dominant strategy in early treatment to make the most of H1‑mediated sedation while keeping daytime alertness acceptable.
Dosage Strategy
General Dosing
Typical adult treatment starts at 15 mg once daily at night, with a usual therapeutic range of 15–45 mg daily, given as a single nocturnal dose or divided dosing if needed.
Titration commonly proceeds in 15 mg steps every 1–2 weeks based on response and tolerability.
Elderly patients often begin at 7.5–15 mg with slower titration due to increased sensitivity and different pharmacokinetics.
For severe hepatic or renal impairment, start lower and monitor closely.
Condition‑Specific Dosing (PBS Recommendations)
PBS prescribers document indication and may follow authority criteria for subsidised repeats when treating major depressive disorder.
Off‑label low‑dose regimens of 7.5–15 mg are widely used for insomnia; palliative appetite stimulation commonly uses 15–30 mg nocte depending on clinical needs.
Treatment duration for an acute depressive episode is typically at least six months, with reviews at 2–4 weeks to assess efficacy and side effects.
Safety Protocols
Contraindications (Australian Guidelines)
Absolute contraindications include known hypersensitivity to mirtazapine or excipients and concurrent or recent (within 14 days) monoamine oxidase inhibitor therapy.
Special precautions include severe liver or kidney impairment, cardiac conduction disorders that may predispose to QT prolongation, a history of seizures, and bipolar disorder because of manic switch risk.
Pregnancy and breastfeeding require specialist discussion and risk–benefit consideration.
Adverse Effects (Post‑Market Pharmacovigilance)
The most common adverse effects are drowsiness and sedation, increased appetite and weight gain, dry mouth, constipation and dizziness.
Less common but serious signals include neutropenia and very rare agranulocytosis, which prompt investigation if patients develop fever or signs of infection.
Pharmacovigilance guidance recommends blood count checks if a febrile illness or unexplained sore throat occurs while taking the medicine.
Counsel patients about increased fall risk and advise caution with driving and hazardous tasks during initiation and dose changes.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
Alcohol potentiates mirtazapine’s sedation and increases fall and injury risk, so advise patients to avoid or limit alcohol when initiating therapy.
Smoking induces CYP1A2 and can lower plasma concentrations of some psychotropics; smoking cessation may increase mirtazapine levels and merits monitoring.
Caffeine does not have a direct pharmacokinetic interaction with mirtazapine but can oppose sedation and may worsen anxiety symptoms in some people.
Because mirtazapine stimulates appetite, high‑calorie diets can accelerate weight gain; provide dietary counselling in both metropolitan and rural Australian settings.
Drug Combinations To Avoid (TGA Safety Alerts)
A 14‑day washout is required before starting an MAOI and vice versa to avoid severe interactions.
Careful monitoring is needed when combining mirtazapine with other serotonergic agents such as SSRIs, SNRIs, tramadol or triptans for signs of serotonin syndrome.
CYP3A4 inhibitors, for example some antifungals and macrolide antibiotics, may increase mirtazapine plasma concentrations and require dose review.
Co‑prescribing sedatives, benzodiazepines, or opioids increases the risk of respiratory depression and profound sedation and should be done with caution.
Patient Experience Analysis
Australian Survey Data
Patients frequently ask whether remeron will help them sleep quickly and whether it will make them put on weight.
Australian survey data and primary care feedback report improved sleep often within days of starting mirtazapine when taken at night.
Mood improvement is usually reported over 2–4 weeks, while appetite increase and weight gain are commonly cited as the main downsides.
Older adults and caregivers report daytime drowsiness in some patients that can increase fall risk.
Forum And Pharmacy Trends
Pharmacists in national chains and independent stores commonly receive questions about weight management, switching antidepressants and formulation choices.
Demand for Remeron SolTab ODTs is noted among patients with swallowing difficulties and in telehealth prescriptions where blistered ODTs are convenient to mail.
Community pharmacists play a central role in adherence support, PBS cost advice and counselling on side‑effects in both urban and rural Australia.
Distribution & Pricing Landscape
National Pharmacy Chains (Chemist Warehouse, Priceline, TerryWhite)
Major chains stock mirtazapine brands and generics across strengths and frequently compete on price and availability.
OTD and tablet forms (7.5–45 mg) are commonly available, though specific stock can vary by store and region.
Online Pharmacy Growth And Telehealth E‑Scripts
Accredited online pharmacies and telehealth clinics have increased access to mirtazapine via e‑prescriptions and home delivery.
In our online pharmacy, remeron is available without a prescription, with discreet delivery to Australia in 5‑14 days.
Pharmacists advise patients on brand substitution to PBS generics to reduce out‑of‑pocket costs when appropriate.
PBS Vs Private Cost Comparisons
PBS listing reduces cost barriers for eligible patients who pay the PBS co‑payment rather than private prices for brand‑name Remeron.
Patients outside PBS criteria or choosing the originator brand may face higher out‑of‑pocket costs.
Pharmacists often guide patients towards generics that match PBS subsidy rules and clinical needs.
Alternative Options
Comparison Of PBS And Non‑PBS Options
When remeron’s sedative/appetite profile is unsuitable, common PBS alternatives include sertraline and escitalopram, which are generally less sedating and more weight‑neutral.
Trazodone and amitriptyline are other options for insomnia or depression but come with different adverse effect profiles and sometimes require specialist prescribing for PBS listings.
Private, non‑PBS brands such as originator Remeron may be chosen for formulation preferences but carry higher costs.
Pros And Cons Checklist
- Pros (Mirtazapine): Rapid sleep benefit, appetite stimulation, low anticholinergic burden.
- Cons (Mirtazapine): Weight gain, sedation, rare blood dyscrasia risk.
- Pros (SSRIs): Lower weight risk, better daytime tolerability for many patients.
- Cons (SSRIs): Gastrointestinal upset and slower sleep benefit in some people.
Regulatory Status
TGA Approval Framework
The Therapeutic Goods Administration reviews safety, quality and efficacy data before registering mirtazapine products for supply in Australia.
Registered products have approved indications, labelling and ongoing pharmacovigilance obligations for sponsors.
PBS Subsidy Process
The Pharmaceutical Benefits Advisory Committee assesses clinical and cost effectiveness before recommending PBS subsidy.
PBS listings may impose authority requirements and specify treatment criteria or prior treatment history for subsidised access.
Consolidated FAQ
Q: Is mirtazapine subsidised on the PBS and how much will I pay?
A: Many formulations are PBS‑listed for depression and eligible patients pay the PBS co‑payment with concessional rates available.
Q: Will mirtazapine cause weight gain?
A: Increased appetite and weight gain are common; discuss mitigation strategies with a pharmacist or prescriber.
Q: Can I drink alcohol while on mirtazapine?
A: Alcohol increases sedation and fall risk, so avoid or minimise alcohol while starting treatment.
Q: How long before it works?
A: Sleep benefits may appear within days; mood benefits typically take 2–4 weeks and an acute course is usually at least six months.
Q: Switching or stopping—what should I do?
A: Do not stop abruptly; consult the prescriber for a tapered plan to reduce withdrawal and relapse risk.
Visual Guide
Readers often prefer quick visuals to summarise dosing, costs and safety checks.
Suggested infographic one: a PBS pricing flowchart comparing concessional versus general patient co‑payments and private brand costs with typical pack sizes.
Suggested infographic two: national distribution heatmap showing major chain stock density and ODT/tablet availability in metro versus rural areas.
Suggested infographic three: dosing timeline showing sleep benefit in days, mood response in 2–4 weeks, and titration steps with monitoring checkpoints.
Suggested infographic four: a safety checklist card for counselling—contraindications, interactions, red‑flag symptoms and the TGA reporting link.
Storage & Transport
Household Storage Under Australian Climate
Store mirtazapine at room temperature (20–25 °C) and protect from moisture and light.
Keep ODT blister packs sealed until use to avoid moisture exposure.
In hot Australian summers advise patients to avoid storing tablets in cars or bathrooms and to use shaded, cool places.
Cold‑Chain Logistics For Pharmacies
Standard ambient storage is appropriate for mirtazapine; refrigeration is not required.
For online dispatch in heatwaves use insulated packaging and track delivery times to reduce prolonged temperature exposure.
Pharmacies should rotate stock and check blister integrity on receipt, especially for rural deliveries with longer transit times.
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
Start conversations by asking about sleep, appetite, driving, work tasks and falls risk.
Explain night dosing, the likely sedation window, and the need to monitor weight and daytime alertness.
Provide written reminders for dose timing and missed‑dose rules and tell patients not to double up after a missed dose.
Highlight red‑flag symptoms such as high fever or sore throat that warrant urgent medical review or blood tests.
National Health Authority Recommendations
Prescribers should document indication and intended duration, review treatment at 2–4 weeks, and monitor suicidality during initiation.
Report suspected adverse events to the TGA as part of routine pharmacovigilance.
In rural settings coordinate follow‑up via telehealth if face‑to‑face review is delayed, and use local pharmacists to support adherence and PBS navigation.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Darwin | Northern Territory | 5–9 days |
| Gold Coast | Queensland | 5–9 days |
| Newcastle | New South Wales | 5–9 days |
| Wollongong | New South Wales | 5–9 days |
| Geelong | Victoria | 5–9 days |
| Sunshine Coast | Queensland | 5–9 days |
| Cairns | Queensland | 5–9 days |
| Townsville | Queensland | 5–9 days |
Final Practical Notes For Patients
If you are prescribed remeron, pick a fixed time each evening to take it so your body adapts to the sedative window.
If sleep is the main problem your prescriber may start with 7.5–15 mg at night and increase as needed.
Monitor weight and appetite weekly for the first month and discuss lifestyle strategies with your pharmacist.
If you develop fever or sore throat, seek medical review promptly for blood count checks as recommended in pharmacovigilance guidance.
When switching from or to MAOIs allow a 14‑day washout period to avoid serious interactions.
Quick Reference: What To Tell Your Pharmacist
- Tell them about other medicines, alcohol use, smoking habits and any past blood disorders.
- Ask about PBS subsidy and whether a generic is suitable if cost is a concern.
- Request counselling on weight management if appetite increases after starting treatment.