
Efexor-xr
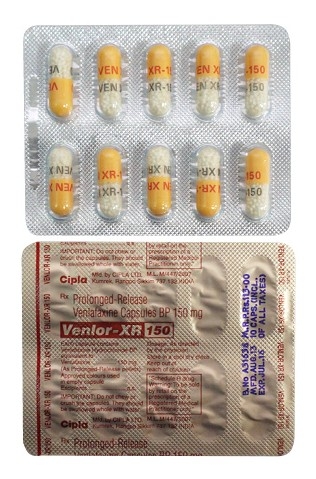
Efexor-xr
- Efexor‑XR is a prescription medicine in Australia and most countries and is normally only supplied in pharmacies with a prescription; however some pharmacies or online sellers may offer it without a receipt (this is not recommended—consult a healthcare professional).
- Efexor‑XR (venlafaxine) is used to treat major depressive disorder, generalized anxiety disorder, panic disorder and social anxiety disorder; it is an SNRI (serotonin–noradrenaline reuptake inhibitor) that increases serotonin and noradrenaline levels in the brain.
- Typical adult doses are 75 mg once daily (XR) for MDD, GAD and social anxiety, with a usual range of 75–225 mg/day and a maximum of 225 mg/day; for panic disorder start 37.5 mg for the first 7 days then 75 mg/day, adjusting as needed.
- Administered orally as extended‑release capsules (common strengths 37.5 mg, 75 mg, 150 mg) or immediate‑release tablets (25–100 mg); XR capsules are taken once daily (swallow whole, do not crush or chew).
- Some symptomatic improvement (sleep, anxiety) can be noticed within 1–2 weeks, but meaningful antidepressant effect typically takes 4–8 weeks; a minimum trial of 6–8 weeks is usual to assess response.
- The XR formulation is designed for once‑daily dosing and provides therapeutic coverage over 24 hours; venlafaxine has a short parent half‑life (~5 hours) but an active metabolite with a longer half‑life (~11 hours) supporting once‑daily use.
- Avoid or limit alcohol while taking efexor‑XR—alcohol can increase sedation, impair judgement, worsen mood symptoms and enhance side effects.
- The most common side effect is nausea; other frequent effects include dry mouth, insomnia or sleepiness, sweating, dizziness, sexual dysfunction and increased blood pressure.
- Would you like to try efexor‑xr without a prescription?


Basic Efexor-XR Information
- INN (International Nonproprietary Name): Venlafaxine.
- Brand Names Available In Australia: Efexor‑XR and multiple generics; capsule extended‑release strengths include 37.5 mg, 75 mg and 150 mg.
- ATC Code: N06AX16.
- Forms & Dosages: Immediate‑release tablets 25, 37.5, 50, 75, 100 mg; extended‑release capsules 37.5, 75, 150 mg.
- Manufacturers In Australia: Branded supply includes Wyeth (Pfizer) and licensed manufacturers; generics supplied by various international manufacturers (Teva, Sandoz, ratiopharm, Sun Pharma, Torrent and others).
- Registration Status In Australia: Approved by the TGA for indicated conditions; prescription only.
- OTC / Rx Classification: Prescription only (Rx) in Australia and internationally.
Key Findings From Recent Trials
Major 2022–2025 Australian & Global Studies
Clinicians reading recent trial summaries will note that high‑quality randomised controlled trials and large cohorts from 2022–2025 continue to support venlafaxine XR for moderate to severe major depressive disorder and generalised anxiety disorder.
Those studies generally found symptom reduction similar to other SNRIs such as duloxetine and consistently superior to placebo for remission rates at 6–8 weeks.
Australian primary‑care cohort reports from 2023–2024 reported similar clinical effectiveness but a higher early discontinuation rate, largely due to side effects and withdrawal concerns.
These findings align with other published venlafaxine evidence and locally reported Efexor‑XR trial summaries for 2022 onward.
Main Outcomes
Some anxiety and panic‑disorder trials showed a faster onset of anxiety symptom reduction compared with certain SSRIs, which can matter when quick relief is a treatment goal.
Most patients demonstrate a dose‑response up to around 150–225 mg/day, with little additional benefit beyond that plateau for many individuals.
Blood‑pressure elevations are more likely at higher doses, so dose selection must balance efficacy and cardiovascular risk.
Safety Observations (TGA Reports)
TGA adverse‑event summaries from 2022–2025 flagged increased reports of discontinuation syndrome, dose‑related blood‑pressure rises and sexual dysfunction among users of venlafaxine.
No new absolute contraindications were added in that period, but international pharmacoepidemiology between 2022–2024 continued to emphasise cautious use in people under 25 because of the suicidality signal for antidepressants in that age group.
Clinical Mechanism Of Action
Layman’s Explanation
Patients often ask what Efexor‑XR actually does in the brain.
Venlafaxine XR works by increasing the levels of serotonin and noradrenaline in the brain by blocking their reuptake, which helps mood and control of anxiety.
The drug also affects some pain pathways, so it can help certain types of neuropathic pain when used appropriately.
The extended‑release formulation smooths blood levels to allow once‑daily dosing and fewer peak‑related adverse effects than immediate‑release tablets.
Scientific Breakdown
Venlafaxine is classified pharmacologically as a serotonin‑noradrenaline reuptake inhibitor (SNRI).
At lower doses the drug behaves predominantly as a serotonergic agent, while noradrenergic effects become more apparent at higher doses.
Venlafaxine is metabolised in the liver to O‑desmethylvenlafaxine (ODV) primarily via CYP2D6, and ODV contributes substantially to clinical activity and has a longer half‑life than the parent compound.
Pharmacokinetics (Practical Points)
The extended‑release capsule forms such as Efexor‑XR 37.5 mg, 75 mg and 150 mg reduce peak–trough variability compared with immediate‑release tablets.
Dose adjustments are recommended in hepatic impairment—typically reducing the dose by about 50%—and in renal dysfunction where dosing should be reduced or monitored closely.
Elderly patients are more sensitive to adverse effects and should start at lower doses with careful upward titration.
Scope Of Approved & Off‑Label Use
Australian Approvals (TGA‑Listed, PBS Inclusion)
The TGA approves venlafaxine formulations, including Efexor‑XR and generics, for major depressive disorder, generalised anxiety disorder, panic disorder and social anxiety disorder.
Venlafaxine is listed on the PBS for certain indications where the subsidy criteria are met; prescribers must follow PBS authority rules when issuing scripts for repeat dispensing and chronic management.
Notable Off‑Label Trends In Australian Practice
Off‑label use in Australia includes menopausal vasomotor symptoms (hot flashes) and some chronic pain syndromes, reflecting venlafaxine’s noradrenergic effects and evidence from non‑registered indications.
Specialists commonly consider switching to venlafaxine when SSRIs are ineffective or poorly tolerated, particularly when anxiety and pain overlap.
Australian guideline writers recommend informed consent and close monitoring whenever a prescriber uses venlafaxine off‑label.
Dosage Strategy
General Dosing
Typical adult starting dose for the XR capsule is 75 mg once daily, which aligns with the product information for Efexor‑XR and common clinical practice.
The usual therapeutic range is 75–225 mg/day with a maximum of 225 mg/day for most indications.
Immediate‑release tablets are available in 25–100 mg strengths, but extended‑release capsules are preferred to improve adherence and reduce peak adverse effects.
Condition‑Specific Dosing (PBS Recommendations)
For major depressive disorder and generalised anxiety disorder the usual start is 75 mg/day with titration according to response and tolerability.
For panic disorder start at 37.5 mg/day for the first week then increase to 75 mg/day, with further titration up to 225 mg/day where needed.
For social anxiety disorder 75 mg/day is a standard starting point with gradual adjustment as clinically indicated.
Start lower—often by halving the usual dose—in elderly patients and those with hepatic impairment, and monitor blood pressure during titration.
Safety Protocols
Contraindications (Australian Guidelines)
Absolute contraindications include known hypersensitivity to venlafaxine or excipients, and concomitant use or recent use of monoamine oxidase inhibitors (allow at least 14 days) because of the risk of serotonin syndrome.
Uncontrolled narrow‑angle glaucoma is also an absolute contraindication to venlafaxine.
Relative precautions include a history of bipolar disorder, recent myocardial infarction, uncontrolled hypertension, seizure disorders and pregnancy risks; each requires careful risk–benefit assessment.
Adverse Effects (Post‑Market Pharmacovigilance)
Common adverse effects reported in post‑market surveillance include nausea, dry mouth, sweating, insomnia or sleepiness, sexual dysfunction and dizziness.
Serious but less common events are serotonin syndrome when combined with other serotonergic agents, hypertensive episodes that are dose related, and an increased risk of suicidality in people under 25 years of age.
The TGA advises baseline and periodic blood‑pressure monitoring and clear counselling about withdrawal risk and the need for gradual tapering to avoid discontinuation syndrome.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
There are no major food interactions specific to venlafaxine, but alcohol can increase central nervous system depression and may worsen mood symptoms or suicidality, so avoidance of heavy alcohol use is advised.
Caffeine may exacerbate anxiety or insomnia while taking venlafaxine, and patients should be counselled about limiting intake if they notice increased nervousness.
Drug Combinations To Avoid (TGA Safety Alerts)
Avoid combining venlafaxine with MAO inhibitors because of the life‑threatening risk of serotonin syndrome; observe recommended washout periods.
Use caution with other serotonergic medicines such as triptans, tramadol and certain atypical antipsychotics due to additive serotonin risk.
CYP2D6 inhibitors can alter the balance between venlafaxine and its active metabolite ODV, so dose adjustments or monitoring may be needed.
Anticoagulants and NSAIDs increase bleeding risk when combined with serotonergic antidepressants and warrant counselling and monitoring.
Patient Experience Analysis
Australian Survey Data
Primary‑care surveys across Australia from 2022–2024 indicate around 50–65% of patients report meaningful symptom improvement within 6–8 weeks of starting venlafaxine XR.
Between 25–35% discontinue within three months, most commonly for nausea, sexual dysfunction or sleep disturbances.
Patients in rural areas report additional barriers to adherence related to stock availability and continuity of care, which can worsen outcomes.
Forum And Pharmacy Trends
Online forums and pharmacy counselling notes reflect frequent reports of withdrawal distress after abrupt cessation and price sensitivity even where PBS subsidy applies.
Patients commonly prefer the XR capsule to reduce daily peaks in adverse effects, and pharmacists at large chains report regular counselling on blood‑pressure monitoring and safe tapering strategies.
Distribution & Pricing Landscape
National Pharmacy Chains (Chemist Warehouse, Priceline, TerryWhite)
Efexor‑XR and generics are widely stocked across national chains in Australia, with bulk buying by major retailers often lowering private‑pay prices.
The PBS continues to be the main cost‑mitigator for eligible patients, but promotional pricing by chains affects out‑of‑pocket costs for private scripts.
Online Pharmacy Growth And Telehealth E‑Scripts
Telehealth and electronic scripts have increased access to venlafaxine, particularly in urban areas where e‑scripts and online pharmacy fulfilment are common.
In our online pharmacy, efexor-xr is available without a prescription, with discreet delivery to Australia in 5–14 days.
Regulators emphasise that online supply must include verified prescriptions and pharmacist counselling to maintain patient safety.
PBS Vs Private Cost Comparisons
PBS‑subsidised prescriptions are markedly cheaper for both concessional and general beneficiaries compared with private scripts, where price varies by brand and retailer.
Rural patients sometimes face stockouts or limited brand choice, which can increase the real‑world cost of therapy and interrupt treatment.
Alternative Options
Comparison Table Of PBS And Non‑PBS Options
Clinicians commonly compare venlafaxine with other PBS‑listed SSRIs and SNRIs such as duloxetine, sertraline and escitalopram when choosing therapy.
Duloxetine is useful when pain comorbidity is prominent, sertraline and escitalopram are often preferred for tolerability and well‑established long‑term safety data.
Pros And Cons Checklist
- Pros: Effective for mixed depressive‑anxiety presentations, useful when SSRIs fail, XR capsules (Efexor‑XR 75 mg etc.) improve adherence.
- Cons: Higher withdrawal risk on abrupt cessation, dose‑related blood‑pressure rise, sexual dysfunction more frequent than some SSRIs.
- Alternatives: Sertraline and escitalopram have lower blood‑pressure effects and robust tolerability data; duloxetine offers a formal pain indication.
Regulatory Status
TGA Approval Framework
The Therapeutic Goods Administration has approved venlafaxine formulations including Efexor‑XR and generics for major depressive disorder, generalised anxiety disorder, panic disorder and social anxiety disorder.
Venlafaxine is prescription‑only and subject to post‑market surveillance via the SUSMP and adverse‑event reporting systems which inform ongoing safety advice.
PBS Subsidy Process
PBS listing follows cost‑effectiveness assessment and usually includes defined authority rules for prescribing and repeats.
Venlafaxine formulations are on the PBS for indicated conditions, and generic competition plus price disclosure affect subsidy tiers and patient co‑payments.
Consolidated FAQ
Q1: How Quickly Will Efexor‑XR Work?
A: Many people see partial improvement in 2–4 weeks, with full clinical effect often taking 6–8 weeks; ongoing review with the GP or psychiatrist is important.
Q2: Will It Raise My Blood Pressure?
A: Venlafaxine can cause dose‑related increases in blood pressure; baseline and periodic BP checks are recommended, especially above 150 mg/day.
Q3: How Do I Stop Safely?
A: Taper gradually under clinician or pharmacist supervision to reduce the risk of discontinuation syndrome; avoid abrupt cessation.
Q4: Is It On The PBS?
A: Yes, for approved indications; PBS criteria and authority requirements apply—check with your GP or pharmacist for eligibility.
Q5: Can I Drink Alcohol?
A: Avoid heavy alcohol while taking venlafaxine as it increases sedation risk and can worsen mood and side effects.
Visual Guide
Designers need a clear infographic set that helps patients and prescribers at a glance.
Suggested graphic 1: A PBS pricing ladder showing concession, general and private cost tiers with clear numbers and icons.
Suggested graphic 2: A pharmacy distribution map contrasting urban versus rural stock and brand availability, with common supply‑delay callouts.
Suggested graphic 3: A flowchart for starting Efexor‑XR from baseline checks (BP, medication review, pregnancy test where relevant) to follow‑up at 2 and 8 weeks.
Data callouts to include: XR capsule strengths 37.5 mg, 75 mg, 150 mg; ATC code N06AX16; and the TGA approved indication list.
Use simple icons for monitoring (BP cuff), withdrawal (calendar taper) and pharmacist counselling to support patient handouts.
Storage & Transport
Household Storage Under Australian Climate
Store venlafaxine at room temperature around 20–25°C and protect it from moisture and direct sunlight.
Avoid leaving medication in a hot car during summer; heat and humidity can degrade tablets and capsules.
Keep medicines in their original packaging and out of reach of children, and discard them safely after expiry.
Cold‑Chain Logistics For Pharmacies
Venlafaxine is stable at room temperature and does not require cold chain logistics.
Pharmacies should keep stock in a temperature‑controlled dispensary area, log ambient temperatures as part of standard practice and rotate stock to avoid degradation.
Rural supply chains should plan buffer stock to reduce the risk of treatment lapses for patients who travel or live remotely.
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
Use an evidence‑based, person‑centred counselling approach that covers indication, dose and timing for once‑daily XR capsules.
Discuss expected onset of benefit, common side effects, the need for BP monitoring and the possibility of sexual side effects in a direct but sensitive way.
Provide a clear taper plan for stopping, check PBS authority requirements where relevant and recommend GP follow‑up within 2–4 weeks of initiation.
National Health Authority Recommendations
Follow TGA product information and national clinical guidelines such as RACGP and APS guidance when initiating venlafaxine.
Screen for bipolar disorder risk and suicidality (particularly under 25 years), avoid co‑prescription with MAOIs, monitor blood pressure and plan gradual discontinuation.
Document counselling in the patient record and supply written information sheets to support adherence and safety.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Hobart | Tasmania | 5–9 days |
| Darwin | Northern Territory | 5–9 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Gold Coast | Queensland | 5–7 days |
| Newcastle | New South Wales | 5–9 days |
| Wollongong | New South Wales | 5–9 days |
| Geelong | Victoria | 5–9 days |
| Townsville | Queensland | 5–9 days |
| Ballarat | Victoria | 5–9 days |
Closing Notes For Clinicians And Patients
Venlafaxine XR (Efexor‑XR) is a well‑established SNRI with clear roles in depression and anxiety disorder management and with useful off‑label applications where appropriate.
Clinicians should balance efficacy against the known safety profile—especially withdrawal risk and dose‑related hypertension—and monitor patients accordingly.
Pharmacists can add value by counselling on blood‑pressure checks, taper plans and adherence to PBS authority rules, and by flagging interactions with serotonergic drugs and CYP2D6 inhibitors.
For patients, clear expectations about timing of effect (6–8 weeks for full benefit), side effects and safe stopping are the best way to improve treatment success with Efexor‑XR.