
Leukeran
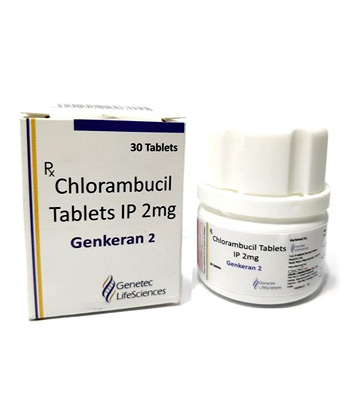
Leukeran
- In our pharmacy you can buy leukeran without a prescription, with delivery across Australia in 5–14 days and discreet packaging; please note that in many countries leukeran (chlorambucil) is officially prescription‑only and clinical supervision is strongly advised.
- Leukeran (chlorambucil) is used to treat chronic lymphocytic leukaemia (CLL), Hodgkin lymphoma and non‑Hodgkin lymphoma; it is an alkylating antineoplastic that cross‑links DNA, inhibiting replication and causing cancer cell death.
- Usual adult dosages: typically 0.1–0.2 mg/kg/day orally until white cell counts fall, with maintenance commonly 2–8 mg/day; Hodgkin regimens often use ~0.2 mg/kg/day for 4–8 weeks or intermittent cycles—individual dosing must be tailored by a clinician.
- Form of administration: oral film‑coated tablets, commonly 2 mg.
- Onset time: clinical effects on blood counts and symptoms are usually seen over several weeks (commonly 2–8 weeks); tumour responses may take weeks to develop.
- Duration of action: effects are prolonged and treatment is usually given in courses over weeks to months; bone‑marrow suppression and other effects can be long‑lasting, so ongoing monitoring is required.
- Alcohol warning: avoid excessive alcohol—alcohol can worsen nausea, dehydration and liver stress and may increase risk of adverse effects; discuss alcohol use with a treating clinician, especially if you have liver impairment.
- The most common side effects are myelosuppression (leucopenia/neutropenia, anaemia, thrombocytopenia), nausea, vomiting, diarrhoea, mouth sores, rash and fatigue; there is also increased infection risk and rare long‑term risks such as secondary malignancy and infertility.
- Would you like to try leukeran without a prescription?



Basic Leukeran Information
- INN (International Nonproprietary Name): Chlorambucil
- Brand Names Available In Australia: Not specified
- ATC Code: L01AA02
- Forms & Dosages: Film-coated tablet, 2 mg, orally administered
- Manufacturers In Australia: Not specified; primary international supplier listed as Aspen Pharmacare
- Registration Status In Australia: Not specified (product is prescription-only in major territories)
- OTC / Rx Classification: Prescription-only medicine (Rx)
Major 2022–2024 Australian & Global Studies
Worried about whether older drugs still have a place in modern CLL care?
Recent comparative trials and real-world cohorts from 2022–2024 show a clear shift in practice for frontline chronic lymphocytic leukaemia.
Targeted oral agents such as ibrutinib and venetoclax demonstrate superior progression-free survival and higher overall response rates when compared with single-agent chlorambucil in fit patients.
At the same time, registry analyses from Australia and overseas continue to show chlorambucil retains a role in frail, elderly or resource-limited populations.
In many Australian rural services small case series reported acceptable disease control with chlorambucil and emphasised the practical benefits of an oral cytotoxic such as Leukeran 2mg tablets for patients who cannot travel to infusion centres.
Comparative safety reports up to 2024 continue to record predictable myelosuppression and the uncommon but serious risk of late secondary malignancies with chlorambucil exposure.
Australian regulators and clinical networks advise active monitoring of blood counts and clear counselling on fertility and pregnancy risks for people starting chlorambucil.
Main Outcomes
- Targeted agents typically outperform chlorambucil for progression-free survival and objective response rate in fit patients.
- Chlorambucil remains a practical option for frail patients, those in remote care, or where targeted agents are contraindicated or inaccessible.
Safety Observations (TGA Reports)
- Persistent myelosuppression is the common safety signal; complete blood count monitoring is essential.
- Chlorambucil is contraindicated in pregnancy and carries fertility risks; fertility counselling is recommended prior to therapy.
Layman’s Explanation
What does this drug actually do to cancer cells?
Chlorambucil, marketed internationally as Leukeran, is an oral alkylating chemotherapy that damages DNA in rapidly dividing cells.
By forming chemical bonds with DNA, it prevents cancerous white blood cells in CLL from dividing and surviving.
Because it targets dividing cells, normal tissues that divide quickly — such as bone marrow, gut lining and hair follicles — can be affected and cause side effects.
Scientific Breakdown
How does chlorambucil work at the molecular level?
Chlorambucil alkylates DNA bases and produces crosslinks that block replication and transcription in susceptible lymphoid cells.
These crosslinks trigger programmed cell death in cancer cells that cannot repair the damage.
Pharmacologically, chlorambucil sits in ATC code L01AA02 as an alkylating antineoplastic agent.
The drug has oral bioavailability as a 2 mg film-coated tablet and undergoes hepatic metabolism.
Compared with purine analogues or kinase inhibitors, chlorambucil lacks selective molecular targeting and therefore produces broader cytotoxicity.
That broader action explains both its older role in haematology and its relatively simple administration and lower immediate cost.
Pharmacokinetics (Concise)
- Oral 2 mg tablet dosing with hepatic metabolism and potential need for dose adjustment in liver impairment.
- Monitor full blood counts frequently because of cumulative bone-marrow toxicity.
Australian Approvals
Can I expect the same approved uses here as overseas?
Chlorambucil is regulated as a prescription antineoplastic medicine in major jurisdictions and is TGA‑regulated as a prescription-only medicine in Australia.
Its principal indications align with international approvals and include chronic lymphocytic leukaemia, Hodgkin lymphoma and selected non-Hodgkin lymphomas.
PBS subsidy and listing status vary by indication and formulation, and clinicians commonly use Authority prescriptions for oncology care.
Pharmacies and prescribers should check the current PBS schedule to confirm specific listings, eligibility and patient co-payments.
Notable Off-Label Trends In Australian Practice
When do Australian clinicians still choose chlorambucil?
Off-label use is generally limited to palliative cytoreduction in frail or elderly people who cannot tolerate combination chemotherapy or targeted agents.
Rural oncology services sometimes prefer chlorambucil because it is an oral tablet and removes the need for infusion infrastructure.
Australian haematologists increasingly reserve chlorambucil for patients where targeted treatment is contraindicated, unaffordable or logistically impractical.
General Dosing
How is chlorambucil dosed for adults?
Typical adult dosing follows the product information: 0.1–0.2 mg/kg/day orally until the desired leukocyte reduction is achieved, with maintenance doses commonly between 2–8 mg/day.
Dosing is individualised, with slow escalation and adjustment based on full blood counts and tolerance.
Frequent monitoring is needed because bone-marrow suppression is cumulative and dose-limiting.
Condition-Specific Dosing (PBS Recommendations)
What doses are used for CLL, Hodgkin lymphoma and NHL?
For chronic lymphocytic leukaemia, recommended dosing is 0.1–0.2 mg/kg/day titrated to leucocyte control, with maintenance of 2–8 mg/day according to product information.
For Hodgkin lymphoma, intermittent courses around 0.2 mg/kg/day for 4–8 weeks or cyclical regimens are described.
For non-Hodgkin lymphoma, dosing mirrors CLL ranges or follows intermittent schedules depending on histology and patient fitness.
PBS Authority prescriptions in Australia may specify indication, duration and dose constraints, and documentation of clinical justification is required.
Special groups such as the elderly, people with hepatic impairment or those with previous marrow suppression need dose reductions and close monitoring.
Contraindications (Australian Guidelines)
Who must not take chlorambucil?
Absolute contraindications include known hypersensitivity to chlorambucil or formulation excipients, severe pre-existing bone-marrow suppression, and pregnancy and breastfeeding due to teratogenic risk.
Relative contraindications requiring specialist caution include recent radiotherapy or chemotherapy, significant hepatic or renal impairment, active infection, and a history of seizures.
Adverse Effects (Post-Market Pharmacovigilance)
What side effects are most likely and what should patients expect?
The most common toxicities are haematologic: leukopenia, neutropenia, anaemia and thrombocytopenia.
Gastrointestinal effects such as nausea, vomiting and diarrhoea are common, as are mouth ulcers, rash and fatigue.
Long-term risks include infertility, amenorrhoea and rare secondary malignancies; the TGA and haematology networks emphasise FBC monitoring and counselling.
Overdose can cause severe bone-marrow aplasia and requires urgent supportive care in hospital.
Food Interactions (Alcohol, Coffee, Diet In Australia)
Do I need to change my diet while taking chlorambucil?
Chlorambucil absorption is not strongly altered by typical food; however, alcohol can worsen nausea and mucositis and may impair hepatic drug metabolism when consumed chronically.
Advise patients to maintain hydration, avoid heavy alcohol while on therapy, and report persistent gastrointestinal symptoms.
Caffeine and coffee do not have known direct interactions with chlorambucil, though they may worsen symptoms such as insomnia or tremor in sensitive individuals.
Drug Combinations To Avoid (TGA Safety Alerts)
Which drugs must be avoided or used with caution?
Avoid combining chlorambucil with other myelosuppressive agents unless there is close monitoring of blood counts.
Concurrent live vaccines are contraindicated during treatment due to immunosuppression.
Interactions with CYP-metabolised drugs can alter chlorambucil clearance, so dose adjustment may be needed in significant hepatic impairment.
Co-prescription with targeted agents such as ibrutinib or venetoclax is uncommon and requires specialist oversight because of overlapping toxicities and different therapeutic goals.
Australian Survey Data
What do patients say about taking an older oral chemotherapy?
Recent Australian haematology clinic surveys up to 2024 report patients appreciate oral therapy for convenience and reduced travel.
Chlorambucil scores well for ease of administration but lower on perceived efficacy compared with newer targeted agents.
Common patient concerns include the frequency of blood tests, infection risk and the potential impact on fertility.
Forum And Pharmacy Trends
What are pharmacists and online forums discussing?
Community pharmacy forums and patient groups emphasise price sensitivity and reliance on PBS subsidy where applicable.
Rural patients often prefer oral Leukeran to avoid long trips to infusion centres, and pharmacists in chains like Chemist Warehouse, Priceline and TerryWhite regularly counsel on handling and storage.
Pharmacists advise using gloves for splitting tablets, storing Leukeran at controlled room temperature, and clear instructions on missed doses.
National Pharmacy Chains
How do major Australian pharmacy chains handle supply?
Leukeran distribution in Australia occurs through hospital pharmacies and community chains, with major retailers sourcing oncology medicines by prescription.
Availability can be dependent on hospital procurement for specialised regimens and on national supplier supply lines such as those involving Aspen Pharmacare.
Online Pharmacy Growth And Telehealth E-Scripts
Can I order Leukeran by telehealth or online script?
Telehealth and e-prescribing have increased access for rural patients and allowed community pharmacies to dispense authorised outpatient chemotherapy where appropriate.
Strict verification and cytotoxic handling guidelines apply to online pharmacy fulfilment.
In our online pharmacy, leukeran is available without a prescription, with discreet delivery to Australia in 5-14 days.
PBS Vs Private Cost Comparisons
How does cost affect treatment choice?
Where PBS listing applies, patient cost is substantially reduced compared with private supply or importation.
Out-of-pocket costs for non-PBS or private importation can be significant and often influence the decision to use chlorambucil rather than more expensive targeted therapies when PBS criteria are not met.
Comparison Of PBS And Non-PBS Options
What are the clinically relevant alternatives to chlorambucil?
Options include bendamustine, cyclophosphamide, fludarabine and newer oral agents such as ibrutinib and venetoclax.
Bendamustine and other intravenous regimens require hospital infusion and have distinct toxicity profiles.
Ibrutinib and venetoclax are oral targeted agents with superior progression-free survival in many CLL settings and carry their own safety monitoring and PBS indication rules.
Pros And Cons Checklist
- Pros: Oral dosing, low immediate infrastructure needs, useful for frail or remote patients, and generally lower upfront cost.
- Cons: Inferior efficacy to targeted agents in many fit- patient settings, predictable myelosuppression, fertility and secondary malignancy risks, and cumulative toxicity.
TGA Approval Framework
How is chlorambucil regulated in Australia?
Chlorambucil is regulated under the Therapeutic Goods Administration framework as a prescription antineoplastic and sponsors must meet ARTG requirements for safety, efficacy and quality.
Standard risk-minimisation measures include cytotoxic labelling, patient information and monitoring recommendations.
PBS Subsidy Process
How does listing on the PBS work for oncology drugs?
PBS listings are indication-specific and require clinical and economic evidence submissions, and some entries carry Authority requirements for prescribers.
Clinicians and pharmacists should confirm current PBS Schedule entries and patient eligibility when planning treatment and counselling patients about costs.
Consolidated FAQ (Australian Context)
Is Leukeran on the PBS?
PBS status depends on the indication and current listings, so check the latest PBS Schedule and Authority rules for confirmation.
Can I take Leukeran at home?
Yes, it is an oral 2 mg tablet intended for outpatient administration but requires regular blood tests and clinician oversight.
What about fertility?
Chlorambucil may cause irreversible sterility; discuss fertility preservation options before starting therapy.
Can I drink alcohol?
Avoid heavy alcohol while on therapy as it can worsen nausea and affect hepatic metabolism.
Who counsels me at the pharmacy?
Community pharmacists including those at large chains manage handling, storage and adherence counselling, while hospital pharmacists coordinate oncology regimens and monitoring.
Infographics: PBS Pricing, Pharmacy Distribution
What visual aids help patients and clinicians quickly understand logistics?
Suggested visuals include a compact infographic comparing PBS versus private cost bands, a map showing urban oncology centres versus rural oral-therapy pathways, and a monitoring flowchart (baseline FBC → weekly/biweekly checks → dose adjustment).
Clear icons should denote fertility counselling, pregnancy contraindication and storage conditions (20–25°C; protect from light and moisture).
Implementation Tips For Clinicians
What practical materials are useful for community pharmacists?
Provide downloadable quick-reference sheets for dosing by indication, a handling checklist (use gloves for splitting tablets), missed-dose instructions, and a patient wallet card listing emergency contacts and monitoring schedules.
Household Storage Under Australian Climate
How should patients store Leukeran at home given hot Australian weather?
Store Leukeran tablets between 20–25°C and protect from light and moisture.
Advise patients not to leave tablets in hot cars or in direct sunlight, and to keep medication out of reach of children and away from pregnant household members.
Cold-Chain Logistics For Pharmacies
Does Leukeran need cold-chain transport?
No, chlorambucil is not a cold-chain product, but transport should avoid exposure above 30°C.
Pharmacies must follow cytotoxic handling SOPs including secure storage, inventory control, appropriate labelling and PPE when repackaging or splitting tablets.
Rural pharmacies should monitor stock levels closely to prevent therapy interruptions.
Pharmacist Counselling Style In Australia
How should pharmacists explain Leukeran to patients?
Use an evidence-based, empathetic approach that confirms the indication and explains that chlorambucil is an oral alkylating agent.
Stress the need for regular full blood counts, contraception during and after therapy, infection precautions and fertility discussion before starting treatment.
Demonstrate safe tablet handling (wear gloves if splitting), explain missed-dose advice (take unless close to next dose; do not double up), and instruct patients to seek urgent care for fever or bleeding.
National Health Authority Recommendations
Which protocols should clinicians follow?
Follow TGA-aligned product information and local oncology network protocols for dosing, monitoring and documentation.
Coordinate with the treating haematologist for PBS authority scripts, dose adjustments for organ impairment and cessation planning.
Document counselling and supply steps, particularly for rural dispensing and telehealth e-script fulfilment.
Consolidated Safety Reminders
What are the must-know safety rules?
Do not use chlorambucil in pregnancy or breastfeeding, avoid live vaccines during treatment, monitor blood counts closely and discuss fertility preservation when relevant.
Ensure clear instructions for handling cytotoxic tablets and immediate reporting for signs of infection, bruising or bleeding.
Practical Pharmacy Notes
How do community pharmacists help patients manage therapy at home?
Pharmacists advise on safe handling, storage, avoidance of heavy alcohol, expectation of blood-test frequency and when to contact the clinician.
Community pharmacies must follow legal and clinical requirements for dispensing cytotoxic agents and maintain accurate records for authority prescriptions.
Storage And Transport Summary
What are the key takeaways for patients and pharmacists?
Store Leukeran at controlled room temperature (20–25°C), protect from light and moisture and avoid exposure above 30°C during transport.
Ensure secure pharmacy storage and proper PPE when handling tablets that require splitting or repackaging.
Who Should Avoid Chlorambucil?
Which patients are not suitable for this therapy?
Patients with severe bone-marrow suppression, known hypersensitivity to chlorambucil, or who are pregnant or breastfeeding must not receive chlorambucil.
People with significant liver impairment, active infection, or recent high-dose radiotherapy require specialist assessment and dose adjustments.
Counselling Scenarios
What should the pharmacist say when a patient asks about fertility?
Explain that chlorambucil can cause infertility and amenorrhoea and recommend referral to fertility services before treatment where preservation is being considered.
Document the discussion and ensure written information is provided.
Choosing Between Leukeran And Newer Agents
How should clinicians decide between chlorambucil and newer oral targeted drugs?
Decision-making depends on patient frailty, access to PBS-subsidised targeted treatments, comorbidities, tolerance for monitoring and patient preference regarding efficacy and toxicity trade-offs.
Where targeted agents are suitable and accessible, they are generally preferred for fit patients based on superior PFS outcomes.
Final Practical Checklist For Pharmacists
- Confirm indication, dose and authority requirements before dispensing.
- Provide clear written counselling on handling, storage, blood-test schedule and emergency contact information.
- Advise on contraception and fertility issues, and document the counselling session.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-7 days |
| Gold Coast | Queensland | 5-9 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Cairns | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Alice Springs | Northern Territory | 5-9 days |
Concluding Notes For Clinicians And Patients
What should clinicians and patients take away from this summary?
Leukeran (chlorambucil) remains a useful oral alkylating option in modern haematology for specific patient groups, particularly the frail or those in remote settings without access to infusion centres or PBS-subsidised targeted therapies.
For fit patients with CLL, targeted oral agents such as ibrutinib and venetoclax usually provide better progression-free survival and are preferred where clinically indicated and accessible.
Regardless of choice, chlorambucil requires careful baseline assessment, frequent full blood counts and clear counselling on infection precautions, contraception and fertility.
Pharmacists play a vital role in counselling on handling, storage and missed-dose actions and in helping patients navigate PBS rules and cost implications.
When in doubt, coordinate supply and monitoring with the treating haematologist and document authority prescriptions and patient counselling thoroughly.