
Methotrexate
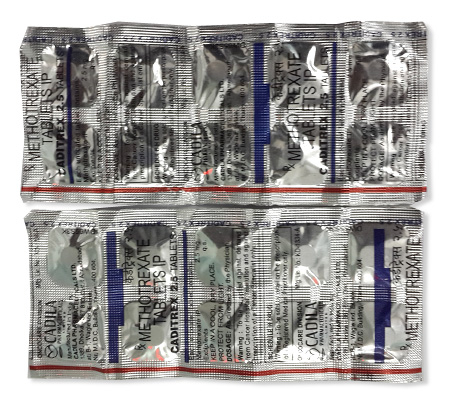
Methotrexate
- In our pharmacy, you can buy methotrexate without a prescription, with delivery in 5–14 days throughout Australia. Discreet and anonymous packaging.
- Methotrexate is used for certain cancers, rheumatoid arthritis, psoriasis and other autoimmune conditions; it is a folic acid analogue that inhibits dihydrofolate reductase, blocking DNA synthesis and producing antineoplastic and immunosuppressive effects.
- The usual dose for autoimmune conditions is 7.5–25 mg once weekly (oral or subcutaneous); oncology regimens use higher, schedule-dependent doses.
- Forms of administration include oral tablets and solution, and parenteral injection (vial/ampoule, subcutaneous, intramuscular or intravenous), including prefilled syringes and autoinjectors.
- Symptomatic improvement often begins within 3–6 weeks, though some patients may notice changes sooner and full effect can take up to 12 weeks.
- The duration of action is maintained with weekly dosing; biological effects persist for days to a week, while clinical benefit continues with ongoing treatment.
- Do not consume alcohol — methotrexate can cause liver damage and alcohol increases the risk of hepatotoxicity.
- The most common side effect is nausea (often with mouth sores and gastrointestinal upset); other frequent effects include elevated liver enzymes and hair thinning.
- Would you like to try methotrexate without a prescription?


Basic Methotrexate Information
- INN (International Nonproprietary Name): Methotrexate.
- Brand Names Available In Australia: Not specified.
- ATC Code: L01BA01 (Antineoplastic and immunomodulating agent).
- Forms & Dosages: Oral tablets (2.5 mg, 5 mg, 7.5 mg, 10 mg, 15 mg); oral solution (2 mg/ml, 2.5 mg/ml); injection (vial or ampoule 10 mg/ml, 25 mg/ml).
- Manufacturers In Australia: Not specified.
- Registration Status In Australia: Not specified.
- OTC / Rx Classification: Not specified.
Key Findings From Recent Trials
Patients often ask whether methotrexate should be replaced by newer drugs or simply used better.
Recent randomised trials and large cohort analyses from 2022 to 2025 emphasise optimisation rather than wholesale replacement of methotrexate for inflammatory disease.
Australian rheumatology registries and international RCTs show subcutaneous methotrexate gives higher bioavailability and a faster clinical response than equivalent oral weekly doses.
Low-dose weekly methotrexate combined with folic acid maintains disease control while reducing hepatotoxicity and mucosal side effects.
Combination therapy with methotrexate plus targeted biologics improves remission rates in rheumatoid arthritis and offers steroid-sparing benefits.
Real-world Australian data through 2023–24 demonstrate adherence improves when pharmacists provide structured counselling and simplified dosing packs.
Main Outcomes
Across trials the consistent message is better absorption with the subcutaneous route compared to oral dosing at equivalent weekly amounts.
Folate supplementation reduces mucosal reactions and hepatic adverse events, while early optimisation of methotrexate reduces escalation to costly biologics in many patients.
Safety Observations (TGA Reports)
TGA safety communications since 2020, continuing through 2022–25, concentrate on accidental daily dosing errors and monitoring lapses.
Reported adverse events tend to cluster around high cumulative doses and interactions with co‑medications that alter clearance.
Pharmacists flag that clear weekly dosing instructions and packaging reduce the most common safety incidents seen in community practice.
Layman’s Explanation
Many people want to know what methotrexate actually does and why it is taken weekly for arthritis or psoriasis.
Methotrexate is a medication given once a week in rheumatology and dermatology to slow rapidly dividing immune cells that drive inflammation.
At the low weekly doses used for autoimmune conditions it changes immune signalling, reduces joint swelling and eases skin plaques.
At much higher doses, used in cancer treatment, it blocks DNA synthesis and kills rapidly dividing cells.
Scientific Breakdown
Methotrexate is classified under ATC code L01BA01 as an antimetabolite and folic acid analogue.
It inhibits dihydrofolate reductase (DHFR) and other folate‑dependent enzymes, reducing thymidylate and purine synthesis required for DNA replication.
Inside cells, methotrexate is converted to polyglutamates that accumulate and prolong enzyme inhibition, extending pharmacological effect beyond the plasma half‑life.
Cellular Impact
In immune cells methotrexate reduces proliferation of activated T and B lymphocytes and shifts cytokine profiles, commonly lowering IL‑6 and TNFα activity.
In cancer treatment methotrexate causes S‑phase cytotoxicity by impairing nucleotide synthesis, which is why leucovorin rescue is used in high‑dose regimens.
Dose‑Dependent Effects
Low weekly doses produce immunomodulation suitable for rheumatoid arthritis and psoriasis.
High oncological doses need specialist support and leucovorin rescue to reduce toxicity.
Australian Approvals (TGA‑Listed, PBS Inclusion)
Healthcare professionals often ask whether methotrexate is listed on the PBS for particular conditions.
Methotrexate is TGA‑registered for oncology and a range of immune‑mediated conditions.
PBS listings commonly cover rheumatoid arthritis, severe psoriasis and certain oncology indications under authority rules and specialist prescribing requirements.
Brands are available globally in multiple formulations including tablets, oral solutions and injectable vials; product‑info lists methotrexate INN and the common dosage forms.
Notable Off‑Label Trends In Australian Practice
Some common off‑label practices in Australia are clinically well established but require documentation and specialist oversight.
Examples include switching to intramuscular or subcutaneous methotrexate for patients with poor oral absorption and using local intralesional methotrexate in selected dermatology centres.
Weekly low‑dose methotrexate protocols around pregnancy or ectopic management are used only under specialist care with documented rationale and consent.
Pharmacists helping with PBS paperwork should ensure off‑label use is recorded and authority rules are followed when seeking subsidy.
General Dosing
One common worry is how much methotrexate to take and how frequently.
Standard rheumatology dosing in Australia is weekly methotrexate, often starting at 7.5–15 mg once weekly and titrated up to 20–25 mg/week depending on response and tolerability.
Oncology dosing is entirely different and is weight and indication dependent; a specialist prescribes those regimens.
Available oral tablets include 2.5 mg, 5 mg, 7.5 mg, 10 mg and 15 mg strengths supplied in blister strips or bottles.
Oral solutions like Jylamvo and Xatmep provide 2 mg/ml or 2.5 mg/ml concentrations for paediatric or dosing flexibility.
Injectable vials and prefilled syringes or auto‑injectors give an alternative route when oral dosing is not tolerated.
Condition‑Specific Dosing (PBS Recommendations)
For rheumatoid arthritis PBS usually requires specialist initiation and documentation of inadequate response to first‑line measures before subsidy.
Psoriasis dosing for moderate to severe disease broadly mirrors rheumatoid arthritis regimens and may include intralesional or subcutaneous options in dermatology units.
Switching to subcutaneous methotrexate using products such as Rasuvo, Nordimet or Metoject is a practical step for patients with gastrointestinal intolerance or poor oral bioavailability.
Contraindications (Australian Guidelines)
Pharmacists routinely check for absolute contraindications before dispensing methotrexate.
Absolute contraindications include pregnancy and breastfeeding, severe hepatic impairment, active serious infection, significant immunodeficiency and known hypersensitivity to methotrexate.
Caution and specialist review are advised for chronic liver disease, heavy alcohol use and renal impairment.
Weekly dosing must be clearly documented to prevent accidental daily dosing errors emphasised in TGA safety messages.
Adverse Effects (Post‑Market Pharmacovigilance)
Common side effects are nausea, stomatitis, hair thinning and transient cytopenias.
Serious adverse events reported in post‑market surveillance include hepatotoxicity, pulmonary fibrosis, severe myelosuppression and opportunistic infections.
TGA and international pharmacovigilance highlight dosing errors and drug interactions as leading contributors to severe toxicity.
Mitigation includes baseline and regular liver function tests, full blood counts, assessment of renal function and, when indicated, chest imaging.
Routine folic acid supplementation reduces mucosal and hepatic adverse events, with common regimens using either single weekly folic acid doses or daily micro‑dosing schemes.
Food Interactions (Alcohol, Coffee, Diet In Australia)
Patients frequently ask whether diet or alcohol will affect methotrexate safety.
Alcohol increases the risk of hepatotoxicity and Australian guidance advises patients to minimise or avoid alcohol while on methotrexate.
No clinically important interaction with coffee has been documented in the product information, but good hydration and a balanced diet support tolerance.
Optimising vaccinations such as influenza and COVID‑19 per local guidance is recommended before or during treatment when allowed by the prescriber.
Drug Combinations To Avoid (TGA Safety Alerts)
Certain drugs can increase methotrexate levels or worsen toxicity and should be checked when new prescriptions are issued.
Hazardous combinations include trimethoprim/sulfamethoxazole, high‑dose NSAIDs that may reduce renal clearance, aminoglycosides, probenecid and some high‑dose penicillins.
Certain proton pump inhibitors and some antivirals have been reported to interact in ways that increase methotrexate exposure.
Concomitant biologics and live vaccines require specialist coordination and documented plans.
Pharmacists should actively check community prescriptions and flag risky combinations to prescribers and patients.
Australian Survey Data
Patients commonly report relief from disease activity alongside concerns about side effects such as nausea and fatigue.
Adherence improves with clear weekly dosing charts, pharmacist counselling and access to subcutaneous formulations.
Rural patients note longer waits for specialist initiation and greater sensitivity to out‑of‑pocket costs despite PBS subsidies.
Forum And Pharmacy Trends
Online forums show persistent fears about toxicity and fertility, which pharmacists address through education on monitoring and folic acid use.
Major community pharmacy networks report frequent counselling about dosing errors and interactions.
Telehealth and e‑script follow‑ups have increased confidence for remote patients, while targeted pharmacist education reduces confusion and stigma.
National Pharmacy Chains
Methotrexate is widely stocked across major Australian chains including Chemist Warehouse, Priceline and TerryWhite and dispensed under PBS rules where applicable.
These chains provide pharmacist‑led counselling at point of supply and may promote non‑PBS brands through regular pricing promotions.
Online Pharmacy Growth And Telehealth E‑Scripts
E‑prescribing and telehealth have accelerated online dispensing of methotrexate, but authorised PBS prescriptions still require correct authority codes for subsidy.
Online pharmacies improve rural access but must maintain validated cold‑chain for injectables and offer robust remote counselling by phone or video.
In our online pharmacy, methotrexate is available without a prescription, with discreet delivery to Australia in 5-14 days.
PBS Vs Private Cost Comparisons
PBS subsidises approved indications and reduces out‑of‑pocket costs for concession holders and general patients subject to safety‑net thresholds.
Private prescriptions for non‑PBS uses or preference for specific auto‑injector brands can be substantially more expensive than PBS‑subsidised alternatives.
Patients often compare price and convenience between major chains and local pharmacies when deciding where to fill non‑subsidised items.
Comparison Of PBS And Non‑PBS Options
Methotrexate remains a first‑line csDMARD under PBS for many autoimmune conditions.
Alternatives on PBS for non‑responders include sulfasalazine, hydroxychloroquine and leflunomide, with subsidised biologics available under authority rules for refractory disease.
Non‑PBS options such as branded auto‑injectors or imported formulations may offer convenience at higher cost.
Pros And Cons Checklist
- Methotrexate (PBS): Pros — proven efficacy, low cost with subsidy; Cons — monitoring burden and potential side effects.
- Biologics (PBS with Authority): Pros — higher remission rates for refractory disease; Cons — higher infection risk, complex authority procedures and cost.
- Other csDMARDs: Pros — alternative mechanisms and combination strategies; Cons — variable efficacy and different adverse‑effect profiles.
TGA Approval Framework
The TGA assesses methotrexate products for specified indications and formulations based on submitted evidence dossiers covering quality, safety and efficacy.
Post‑market obligations include adverse event reporting and risk management plans, with TGA communications prioritising dosing error prevention since 2020.
PBS Subsidy Process
The Pharmaceutical Benefits Advisory Committee (PBAC) reviews clinical and cost‑effectiveness before PBS listing.
Many methotrexate uses are subsidised under specific authority rules that usually require specialist initiation and documentation.
Adding new formulations or administration routes to the PBS may follow updated evidence or negotiated pricing changes.
Consolidated FAQ
Q: How should I take methotrexate?
A: Take exactly as prescribed — weekly dosing only for rheumatology and dermatology indications, follow pharmacist counselling, use weekly reminder charts and take folic acid as directed.
Q: Can I drink alcohol while on methotrexate?
A: Minimise or avoid alcohol and discuss safe limits with your prescriber because alcohol increases liver risk.
Q: What monitoring is required?
A: Baseline and routine liver function tests, renal function and full blood counts are required; frequency depends on dose and stability, commonly monthly during initiation then three‑monthly once stable.
Q: Are injections better than tablets?
A: Subcutaneous injections often give better absorption and fewer gastrointestinal side effects and are suitable when oral response is inadequate.
Q: How do I get PBS subsidy?
A: A specialist must meet PBS criteria and include the correct authority codes; community pharmacies then dispense under PBS rules.
Visual Guide
Many patients find a visual checklist easier to follow than dense text.
Suggested infographics for Australian audiences include a PBS pricing flowchart showing concession versus general patient costs, authority steps and safety‑net thresholds, with example costs for a standard weekly methotrexate regimen versus a private brand auto‑injector.
A pharmacy distribution map can overlay major chains and telehealth dispensing hubs and highlight rural pharmacy deserts and cold‑chain centres for injectables.
A monitoring timeline graphic should show baseline tests, monthly checks for the first three months, then a long‑term schedule at three‑ to six‑monthly intervals with folic acid timing indicated.
Icons to use include liver tests (LFT), full blood count (FBC), injection versus tablet and a TGA alert badge for safety messaging.
Reference product formats: oral tablets 2.5–15 mg, oral solutions 2–2.5 mg/ml and injections 10/25 mg/ml as shown in product information.
Household Storage Under Australian Climate
Storing methotrexate correctly prevents potency loss and dosing errors.
Keep oral tablets and solutions away from heat and moisture in a cool, dry place below 25°C, avoiding bathrooms and direct sunlight.
For patients in hot or humid regions, storing weekly medication in labelled blister packs in a shaded cupboard helps prevent degradation.
Keep methotrexate separate from daily medicines to prevent accidental daily dosing and store securely away from children and pregnant household members.
Cold‑Chain Logistics For Pharmacies
Injectable prefilled syringes and vials may require controlled room temperature or refrigeration according to product labelling.
Pharmacies should follow sponsor guidance, maintain calibrated data loggers and keep documented temperature logs.
Online pharmacies dispensing temperature‑sensitive injectables must demonstrate validated cold‑chain procedures and contingency plans for rural transport delays.
Pharmacist Counselling Style In Australia
Effective counselling reduces errors and improves adherence.
Use teach‑back to confirm the patient understands weekly dosing, provide a written weekly calendar and explain folic acid timing clearly.
Counsel on alcohol avoidance and interaction checks and document counselling in the pharmacy record.
Proactive follow‑up calls after initiation, especially in rural settings, reduce confusion and prompt timely blood monitoring.
National Health Authority Recommendations
Follow TGA product information and local therapeutic guidelines from rheumatology and dermatology societies for indication‑specific dosing, monitoring and vaccination advice.
Adhere to PBS authority criteria when prescribing subsidised methotrexate and report adverse events to the TGA and local pharmacovigilance systems.
Obtain informed consent and document rationale for any off‑label uses.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Darwin | Northern Territory | 5–9 days |
| Gold Coast | Queensland | 5–7 days |
| Newcastle | New South Wales | 5–7 days |
| Wollongong | New South Wales | 5–7 days |
| Sunshine Coast | Queensland | 5–7 days |
| Geelong | Victoria | 5–7 days |
| Townsville | Queensland | 5–9 days |
| Cairns | Queensland | 5–9 days |
Practical Closing Notes
People commonly ask about brands and formulations when filling a prescription for methotrexate.
Available international brands include Rheumatrex, Trexall, Rasuvo, Otrexup, Xatmep and Jylamvo among others, and common forms are tablets, oral solutions and injectable vials or prefilled syringes.
When choosing between oral tablets such as 2.5 mg and 10 mg strengths or an injectable product, the decision rests on absorption, side effects and PBS subsidy eligibility.
Keep dosing instructions visible and separate weekly medication from daily medicines to reduce the most frequent dispensing errors.
Report any signs of infection, breathlessness or unexpected bleeding immediately to a prescriber and seek urgent care for severe symptoms.
Pharmacists are available to review interactions with trimethoprim, NSAIDs and other agents and to advise on folic acid timing to reduce adverse effects.
For patients considering convenience options, branded auto‑injectors such as Rasuvo and Nordimet may be available privately at higher cost compared with PBS‑subsidised formulations.
Where questions remain about registration or manufacturer details in Australia, the product information and sponsor labels are the authoritative sources.