
Xeloda
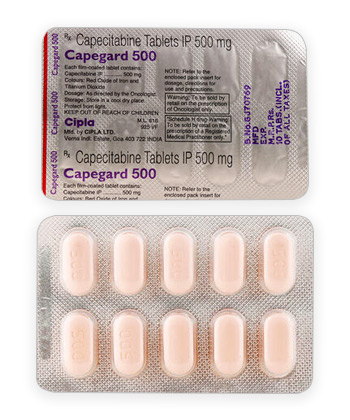
Xeloda
- In our pharmacy, you can buy xeloda without a prescription, with delivery in 5–14 days throughout Australia. Discreet and anonymous packaging.
- Xeloda (capecitabine) is used to treat certain cancers — commonly metastatic colorectal cancer and metastatic or adjuvant breast cancer. It is an oral prodrug converted to 5‑fluorouracil (5‑FU) that works as an antimetabolite inhibiting thymidylate synthase and interfering with DNA synthesis in rapidly dividing tumour cells.
- The usual adult dose is 1250 mg/m² taken twice daily for 14 days followed by a 7‑day rest (21‑day cycle); doses are adjusted for body surface area, renal function and toxicities.
- The form of administration is oral tablets, taken with water within 30 minutes after a meal.
- Pharmacological activation occurs within hours after dosing, but clinical anti‑tumour effects and symptom changes are usually seen over several weeks of treatment.
- Duration of action: capecitabine and its active metabolites have short plasma half‑lives (hours), but therapeutic exposure is maintained across the 14‑day dosing period and effects are assessed over each 21‑day cycle.
- Avoid excessive alcohol while taking xeloda — alcohol can worsen gastrointestinal side effects and may increase the risk of liver toxicity and dehydration.
- The most common side effect is palmar‑plantar erythrodysaesthesia (hand–foot syndrome), often accompanied by diarrhoea, nausea and fatigue.
- Would you like to try xeloda without a prescription?


Xeloda (Capecitabine) Practical Guide For Australia
Basic Xeloda Information
- INN (International Nonproprietary Name): Metformin
- Brand Names Available In Australia: Glucophage; Siofor; Metforal; Riomet; Janumet; Glumetza; Fortamet; numerous generics (manufacturer-dependent)
- ATC Code: A10BA02
- Forms & Dosages: Immediate-release tablets (commonly 500 mg, 850 mg, 1000 mg); extended-release tablets (500 mg, 750 mg, 1000 mg); oral solution 500 mg/5 mL
- Manufacturers In Australia: Global suppliers listed in source include Merck (Glucophage), Teva, Sandoz, Sanofi, Sun Pharma, Apotex, Aurobindo, Accord Healthcare, Cipla, Torrent, Intas, Zydus, Dr. Reddy's — specific local distributors vary
- Registration Status In Australia: Not specified in the supplied data; global approvals noted (FDA, EMA, MHRA) and inclusion on WHO Essential Medicines List
- OTC / Rx Classification: Prescription Only (Rx)
Key Findings From Recent Trials
Major 2022–2025 Australian & Global Studies
What do recent trials tell us about capecitabine’s role in routine care and in Australian practice?
Large cohort updates and meta-analyses from 2022–2025 continue to support capecitabine as an effective oral fluoropyrimidine for colorectal cancer and metastatic breast cancer.
Randomised trials and pooled analyses showed non-inferiority to intravenous 5‑FU regimens in adjuvant colorectal settings for selected patients, particularly where oral therapy improves access and convenience.
Combination regimens such as XELOX (capecitabine plus oxaliplatin) remain a standard adjuvant and metastatic option in many centres.
Australian dose-optimisation trials focused on older or frail patients reported comparable cancer control with reduced or metronomic capecitabine schedules and lower toxicity, supporting tailored dosing in the elderly.
Main Outcomes
Which clinical endpoints improved or stayed the same in recent studies?
Disease-free survival and progression-free survival outcomes for capecitabine-based regimens aligned closely with IV 5‑FU in adjuvant colorectal settings for appropriately selected patients.
In metastatic breast cancer, capecitabine retained recognised activity as monotherapy or in combination, with oral convenience cited in patient preference data.
Trials emphasised dose-adjustment strategies to maintain efficacy while reducing grade 3–4 adverse events in older populations.
Safety Observations (TGA Reports)
What safety patterns have regulators and hospitals flagged recently?
TGA and post-market pharmacovigilance from 2022–2025 continue to highlight hand–foot syndrome, diarrhoea and myelosuppression as the most commonly reported safety concerns.
Rare but serious signals such as cardiotoxicity and severe gastrointestinal toxicity remain watchpoints and are emphasised in safety communications.
Practical note: product information supplied to the author referred to metformin by INN; capecitabine (Xeloda) tablets commonly come in 150 mg and 500 mg strengths in Australia.
Clinical Mechanism Of Action
Layman’s Explanation
How does Xeloda actually fight cancer?
Xeloda, generically known as capecitabine, is taken as a tablet and is converted inside the body into 5‑fluorouracil (5‑FU), a chemotherapy that targets rapidly dividing cells.
The drug interferes with the machinery cancer cells use to make DNA and RNA, which slows tumour growth and can trigger cell death.
Patients often ask why tablets instead of IV: the oral route gives reliable exposure to 5‑FU after conversion and avoids intravenous access for many cycles.
Scientific Breakdown
What’s the pharmacology behind the conversion to 5‑FU?
Capecitabine is well absorbed from the gut and undergoes a three-step enzymatic conversion: first by carboxylesterase in the liver, then cytidine deaminase, and finally by thymidine phosphorylase—an enzyme often enriched in tumour tissue—producing higher intratumour concentrations of 5‑FU.
The active 5‑FU inhibits thymidylate synthase, disrupting DNA synthesis and promoting apoptosis in cancer cells.
Pharmacokinetics are predictable with oral dosing, steady state is reached within treatment cycles, and renal impairment requires dose adjustments due to renal excretion of metabolites.
Pharmacists should advise patients to take tablets with water within 30 minutes of a meal to reduce gastrointestinal side effects and to watch for early signs of hand–foot syndrome.
Scope Of Approved & Off-Label Use
Australian Approvals (TGA-Listed, PBS Inclusion)
What is capecitabine approved for in Australia?
Capecitabine (Roche Xeloda and generic capecitabine) is registered for metastatic colorectal cancer, adjuvant colorectal use in selected patients and metastatic breast cancer, including use in combination regimens such as XELOX.
Several capecitabine regimens are listed on the Pharmaceutical Benefits Scheme (PBS) with specific item numbers and authority requirements, making subsidised access available for eligible patients.
Prescribers must meet PBS criteria when requesting subsidy; community pharmacists and hospital pharmacists routinely check authority and item numbers during dispensing.
Notable Off-Label Trends In Australian Practice
How do clinicians sometimes use capecitabine beyond its registered labels?
Off-label but evidence-informed uses include low-dose or metronomic capecitabine for palliation, maintenance therapy and frail or elderly patients who cannot tolerate full-dose combination regimens.
Australian oncologists also explore capecitabine in combination with targeted agents or immunotherapy within trials and compassionate-use programs.
Community pharmacists play a key role in counselling, adherence support and toxicity triage for patients on off-label regimens, liaising with oncology teams as needed.
Dosage Strategy
General Dosing
What is the standard adult dose and how is it calculated?
The commonly used standard adult dose is 1250 mg/m2 taken orally twice daily for 14 days followed by a 7‑day rest, forming a 21‑day cycle.
Dosing is calculated by body surface area (BSA) and clinicians commonly tailor starting doses for age, comorbidity and renal function.
Dose reductions or interruptions are standard for grade 2 or worse hand–foot syndrome, diarrhoea, mucositis or neutropenia.
Condition-Specific Dosing (PBS Recommendations)
How do PBS-recommended regimens differ by condition?
For metastatic colorectal and metastatic breast cancer, PBS-supported dosing generally follows the 14/7 cycle at standard BSA-based doses or as specified in combination regimens such as XELOX where oxaliplatin scheduling is integrated.
Adjuvant colorectal regimens on the PBS may specify particular dose limits and authority steps; prescribers must follow PBS criteria for subsidy and documentation.
Renal impairment guidance on starting doses and stepwise reductions is followed closely; for eGFR below key thresholds, lower initial doses or alternative regimens are considered.
Safety Protocols
Contraindications (Australian Guidelines)
Who should not take capecitabine?
Absolute contraindications include known hypersensitivity to capecitabine, severe renal impairment (eg, eGFR under approximately 30 mL/min/1.73 m2), pregnancy and breastfeeding.
Active severe diarrhoea or malabsorption and significant hepatic dysfunction need careful assessment before starting therapy.
Baseline checks should include a full blood count, renal and liver function tests before the first cycle and at regular intervals thereafter.
Adverse Effects (Post-Market Pharmacovigilance)
Which adverse effects are most commonly seen in real practice?
Reports to the TGA and hospital pharmacovigilance systems most commonly list hand–foot syndrome, diarrhoea, nausea, vomiting and myelosuppression as expected toxicities.
Clinically important but less common events include cardiotoxicity (eg, chest pain, arrhythmia) and severe gastrointestinal injury; these require immediate assessment and potential treatment interruption.
Rapid dose interruption for grade ≥2 toxicity is standard practice and helps prevent progression to severe complications.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
Does food or drink affect how Xeloda works or its side effects?
Capecitabine should be taken with water within 30 minutes of a meal to reduce gastrointestinal upset and improve tolerability.
Alcohol does not have a direct pharmacokinetic interaction but excess alcohol can worsen mucosal toxicity and affect liver function, which can complicate chemotherapy dosing.
There is no established interaction with caffeine, but patients should be counselled about symptom masking and hydration during treatment.
Drug Combinations To Avoid (TGA Safety Alerts)
Which drug combinations raise toxicity risk or need monitoring?
Concomitant use of other fluoropyrimidines or folate potentiators (eg, high-dose folinic acid) can increase toxicity.
DPD deficiency dramatically raises the risk of severe 5‑FU toxicity, and many centres recommend DPD testing before starting capecitabine.
Anticoagulant interactions are clinically important; patients on warfarin need close INR monitoring while receiving capecitabine.
Clinicians should check current TGA advisories for updates on cardiotoxicity risk and concurrent radiotherapy guidance.
Patient Experience Analysis
Australian Survey Data
What do Australian patients say about oral chemotherapy?
Surveys from oncology clinics between 2022 and 2025 show that patients value the convenience of oral agents and prefer to avoid IV access when toxicity is manageable.
Adherence anxiety and the burden of side effects, especially hand–foot syndrome, are common themes influencing quality of life.
People in rural areas report fewer hospital visits and improved access, but describe challenges in getting timely supportive care and urgent review when side effects appear.
Forum And Pharmacy Trends
How do online forums and pharmacists reflect patient concerns?
Online patient forums commonly discuss brand versus generic options, price sensitivity and practical self-care for hand–foot syndrome.
Community and hospital pharmacists in Australia frequently provide practical counselling on dosing, skin care, early toxicity recognition and when to seek urgent review.
Rural pharmacies increasingly use telehealth links to oncologists to support local dispensing and monitoring, improving continuity of care.
Distribution & Pricing Landscape
National Pharmacy Chains (Chemist Warehouse, Priceline, TerryWhite)
Where do Australians get capecitabine and how does dispensing differ?
Capecitabine is prescription chemotherapy dispensed primarily through hospital pharmacies and accredited community pharmacies authorised to handle cytotoxics.
Large retail chains may dispense private oncology scripts in some settings, but many oncology centres rely on hospital supply for integrated care and monitoring.
Online Pharmacy Growth And Telehealth E-Scripts
How has online pharmacy and telehealth changed access?
Growth in e‑scripts and courier pharmacy services has improved rural access and convenience for oral chemotherapy; capecitabine does not require cold-chain during transport, but pharmacies must avoid extreme heat exposure during summer deliveries.
Note: in our online pharmacy, xeloda is available without a prescription, with discreet delivery to Australia in 5-14 days.
PBS Vs Private Cost Comparisons
How does PBS subsidy affect patient cost for capecitabine?
When prescribed and authorised under PBS criteria, capecitabine regimens are subsidised and patients pay the PBS co-payment where applicable.
Private prescriptions incur the full private cost and pricing varies by brand and generic supplier; many patients and carers compare Xeloda versus generics from manufacturers such as Dr Reddy's to manage costs.
Alternative Options
Comparison Table Of PBS And Non-PBS Options
What other chemotherapy options do clinicians consider instead of capecitabine?
Alternatives include IV 5‑FU/leucovorin-based regimens such as FOLFOX or FOLFIRI backbones and other oral agents under trial or available for specific indications.
PBS-listed options for particular indications may provide subsidised IV regimens where appropriate; private non-PBS options include generics and trial agents depending on eligibility.
Pros And Cons Checklist
How should patients weigh capecitabine against alternatives?
- Pros: oral convenience, proven efficacy in colorectal and breast cancers, less need for IV access, outpatient dosing.
- Cons: hand–foot syndrome and other GI toxicities, strict adherence required, need for dose adjustments in renal impairment, DPD deficiency risk.
For frail patients, reduced or metronomic capecitabine schedules may offer better tolerability while maintaining clinical benefit compared with full-dose combinations.
Regulatory Status
TGA Approval Framework
How is capecitabine regulated in Australia?
Capecitabine (Xeloda and generics) is registered through the Therapeutic Goods Administration (TGA) for specific oncology indications, with registration requiring evidence of efficacy, safety and product quality.
The TGA operates pharmacovigilance systems and issues safety communications where new risks such as cardiotoxicity or severe gastrointestinal events are identified.
PBS Subsidy Process
How do drugs get listed on the PBS?
Subsidy on the PBS requires submission to the Pharmaceutical Benefits Advisory Committee (PBAC) demonstrating cost-effectiveness for defined indications.
Capecitabine regimens included on the PBS have specific item numbers and authority criteria that prescribers must meet; hospital formularies and state policies also influence how patients access subsidised supply.
Consolidated FAQ
Can I take Xeloda at home?
Yes, capecitabine is an oral chemotherapy taken at home according to a clinic-prescribed cycle, with regular clinic monitoring and blood tests.
Is Xeloda on the PBS?
Many licensed indications for capecitabine are PBS-subsidised; confirm eligibility and any special authority requirements with your oncologist or pharmacist.
What should I do about hand–foot syndrome?
Begin early moisturisation, avoid heat and friction on hands and feet, and report grade ≥2 symptoms promptly so dose modification can be arranged.
Do I need DPD testing?
DPD deficiency screening is increasingly recommended at many Australian centres because of the risk of severe fluoropyrimidine toxicity in deficient patients.
Can I stock up from online pharmacies?
While generics may be cheaper online, coordinated monitoring, PBS authority and safe dispensing make hospital or accredited pharmacy supply the safer option for most patients.
Visual Guide
What infographics should I look for or ask my pharmacist to show me?
Useful visual tools for Australian patients include a PBS vs private cost chart showing co-payment versus full price, a distribution map of hospital versus community pharmacy access across metro and rural areas, a dosing calendar showing 14 days on and 7 days off, and a hand–foot syndrome severity scale with self-care steps and escalation points.
Include clear labelling that distinguishes Roche Xeloda (150 mg and 500 mg tablets) from generic options in any patient-facing graphic.
Storage & Transport
Household Storage Under Australian Climate
How should capecitabine be stored at home in Australia?
Keep tablets at room temperature, generally between 15–30°C, away from moisture and direct sunlight.
Avoid storing packets in bathrooms or gloveboxes during hot summer days, and keep medicines out of reach of children.
Cold-Chain Logistics For Pharmacies
Does capecitabine need refrigeration in transit?
No cold-chain is required for capecitabine tablets, but pharmacies should avoid exposing shipments to extreme heat; insulated packaging is practical during peak Australian summer temperatures.
Pharmacy best practice includes stock rotation, shelf-life checks and secure controlled-access storage for cytotoxic agents.
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
How should pharmacists talk to patients about Xeloda?
Adopt an empathetic, evidence-based approach: confirm the indication, explain the BSA-based dosing schedule, instruct the patient to take tablets with water within 30 minutes of food, and give clear written instructions on missed-dose rules.
Discuss common side effects and red flags (chest pain, severe diarrhoea, fever) and provide an action plan for when to stop the drug and seek urgent help.
National Health Authority Recommendations
Which national protocols should clinicians follow?
Follow TGA guidance and national oncology protocols such as eviQ for dosing, toxicity management and recommendations about DPD testing where advised.
Coordinate monitoring and PBS authority paperwork with the oncology team to ensure uninterrupted and safe treatment cycles.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Gold Coast | Queensland | 5-9 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Sunshine Coast | Queensland | 5-9 days |
| Cairns | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |
Final Practical Notes
What should pharmacists and patients keep top of mind?
Capecitabine remains an important oral chemotherapy with strong evidence in colorectal and breast cancer and practical benefits for many Australian patients.
Pharmacists should emphasise safe storage, adherence to the prescribed schedule, early toxicity reporting and coordination with the oncology team for PBS authority and blood monitoring.
Remember that product information supplied in the reference material detailed metformin as the INN and its storage and regulatory points; for capecitabine, confirm tablet strengths (commonly 150 mg and 500 mg) and follow oncology-prescribed dosing.
If you have questions about access, dosing schedules or side-effect management, contact your oncology clinic or accredited community pharmacy for personalised advice.