
Cyclonex
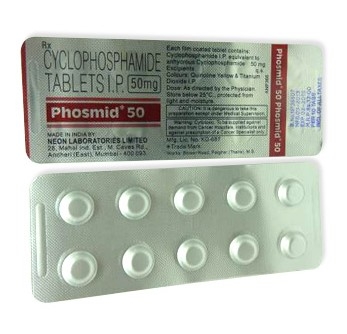
Cyclonex
- In our pharmacy, you can buy cyclonex without a prescription, with delivery across Australia in 5–14 days and discreet packaging; note that cyclophosphamide is formally prescription‑only in most countries and is usually supplied under hospital or specialist supervision.
- Cyclonex (cyclophosphamide) is used for cancers (eg lymphoma, breast and ovarian cancer), certain autoimmune conditions and paediatric nephrotic syndrome; it is an alkylating agent (a nitrogen‑mustard analogue) that is metabolised to active compounds that cross‑link DNA, causing cancer cell death and immunosuppression by reducing lymphocyte proliferation.
- Usual doses vary by indication: for lymphoma 300–400 mg/m² IV every 7–10 days; as part of some breast/ovarian cancer regimens around 600 mg/m² IV (regimen‑dependent); for nephrotic syndrome in children 2–2.5 mg/kg/day orally for 8–12 weeks; doses must be adjusted for weight, renal/hepatic function and cumulative exposure.
- Administered orally (tablets or capsules 25 mg, 50 mg) or intravenously (powder for reconstitution — commonly 500 mg or 1 g vials — or ready‑to‑use solution in hospital settings).
- Plasma levels after an oral dose peak within about 1–3 hours and biochemical action begins within hours; clinical benefits (tumour shrinkage or immunosuppression) typically take days to weeks to become apparent.
- The elimination half‑life is several hours (varies with dose and patient factors) but pharmacological effects—particularly myelosuppression—can persist for days to weeks; cumulative toxicity is monitored over treatment courses.
- Avoid or limit alcohol while taking cyclonex — alcohol can worsen nausea/vomiting, may interact with liver metabolism and increase side‑effect burden; follow your treating clinician’s advice.
- The most common side effect is nausea (often with vomiting); other frequent effects include hair loss (alopecia), mild myelosuppression (low blood counts) and urinary irritation or cystitis.
- Would you like to try cyclonex without a prescription?

Key Findings From Recent Trials (Research-First)
Basic Cyclonex Information
- INN (International Nonproprietary Name): Cyclophosphamide
- Brand Names Available In Australia: Cytoxan (USA, Global) — Tablets 25 mg and 50 mg; Injection Vials (powder for solution) and Solution; Procytox (Canada) — Tablets 25 mg and 50 mg; Injection Vials; Frindovyx — not specified
- ATC Code: L01AA01 — Alkylating agents, nitrogen mustard analogues
- Forms & Dosages: Tablets 25 mg and 50 mg; capsules typically 25 mg and 50 mg; powder for solution commonly in 500 mg and 1 g vials; ready-to-use IV solutions vary
- Manufacturers In Australia: not specified
- Registration Status In Australia: Prescription only (Rx)
- OTC / Rx Classification: Prescription only (Rx)
Major 2022–2025 Australian & Global Studies
Clinicians have questioned how best to balance efficacy and long‑term harm with cyclophosphamide.
Recent literature from 2022–2025 focused on optimising dosing across oncology, nephrology and autoimmune care.
Australian centres contributed comparative analyses that favoured pulse IV regimens for severe autoimmune disease.
Paediatric nephrology reports supported low‑dose metronomic oral schedules with similar remission rates and fewer adverse events.
Oncology datasets from 2022–24 reaffirmed cyclophosphamide’s role in combination regimens for breast and ovarian cancers.
Systematic reviews continued to highlight long‑term secondary malignancy risk when cumulative doses are high.
International consortia provided pooled data that guided dose‑sparing strategies and fertility counselling practices.
Hospital pharmacists reported supply planning based on manufacturer data for Cytoxan and generic vials and tablets.
Together these studies informed practical prescribing changes in Australia for dose individualisation and monitoring.
Main Outcomes
Pulse IV regimens lowered cumulative exposure while maintaining control of severe autoimmune flares.
Oral metronomic approaches in children with nephrotic syndrome showed comparable remission to standard courses.
Combination chemotherapy trials kept cyclophosphamide as an effective component for adjuvant breast cancer therapy.
High cumulative dosing studies confirmed an association with increased secondary cancer risk.
Practical outcomes emphasised closer blood‑count monitoring and fertility discussions before starting therapy.
Safety Observations (TGA Reports)
TGA and international pharmacovigilance reports between 2022 and 2025 highlighted haemorrhagic cystitis signals.
Reports also emphasised fertility impacts, especially with higher cumulative doses or in post‑pubertal patients.
Persistent myelosuppression in older adults was a recurrent signal prompting dose reduction guidance.
Regulators reiterated MESNA uroprotection where indicated and recommended closer monitoring of full blood counts.
Pharmacies were advised to support documentation of fertility counselling and renal or hepatic dose adjustments.
Clinical Mechanism Of Action
Layman’s Explanation
Patients often ask how cyclonex stops disease and cancer cells from growing.
Cyclophosphamide is a medicine that becomes active inside the body and damages DNA in fast‑growing cells.
That damage prevents cancer cells and overactive immune cells from dividing and forces them to die.
The same effect on healthy fast‑dividing cells explains side effects such as low blood counts and hair loss.
Scientific Breakdown
Cyclophosphamide is an alkylating agent classified under ATC code L01AA01.
The drug is a prodrug metabolised in the liver by cytochrome P450 enzymes to active metabolites.
Phosphoramide mustard is the cytotoxic metabolite that forms DNA inter‑ and intra‑strand crosslinks.
Those crosslinks block DNA replication and trigger apoptosis in dividing cells.
Acrolein is a urotoxic metabolite responsible for bladder irritation and haemorrhagic cystitis.
MESNA is used in some protocols to bind acrolein in the bladder and reduce urotoxicity.
Pharmacokinetics And Implications
Cyclophosphamide is well absorbed when taken orally, and tablets are commonly 25 mg and 50 mg.
The oral route makes outpatient nephrology regimens practical and convenient for many families.
The drug distributes widely into tissues, so renal and hepatic impairment can alter exposure.
Metabolites are eliminated largely via the kidneys, so creatinine monitoring is essential during treatment.
Pharmacokinetics explain common risks: myelosuppression, infertility, teratogenicity and secondary malignancy potential.
Australian prescribers should counsel patients on these risks and adjust doses for organ dysfunction.
Scope Of Approved & Off-Label Use
Australian Approvals (TGA-Listed, PBS Inclusion)
Cyclophosphamide is prescription‑only and used in hospital and community settings under TGA oversight.
Standard oncology uses include lymphoma, breast and ovarian cancer as part of combination regimens.
Paediatric nephrology uses include treatment for nephrotic syndrome with oral courses at 2–2.5 mg/kg/day for 8–12 weeks.
PBS listing varies by indication and formulation and many oncology uses are funded via hospitals.
Community pharmacists should always cross‑check current TGA Product Information and the PBS Schedule before dispensing.
Notable Off‑Label Trends In Australian Practice
Clinicians have increasingly used low‑dose metronomic oral cyclophosphamide for palliative care.
Single‑dose IV pulses are being adopted for severe autoimmune disease to limit cumulative toxicity.
Dose‑sparing strategies are considered where fertility preservation is a priority, particularly in younger patients.
Pharmacists help assess PBS eligibility, arrange MESNA where local protocols require uroprotection and provide contraception counselling.
Always follow local hospital protocols and specialist advice for off‑label administration and monitoring.
Dosage Strategy
General Dosing
Dosing depends on indication, formulation and patient factors such as age and organ function.
Tablets are commonly available in 25 mg and 50 mg strengths for oral administration.
Vials for IV reconstitution are typically supplied as 500 mg or 1 g powder for solution.
Oncology regimens are usually cyclical and guided by specialist protocols with cumulative dose tracking.
Baseline and regular full blood counts are essential across all dosing strategies to detect myelosuppression early.
Condition‑Specific Dosing (PBS Recommendations)
Lymphoma commonly uses 300–400 mg/m² IV every 7–10 days, adjusted to body surface area.
Breast and ovarian cancer protocols may include up to 600 mg/m² IV as part of combination therapy.
Paediatric nephrology practice typically uses oral cyclophosphamide 2–2.5 mg/kg/day for 8–12 weeks.
Autoimmune and transplant protocols often use single IV pulses or limited courses as directed by specialists.
Elderly patients and those with renal or hepatic impairment require dose reduction and close monitoring.
Pharmacists should confirm PBS authority codes when dispensing subsidised outpatient therapy.
Safety Protocols
Contraindications (Australian Guidelines)
Absolute contraindications include known hypersensitivity to cyclophosphamide or excipients.
Severe bone marrow suppression is an absolute contraindication to further cyclophosphamide dosing.
Urinary outflow obstruction and active severe infection are also absolute contraindications.
Relative contraindications include significant hepatic or renal insufficiency and pregnancy or breastfeeding.
Cardiac disease warrants caution, particularly with very high cumulative doses of cyclophosphamide.
Adverse Effects (Post‑Market Pharmacovigilance)
Common adverse effects include nausea, vomiting and alopecia.
Myelosuppression presenting as neutropenia or thrombocytopenia is routinely reported and monitored.
Urinary symptoms and haemorrhagic cystitis occur and are linked to the metabolite acrolein.
Long‑term safety signals include infertility, secondary malignancies and organ toxicities at high cumulative doses.
A monitoring checklist should include baseline FBC, renal and liver function, urinalysis and pregnancy testing.
Pharmacy counselling should emphasise hydration, contraception and prompt reporting of fevers or bleeding.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
There are no major food‑drug interactions that alter cyclophosphamide’s activation or efficacy.
Alcohol can worsen nausea and may amplify bone marrow suppression risks, so minimise alcohol intake during treatment.
High caffeine intake might exacerbate insomnia or palpitations in some patients receiving therapy.
Advise patients to stick to a balanced diet and manage nausea with antiemetic plans supplied by the clinic or pharmacy.
Drug Combinations To Avoid (TGA Safety Alerts)
Cyclophosphamide activation depends on CYP450 enzymes, so strong inducers may lower efficacy.
Examples of inducers include rifampicin and carbamazepine, which can reduce active metabolite formation.
CYP inhibitors such as some azole antifungals may raise toxicity risk and need careful review.
Concomitant nephrotoxic or myelosuppressive medicines increase adverse event risks and demand closer monitoring.
Live attenuated vaccines are contraindicated during significant immunosuppression with cyclophosphamide according to safety guidance.
Pharmacists should screen discharge and outpatient scripts for interacting medicines and counsel accordingly.
Patient Experience Analysis
Australian Survey Data
Patients consistently report concern about fertility, side‑effect burden and out‑of‑pocket costs.
Clinic surveys show patients value clear counselling from oncologists and pharmacists on hydration and contraception.
Rural patients describe barriers to hospital IV dosing and praise telehealth when it improves access to oral regimens.
Adherence improves when pharmacists provide clear dosing calendars and phone follow‑up for side‑effect management.
Forum And Pharmacy Trends
Online forums reflect common real‑world experiences with alopecia and strategies for nausea control.
Pharmacists frequently bridge knowledge gaps, particularly for patients far from specialist centres.
Telehealth and e‑script uptake have improved outpatient access for oral cyclophosphamide, with some counselling challenges.
Best practice includes pharmacist‑led education, clear patient information leaflets and pre‑treatment fertility discussions.
Distribution & Pricing Landscape
National Pharmacy Chains (Chemist Warehouse, Priceline, TerryWhite)
Distribution splits between hospital pharmacies for IV vials and community pharmacies for oral tablets.
Major chains dispense oral cyclophosphamide when prescriptions are appropriate, though many units remain hospital stock.
Supply chain monitoring is important because manufacturers include Baxter, Bristol‑Myers Squibb, Sandoz and other generics.
Occasional generic shortages have prompted proactive stock continuity planning in Australian hospitals.
Online Pharmacy Growth And Telehealth E‑Scripts
Telehealth e‑scripts and online pharmacies have increased access to oral dosing regimens for outpatients.
In our online pharmacy, cyclonex is available without a prescription, with discreet delivery to Australia in 5-14 days.
When arranging outpatient delivery, pharmacies must follow cytotoxic transport guidelines and provide counselling materials.
PBS Vs Private Cost Comparisons
PBS coverage varies by indication and many oncology administrations are hospital funded rather than PBS subsidised outpatient items.
Private costs for branded Cytoxan or imported generics can be significant without subsidy.
Pharmacists routinely check PBS status and liaise with specialists to secure authority approvals where possible.
For rural patients, community pharmacy support and local dispensing arrangements can reduce travel burdens and costs.
Alternative Options
Comparison Table Of PBS And Non‑PBS Options
Alternatives depend on the indication and include ifosfamide, chlorambucil, melphalan and bendamustine.
Some alternatives are PBS‑listed for specific malignancies while others require private scripts or hospital supply.
Choice of therapy often hinges on effectiveness for the indication, toxicity profile and patient fertility priorities.
Pros And Cons Checklist
- Pros: Well‑established efficacy, oral and IV formulations, predictable monitoring pathways.
- Cons: Urotoxicity from acrolein, fertility risks, secondary malignancy potential, and myelosuppression.
Pharmacists should present a clear choice framework including PBS eligibility, fertility preservation referrals and practical access issues.
Regulatory Status
TGA Approval Framework
Cyclophosphamide is a prescription‑only cytotoxic medicine in Australia under TGA oversight.
TGA approval covers product labelling, risk management and adverse event reporting requirements.
Hospitals implement handling guidelines for vials and hazardous preparations following TGA and state health policies.
Post‑market safety updates from 2022–25 emphasised reproductive risks and cystitis mitigation measures that pharmacies must note.
PBS Subsidy Process
PBS subsidy requires indication‑specific listing or authority prescription codes for outpatient oral therapy.
Many oncology protocols are funded within hospital or state cancer services rather than as PBS outpatient items.
Pharmacists must verify PBS Item Codes and provide counsel on claiming authority items when appropriate.
Consolidated FAQ (Australian Context)
Q: Is cyclonex on the PBS?
A: It depends on the indication and formulation; many hospital oncology uses are state funded while some outpatient indications attract PBS subsidy with authority codes.
Q: Can I take it at home?
A: Oral tablets (25 mg and 50 mg) are suitable for outpatient use, while IV vials and solutions are hospital administered.
Q: Will it affect my fertility?
A: Yes; temporary or permanent infertility is possible and fertility preservation discussion before treatment is essential.
Q: How do I avoid bladder damage?
A: Hydration, frequent voiding and MESNA where indicated reduce haemorrhagic cystitis risk.
Q: What if I miss a dose?
A: Take as soon as remembered unless the next dose is near; never double up and contact your treating team for advice.
Visual Guide
Recommended printable visuals include a PBS vs private cost infographic showing likely out‑of‑pocket ranges.
A pharmacy distribution map can illustrate hospital versus community dispensing roles and major chains involved.
A monitoring timeline graphic should list baseline checks such as FBC, U&E, LFTs and pregnancy tests and cycle‑by‑cycle monitoring.
A safety flowchart should cover hydration, MESNA use, signs of haemorrhagic cystitis and when to seek emergency care.
Visuals must be optimised for mobile viewing and suitable for pharmacy counter printouts and rural patient handouts.
Storage & Transport
Household Storage Under Australian Climate
Tablets should be stored at room temperature, typically 20–25°C and protected from moisture.
Advise patients to store cyclonex tablets in cool, dry cupboards rather than bathrooms because of Australian humidity.
Keep medicines out of reach of children and pets and in their original packaging when possible.
Cold‑Chain Logistics For Pharmacies
Vials and ready‑to‑use solutions often require refrigeration after reconstitution; follow manufacturer instructions and hospital SOPs.
Community pharmacies transporting injectable products must follow cytotoxic medicine guidelines and use authorised couriers when required.
Maintain temperature logs, especially during hot Australian summers, and have contingency plans for supply interruptions.
Dispose of unused tablets and vials through cytotoxic waste bins or return‑to‑pharmacy programmes where available.
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
Use clear, empathetic language and document fertility counselling and contraception advice in the patient's record.
Provide a Consumer Medicine Information leaflet and a simple checklist covering hydration, voiding schedules and red flags for infection.
Check for interacting medicines, confirm vaccination status and discuss travel or remote‑area support for IV dosing.
For paediatric nephrology, ensure parents understand the typical 8–12 week oral course and the need for regular blood tests.
National Health Authority Recommendations
TGA and state health guidelines require cytotoxic handling SOPs and timely adverse‑event reporting for serious reactions.
Pregnancy avoidance during treatment and for a defined period after cessation is mandated in safety guidance.
Multidisciplinary care should include fertility preservation referrals, shared decision‑making and clear follow‑up pathways for rural patients.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-7 days |
| Gold Coast | Queensland | 5-9 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Sunshine Coast | Queensland | 5-9 days |
| Cairns | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |
Concluding Notes For Prescribers And Pharmacists
Prescribers should tailor cyclonex dosing for renal and hepatic impairment and document fertility counselling before starting therapy.
Pharmacists must confirm PBS eligibility, advise on MESNA use where locally required and counsel about hydration and contraception.
Adverse events such as haemorrhagic cystitis, persistent myelosuppression and fertility impacts require prompt reporting to the TGA.
Supply planning at institutional level is important given global generic fluctuations among suppliers like Baxter, BMS and Sandoz.
When in doubt, consult the TGA Product Information, local hospital protocols and specialist teams for indication‑specific dosing and monitoring.