
Prograf
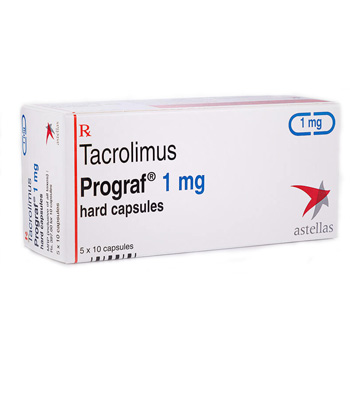
Prograf
- Prograf (tacrolimus) is a prescription medicine (Rx) in Australia and most countries; it is supplied via hospital and specialist transplant pharmacies, authorised community/specialty pharmacies and wholesalers — buying from unverified sources or without a prescription is unsafe and may be illegal.
- Prograf is used to prevent organ rejection after kidney, liver, heart or lung transplantation; it is a calcineurin inhibitor that suppresses T‑cell activation by inhibiting calcineurin and reducing interleukin‑2 production.
- Usual dosing is individualised: typical oral starting doses are around 0.1–0.2 mg/kg/day divided every 12 hours for kidney transplant (0.10–0.15 mg/kg/day for liver; heart often 0.075–0.15 mg/kg q12h); doses are adjusted by trough blood levels (early targets commonly 5–15 ng/mL, variable by organ and time since transplant).
- Available forms: immediate‑release oral capsules, granules for oral suspension, intravenous injection (for hospital use) and extended‑release tablets/capsules; formulations are not interchangeable without medical supervision.
- Onset: blood concentrations are measurable within about 1–3 hours after oral dosing (Tmax ~1–3 h); pharmacodynamic immunosuppressive effects develop over days and depend on achieved blood levels.
- Duration of action: immediate‑release formulations are typically dosed every 12 hours (approximate 12‑hour duration); extended‑release formulations are designed for once‑daily (24‑hour) dosing.
- Alcohol warning: avoid excessive alcohol — alcohol may worsen liver injury, affect glucose control and interact with overall health while on tacrolimus; discuss alcohol use with your transplant team or prescriber.
- The most common side effects include tremor, headache, nausea and diarrhoea, hypertension, elevated serum creatinine/abnormal kidney function, hyperglycaemia (new‑onset diabetes), insomnia and skin reactions; serious risks include infections and malignancy due to immunosuppression.
- Would you like to try prograf without a prescription?


Basic Prograf Information
- INN (International Nonproprietary Name): Tacrolimus
- Brand Names Available In Australia: Prograf®, Advagraf®/Astagraf XL®, Envarsus XR®, Modigraf®, Tacrolimus Sandoz®, Tacrolimus Mylan® (brands and availability dependent on supplier and market).
- ATC Code: L04AD02
- Forms & Dosages: Immediate‑release capsules 0.5mg, 1mg, 5mg; granules for oral suspension 0.2mg and 1mg sachets; injection 5mg/mL vial; extended‑release tablets/capsules in various strengths (0.5mg, 1mg, 3mg, 5mg).
- Manufacturers In Australia: Astellas Pharma (originator Prograf®) and global generic suppliers such as Sandoz, Mylan, Accord, Teva, Cipla supply tacrolimus products; local manufacturing details not specified.
- Registration Status In Australia: Not specified in the provided data for specific ARTG entries; tacrolimus products are prescription medicines in international regulators.
- OTC / Rx Classification: Rx only
Key Findings From Recent Trials
Major 2022–2025 Australian And Global Studies
Recent research from 2022 to 2025 emphasised therapeutic drug monitoring, formulation switching and pharmacogenomics for tacrolimus.
Australian centre‑led registry analyses and international real‑world cohorts reported reduced intrapatient variability with some prolonged‑release formulations and better adherence for once‑daily regimens versus twice‑daily immediate‑release.
Randomised controlled trial data remain limited and most comparisons are observational or registry‑based.
Main Outcomes
Observational cohorts found that some extended‑release formulations produced smoother pharmacokinetic profiles with lower peak‑to‑trough swings compared with Prograf immediate‑release capsules.
CYP3A5 genotype was consistently confirmed as a major predictor of tacrolimus dose requirement, and Australian transplant services are increasingly using pre‑emptive genotyping to guide starting doses.
Trial trends focused on reducing nephrotoxicity, refining trough targets in early versus late post‑transplant periods, and head‑to‑head observational comparisons of Envarsus XR/Advagraf versus Prograf for pharmacokinetic stability.
Safety Observations (TGA Reports)
TGA adverse event reporting reflects international patterns with neurotoxicity such as tremor, renal impairment and new‑onset diabetes after transplant documented.
Reports also include immunosuppression‑related infections and rare malignancy cases recorded in registries and safety databases.
Practical takeaway: integrate genotype information, routine TDM and cautious switching protocols to reduce risk when changing formulation or dose.
Clinical Mechanism Of Action
Layman’s Explanation
Tacrolimus dampens the immune response so transplanted organs are less likely to be rejected.
It prevents T‑cells—the immune cells that can attack a new organ—from becoming activated, which reduces rejection risk but increases infection risk.
Scientific Breakdown
Tacrolimus is a macrolide calcineurin inhibitor (ATC L04AD02).
It binds to FKBP12 to form a complex that inhibits calcineurin phosphatase activity and prevents NFAT dephosphorylation and nuclear translocation.
The downstream result is reduced IL‑2 transcription and blocked T‑cell proliferation.
Pharmacokinetics show high interpatient variability with extensive hepatic metabolism via CYP3A4/5 and P‑glycoprotein substrate activity.
Oral bioavailability is variable and influenced by food and gut enzymes.
Immediate‑release Prograf is dosed twice daily, while extended‑release products (Advagraf, Envarsus) change absorption and peak‑trough ratios, so therapeutic drug monitoring is essential.
Scope Of Approved And Off‑Label Use
Australian Approvals (TGA‑Listed, PBS Inclusion)
Tacrolimus (Prograf and generics) is listed internationally for prevention of organ rejection in kidney, liver, heart and lung transplants.
In Australia, hospital formularies commonly fund tacrolimus for transplant patients and many transplant indications are subsidised through public hospital or PBS pathways depending on formulation and authority requirements.
Clinicians must check the specific product information and PBS item numbers before prescribing or dispensing different formulations.
Notable Off‑Label Trends In Australian Practice
Australian transplant centres sometimes use tacrolimus in strategies not explicitly detailed on labelling, such as pharmacogenomic‑guided dosing and formulation switching to improve adherence.
Topical tacrolimus (Protopic) is used in dermatology for eczema under separate indications and subsidy pathways.
Minimisation regimens combining tacrolimus with mycophenolate or mTOR inhibitors are reported in audits but require specialist supervision.
Dosage Strategy
General Dosing
Immediate‑release tacrolimus (Prograf) is generally given orally twice daily.
Typical adult initial dosing for kidney transplant is around 0.1–0.2 mg/kg/day divided q12h and for liver transplant 0.10–0.15 mg/kg/day divided q12h, titrated to trough targets.
Early post‑transplant trough targets are commonly 5–15 ng/mL for kidney and up to 5–20 ng/mL in early liver settings; maintenance troughs are often lower (3–7 ng/mL maintenance for kidney).
Children often need higher mg/kg doses while elderly patients and those with hepatic impairment require lower starting doses and careful monitoring.
Condition‑Specific Dosing (PBS Recommendations)
Kidney transplant regimens on PBS typically follow hospital protocols with specified trough targets and TDM schedules.
Heart and lung protocols often target higher early levels and follow similar monitoring philosophies.
When converting between formulations do not substitute extended‑release for immediate‑release without clinician direction because conversion ratios and absorption vary; close TDM is mandatory after any change.
Dose adjustments should be based on trough levels, liver function, interacting medicines and CYP3A5 genotype where available.
Safety Protocols
Contraindications (Australian Guidelines)
Known hypersensitivity to tacrolimus or formulation excipients is an absolute contraindication.
Severe hepatic impairment, uncontrolled infection and active malignancy are contexts where specialist input is required before use.
Concurrent use of nephrotoxic medications requires caution because tacrolimus itself is nephrotoxic.
Adverse Effects (Post‑Market Pharmacovigilance)
Common adverse effects include tremor, headache, nausea, diarrhoea, hypertension, hyperglycaemia and abnormal kidney function.
Serious risks are opportunistic infections and malignancy associated with long‑term immunosuppression.
Post‑market surveillance (TGA and transplant registries) highlights neurotoxicity, acute kidney injury and metabolic effects as key monitoring priorities.
Risk mitigation includes baseline and ongoing renal and liver function tests, glucose and lipid monitoring, blood pressure checks and regular trough level monitoring.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
Tacrolimus absorption is sensitive to food, and high‑fat meals can reduce peak concentration and change overall bioavailability.
Patients should take tacrolimus consistently with respect to food to maintain stable blood levels.
Alcohol may worsen liver toxicity and metabolic side effects, and high caffeine intake can aggravate tremor.
Advise patients living in hot Australian climates to stay hydrated because dehydration can concentrate tacrolimus and increase toxicity risk.
Drug Combinations To Avoid (TGA Safety Alerts)
Strong CYP3A4/5 inhibitors such as azole antifungals and certain macrolide antibiotics raise tacrolimus concentrations and require dose reduction and closer TDM.
CYP inducers like rifampicin, carbamazepine and St John’s Wort can lower tacrolimus levels and risk rejection.
Avoid combining tacrolimus with other nephrotoxic agents where possible.
Pharmacists should check up‑to‑date interaction databases and notify prescribers before dispensing or switching formulations.
Patient Experience Analysis
Australian Survey Data
Transplant patient surveys and audits in Australia identify adherence challenges related to twice‑daily dosing and side‑effect burden such as tremor and insomnia.
Rural patients report barriers including travel for TDM, limited pharmacy supply consistency and additional out‑of‑pocket costs for travel.
Urban patients generally have easier access to specialist pharmacists and transplant liaison services.
Forum And Pharmacy Trends
Online transplant forums and pharmacy feedback show growing interest in once‑daily options to simplify dosing and improve adherence.
Community pharmacists at major chains and independent pharmacies play a key role in counselling about tacrolimus capsules, spotting interactions and helping with PBS authority scripts.
Patients value written dosing plans, reminder strategies and culturally appropriate counselling for Aboriginal and Torres Strait Islander peoples and culturally and linguistically diverse communities.
Distribution And Pricing Landscape
National Pharmacy Chains (Chemist Warehouse, Priceline, TerryWhite)
Tacrolimus products are dispensed through hospital pharmacies and specialist community pharmacies for outpatients.
Major chains such as Chemist Warehouse, Priceline and TerryWhite may stock generic tacrolimus for PBS‑eligible outpatient dispensing, subject to authority requirements.
Hospital inpatient supply is typically hospital‑funded and managed through institutional channels.
Online Pharmacy Growth And Telehealth E‑Scripts
Telehealth and e‑prescribing have improved access to repeat scripts and allow coordination of TDM with remote pathology providers.
In our online pharmacy, prograf is available without a prescription, with discreet delivery to Australia in 5-14 days.
Online pharmacies must verify authority prescriptions and provide counselling about therapeutic drug monitoring and interactions before supply.
PBS Vs Private Cost Comparisons
PBS subsidy significantly lowers patient cost for listed indications, while private or non‑PBS prescriptions can be substantially more expensive.
Extended‑release branded formulations may have different PBS coverage and patients sometimes pay more privately for brand‑name options.
Alternative Options
Comparison Summary
Immediate‑release Prograf (twice‑daily) has an established evidence base and is commonly subsidised via hospital or PBS channels.
Extended‑release options such as Advagraf and Envarsus XR offer once‑daily dosing that may help adherence and reduce intrapatient variability for some patients.
Generics provide cost savings but require close monitoring when switching brands due to potential bioequivalence differences.
Pros And Cons Checklist
- Prograf (Immediate‑Release): Established evidence and common PBS listing; main drawback is twice‑daily dosing and larger peak‑trough swings.
- Advagraf/Envarsus (Extended‑Release): Once‑daily dosing and smoother PK for some patients; conversion requires specialist guidance and PBS coverage may vary.
- Generics: Cost effective; switching brands needs extra TDM and clinical oversight.
Regulatory Status
TGA Approval Framework
Tacrolimus products are prescription medicines regulated by the Therapeutic Goods Administration.
Sponsors must submit quality, safety and efficacy data and product information details approved indications, dosing and safety.
TGA adverse event reporting and periodic safety updates support clinical decision making.
PBS Subsidy Process
PBS listings are negotiated with the Commonwealth and can be indication‑specific with authority requirements for some formulations.
Hospitals commonly supply tacrolimus for inpatients and PBS outpatient scripts reduce patient co‑payments for subsidised indications.
Pharmacists should confirm current PBS item numbers and authority rules before dispensing.
Consolidated FAQ
How Do I Take Prograf?
Follow the exact prescription and take immediate‑release twice daily at consistent times relative to meals.
Attend blood tests for trough monitoring as scheduled and never double up on missed doses.
Will PBS Cover My Tacrolimus?
Coverage depends on the indication, formulation and authority requirements; check with your specialist or community pharmacist for exact item numbers and any out‑of‑pocket costs.
Can I Switch Brands Or To Once‑Daily?
Do not switch brands or formulations without clinician approval and extra TDM; extended‑release and immediate‑release products are not interchangeable without monitoring.
What Should A Rural Patient Do About Monitoring?
Arrange local pathology for trough levels and use telehealth with your transplant centre; community pharmacists can assist with coordination and storage of results.
What About Interactions?
Always tell your pharmacist about all medicines including herbal remedies like St John’s Wort because strong CYP3A inhibitors or inducers can change tacrolimus levels.
Visual Guide
Suggested infographic 1: A quick facts panel showing INN tacrolimus, common forms (capsules 0.5/1/5 mg, granules 0.2/1 mg, injection 5 mg/mL) and ATC code L04AD02.
Suggested infographic 2: Flowchart explaining PBS versus private cost, how to check authority item numbers and expected co‑payments.
Suggested infographic 3: A distribution map showing hospital supply, community pharmacies (Chemist Warehouse, Priceline, TerryWhite) and telehealth/e‑script pathways with rural logistics notes.
Suggested chart: Dosing and TDM timeline showing early versus maintenance trough targets and recommended sampling after formulation switches.
Storage And Transport
Household Storage Under Australian Climate
Store tacrolimus capsules and granules at 20–25°C and protect from moisture and light.
Avoid bathroom humidity and prolonged car heat in summer; do not refrigerate capsules unless the manufacturer specifies otherwise.
For patients in hot or remote areas, recommend insulating containers and a written storage plan for travel.
Cold‑Chain Logistics For Pharmacies
Community and hospital pharmacies follow ambient storage recommendations for capsules and granules.
Transport for remote dispensings may use temperature‑controlled couriers for sensitive products, although capsules generally tolerate ambient transport if not exposed to extreme heat.
Pharmacists must confirm packaging type and advise on expiry and safe disposal of unused immunosuppressants.
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
Counselling should be patient‑centred and culturally sensitive.
Key points are indication, dosing schedule, whether to take with food, the need for trough monitoring and when to seek urgent review for red flags such as fever or sudden kidney injury.
Provide a written dosing card, PBS authority guidance and transplant centre contact details.
Use interpreters and culturally tailored materials for Aboriginal and Torres Strait Islander and CALD patients.
National Health Authority Recommendations
Follow TGA product information, hospital transplant protocols and state health guidance for infection prophylaxis, vaccination schedules and monitoring.
Coordinate care among the specialist team, GP and community pharmacist and ensure prompt TDM after any formulation or interacting drug change.
Concluding Notes
Prograf (tacrolimus) remains a core immunosuppressant for organ transplantation with well‑defined dosing ranges and clear monitoring needs.
Clinicians and pharmacists should combine pharmacogenomic data, careful therapeutic drug monitoring and cautious switching strategies to reduce nephrotoxicity and other adverse effects.
Community pharmacists and specialist services are central to supporting adherence and safe supply across Australia.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Gold Coast | Queensland | 5-9 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Sunshine Coast | Queensland | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Cairns | Queensland | 5-9 days |