Quetiapine
Quetiapine
- Quetiapine can be purchased from pharmacies in Australia as a prescription-only medicine, and supply is subject to a valid prescription from a registered healthcare professional.
- Quetiapine is an atypical (second-generation) antipsychotic used for schizophrenia, bipolar disorder, and sometimes as adjunct treatment in depression. It works by affecting dopamine and serotonin receptors in the brain.
- The usual dose depends on the condition: for adults with schizophrenia, treatment often starts at 50 mg twice daily and is titrated to 300–400 mg per day; for bipolar disorder, doses commonly range up to 400 mg per day for mania and 300 mg per day for depression. Doses may be adjusted by a doctor.
- It is taken by mouth as immediate-release or extended-release tablets.
- Quetiapine may start to make you feel drowsy within a few hours, but its full therapeutic effect usually takes several days to weeks of regular use.
- The duration of action varies by formulation: immediate-release tablets generally last around 6 hours, while extended-release tablets provide coverage for about 24 hours.
- Alcohol should be avoided, as it can increase drowsiness, dizziness, and the risk of side effects.
- The most common side effects are drowsiness, dizziness, dry mouth, weight gain, increased appetite, constipation, headache, and mild fast heart rate.
- Would you like to try quetiapine without a prescription?

Key Findings From Recent Trials And Market Trends
Basic Quetiapine Information
- INN (International Nonproprietary Name): Quetiapine
- Brand Names Available In Australia: Seroquel, Seroquel XR, Quetiaccord, Quetiapine Sandoz, Quetiapine RBX, APX-Quetiapine
- ATC Code: N05AH04
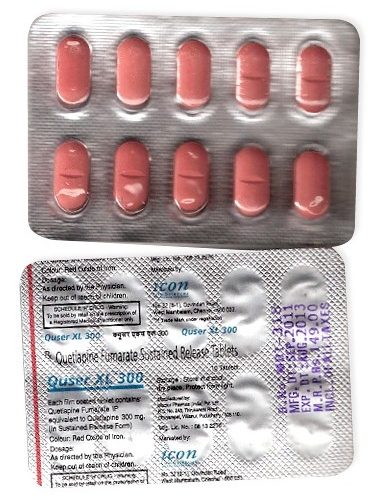
- Forms & Dosages: Immediate-release tablets 25 mg, 50 mg, 100 mg, 150 mg, 200 mg, 300 mg, 400 mg; extended-release tablets 50 mg, 150 mg, 200 mg, 300 mg, 400 mg
- Manufacturers In Australia: Accord, Sandoz, Apotex, other local generic suppliers
- Registration Status In Australia: Prescription only (Rx)
- OTC / Rx Classification: Prescription only (Rx)
What has changed in the last few years is not the fact that quetiapine is an atypical antipsychotic, but how carefully it is being positioned in everyday Australian practice.
Between 2022 and 2025, prescribing has continued to shift towards clearer use in schizophrenia, bipolar disorder, and selected adjunctive depression cases, while clinicians have become more cautious about sedation, weight gain, and metabolic monitoring.
That matters in Australia because the PBS, generic substitution, and community pharmacy follow-up all shape whether a patient stays on treatment long enough to benefit from it.
Quetiapine, sold as Seroquel, Seroquel XR, and Australian generics such as Quetiaccord, remains an oral atypical antipsychotic with a strong place in psychiatric care, but it is not a “set and forget” medicine.
Real-world use still shows a familiar pattern: people often accept it well at first because sleep improves quickly, then later struggle with morning grogginess, appetite increase, or weight gain.
That trade-off is why recent evidence and market behaviour are being read more practically now, especially in people who need to keep working, driving, or caring for family.
For schizophrenia, quetiapine tablets remain a recognised option where a balance is needed between symptom control and extrapyramidal tolerability, although other atypical antipsychotics may be preferred when weight gain or sedation is a major concern.
For bipolar disorder, quetiapine XR continues to be used widely because the extended-release profile can be easier to live with than immediate-release dosing for some patients, even if sedation still occurs.
In adjunctive depression, the evidence base supports selected patients, but the practical discussion in Australia often comes down to cost, tolerability, and whether the person can manage the titration phase.
Post-market safety signals still centre on the same themes that pharmacists screen for every day: metabolic syndrome, orthostatic hypotension, falls risk, QT prolongation in susceptible patients, and additive CNS depression with other medicines.
So the key lesson from recent trials and market trends is simple: quetiapine still has an important role, but success depends on matching the formulation, dose, and monitoring plan to the person in front of you.
Clinical Mechanism Of Action
Ever wondered why one tablet can make a person feel calmer, sleepier, and sometimes a bit light-headed at the same time?
Quetiapine works on several receptors in the brain and body, and that broad action explains both its benefits and its downsides.
In plain language, it helps dampen overactive signalling involved in psychosis and mood symptoms, while also affecting pathways linked to sleepiness and blood pressure.
Its main pharmacology includes serotonin 5-HT2A antagonism and dopamine D2 antagonism, which is why it sits in the atypical antipsychotic class.
That receptor mix is part of why quetiapine is used in schizophrenia and bipolar disorder, and why it is sometimes chosen when clinicians want fewer movement-related side effects than with older antipsychotics.
The flip side is that histamine H1 blockade contributes to sedation, and alpha-1 adrenergic blockade contributes to orthostatic hypotension.
That is the mechanism behind the “I stood up too quickly and felt faint” story that patients sometimes describe after starting quetiapine tablets.
Dosage forms matter too.
Immediate-release tablets can feel more noticeable soon after a dose, while Seroquel XR and other extended-release products are designed to smooth out the release over the day.
In practice, patients often report that quetiapine XR vs IR feels different even when the total daily dose is similar.
That difference can help with daytime functioning, but it does not remove the need for careful quetiapine titration.
Australian strengths commonly include quetiapine 25 mg, 50 mg, 100 mg, 150 mg, 200 mg, 300 mg, and 400 mg in immediate-release form, with XR strengths from 50 mg up to 400 mg.
Lower strengths are often used early in treatment or for gradual dose increases, especially when sedation is a concern.
Because the mechanism touches several receptor systems at once, the dose itself also shapes the clinical picture, which is why prescribers usually build up slowly over several days rather than starting high.
That cautious approach helps reduce dizziness, excessive sleepiness, and sudden blood-pressure drops.
Scope Of Approved And Off-Label Use
Patients often ask whether quetiapine is “approved for everything it is used for”, and the short answer is no.
In Australia, quetiapine is a prescription-only medicine, and the difference between TGA approval and off-label use matters.
TGA-approved use covers major psychiatric conditions such as schizophrenia and bipolar disorder, with adjunctive depression use recognised in some settings depending on formulation and jurisdiction.
Off-label quetiapine prescribing is also seen in practice, particularly for insomnia and anxiety-related symptoms, but these uses should be approached carefully because the evidence is not as strong as it is for registered indications.
That is where PBS subsidy rules, clinical judgement, and patient affordability all intersect.
If a prescriber chooses a PBS-listed option, the conversation in pharmacy is often very practical: what is the cheapest equivalent, can the brand be substituted, and will the patient cope with the sedation profile.
Australian patients may see the medicine written as quetiapine, Seroquel, Seroquel XR, Quetiapine Sandoz, Quetiapine RBX, APX-Quetiapine, or Quetiaccord, depending on the script and stock available.
That can be confusing at the counter, especially when the person is switching between generic quetiapine suppliers.
In day-to-day Australian practice, quetiapine uses tend to cluster around three areas.
- Schizophrenia management, where symptom control and tolerability both matter.
- Bipolar disorder, including mania and bipolar depression.
- Adjunctive depression treatment, usually when other options have not been enough or have not been tolerated.
Insomnia is the off-label area that attracts the most public attention, partly because quetiapine can be sedating even at low doses.
That said, sedation is not the same thing as a proper sleep medicine effect, and many patients later discover that they wake foggy, hungry, or constipated.
For that reason, prescribers and pharmacists in Australia usually weigh the evidence, the PBS subsidy, and the long-term side effect burden before supporting off-label use.
Dosage Strategy
How fast should quetiapine be started, and what dose is “normal”?
The answer depends on the indication, the formulation, and the person’s age and liver function.
For adults with schizophrenia, the usual starting dose is 50 mg twice daily with immediate-release tablets, then titrated over several days towards a target of 300 to 400 mg a day in divided doses.
The maximum daily dose for immediate-release schizophrenia treatment is 750 mg.
For bipolar disorder, the starting dose is commonly 50 mg once or twice daily, with targets up to 400 mg a day for mania and 300 mg a day for depression.
For mania, the maximum daily dose can reach 800 mg.
For adjunctive depression, Seroquel XR is often started low, such as 50 mg daily, with a usual target of up to 300 mg daily.
Slow quetiapine dosing is not just a formality.
It helps reduce drowsiness, dizziness, and orthostatic hypotension, which are the side effects most likely to make someone stop the medicine early.
In older adults, a lower starting point such as 25 mg twice daily is typical, and titration should be slower because CNS effects and blood-pressure drops are more likely.
Liver impairment also calls for caution, with a lower initial dose, often around 25 mg daily, and gradual increase.
Renal impairment does not usually require a major adjustment, but monitoring is still sensible.
There are practical differences between IR and XR dosing too.
Some patients tolerate a once-daily XR routine better because it is simpler, while others need immediate-release tablets because the prescriber is aiming for a more flexible divided-dose plan.
Missed-dose advice should be clear from the start.
If the next dose is due soon, skip the missed dose and do not double up.
That rule is especially important with quetiapine 100 mg or higher strengths, where an extra tablet can cause marked sleepiness or low blood pressure.
A person who misses doses repeatedly should speak to the prescriber or pharmacist, because repeated gaps can undo symptom control and make side effects more noticeable when treatment restarts.
Safety Protocols
What are the red flags before a prescription is continued or a repeat is supplied?
With quetiapine safety Australia-wide, the first checks are hypersensitivity, interacting medicines, and whether the patient has a risk profile that needs closer monitoring.
Known hypersensitivity to quetiapine or excipients is an absolute contraindication.
Co-administration with potent CYP3A4 inhibitors such as ketoconazole is another major issue because it can require dosage adjustment.
There are also relative contraindications that deserve a proper review rather than a rushed repeat.
- Cardiovascular disease, especially arrhythmias or QT prolongation.
- Dementia-related psychosis in older adults, where mortality risk is increased.
- Hepatic impairment.
- Seizure risk.
- Diabetes or other metabolic syndrome risk factors.
Common quetiapine side effects reported in post-market surveillance include drowsiness, dizziness or orthostatic hypotension, dry mouth, weight gain, increased appetite, constipation, mild tachycardia, and headache.
Those are not minor details in primary care or community pharmacy.
Weight, blood glucose, lipids, blood pressure, and falls risk all matter.
A patient who starts at a low dose but gains weight over several months may still be benefiting psychiatrically while quietly accumulating metabolic risk.
That is why metabolic monitoring is part of responsible quetiapine monitoring, not an optional extra.
People with diabetes, pre-diabetes, or a family history of metabolic disease need special attention.
Older adults are also more vulnerable to orthostatic hypotension and CNS effects, which can lead to falls, confusion, and reduced independence.
QT prolongation is not common in every patient, but it matters enough that pharmacists should screen for relevant cardiac history and combinations that increase risk.
When in doubt, the safest advice is to pause and check before dispensing.
Interaction Mapping
One of the most useful questions in counselling is also the simplest: what else is the patient taking tonight?
Alcohol and quetiapine is the interaction people often understand most quickly, because the combination can increase sedation, impair judgement, and worsen falls risk.
That means a Friday night drink can matter more than many patients expect, especially if they have just started treatment or their dose has been increased.
Other CNS depressants also need care, particularly sedatives, opioids, and benzodiazepines.
These combinations can compound drowsiness and make driving or machinery use unsafe.
CYP3A4 inhibitors are another key screen for pharmacists and telehealth prescribers.
Strong inhibitors such as ketoconazole can raise quetiapine exposure, so the script and the medicine list need to be checked together.
Food is not the main interaction concern here, but routine advice about taking tablets consistently still helps adherence.
Caffeine is not a major direct interaction with quetiapine, although too much coffee can disrupt sleep, increase anxiety, and make it harder for some patients to stick with their evening routine.
That kind of practical advice often matters more than labelling every drink as “forbidden”.
What pharmacists must screen for in real consultations is the mix of sedation, blood-pressure effects, and metabolic risk.
If a person is already taking a hypnotic, a pain medicine with sedating effects, or a medicine that affects heart rhythm, the counselling conversation needs to be more detailed.
Patients should also be reminded not to start or stop interacting medicines without checking, because quetiapine interactions can change quickly when treatment is altered elsewhere.
Patient Experience Analysis
What do people actually say about living with quetiapine?
Australian patient experience tends to split into two camps.
Some people appreciate the calm, the reduction in agitation, or the improvement in sleep.
Others focus on morning grogginess, increased appetite, dry mouth, constipation, and the feeling that they are “not quite themselves” early in treatment.
That gap between clinical efficacy and lived experience is why adherence can be patchy even when the medicine is helping.
Real-world use also reflects strong price sensitivity in Australia.
Patients often ask for the PBS medicine, the cheapest equivalent, or a familiar pharmacy brand they have used before.
That is especially true for people on long-term treatment who need repeat scripts and want predictable supply.
Community pharmacy plays a big role here because people often return with practical questions after the first few days, such as whether the drowsiness is normal or whether they can drive in the morning.
In rural and regional areas, access can be more difficult if a specific brand or strength is out of stock.
That is where brand substitution, e-script access, and pharmacist counselling become especially important.
For some people, the sedative effect is actually part of the reason they stay on treatment, particularly when sleep has been poor for a long time.
But if the medicine leaves them too sleepy to work, care for children, or drive safely, adherence often falls away.
So the patient experience is rarely just about symptom control.
It is about function, convenience, cost, and whether the medicine fits real life.
Distribution And Pricing Landscape
Where do Australians usually get quetiapine, and why does the same medicine seem to have so many names?
Access is spread across national pharmacy chains such as Chemist Warehouse, Priceline, and TerryWhite Chemmart, as well as independent pharmacies across metro and regional Australia.
Availability is usually easier in major cities, but smaller towns can face stock delays or limited brand choices.
That is where online ordering and e-script access have changed the experience for many people.
Telehealth prescribing has made it simpler for patients to renew treatment, particularly when they already have a stable regimen.
Australian generics such as Quetiaccord, Quetiapine Sandoz, and other local equivalents are common substitution options, and that can lower cost significantly under PBS rules.
Patients often ask for the cheapest equivalent, which is reasonable when treatment is long term and budgets are tight.
In our online pharmacy, quetiapine is available without a prescription, with discreet delivery to Australia in 5-14 days.
That access model appeals to some customers looking for privacy and convenience, especially when they are comparing brands or prices.
PBS pricing remains a major driver of purchase decisions.
For many patients, the PBS medicine is the difference between continuing treatment and stopping early.
That is why pharmacists often spend time explaining generic substitution, pack sizes, and whether immediate-release and XR products are interchangeable.
Pack presentation also varies.
Australian products are commonly supplied in blister packs, often in 30- or 60-tablet boxes, depending on strength and manufacturer.
When stock is tight, patients may be offered a different brand with the same active ingredient, and that should be explained clearly at the counter.
Alternatives To Quetiapine
Sometimes the better question is not “Is quetiapine the right drug?” but “Is it the right fit for this person?”
That is where alternatives such as olanzapine, risperidone, aripiprazole, ziprasidone, and clozapine come into the conversation.
Each has a different balance of sedation, metabolic burden, activation, and extrapyramidal symptom risk.
| Medicine | Main Strength | Main Limitation | Typical Fit |
|---|---|---|---|
| Quetiapine | Useful for sleep disturbance and mood symptoms | Sedation and weight gain | Schizophrenia, bipolar disorder, adjunctive depression |
| Olanzapine | Strong antipsychotic effect | Higher metabolic burden | When efficacy is prioritised and weight risk is acceptable |
| Risperidone | Effective for psychosis | More risk of movement-related effects | When sedation is less desirable |
| Aripiprazole | Less sedating and often more activating | Can feel restless for some people | When weight gain and sedation are major concerns |
| Ziprasidone | Different side-effect profile | May not suit every patient | Selected patients needing an alternative profile |
| Clozapine | Reserved for treatment-resistant cases | Requires close monitoring | When other options have failed |
The practical pros and cons checklist usually comes down to this.
- If sedation is helpful, quetiapine may suit.
- If weight gain is already an issue, aripiprazole may be considered.
- If psychosis is severe and treatment-resistant, clozapine may be needed.
- If a patient cannot tolerate movement side effects, quetiapine may be preferable to some alternatives.
Australian prescribing habits also reflect PBS and access realities, so the “best” option is often the one the patient can safely and affordably continue.
Regulatory Status
Quetiapine sits within the TGA registration framework as a prescription medicine, which means it must be prescribed by an authorised prescriber and dispensed under normal pharmacy controls.
That prescription-only status is important because dose, indication, and interaction screening all need clinical oversight.
PBS subsidy matters because it directly affects patient affordability and continuation.
When a medicine is PBS-listed, the out-of-pocket cost can be much more manageable, especially for ongoing psychiatric treatment.
Australian suppliers include Accord and other generics, and branding can vary by territory, strength, and formulation.
That is why a repeat script written for quetiapine may be dispensed as Seroquel, Quetiaccord, or another approved generic equivalent, depending on stock and substitution rules.
Patients should always ask the pharmacist about the brand, the formulation, and whether the tablet is immediate-release or XR before leaving the counter.
That small check can prevent dosing errors and confusion later at home.
Repeat scripts, dose changes, and brand switches are all easier when the person understands the medicine name rather than only the packaging colour.
Consolidated Frequently Asked Questions
Is quetiapine the same as Seroquel?
Yes.
Quetiapine is the INN, while Seroquel and Seroquel XR are brand names.
Australian generics such as Quetiaccord or Quetiapine Sandoz contain the same active ingredient, though the pack and brand may differ.
Can I take quetiapine for sleep?
Quetiapine is sometimes used off label for sleep, but that is not the same as being a standard sleep medicine.
Sedation is common, and some people do sleep better, but the trade-off can be weight gain, dry mouth, constipation, and morning grogginess.
What happens if I miss a dose?
Take the next dose as soon as you remember.
If it is close to the time for the next dose, skip the missed one and do not double up.
If doses are being missed often, speak to the prescriber or pharmacist.
Does quetiapine cause weight gain?
Yes, weight gain and increased appetite are common side effects.
That is why regular weight checks, glucose monitoring, and lipid checks are part of good quetiapine monitoring.
Is quetiapine safe to stop suddenly?
Stopping suddenly can cause problems for some people, including return of symptoms.
Any change in dose should be discussed with a healthcare professional, especially after long-term use.
Visual Guide
A good visual summary helps patients compare quetiapine tablets, strengths, and brands without having to read a long leaflet.
A simple infographic could show the difference between immediate-release and XR products, along with common strengths such as quetiapine 25 mg, 100 mg, 200 mg, and 400 mg.
It could also highlight Australian brand examples including Quetiaccord and Quetiapine Sandoz, plus common pack sizes in blisters.
A second panel could show PBS pricing at a glance, since patients often want to know whether the generic option is cheaper than the brand they have used before.
A distribution map could be useful too, with metro areas usually having faster brand access than rural locations.
That kind of callout is especially helpful for people ordering through community pharmacy or online pharmacy channels.
Storage And Transport
How should quetiapine be kept at home, especially in Australian heat?
The simple rule is room temperature, between 15 and 30°C, in the original packaging, protected from moisture and light.
That matters more than many people think.
A car glove box, a hot kitchen bench, or a bag left in the sun can expose tablets to conditions that are well outside recommended storage.
For families and carers, original packaging also makes it easier to identify the strength, brand, and expiry date.
That is useful during travel across regional areas, when medicine supplies may need to last longer than expected.
Pharmacy deliveries should also stay sealed until use, and tablets should not be transferred into unlabelled containers unless a pharmacist has advised it.
Moisture and light protection is particularly important if the medicine is stored in a bathroom or near a window.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-7 days |
| Gold Coast | Queensland | 5-9 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Cairns | Queensland | 5-9 days |
Guidelines For Proper Use
Pharmacist counselling in Australia usually starts with the questions that affect day-to-day safety.
Will this medicine make the person sleepy?
Can they drive?
Should it be taken at night?
Are they drinking alcohol or taking other sedating medicines?
Those are not small points; they are often the difference between good adherence and an early stop.
Driving advice should be clear, especially after a dose increase or when first starting quetiapine.
If the person feels drowsy, light-headed, or less alert, they should avoid driving or operating machinery until they know how the medicine affects them.
Alcohol avoidance is also standard counselling because additive sedation can be significant.
National guidance and routine pharmacy practice both support ongoing review of need, not just initial supply.
Metabolic monitoring should include weight, blood pressure, glucose, and lipids at appropriate intervals, particularly in patients with diabetes risk or long-term treatment.
Rural access issues mean follow-up is not always easy, so community pharmacists often become the regular point of contact for adherence, side effects, and brand changes.
If a patient is unsettled by morning grogginess, a pharmacist may suggest confirming whether the dose timing or formulation is being used as intended, then refer back to the prescriber if changes are needed.
Urgent help is needed if there are signs of severe dizziness, fainting, confusion, chest symptoms, or an overdose concern.
Proper quetiapine counselling, regular monitoring, and honest discussion about side effects all improve the chance that the medicine will do its job safely over the long term.