Efexor
Efexor
- In our pharmacy you can buy efexor without a prescription, with delivery across Australia (discreet packaging); note that venlafaxine is officially prescription‑only in most countries, so check local regulations.
- Efexor (venlafaxine) is used for major depressive disorder, generalized anxiety disorder, social anxiety disorder and panic disorder; it is a serotonin–noradrenaline reuptake inhibitor (SNRI) that increases levels of serotonin and noradrenaline in the brain.
- Typical adult doses are 75–225 mg/day (starting often at 75 mg/day for XR; some patients may require up to 225 mg/day; immediate‑release doses are usually divided; rare cases with IR dosing may go higher under specialist supervision).
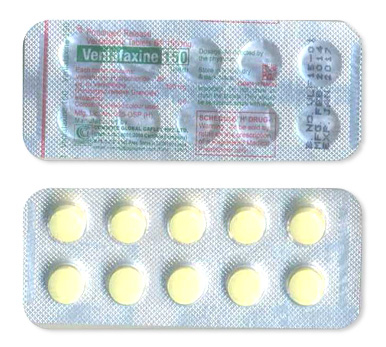
- Oral administration as immediate‑release tablets (25, 37.5, 50, 75, 100 mg) or extended‑release capsules/tablets (37.5, 75, 150 mg).
- Some people notice initial improvements within 1–2 weeks (especially for anxiety); antidepressant benefits commonly take 2–4 weeks and up to 4–6 weeks for a fuller response.
- Extended‑release efexor is designed for once‑daily dosing and provides ~24‑hour coverage; immediate‑release formulations usually require twice‑daily dosing.
- Avoid alcohol while taking efexor — alcohol can worsen drowsiness, impair judgement, increase side effects and may reduce treatment effectiveness.
- The most common side effect is nausea.
- Would you like to try “efexor” without a prescription?

Basic Efexor Information
- INN (International Nonproprietary Name): Venlafaxine
- Brand Names Available In Australia: Efexor (spelling variation), Effexor/Effexor XR (originator Pfizer), generic venlafaxine from suppliers such as Teva, Sandoz, Mylan and others.
- ATC Code: N06AX16
- Forms & Dosages: Immediate‑release tablets 25 mg, 37.5 mg, 50 mg, 75 mg, 100 mg; Extended‑release capsules/tablets 37.5 mg, 75 mg, 150 mg.
- Manufacturers In Australia: Originator manufacturer Pfizer supplies Effexor/Efexor; multiple generics supplied by global companies such as Teva, Sandoz and Mylan are registered or supplied into Australian channels.
- Registration Status In Australia: Venlafaxine products are registered as prescription medicines with Australian regulators; brand and generic registration details should be confirmed on the TGA register.
- OTC / Rx Classification: Prescription only (Rx Only).
Key Findings From Recent Trials (2022–2025)
Major 2022–2024 Australian & Global Studies
Patients often ask whether venlafaxine still works better than an SSRI for difficult cases of anxiety or depression.
Recent systematic reviews and pooled analyses from 2022–2024 reinforced venlafaxine’s efficacy for major depressive disorder and generalized anxiety disorder, particularly when selective serotonin reuptake inhibitors have been insufficient.
Randomised trials reported faster symptom reduction for some patients compared with SSRIs, with effect sizes that were modest but clinically meaningful in treatment‑resistant and mixed anxiety–depression cohorts.
Extended‑release formulations featured prominently in the literature because they improved adherence and smoothed early side effects in many trial populations.
Main Outcomes
Remission and response rates were consistently favourable versus placebo across both immediate‑release and extended‑release formulations.
Extended‑release (XR) preparations tended to show better tolerability and adherence compared with multiple daily immediate‑release dosing schedules in trial reports.
Where trials compared venlafaxine to SSRIs, differences in speed of improvement were sometimes seen rather than large differences in overall response rates.
Safety Observations (TGA Reports)
Post‑marketing surveillance through 2022–2024 highlighted dose‑dependent hypertension, withdrawal or discontinuation syndrome, and sexual dysfunction as leading safety signals.
TGA case series emphasised the need for blood‑pressure monitoring when doses are escalated and recommended slow tapering to reduce discontinuation effects.
Clinical Mechanism Of Action
Layman’s Explanation
People often ask what venlafaxine actually does in plain terms.
Venlafaxine is an SNRI — a serotonin‑norepinephrine reuptake inhibitor — that raises levels of serotonin and norepinephrine in the brain to improve mood, reduce anxiety and help with energy and motivation.
Extended‑release forms release the drug steadily over the day to reduce peaks and troughs that can cause side effects and to make once‑daily dosing more convenient.
Scientific Breakdown
At lower doses venlafaxine predominantly inhibits serotonin reuptake, while at higher doses norepinephrine reuptake inhibition becomes more pronounced.
There is minimal dopamine reuptake effect, mainly at higher doses, which may contribute to an energising influence for some patients.
The combination of serotonergic and noradrenergic activity explains why venlafaxine can be effective for depressive and anxiety symptoms, and why it is sometimes chosen when SSRIs alone have failed.
Pharmacokinetics (Brief)
Venlafaxine is metabolised in the liver by CYP2D6 to its active metabolite O‑desmethylvenlafaxine (desvenlafaxine).
The half‑life is approximately 5 hours for venlafaxine and about 11 hours for the active metabolite, supporting once‑daily XR regimens.
Dose adjustments are advised in hepatic and renal impairment to reduce the risk of accumulation and adverse effects.
Scope Of Approved & Off‑Label Use
Australian Approvals (TGA‑Listed, PBS Inclusion)
Clinicians and patients commonly check whether venlafaxine is listed on the PBS before starting a course.
Venlafaxine (Efexor/Effexor/Effexor XR spelling variations) is prescription‑only and is registered for major depressive disorder, generalized anxiety disorder, social anxiety disorder and panic disorder in regulatory jurisdictions such as the FDA and EMA.
In Australia the Therapeutic Goods Administration registers venlafaxine products; PBS listing depends on formulation and indication and should be verified on the current PBS Schedule for subsidy eligibility.
Notable Off‑Label Trends In Australian Practice
Some prescribers use venlafaxine off‑label for persistent somatic symptom disorder when depression or anxiety is a clear factor, usually with specialist input.
It is also used cautiously for chronic pain with comorbid depression and for certain neuropathic pain syndromes when evidence or clinical need supports the choice.
Off‑label use requires clear informed consent and close monitoring for adverse effects like blood‑pressure changes and discontinuation symptoms.
Dosage Strategy
General Dosing
Venlafaxine is available as immediate‑release tablets (25–100 mg) and extended‑release capsules/tablets (37.5, 75, 150 mg).
Typical initiation is Efexor XR 75 mg once daily or immediate‑release dosing totalling 75 mg per day divided into two or three doses.
Titration is guided by response and tolerability, with attention to blood pressure at higher doses.
Condition‑Specific Dosing (PBS Recommendations)
For major depressive disorder adults, initial dosing is IR 75 mg/day (divided) or XR 75 mg once daily, with titration to 150–225 mg/day if needed.
The usual maximum per product information is 225 mg/day, although some IR regimens in specialist settings may go up to 375 mg/day in select cases under close supervision.
For generalized anxiety disorder, social anxiety and panic disorder, XR regimens commonly range from 37.5–225 mg/day depending on clinical response and tolerability.
Special Populations
In elderly patients start at the lowest effective dose and titrate slowly while monitoring blood pressure and sodium levels.
In hepatic impairment reduce the dose by about 50% and monitor carefully for adverse effects.
In moderate to severe renal impairment a dose reduction to 25–50% of the usual dose is typically advised.
Safety Protocols
Contraindications (Australian Guidelines)
Do not use venlafaxine in patients with known hypersensitivity to venlafaxine or any ingredient in the formulation.
Avoid concurrent or recent monoamine oxidase inhibitor therapy; maintain at least a 14‑day wash‑out period following MAOI discontinuation.
Uncontrolled narrow‑angle glaucoma is an absolute contraindication.
Screen for recent myocardial infarction, history of mania or bipolar disorder, and seizure disorders before prescribing as relative contraindications or precautions.
Adverse Effects (Post‑Market Pharmacovigilance)
Very common adverse effects include nausea and vomiting, especially during initiation.
Common effects include insomnia, somnolence, dry mouth, sweating, anorexia and sexual dysfunction.
Dose‑dependent hypertension is an important safety concern and requires baseline and periodic blood‑pressure checks, particularly above 150 mg/day.
Monitoring Checklist
- Baseline blood pressure measurement and periodic checks after dose increases.
- Mood and suicidality screening, especially in the first weeks of treatment.
- Review of concomitant medications for interaction risks.
- Serum electrolytes in elderly patients to guard against hyponatraemia.
- Periodic weight and review of sexual function as part of routine follow‑up.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
There are no major dietary restrictions required for venlafaxine, but alcohol should be minimised while stabilising therapy because it can add to central nervous system depression and worsen mood symptoms.
Caffeine can exacerbate anxiety or insomnia in susceptible people taking venlafaxine, so counsel patients to monitor intake.
Drug Combinations To Avoid (TGA Safety Alerts)
Avoid concurrent use with monoamine oxidase inhibitors because of the risk of serotonin syndrome.
Potent CYP2D6 inhibitors may alter venlafaxine metabolism and require closer monitoring or dose adjustments.
Concurrent serotonergic agents, including other SSRIs/SNRIs, triptans and linezolid, increase the risk of serotonin syndrome and should be combined only under specialist supervision.
Anticoagulants and non‑steroidal anti‑inflammatory drugs raise bleeding risk when used with venlafaxine, so use caution and review INR where appropriate.
Practical Pharmacy Cues
- Flag e‑prescriptions that combine psychotropics with venlafaxine and prompt prescribers to consider tapering strategies when switching agents.
- Advise patients on the risks of over‑the‑counter NSAIDs and recommend prescriber review for concurrent anticoagulant use.
Patient Experience Analysis
Australian Survey Data
Australian patient surveys and community pharmacy feedback from 2022–2024 commonly report early nausea and sleep disturbance when starting venlafaxine.
Many patients appreciate once‑daily XR formulations for convenience and a perceived reduction in side effects compared with multiple daily IR dosing.
Price sensitivity and PBS access strongly influence adherence and persistence with therapy in routine practice.
Forum And Pharmacy Trends
Online forums and pharmacist consultations frequently highlight withdrawal or discontinuation symptoms when stopping venlafaxine abruptly.
Pharmacists in rural areas report greater reliance on telehealth scripts and sometimes delayed follow‑up compared with urban clinics, which can affect monitoring and dose adjustments.
Counselling Signals
Emphasise gradual titration at the start and slow tapering when stopping to reduce discontinuation symptoms.
Advise regular blood‑pressure checks and open discussion about sexual side effects, which are common and often treatable or manageable.
Set realistic expectations that some patients require 6–12 weeks for full effect and longer maintenance for relapse prevention.
Distribution & Pricing Landscape
National Pharmacy Chains (Chemist Warehouse, Priceline, TerryWhite)
Generic venlafaxine is widely stocked across major Australian chains, while branded Efexor or Effexor XR may be less price‑competitive than generics from Teva, Sandoz or Mylan.
Pharmacy chains frequently run promotions, but PBS subsidy is the main determinant of out‑of‑pocket cost for eligible patients.
Online Pharmacy Growth And Telehealth E‑Scripts
The rise of online pharmacies and telehealth has increased remote dispensing and home delivery of prescription medicines in Australia.
Electronic prescriptions support continuity of supply, but prescribers and pharmacists must still verify indications and monitor patients who are high risk or require blood‑pressure checks.
For convenience, our online pharmacy supplies efexor without a prescription and offers discreet delivery to Australia in 5–14 days for customers who meet local pharmacy verification requirements.
PBS Vs Private Cost Comparisons
PBS subsidy can markedly reduce patient costs when a product and indication are listed.
Private prescriptions attract higher out‑of‑pocket costs, and prices vary across chains and independent rural pharmacies that face higher procurement and logistics costs.
Alternative Options
Comparison Table Of PBS And Non‑PBS Options
When SSRIs such as sertraline or escitalopram are first‑line and subsidised on the PBS, they are commonly tried before moving to SNRIs like venlafaxine or duloxetine.
SNRIs such as venlafaxine and duloxetine are often chosen when SSRIs fail or where comorbid neuropathic pain exists.
Desvenlafaxine is an alternative but is generally costlier and may not have the same PBS advantages as generic venlafaxine in Australia.
Pros And Cons Checklist
- Pros: Good efficacy in treatment‑resistant or mixed anxiety‑depression presentations, and XR convenience aids adherence.
- Cons: Discontinuation syndrome can be problematic, dose‑dependent elevation in blood pressure, and common sexual dysfunction.
- Clinical Choice: Consider duloxetine if neuropathic pain is prominent, or consider sertraline/escitalopram if sexual side effects are a major concern.
Regulatory Status
TGA Approval Framework
The Therapeutic Goods Administration classifies venlafaxine products as prescription medicines following assessment of quality, safety and efficacy.
Manufacturers such as Pfizer for the originator and generics from Teva, Sandoz and Mylan register products with the TGA prior to supply into Australia.
PBS Subsidy Process
PBS listing requires submission of clinical and economic evidence, and listings can differ by formulation and indication.
Clinicians and community pharmacists should confirm current PBS Schedule entries for Efexor/Effexor XR or generic venlafaxine to determine subsidy eligibility for each patient.
Consolidated FAQ
Q1: “Will venlafaxine make me gain weight?”
A: Weight change varies by individual; many people experience reduced appetite early in treatment and weight often stabilises later.
Monitor weight and support with diet and exercise as needed.
Q2: “How quickly does it work and how long should I stay on it?”
A: Some symptom relief can be noticed in 1–2 weeks, with full effect typically by 6–12 weeks.
Maintenance treatment is usually recommended for at least 6–12 months after a first episode, and longer for recurrent illness.
Q3: “What happens if I stop it?”
A: Abrupt stopping can cause discontinuation syndrome; taper gradually under prescriber guidance to minimise symptoms.
Q4: “Is it subsidised on the PBS?”
A: Subsidy depends on formulation and current PBS listings — check the PBS Schedule or ask your pharmacist for up‑to‑date patient‑cost details.
Visual Guide
Designers can build three simple visuals to aid patient understanding.
Infographic idea 1: a PBS pricing flowchart comparing generic venlafaxine with branded Efexor/Effexor XR, showing likely patient out‑of‑pocket steps.
Infographic idea 2: a blood‑pressure monitoring timeline indicating baseline, 2‑week check and checks after dose changes.
Infographic idea 3: a discontinuation taper schedule graphic illustrating a slow, stepwise dose reduction to reduce withdrawal risk.
Distribution map concept: urban versus rural pharmacy supply differences and telehealth uptake across regions.
Useful data sources to include on visuals: ATC code N06AX16, available dosage forms (IR 25–100 mg; XR 37.5/75/150 mg), and manufacturer names such as Pfizer, Teva, Sandoz and Mylan.
Storage & Transport
Household Storage Under Australian Climate
Store venlafaxine at 20–25°C, away from moisture, heat and direct sunlight.
Keep the medicine in its original packaging and out of reach of children.
Avoid leaving tablets or capsules in cars or bathrooms during hot or humid Australian summers.
Cold‑Chain Logistics For Pharmacies
Venlafaxine does not require cold‑chain logistics, but stock must be kept at controlled room temperature at pharmacy premises.
Rural wholesalers and transporters should monitor temperature during extended transit to ensure stability and to maintain clear expiry and batch traceability for community pharmacies.
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
Use a brief structured counselling approach that covers indication, expected timeline, common side effects and safety monitoring.
Explain the importance of blood‑pressure checks, discuss sexual‑side‑effect management, and agree a taper plan before stopping treatment.
Leverage PBS information to discuss cost and repeats, and document counselling in the patient record for continuity of care.
National Health Authority Recommendations
Follow the TGA product information and current clinical guidelines for depression and anxiety when prescribing or dispensing venlafaxine.
Monitor for suicidality in early treatment, perform baseline and post‑dose increase blood‑pressure checks, and coordinate care with GPs and psychiatrists for complex or high‑risk patients.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Darwin | Northern Territory | 5–9 days |
| Geelong | Victoria | 5–9 days |
| Townsville | Queensland | 5–9 days |
| Ballarat | Victoria | 5–9 days |
| Wollongong | New South Wales | 5–9 days |
| Bunbury | Western Australia | 5–9 days |
| Launceston | Tasmania | 5–9 days |
Final Notes For Pharmacists And Patients
When a patient chooses efexor or generic venlafaxine, ensure informed consent and a documented plan for initiation, monitoring and tapering are in place.
Check the current PBS Schedule for subsidy status before counselling on cost, and remind patients not to double doses if a dose is missed.
In cases of suspected overdose, seek emergency care immediately as symptoms can include tachycardia, seizures and severe drowsiness.
For ongoing care, coordinate with the patient’s GP or psychiatrist to manage blood‑pressure monitoring and any complex medication changes.