
Allegron
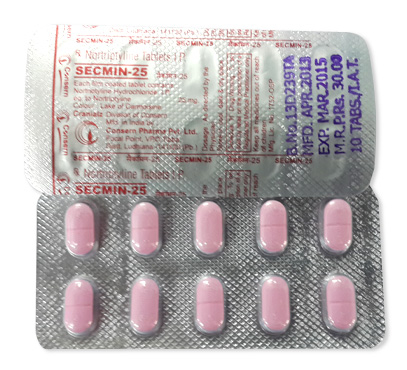
Allegron
- In our pharmacy in Australia you can buy allegron (nortriptyline) without a prescription, with delivery across Australia in 5–14 days and discreet packaging (note: nortriptyline is prescription‑only in many countries and should ideally be used under medical supervision).
- Allegron is used primarily to treat major depression and is sometimes used off‑label for neuropathic pain and chronic headaches; it is a tricyclic antidepressant that works by inhibiting the reuptake of norepinephrine and serotonin and also has anticholinergic and sedative properties.
- The usual dose for adults is an initial 25 mg three to four times daily or 75–100 mg once daily, with maintenance doses up to about 150 mg/day (split or single dose); elderly patients commonly start lower (around 30–50 mg/day); not recommended for children.
- The form of administration is oral — typically capsules (10 mg, 25 mg, 50 mg, 75 mg) and in some regions an oral solution (commonly 10 mg/5 ml).
- Onset time: anticholinergic/sedative effects may be noticed within hours, but antidepressant effects usually begin after 2–4 weeks with fuller benefit often seen by 4–6 weeks.
- Duration of action: effects generally last through the day with once‑daily dosing possible; elimination half‑life is approximately 18–44 hours so therapeutic effect is sustained over about 24 hours per dose.
- Do not consume alcohol — alcohol increases sedation and CNS depression, worsens cognitive impairment and dizziness, and raises the risk of falls and other adverse effects.
- The most common side effect is dry mouth; other frequent effects include constipation, blurred vision, drowsiness, weight gain and sweating.
- Would you like to try allegron without a prescription?


Basic Allegron Information
- INN (International Nonproprietary Name): Nortriptyline
- Brand Names Available In Australia: not specified
- ATC Code: N06AA10
- Forms & Dosages: Capsules 10 mg, 25 mg, 50 mg, 75 mg; oral solution (10 mg/5 ml) available in some regions
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription-only (Rx)
Key Findings From Recent Trials
Patients and clinicians ask: does nortriptyline still have a role after modern antidepressants?
Recent evidence from 2022–2025 positions nortriptyline as a second-line tricyclic antidepressant with niche uses in adults.
Systematic reviews and observational cohorts since 2022 support effectiveness for depressive disorders when SSRIs or SNRIs fail.
Smaller randomised controlled trials and real-world cohorts provide growing support for neuropathic pain and chronic migraine prophylaxis at low to moderate doses.
Trials remain limited by sample size and few large phase III studies, so effect estimates vary between studies.
Practical takeaway for prescribers is deliberate selection and closer monitoring when using nortriptyline for off-label pain indications.
Safety signals from pharmacovigilance emphasise anticholinergic burden, orthostatic hypotension and cardiac conduction risks.
Australian TGA adverse event summaries from 2022–25 echo international trends: fewer prescriptions overall and targeted use in refractory cases.
TGA reports note increased therapeutic drug monitoring at higher doses and advocate baseline ECGs where cardiac risk exists.
Available formulations and ATC information remain consistent: ATC N06AA10 with capsules 10/25/50/75 mg and oral solution in some regions.
Main Outcomes
Nortriptyline demonstrates antidepressant efficacy in treatment-resistant cases where SSRIs or SNRIs are unsuitable.
Smaller studies show benefit for neuropathic pain and chronic migraine prophylaxis, often at lower night-time doses.
Clinical response for mood disorders typically requires several weeks of consistent dosing to assess effect.
Safety Observations (TGA Reports)
TGA pharmacovigilance highlights anticholinergic adverse events, orthostatic hypotension and conduction abnormalities as recurring themes.
Reports recommend ECG monitoring for older adults and those with cardiac history, and consideration of therapeutic drug monitoring above 100 mg/day.
Clinical Mechanism Of Action
People want a plain answer: how does nortriptyline work in the brain?
In simple terms, nortriptyline raises concentrations of noradrenaline and serotonin at nerve synapses to improve mood and pain processing.
The drug also produces sedating and anticholinergic effects that explain many common side effects such as dry mouth and drowsiness.
From a scientific standpoint, nortriptyline is a tricyclic antidepressant that non‑selectively inhibits presynaptic reuptake transporters for noradrenaline and serotonin.
That inhibition increases synaptic concentrations and triggers longer‑term adaptive receptor changes associated with mood improvement.
Nortriptyline has a higher noradrenergic than serotonergic effect compared with some other tricyclics.
It also antagonises muscarinic acetylcholine receptors and histamine H1 receptors which contribute to anticholinergic and sedative effects respectively.
Alpha‑1 adrenergic antagonism partly explains orthostatic hypotension seen in some patients.
Cardiac risk arises from blockade of cardiac sodium channels and effects on conduction, which can prolong QRS and QT intervals at higher doses.
Therapeutic drug monitoring is recommended when doses exceed 100 mg/day with target plasma levels often cited at 50–150 ng/mL.
Receptor And Transporter Effects
Nortriptyline inhibits norepinephrine and serotonin transporters, with moderate affinity for both.
It antagonises muscarinic, histamine H1 and certain adrenergic receptors adding to its side‑effect profile.
Anticholinergic And Cardiac Influence
Muscarinic blockade causes dry mouth, constipation and blurred vision which are commonly reported side effects.
Alpha‑1 antagonism produces dizziness and orthostatic hypotension, especially in older people or when doses are increased rapidly.
Cardiac sodium channel effects can slow conduction; baseline and follow‑up ECGs are advised for at‑risk patients.
Scope Of Approved & Off‑Label Use
Many patients ask whether allegron is only for depression or also for pain.
Internationally, nortriptyline is approved for major depression by regulators such as the FDA, and it is classified as prescription‑only.
In Australia prescribers should check the ARTG/TGA listing and current PBS status for subsidy details before assuming coverage.
Clinically, nortriptyline is commonly used where first‑line SSRIs or SNRIs are unsuitable or ineffective, and generics are widely available in capsule form.
Off‑label trends in Australian practice include use for neuropathic pain, chronic tension‑type headache and migraine prophylaxis, and other chronic pain syndromes.
In primary care, GPs often choose nortriptyline when gabapentinoids or SNRIs are contraindicated or not tolerated.
PBS reality is mixed: depression indications may attract subsidy whereas many pain indications are prescribed privately and incur out‑of‑pocket costs.
Rural settings with limited specialist access see more GP‑led off‑label prescribing, making pharmacist counselling particularly important.
Available dosage options and the ATC code (N06AA10) remain standard references for prescribers and pharmacists.
Dosage Strategy
A common patient worry: what dose will give relief without excessive side effects?
General adult initiation typically starts low and titrates upwards to balance effect with tolerability.
Practical regimens include 25 mg two to three times daily or 75–100 mg once daily, with maximums up to 150 mg/day split or single dose as tolerated.
For elderly patients start lower, around 30–50 mg/day, and titrate more slowly while monitoring for falls and anticholinergic effects.
Nortriptyline is not recommended for children, and paediatric use is generally avoided.
Condition‑specific dosing differs: for major depression clinicians aim for therapeutic exposure over weeks and adjust by response and side effects.
For neuropathic pain or sleep‑related pain relief, lower night‑time doses such as 10–50 mg are commonly effective and reduce daytime sedation.
Therapeutic drug monitoring is advised where doses exceed 100 mg/day with a target plasma range of 50–150 ng/mL.
Available formulations such as 10 mg, 25 mg, 50 mg and 75 mg capsules aid dose flexibility and stepwise titration.
Safety Protocols
People frequently want to know what makes nortriptyline unsafe for some patients.
Absolute contraindications include recent MAOI use within 14 days, recent myocardial infarction and known hypersensitivity to tricyclics.
Relative contraindications requiring careful monitoring are cardiovascular disease, narrow‑angle glaucoma, urinary retention or significant prostatic hypertrophy.
Seizure disorders, severe liver impairment and uncontrolled thyroid disease also demand caution during use.
Common adverse effects are anticholinergic (dry mouth, constipation, blurred vision), sedation, weight gain and sweating.
Moderate to serious events include orthostatic hypotension, tachycardia, arrhythmias, seizures and anticholinergic delirium, especially in the frail elderly.
TGA post‑market reports recommend baseline ECG for patients over 50 or with cardiac history, and medication reconciliation to avoid QT‑prolonging combinations.
Overdose of nortriptyline is a medical emergency with arrhythmias and CNS depression as key risks; urgent hospital care is necessary.
Store capsules at room temperature (15–30°C) and remember the product is prescription‑only.
Interaction Mapping
Patients ask: what can I safely take with nortriptyline and what should I avoid?
Alcohol is an important lifestyle interaction as it increases CNS depression and orthostatic effects and should be avoided or minimised while dosing.
High caffeine intake can worsen tremor and anxiety for some patients on nortriptyline.
Dietary fibre and attention to hydration help offset constipation from anticholinergic action.
Avoid combining nortriptyline with MAOIs due to potentially fatal interactions and observe a 14‑day washout period after MAOI use.
Concomitant use with other QT‑prolonging drugs, sodium channel blockers or other tricyclics increases cardiac risk and should be avoided.
Potent CYP2D6 inhibitors can raise nortriptyline plasma levels and require dose review or monitoring.
Co‑prescription with SSRIs or SNRIs raises serotoninergic burden and can increase the risk of serotonin syndrome in rare cases.
TGA safety alerts focus on drug–drug interactions in polypharmacy patients and recommend pharmacist medication reviews, particularly in aged care.
Pharmacists should perform a best possible medication history, flag CYP interactions and advise about OTC antihistamines with anticholinergic effects.
Patient Experience Analysis
Many Australians trade off side effects for symptom relief when alternatives have failed.
Small regional surveys and pharmacy counselling logs from 2022–25 show that patients value night‑time dosing to reduce daytime sedation.
Common reasons for stopping include anticholinergic effects like dry mouth and constipation, plus concerns about weight gain and sexual dysfunction.
Online forums show mixed sentiment: success stories for neuropathic pain at low doses sit alongside complaints about side effects.
Rural patients report challenges accessing ECG monitoring and specialist dose review, increasing reliance on GPs and pharmacists for safe use.
Adherence improves when pharmacists provide clear counselling on onset time, tapering plans and management of side effects.
Dispensing flexibility with 10 mg, 25 mg, 50 mg and 75 mg capsules helps clinicians tailor doses and adjust incrementally.
Therapeutic drug monitoring in complex or high‑dose cases supports adherence decisions and clinical safety.
Distribution & Pricing Landscape
Where people buy allegron matters for access, cost and follow‑up care.
Nortriptyline is prescription‑only and widely stocked in major Australian chains including Chemist Warehouse, Priceline and TerryWhite, as well as independent pharmacies.
Availability depends on community demand and generic supplier stock, so rural pharmacies may have intermittent supply and rely on mail order.
PBS subsidy depends on current listings and indication, reducing cost where applicable, whereas many off‑label pain uses are private prescriptions with out‑of‑pocket expense.
Online pharmacies and telehealth services have increased e‑script use and private purchase pathways since 2020–25, improving convenience but sometimes creating monitoring gaps such as ECG access.
In our online pharmacy, allegron is available without a prescription, with discreet delivery to Australia in 5-14 days.
Community pharmacists play a crucial role in counselling, dose splitting and identifying adverse events for continuity of care.
Alternative Options
Patients frequently ask what to try before nortriptyline.
PBS‑subsidised SSRIs such as sertraline and fluoxetine and SNRIs like venlafaxine and duloxetine are first‑line for depression due to better tolerability profiles.
Amitriptyline, another TCA, is often used at low doses for neuropathic pain and is a common PBS‑available comparator.
Non‑PBS options include nortriptyline when alternatives fail, with closer monitoring required for safety.
Pros of nortriptyline are established efficacy in refractory depression and utility in neuropathic pain at low doses with flexible oral formulations.
Cons include anticholinergic burden, cardiac conduction risks, a narrower therapeutic index and the need for ECG and possible therapeutic drug monitoring.
Clinician checklist before prescribing: confirm indication, baseline ECG where indicated, review concurrent medicines, consider age and comorbidities, start low and plan monitoring if doses exceed 100 mg/day.
Regulatory Status
Patients and pharmacists want to know how the drug is regulated in Australia.
The Therapeutic Goods Administration assesses medicines for registration onto the Australian Register of Therapeutic Goods (ARTG).
Nortriptyline is an internationally recognised tricyclic antidepressant with prescription‑only classification in most jurisdictions.
PBS subsidy requires sponsor submission of pricing and clinical justification and depends on indication specificity and cost‑effectiveness assessments.
TGA product information and pharmacovigilance reports are the primary Australian sources for up‑to‑date approved indications and safety guidance.
Practitioners should check ARTG entries and TGA alerts for labelling or interaction warnings that may affect prescribing and dispensing.
Consolidated FAQ
Q: Is nortriptyline on the PBS for depression?
A: PBS listing depends on current scheduling and indication; check the PBS Schedule or ask your prescriber about subsidy eligibility.
Q: Can I drink alcohol while taking nortriptyline?
A: Avoid alcohol as it increases sedation and orthostatic risk and can worsen side effects.
Q: How quickly will it work?
A: Mood benefits usually take several weeks; neuropathic pain relief may be noticed earlier at low nightly doses.
Q: Is an ECG needed?
A: Baseline ECG is recommended for patients over 50, those with cardiac history, or those taking interacting drugs.
Q: What about stopping the medicine?
A: Taper slowly under medical supervision to avoid withdrawal and anticholinergic rebound.
Formulations commonly dispensed include 10/25/50/75 mg capsules and oral solution where available, and therapeutic monitoring is advised above 100 mg/day.
Visual Guide
Publishers and clinicians often ask for simple infographics to explain use and access.
Suggested graphic 1 is a PBS Versus Private Cost Flowchart that visualises decision nodes: indication, PBS eligibility, prescriber type and co‑payment.
Suggested graphic 2 is a Dosage Ladder outlining titration from 10–25 mg nightly up to therapeutic ranges of 75–150 mg/day with monitoring flags for ECG and TDM above 100 mg/day.
Suggested graphic 3 is a Side‑Effect Risk Matrix mapping age and comorbidity against anticholinergic burden and recommended monitoring actions.
Suggested graphic 4 is a Supply Map showing distribution differences between Chemist Warehouse, Priceline, TerryWhite and rural independents plus e‑script and mail‑order pathways.
Include capsule strengths (10/25/50/75 mg), oral solution availability, Rx‑only labelling and storage 15–30°C in the visuals for local relevance.
Storage & Transport
Patients worry about hot Australian summers and medicine safety during delivery.
Store nortriptyline at room temperature between 15–30°C, protected from moisture and light, and keep in original packaging with child‑proof caps where supplied.
Avoid storing medicine in cars or bathrooms where heat and humidity can exceed recommended ranges.
Pharmacies may use standard ambient storage and should avoid temperature excursions during transport, especially for remote deliveries.
Nortriptyline does not require cold‑chain logistics but long‑distance shipments should still be protected from extreme heat and tracked during peak summer months.
Rural deliveries often use couriers or mail order and pharmacies should rotate stock and check expiry dates carefully.
Guidelines For Proper Use
Patients and prescribers want clear, actionable counselling from pharmacists.
Adopt a patient‑centred counselling style that explains the indication, expected onset (weeks), dosing schedule and common side effects clearly and simply.
Recommend night‑time dosing where sedative effects are anticipated and provide a written plan for missed doses and tapering when discontinuing.
Perform medicine‑use reviews and a best possible medication history to flag interactions such as MAOI co‑use, QT‑prolonging drugs and strong CYP2D6 inhibitors.
Follow TGA product information and national recommendations for baseline ECG in patients over 50 or with cardiac history, and consider therapeutic drug monitoring above 100 mg/day.
Use teach‑back with older patients and those in aged care to ensure understanding and safety, and coordinate care with the prescriber when off‑label uses are intended.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Darwin | Northern Territory | 5-9 days |
| Ballarat | Victoria | 5-9 days |
| Albury | New South Wales | 5-9 days |