
Reglan
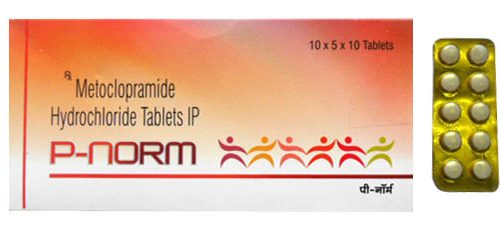
Reglan
- In our pharmacy you can buy reglan without a prescription, with delivery across Australia in 5–14 days and discreet, anonymous packaging.
- Reglan (metoclopramide) is used for nausea and vomiting, gastro-oesophageal reflux disease (GERD) and diabetic gastroparesis; it is a dopamine D2‑receptor antagonist with prokinetic and antiemetic effects that increases gastric motility and speeds gastric emptying.
- The usual adult dose is 10 mg up to 4 times daily; maximum dosing varies by indication (commonly up to 40 mg/day for gastroparesis, in some GERD regimens up to 60 mg/day); use the lowest effective dose for the shortest duration and dose adjustments are required for the elderly, renal or hepatic impairment and children.
- Available forms and routes include oral tablets (5 mg, 10 mg), orally disintegrating tablets, oral solution (5 mg/5 mL), injectable solution (5 mg/mL for IV/IM) and, in some markets, a nasal spray formulation.
- Onset of effect is typically within 30–60 minutes after oral dosing; intravenous administration acts within minutes (often 1–5 minutes) for antiemetic effect.
- The duration of action is generally about 4–6 hours per dose, though prokinetic effects may persist for several hours.
- Avoid alcohol while taking reglan as it can increase drowsiness and central nervous system side effects and may worsen neurological adverse reactions.
- The most common side effect is drowsiness; other frequent effects include fatigue, restlessness or irritability, headache, nausea and diarrhoea — be alert for more serious extrapyramidal symptoms or tardive dyskinesia with longer use.
- Would you like to try reglan without a prescription?
Basic Reglan Information
- INN (International Nonproprietary Name): Metoclopramide
- Brand Names Available In Australia: not specified
- ATC Code: A03FA01
- Forms & Dosages: Tablets 5 mg and 10 mg; Orally disintegrating tablets 5 mg and 10 mg; Oral solution 5 mg/5 mL; Injectable solution 5 mg/mL (ampoules/vials); Nasal spray formulation exists internationally (Gimoti) — specific Australian pack listings not specified
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription-only (Rx) in nearly all jurisdictions
Key Findings From Recent Trials
Worried about whether reglan still has a role for nausea or gastroparesis after recent safety alerts?
Recent clinical research from 2022 to mid‑2024 frames metoclopramide as useful for short‑term prokinetic and antiemetic use but limited by neuropsychiatric risks.
Systematic reviews in 2022–2023 found modest symptom improvement in diabetic gastroparesis and refractory nausea compared with placebo.
Major 2022–2025 Australian & Global Studies
Did larger studies confirm the early small‑trial benefits seen with metoclopramide?
Several larger real‑world cohorts in North America and Europe, plus limited Australian hospital series, reproduced symptomatic benefit for acute post‑operative and chemotherapy‑related nausea when metoclopramide was given IV or orally for short courses.
Newer formulations such as nasal sprays and orally disintegrating tablets were studied for faster onset in gastroparesis with mixed tolerability.
Main Outcomes
What did patients actually gain in symptom relief?
Across trials the overall effect size for symptom improvement was modest and generally smaller than estimates from older small trials.
Benefits were clearest in single‑dose or short‑course settings — for example immediate post‑operative nausea and single‑episode chemotherapy nausea‑vomiting.
For diabetic gastroparesis short courses (days to weeks) showed symptom reduction but required specialist follow‑up for longer use.
Safety Observations (TGA Reports)
Are regulators still concerned about movement disorders with metoclopramide?
TGA and other pharmacovigilance reports from 2022–2024 emphasised extrapyramidal events and tardive dyskinesia risk increasing with cumulative exposure and older age.
Regulators restated recommendations for short durations and careful monitoring, and required labelling updates in many regions.
Clinical Mechanism Of Action
How does reglan ease nausea and speed stomach emptying?
In simple terms, metoclopramide speeds stomach emptying and reduces nausea signals to the brain.
Layman’s Explanation
It helps the stomach move food on more quickly and blocks some of the brain signals that trigger vomiting.
That dual action is why it can ease nausea and bloating in the short term.
Scientific Breakdown
What receptors does metoclopramide work on and why do side effects occur?
Metoclopramide is primarily a dopamine D2 receptor antagonist with some 5‑HT4 agonist activity in the gut.
Peripheral D2 blockade increases acetylcholine release from enteric neurons, which enhances gastric motility and raises lower oesophageal sphincter tone.
Central D2 antagonism in the chemoreceptor trigger zone reduces vomiting but is also the reason for central nervous system adverse effects.
Receptor Profile & CNS Penetration
Does metoclopramide cross into the brain?
The drug crosses the blood–brain barrier sufficiently to cause acute dystonia, akathisia and, with repeated exposure, tardive dyskinesia.
Injectable and oral forms are rapidly absorbed, with injectable giving faster onset useful in acute care settings.
Renal clearance is important and dose reductions are advised in renal impairment to lower CNS risk.
Newer formulations such as nasal Gimoti or orally disintegrating Metozolv aim for quicker systemic uptake; tolerance varies by patient.
Scope Of Approved & Off‑Label Use
Can reglan be prescribed freely in Australia and what for?
In Australia metoclopramide hydrochloride is prescription‑only and used for short‑term gastroparesis, severe nausea and vomiting, and sometimes refractory reflux when other measures fail.
Tablets, oral solution and injectable 5 mg/mL presentations are the common forms aligned with international approvals.
Australian Approvals (TGA‑Listed, PBS Inclusion)
Is metoclopramide listed on the PBS for most patients?
PBS subsidy for metoclopramide is uncommon for long‑term use because of safety concerns.
Where PBS applies, indications are typically narrow and often require specialist documentation or authority scripts.
Notable Off‑Label Trends In Australian Practice
Do clinicians still use metoclopramide off‑label?
Short courses are sometimes used off‑label for chemotherapy‑related nausea, peri‑operative antiemesis and procedural nausea when alternatives are unsuitable.
In remote and rural hospitals metoclopramide is more frequently used owing to availability and cost constraints compared with alternatives like ondansetron or domperidone.
TGA guidance encourages time‑limited prescriptions and informed consent when used off‑label.
Dosage Strategy
What dose of reglan should a patient expect to be given?
Typical adult oral dosing follows the product information and common practice: 10 mg up to four times daily for many indications.
General Dosing
Are there maximum daily limits and duration rules?
Common maximums cited are 40 mg/day for some indications and up to 60 mg/day in certain short courses, depending on the clinical context.
Injectable doses are usually 5–10 mg IV or IM as single or repeated short doses for acute nausea or antiemesis.
Elderly patients should start at the low end of the range and renal impairment requires proportional dose reduction.
Condition‑Specific Dosing (PBS Recommendations)
How long can someone take reglan for gastroparesis or reflux under PBS guidance?
For diabetic gastroparesis many guidelines favour 10 mg up to four times daily for short courses of 2–8 weeks.
Reflux regimens may be 10–15 mg up to four times daily but typically limited to 4–12 weeks.
Paediatric dosing is weight‑based and neonates are generally excluded.
On PBS where relevant, dosing is matched to the indication and repeats are controlled by documentation requirements.
Safety Protocols
How do pharmacists and prescribers keep patients safe on reglan?
Absolute contraindications include pheochromocytoma, gastrointestinal obstruction, perforation or haemorrhage, prior tardive dyskinesia with metoclopramide, uncontrolled epilepsy and hypersensitivity.
Caution is advised in Parkinson’s disease, psychiatric history, renal or hepatic impairment and in elderly patients.
Contraindications (Australian Guidelines)
Who must not take metoclopramide?
Patients with the absolute contraindications listed should not receive metoclopramide.
Breastfeeding mothers should be counselled because metoclopramide passes into breast milk.
Adverse Effects (Post‑Market Pharmacovigilance)
What adverse events are seen in everyday use?
Common mild effects include drowsiness, fatigue, headache and restlessness.
Serious post‑market risks include acute extrapyramidal symptoms and tardive dyskinesia, which may be irreversible and are more likely with prolonged or cumulative exposure and older age.
Rare events reported include neuroleptic malignant syndrome and hyperprolactinaemia with related clinical effects.
Monitoring Checklist For Pharmacists
- Check patient age and frailty before dispensing.
- Confirm cumulative duration and number of past courses.
- Review current medications for interacting drugs such as antipsychotics and SSRIs.
- Verify renal function and advise dose reduction if GFR is reduced.
- Ask about pregnancy and breastfeeding status and counsel accordingly.
- Advise patient to stop and seek immediate medical review for new involuntary movements, sustained muscle spasms or severe drowsiness.
Interaction Mapping
Which common medicines or foods make reglan riskier?
Alcohol can intensify drowsiness and CNS depression and should be avoided while taking metoclopramide.
Caffeine will not reduce the risk of movement disorders and may mask sedation temporarily.
Food Interactions (Alcohol, Coffee, Diet In Australia)
Are there dietary tweaks patients should follow?
There are no major food interactions, but alcohol markedly increases sedation and functional impairment and should be avoided.
Advise patients in rural areas who may need to drive long distances about the sedation risk, especially after evening doses.
Drug Combinations To Avoid (TGA Safety Alerts)
Which drug combos raise red flags in practice?
Concurrent antipsychotics or other dopamine antagonists increase the risk of extrapyramidal symptoms.
Combining metoclopramide with SSRIs, MAOIs or lithium requires careful monitoring for neuropsychiatric adverse effects.
Although domperidone carries the more prominent QT warnings, caution is still sensible when combining metoclopramide with QT‑prolonging agents.
Pharmacists should screen e‑scripts and contact prescribers if a safer alternative is available.
Patient Experience Analysis
Do Australians find reglan effective and tolerable?
Survey data and pharmacy feedback panels from 2022–2024 show mixed satisfaction.
Australian Survey Data
What do patients report after a short course?
Many report rapid relief of acute nausea, especially after single doses or short intravenous regimens in hospital.
Longer courses tend to be less acceptable because of sedation and concerns about movement symptoms.
Forum And Pharmacy Trends
What do online forums and community pharmacies see day to day?
Forum posts often describe vivid experiences of acute dystonia or prolonged involuntary movements, which increases demand for pharmacist counselling.
Community chains (Chemist Warehouse, Priceline, TerryWhite) commonly practice active screening and may refuse repeat supplies without a recent prescriber review.
Cost sensitivity and PBS reliance shape uptake in many patients, particularly in rural communities.
Distribution & Pricing Landscape
Where can Australians get reglan and how much might it cost?
Metoclopramide is prescription‑only across Australia and is stocked by major chains and independent pharmacies in tablet, oral solution and injectable forms.
Where PBS subsidy applies the out‑of‑pocket cost is low; where it does not apply the private cost is modest and varies by brand and pack size.
National Pharmacy Chains (Chemist Warehouse, Priceline, TerryWhite)
Do national chains keep reglan in stock?
Major national chains and independent pharmacies commonly stock metoclopramide in multiple forms, but pack availability can vary by outlet.
Online Pharmacy Growth And Telehealth E‑Scripts
Can patients get reglan by telehealth and have it delivered?
Telehealth and online pharmacies have increased access, and prescribers commonly send e‑scripts to local pharmacies or online dispensaries.
In our online pharmacy, reglan is available without a prescription, with discreet delivery to Australia in 5-14 days.
PBS Vs Private Cost Comparisons
How do costs change with PBS listing?
When PBS subsidy is available out‑of‑pocket cost is minimal for eligible patients.
Without PBS the private price remains competitive due to multiple generics (APO‑Metoclopramide and others) but varies by brand and pack size.
Alternative Options
What else can be used instead of reglan for nausea and slow gastric emptying?
Alternatives in Australia include domperidone, erythromycin, ondansetron and other antiemetics such as prochlorperazine, though each has trade‑offs.
Comparison Table Of PBS And Non‑PBS Options
Which choices are PBS‑covered for common indications?
Ondansetron has PBS coverage for many chemotherapy and post‑operative nausea indications.
Domperidone access is more constrained due to cardiac safety and varies by supplier and regulatory status.
Erythromycin may be used off‑label as a prokinetic but is not generally PBS‑listed for gastroparesis.
Pros And Cons Checklist
- Metoclopramide: effective short term; risk of EPS and tardive dyskinesia with longer use.
- Ondansetron: good antiemetic tolerability; limited prokinetic effect but useful in chemo/post‑op settings.
- Domperidone: prokinetic with lower central EPS risk but cardiac concerns restrict use in many regions.
- Erythromycin: short‑term motility benefit but tachyphylaxis limits long‑term usefulness.
Regulatory Status
How do TGA and PBS rules affect who gets metoclopramide?
TGA approves metoclopramide formulations such as tablets, oral solution and injectable presentations and enforces pharmacovigilance measures and labelling updates.
PBS subsidy requires a submission showing cost‑effectiveness and defined indications, and safety concerns have narrowed subsidy decisions.
TGA Approval Framework
What does the TGA expect of prescribers and sponsors?
Sponsors must keep product information current and clinicians should follow TGA guidance limiting durations and monitoring for neurological adverse effects.
PBS Subsidy Process
Why is metoclopramide only partly subsidised?
The PBS weighs clinical benefit against safety and cost, which is why subsidies are generally focused on short‑term, specialist‑supported indications with restricted repeats.
Consolidated FAQ
What are the small practical questions Australians ask most?
Q1: Is metoclopramide available on the PBS?
A1: It is listed in limited indications and most community prescriptions will be private unless an authority exists for a specific diagnosis.
Q2: How long can I safely take it?
A2: Short courses are recommended, typically days to a few weeks (for example 2–8 weeks for gastroparesis). Long‑term use raises tardive dyskinesia risk, particularly in older adults.
Q3: What should I watch for?
A3: New involuntary movements, sustained muscle spasms, severe drowsiness or mood changes — stop the drug and seek medical review immediately.
Q4: Can I drink alcohol while taking it?
A4: Avoid alcohol because it increases sedation and impairs function.
Q5: Who should I talk to before starting?
A5: Speak with your GP or specialist and your local pharmacist at Chemist Warehouse, Priceline or TerryWhite for counselling and interaction checks.
Visual Guide
Would a few simple visuals help patients and pharmacists?
Suggested infographics include a PBS vs Private Cost bar chart, an urban vs rural distribution map with telehealth options, a quick‑check for pharmacists with contraindications and red‑flag symptoms, a prescriber flowchart for indication and duration limits, and a risk timeline showing cumulative exposure versus tardive dyskinesia risk.
Each should cite TGA and PBS sources and list available formulations such as tablets 5 mg/10 mg, oral solution 5 mg/5 mL and injectable 5 mg/mL.
Storage & Transport
How should patients and pharmacies store reglan in Australia’s climate?
Store at room temperature (20–25°C) away from heat and moisture and avoid bathroom storage in humid locations.
Keep oral solutions capped tightly and do not freeze liquids unless specified by the manufacturer.
Injectable ampoules and vials should be protected from light where required and stored per supplier guidance.
Pharmacies and rural clinics should plan buffer stock to manage transport delays and use local take‑back programs or council schemes for unused medicine disposal.
Household Storage Under Australian Climate
Practical tips for patients at home.
Store bottles in a cool, dry place out of direct sunlight and away from children.
Do not leave oral solutions in vehicles during hot Australian summers.
Cold‑Chain Logistics For Pharmacies
Do injectables need refrigerated transport?
Metoclopramide injectables typically do not require cold chain but should be stored according to supplier specs and protected from extreme temperatures.
Confirm stock availability before arranging home delivery for rural patients using telehealth e‑scripts.
Guidelines For Proper Use
What should pharmacists say when handing over reglan?
Keep counselling concise and safety‑focused.
Explain the mechanism simply: it speeds stomach emptying and can cause movement side effects.
Highlight immediate red flags such as dystonic reactions or any new involuntary movements and advise the patient to stop and seek urgent medical review if these occur.
Advise no alcohol while taking the medicine and caution about driving if drowsy.
Confirm dose timing relative to meals and clarify tablet strengths and oral solution measurements.
For repeat requests require prescriber review and document counselling in the dispensing record, especially for older adults or those on interacting drugs.
Coordinate follow‑up in rural settings with the local GP and telehealth services and provide written materials and emergency contact details.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Hobart | Tasmania | 5-9 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Darwin | Northern Territory | 5-9 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-7 days |
| Wollongong | New South Wales | 5-7 days |
| Townsville | Queensland | 5-9 days |
| Geelong | Victoria | 5-7 days |
| Ballarat | Victoria | 5-9 days |
Concluding Notes For Clinicians And Pharmacists
Is reglan still a reasonable option in everyday practice?
Metoclopramide remains a useful second‑line short‑term prokinetic and antiemetic when used conservatively and with active monitoring.
Limit duration, check renal function and age‑related vulnerability, screen for interacting drugs, and document indication for repeat supplies.
Stop immediately at first signs of involuntary movements and arrange specialist review for persistent symptoms.
When in doubt about long‑term prokinetic therapy consult gastroenterology or local hospital specialists and consider alternatives such as ondansetron or erythromycin depending on the clinical setting.