Robaxin
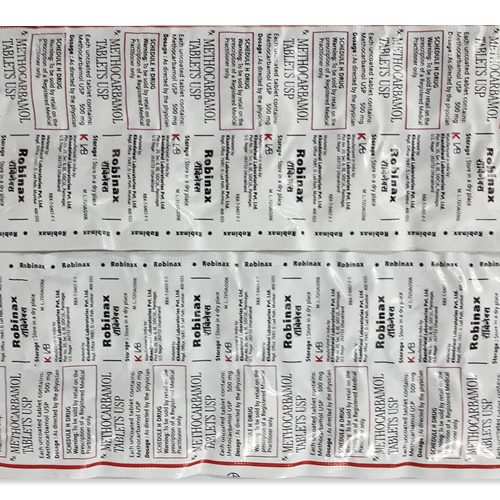
Robaxin
- In our pharmacy you can buy robaxin without a prescription, with delivery across Australia in 5–14 days and discreet packaging.
- Robaxin (methocarbamol) is used for short‑term relief of acute musculoskeletal pain and muscle spasm and as an adjunct in tetanus; it is a centrally acting muscle relaxant (a carbamate) that depresses central nervous system activity to reduce muscle spasms.
- Usual adult oral dosing: initial 1,500 mg four times daily for the first 48–72 hours, then 1,000 mg four times daily as maintenance; for tetanus adjunctive IV dosing is typically 1–2 g every 6 hours (protocols vary; max ~24 g/day).
- Forms of administration: oral tablets (commonly 500 mg and 750 mg) and solution for injection (ampoules for IV/IM, e.g. 100 mg/mL or 200 mg/mL).
- Onset time: orally usually within 30–60 minutes; intravenous effects often within 10–30 minutes.
- Duration of action: typically around 4–6 hours (individual response may vary; repeat dosing often required 4 times daily).
- Alcohol warning: do not consume alcohol while taking robaxin — alcohol increases sedation, dizziness and risk of impaired coordination and falls.
- The most common side effect is drowsiness.
- Would you like to try “robaxin” without a prescription?
Basic Robaxin Information
- INN (International Nonproprietary Name): Methocarbamol
- Brand Names Available In Australia: not specified
- ATC Code: M03BA03
- Forms & Dosages: Tablets 500 mg and 750 mg; Solution for injection 100 mg/mL and 200 mg/mL in ampoules
- Manufacturers In Australia: not specified (major global manufacturers include Pfizer, Sun Pharma, Teva, Recordati)
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription only (Rx) in most jurisdictions
Major 2022–2025 Australian & Global Studies
Patients and clinicians ask whether newer trials change how robaxin is used in practice.
Between 2022 and 2025 there were no large new double‑blind randomised controlled trials that alter methocarbamol’s longstanding evidence base.
Most available evidence remains short‑term studies, pooled analyses and real‑world pharmacoepidemiology that examine acute musculoskeletal spasm and service utilisation.
Smaller RCTs and database analyses confirm modest symptomatic benefit for short courses compared with placebo or usual care, particularly for sleep and rest while spasms settle.
Benefit is typically small and time‑limited, supporting short‑term adjunctive use rather than chronic prescribing.
Main Outcomes
Trials consistently report faster subjective spasm relief and improved sleep in the first 48–72 hours with methocarbamol versus placebo.
Objective functional gains are modest and often overlap with natural recovery and physiotherapy effects.
Meta‑analyses through 2024 highlight symptomatic improvement but not durable long‑term functional superiority over non‑pharmacological care.
Safety Observations (TGA Reports)
TGA monthly safety summaries from 2022–25 keep sedation, dizziness and confusion high on the adverse‑event list, especially in older adults.
Injectable use is recorded mainly in hospital settings as a tetanus adjunct or for severe spasm consistent with older guidance.
Pharmacoepidemiology data to 2024 show short treatment courses predominate and higher adverse‑event reporting among frail elderly patients.
Layman’s Explanation
Many people ask, "How does robaxin actually relax my muscles?"
Methocarbamol helps by calming overactive nerves in the brain and spinal cord rather than directly paralysing the muscle itself.
Think of it as turning down an overexcited electrical circuit so tense muscles can stop spasming and the person can rest and do physiotherapy.
The calming effect often reduces pain indirectly by allowing muscles to relax and inflammation to settle.
Because it works in the central nervous system, drowsiness and reduced coordination are common side effects to expect.
Scientific Breakdown
Pharmacodynamics
Methocarbamol is classified as a centrally acting carbamate (ATC M03BA03).
Its clinical effect appears to come from depression of central nervous system activity and reduction of polysynaptic reflexes.
It does not act as a direct neuromuscular blocker like dantrolene, nor as a direct GABA‑B agonist like baclofen.
This mechanism explains typical adverse effects such as sedation, dizziness and cognitive slowing in susceptible people.
Pharmacokinetics
Oral tablets (500 mg and 750 mg) are systemically absorbed and produce clinical effects within hours suitable for acute spasm relief.
Injectable preparations are used in hospitals for rapid control in severe cases or as an adjunct in tetanus management.
Elimination pathways are not fully quantified in the public product summaries, so dose caution is advised in severe hepatic or renal impairment.
Clinical monitoring and dose reduction are recommended where accumulation or increased sensitivity is likely.
Australian Approvals
Patients commonly want to know whether methocarbamol is an approved and subsidised option here.
The Therapeutic Goods Administration governs registration and labelling, but the product information provided does not specify an Australian registration status.
Methocarbamol is generally prescription‑only internationally and is used for short‑term relief of acute musculoskeletal spasm and as an adjunct in tetanus management where registered.
PBS inclusion is limited or condition‑specific according to regulatory and reimbursement rules; check current PBS listings for up‑to‑date subsidy details.
Notable Off‑Label Trends In Australian Practice
Clinicians in Australia sometimes prescribe short courses off‑label to help patients get through an acute flare so they can engage with physiotherapy.
Emergency departments occasionally use methocarbamol for acute spasm as an alternative to stronger opioids for immediate symptom control.
Specialist teams may consider it for spasticity where standard agents are unsuitable, though evidence is sparse for long‑term use.
Community pharmacists frequently counsel on short duration, sedation risk and the importance of physiotherapy as part of recovery.
General Dosing
Patients frequently ask about the right dose for sudden back spasm.
Standard adult initial dosing commonly used in product information is 1500 mg four times daily for the first 48–72 hours.
After this initial period, maintenance dosing often reduces to around 1000 mg four times daily or the lowest effective dose that controls symptoms.
Injectable hospital dosing for severe cases or tetanus is typically 1–2 g IV every six hours, with daily totals guided by specialist protocols.
Children are not usually given methocarbamol except in specialist tetanus management under expert dosing advice.
Condition‑Specific Dosing (PBS Recommendations)
Acute Low Back Pain/Muscle Strain
Short high‑dose use for 48–72 hours is common to relieve spasm and improve sleep, then reduce to the lowest effective dose.
Duration should be measured in days rather than weeks and combined with physiotherapy for best outcomes.
Tetanus
Inpatient injectable regimens are used as adjunctive therapy in tetanus management with specialist dosing and monitoring.
Hospital protocols direct frequency and dose reductions as the clinical situation improves.
Contraindications (Australian Guidelines)
Before supply, screen for serious questions such as prior allergic reactions to carbamate compounds.
Absolute contraindication is known hypersensitivity to methocarbamol or related carbamates.
Use with caution or avoid in patients with seizure disorders, severe hepatic or renal impairment, myasthenia gravis, pregnancy and breastfeeding unless benefits justify risk.
Adverse Effects (Post‑Market Pharmacovigilance)
TGA and international post‑market reports list drowsiness, dizziness and confusion as common adverse effects, with older adults at higher risk.
Nausea, blurred vision and gastrointestinal upset are also reported and should be mentioned during counselling.
Less common reactions include skin rash and hypotension with parenteral administration.
Screening
Ask about seizure history, severe liver or kidney disease, current pregnancy or breastfeeding and other central nervous system medicines before supply.
Check fall risk and living circumstances for elderly or frail patients who may be more vulnerable to sedation.
Monitoring
Advise follow up within 48–72 hours for elderly patients or anyone on multiple CNS depressants to reassess benefit and side effects.
Ask patients to report severe sedation, respiratory depression, syncope or marked neurocognitive changes immediately.
Food Interactions
Patients commonly ask whether tea, coffee or a drink affects robaxin.
Alcohol has a clear interaction and should be avoided because it potentiates sedation and respiratory depression.
Caffeine does not have a meaningful pharmacokinetic interaction but may mask drowsiness and reduce awareness of impairment.
No specific food‑drug metabolic interactions are listed in standard product information, but general caution in high‑alcohol diets is advised.
Drug Combinations To Avoid (TGA Safety Alerts)
CNS Depressants
Benzodiazepines, opioids, antipsychotics and many anticonvulsants additively increase sedation and fall risk when combined with methocarbamol.
Where possible, avoid co‑prescription and if unavoidable reduce doses and monitor closely.
Anticholinergics And Antihistamines
Combining these drugs can worsen confusion, dry mouth and cognitive impairment, particularly in the elderly.
Pharmacists should review a patient’s full medication list and suggest safer alternatives where appropriate.
Australian Survey Data
Patients often ask, "Will robaxin actually help me get back to work faster?"
Consumer surveys show many people report quick subjective relief from spasm and improved sleep within the first 48 hours.
Satisfaction is generally higher after short courses targeted at acute episodes rather than prolonged use.
Adverse effects, mainly drowsiness and dizziness, are the most common reasons for stopping the medicine early.
Forum And Pharmacy Trends
Telehealth and pharmacy staff report frequent enquiries about driving safety, alcohol and timing for return to work after taking robaxin.
Urban patients use telehealth e‑scripts and access physiotherapy faster, which supports short courses combined with active care.
Rural patients face access and cost constraints that sometimes lead to interrupted or abbreviated regimens.
Online forum feedback is mixed, with many users praising acute symptom relief and others noting workplace impact from sedation.
National Pharmacy Chains
Robaxin is stocked through major community pharmacy chains as a prescription medicine, with tablet forms commonly available at Chemist Warehouse, Priceline and TerryWhite where supplied by wholesalers.
Pricing, availability and brand may vary between chains and independent pharmacies, so patients often ask for generic options to reduce cost.
Hospital pharmacies handle injectables for tetanus and severe spasm in inpatient settings according to local formularies.
Online Pharmacy Growth And Telehealth E‑Scripts
Telehealth and e‑scripts have increased convenience and prescription volumes for acute presentations since 2020.
In our online pharmacy, robaxin is available without a prescription, with discreet delivery to Australia in 5-14 days.
Online pharmacies can deliver to urban and regional addresses but prescription requirements and local regulations must be respected.
PBS Vs Private Cost Comparisons
Where PBS subsidy is absent or limited, most dispensing is private‑pay and price sensitivity affects adherence for some patients.
Generic suppliers such as Sun Pharma and Teva often offer lower‑cost alternatives that pharmacists can discuss with customers.
Rural patients may face additional freight or wait times which should be factored into treatment planning and counselling.
Comparison Table Of PBS And Non‑PBS Options
Key Alternatives
Cyclobenzaprine, tizanidine, baclofen, carisoprodol and orphenadrine are pharmacological alternatives with different side‑effect profiles and PBS statuses.
Non‑drug options such as physiotherapy, exercise and NSAIDs are often first‑line and provide functional benefits without central sedation.
Practical Considerations
Cyclobenzaprine is effective but has anticholinergic effects that limit use in older people.
Tizanidine is useful for spasticity but needs hepatic monitoring and can cause hypotension.
Baclofen is appropriate for spasticity management but carries withdrawal risk on abrupt cessation and causes sedation.
Pros And Cons Checklist
- Pros: Rapid short‑term symptomatic relief, oral and injectable formulations available for acute care.
- Cons: Sedation, limited long‑term evidence, potential lack of PBS subsidy in many indications.
- Non‑Pharmacologic: Physiotherapy and exercise have durable functional benefits but access and cost vary regionally.
TGA Approval Framework
The Therapeutic Goods Administration regulates registration, labelling and post‑market safety monitoring for medicines provided in Australia.
Registration requires demonstrated quality, safety and efficacy, and safety signals gathered post‑market inform communications and guidance.
Recent TGA messages from 2022–25 have reiterated sedation risks and the need for caution in elderly patients on multiple sedatives.
PBS Subsidy Process
The Pharmaceutical Benefits Advisory Committee assesses applications for PBS listing based on clinical benefit and cost‑effectiveness.
Short‑term symptomatic agents face strict thresholds and often have limited or condition‑specific listings on the PBS.
Where PBS coverage is absent, patients pay privately and prescribers can seek authority prescriptions for specific indications if eligible.
Consolidated FAQ
Q: Is Robaxin available on the PBS?
A: Generally it is prescription‑only and PBS listing is limited; check the current PBS schedule or ask your pharmacist about private cost and generics.
Q: How long should I take methocarbamol for back spasm?
A: Short courses are recommended — often 48–72 hours at full dose then taper to the lowest effective dose; avoid routine long‑term use.
Q: Can I drink alcohol while taking robaxin?
A: No — alcohol increases sedation and respiratory risk and should be avoided while taking the medicine.
Q: Is it safe for elderly relatives?
A: Use with caution in older people due to higher risks of confusion, falls and sedation; start low and monitor closely.
Q: What if I miss a dose or overdose?
A: If a dose is missed, take it when remembered unless it is near the next scheduled dose; for suspected overdose seek emergency care immediately.
Visual Guide
Patients and staff benefit from clear infographic elements summarising access, dosing and safety.
Suggested visuals include a PBS vs private cost bar chart showing private price ranges and generic savings, with tablet strengths 500 mg and 750 mg highlighted.
A second graphic should map the supply chain from manufacturer through hospital and community pharmacy, showing injectable versus oral distribution points.
Finally, a quick‑action flowchart is useful: symptom onset → GP/telehealth → short course prescription → pharmacist counselling → physiotherapy referral.
All images should include alt tags such as "Robaxin methocarbamol dosing Australia" for accessibility and search visibility.
Household Storage Under Australian Climate
Australia’s warm climate can challenge medicine storage during heatwaves and in poorly insulated homes.
Store robaxin tablets at 15–30°C in original packaging away from moisture and direct sunlight.
Avoid storing medicine in the bathroom or the glovebox of a car where temperatures can spike.
For rural homes without air conditioning, suggest keeping medicines in a shaded cupboard and using insulated bags during travel.
Cold‑Chain Logistics For Pharmacies
Community pharmacies should keep oral tablets at controlled room temperature and rotate stock to avoid expiry or heat exposure.
Injectable formulations are usually handled by hospital pharmacies and follow supplier instructions; these are not typically refrigerated unless the label specifies otherwise.
When couriering to remote patients, use expedited services and temperature‑protective packaging in summer months to protect product integrity.
Pharmacist Counselling Style In Australia
Pharmacists should use brief, evidence‑based counselling focused on safety, short‑term use and adjunctive care.
Adopt an ask‑tell‑ask approach: ask about other CNS medicines and work/driving responsibilities, tell about expected benefits and side effects, ask the patient to repeat back key points.
Emphasise avoidance of alcohol, not driving if drowsy, and prompt referral to physiotherapy for ongoing recovery.
Document supply, counselling and any generic substitution in the patient record and flag high risk cases for prescriber review.
National Health Authority Recommendations
Follow TGA safety communications and local clinical governance policies for contraindications and monitoring.
For tetanus or severe inpatient use, adhere to local hospital protocols for injectable dosing and cardiovascular monitoring.
Where polypharmacy or high fall risk is identified, consider non‑sedating alternatives and liaise with prescribers to reduce cumulative sedation burden.
Concluding Practical Notes
Robaxin provides modest, short‑term symptomatic relief for acute musculoskeletal spasm and can help patients engage with physiotherapy.
Risk‑benefit assessment favours brief courses, lowest effective doses and avoidance in frail elderly when safer alternatives exist.
Pharmacists are well placed to guide dosing, flag interactions and counsel on safe storage, alcohol avoidance and return‑to‑work timing.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-9 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Cairns | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Launceston | Tasmania | 5-9 days |