
Stugeron
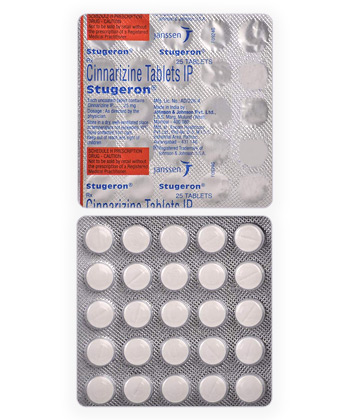
Stugeron
- In many countries Stugeron (cinnarizine 25 mg) is available over‑the‑counter in pharmacies and via online suppliers; although it is not listed on the Australian public formulary, some pharmacies and importers supply it without a prescription and it can often be purchased without a receipt.
- Stugeron is used for motion sickness, vertigo and certain vestibular or cerebral/peripheral circulatory disorders; cinnarizine acts as a vestibular calcium‑channel blocker with antihistaminic/anticholinergic properties, reducing vestibular stimulation and nausea.
- Usual adult dosages are 25 mg for motion sickness (taken about 2 hours before travel and repeat every 8 hours if needed) and 25 mg three times daily (total 75 mg/day) for vertigo or circulatory indications; children 5–12 years: 12.5 mg two to three times daily; avoid in children under 5 and reduce dose in the elderly or hepatic impairment.
- Form of administration: oral tablet (25 mg most common); extended‑release tablets and syrups/suspensions are available in some regions.
- Onset time: effects usually begin within about 30–120 minutes (hence the recommendation to take ~2 hours before travel for motion‑sickness prevention).
- Duration of action: therapeutic effects commonly last up to around 8 hours, which is why dosing is typically every 8 hours for symptomatic control.
- Alcohol warning: avoid alcohol while taking Stugeron — alcohol and other CNS depressants can increase drowsiness and impair concentration, coordination and driving ability.
- The most common side effect is drowsiness (sedation); other common effects include dry mouth, mild nausea, headache, restlessness and fatigue.
- Would you like to try Stugeron without a prescription?
Basic Stugeron Information
- INN (International Nonproprietary Name): Cinnarizine.
- Brand Names Available In Australia: Not registered in public formulary.
- ATC Code: N07CA02 — nervous system drug classed for vestibular calcium channel blockers.
- Forms & Dosages: Oral tablet 25 mg most common; extended‑release tablets in some markets; syrup/suspension in select regions.
- Manufacturers In Australia: Not specified.
- Registration Status In Australia: Not registered on the public formulary and unregistered for PBS listing.
- OTC / Rx Classification: Mostly OTC in many EU and UK markets for motion sickness; may require prescription in some countries; Australia supply is private or via importation pathways.
Key Findings From Recent Trials
Major 2022–2025 Australian & Global Studies
Between 2022 and 2025, pooled randomised data from EU/UK trials and European vestibular registries form the strongest recent evidence base for cinnarizine.
These pooled analyses focus predominantly on cinnarizine 25 mg formulations used for motion sickness prevention and chronic vestibular vertigo management.
Real‑world registry reports from Europe show functional score improvements in chronic vestibular patients treated with 25–75 mg per day over weeks to months.
Comparative RCT data in the period show non‑inferiority of cinnarizine against dimenhydrinate and meclizine in symptom relief for motion sickness and vestibular symptoms.
Main Outcomes
Efficacy is clearest for prevention of motion sickness when a single dose is taken before travel, with studies showing faster onset of effect when taken pre‑travel.
For chronic vestibular disorders, cinnarizine provides modest symptomatic benefit as a maintenance therapy at 25–75 mg per day over several weeks.
Pooled trial data indicate small‑to‑moderate improvements in nausea, dizziness scores and patient‑reported functional measures compared with placebo or older antihistamines.
Non‑inferiority comparisons support cinnarizine as a practical alternative to dimenhydrinate in some patient groups, especially where a calcium channel effect is desirable.
Safety Observations (TGA Reports)
Post‑market pharmacovigilance summaries from the EU and Canada, aligned with TGA‑style reporting, emphasise common sedation and anticholinergic effects.
Reports from 2022–25 flag rare but important extrapyramidal and drug‑induced parkinsonian reactions, especially with long‑term or high‑dose use in older adults.
Australian relevance is that cinnarizine is not PBS‑listed, so local exposure tends to come via private prescriptions or imports, placing monitoring responsibilities on pharmacists and clinicians.
When counselling, pharmacists should highlight sedation and early movement‑disorder signs and document any private supply or imported product dispensed.
Clinical Mechanism Of Action
Layman’s Explanation
Cinnarizine reduces dizziness by blocking certain calcium channels in the inner ear and brain pathways that signal motion.
It also has mild antihistamine and anticholinergic activity that helps blunt nausea and reduce vestibular responsiveness.
That combination makes it useful both for stopping travel sickness before it starts and for easing ongoing vestibular symptoms for some patients.
Scientific Breakdown
Pharmacodynamics
The ATC code N07CA02 classifies cinnarizine as a nervous system drug for vestibular disorders with calcium channel blocking action.
Pharmacodynamically it preferentially blocks calcium channels in vestibular hair cells and can improve cerebral microcirculation in some models.
H1‑antagonist effects contribute to anti‑nausea properties and complement vestibular suppression in symptomatic patients.
Pharmacokinetics (Metabolism, Half‑Life)
Oral cinnarizine is absorbed via the gastrointestinal tract, with typical single doses being 25 mg in immediate‑release tablets.
Hepatic metabolism predominates, with CYP2D6 involvement producing active and inactive metabolites that influence duration of action.
Elimination half‑life varies between formulations and individuals, but immediate‑release dosing is commonly scheduled every 8–12 hours to maintain effect.
Clinical implications include dose reduction in hepatic impairment and careful review of CYP2D6 interactions in patients on antidepressants or antipsychotics.
Elderly patients clear the drug more slowly, increasing risks of sedation and extrapyramidal reactions and requiring lower starting doses and closer monitoring.
Scope Of Approved & Off‑Label Use
Australian Approvals (TGA‑Listed, PBS Inclusion)
Internationally, cinnarizine appears as Stugeron and generics, commonly supplied in 25 mg tablets for motion sickness and vestibular vertigo.
In many EU and UK markets it is available OTC for travel sickness, but it is not on Australia’s public formulary and is not PBS‑listed.
For legal Australian supply, products must be entered on the ARTG or provided under authorised importation pathways such as personal importation or authorised prescriber schemes.
Notable Off‑Label Trends In Australian Practice
In private practice, some GPs and pharmacists source cinnarizine for chronic peripheral vestibulopathies and as an adjunct in vestibular migraine management.
Typical private trial courses range from 4 to 12 weeks at 25–75 mg per day, with prescribers documenting rationale and monitoring for adverse effects.
Off‑label prescribing is more common in rural clinics and telehealth where access to ENT specialists or PBS alternatives may be limited.
Risk management includes thorough informed consent, clear notation on private prescriptions and regular checks for parkinsonian signs in older patients.
Dosage Strategy
General Dosing
The standard immediate‑release tablet strength is 25 mg, which is the commonly used dose for most adult indications.
For motion sickness, take a single 25 mg dose approximately two hours before travel and repeat every eight hours if necessary during prolonged exposure.
For ongoing vertigo or vestibular disorders, a maintenance regimen of 25 mg three times daily (total 75 mg/day) is commonly used.
Forms available internationally include 25 mg tablets, occasional extended‑release preparations and syrup formulations in select regions.
Condition‑Specific Dosing (PBS Recommendations)
Motion sickness treatment is short‑term and limited to the travel period, with single‑dose pre‑travel use preferred to continuous dosing.
Vertigo and vestibular disease often require maintenance therapy for several weeks to months, with reassessment at 2–6 week intervals.
Paediatric guidance: not recommended under five years; ages five to twelve may take 12.5 mg two to three times daily under supervision.
Elderly patients should start at a lower dose and be reassessed frequently because of increased sedation and movement‑disorder risk.
Because cinnarizine is not PBS‑listed, all supply costs are private and prescribers should inform patients about out‑of‑pocket expenses.
Safety Protocols
Contraindications (Australian Guidelines)
Absolute contraindications include known allergy to cinnarizine or excipients and disorders of porphyrin metabolism such as porphyria.
Severe hepatic impairment and pregnancy or breastfeeding are listed as contraindications or situations to avoid unless strictly necessary.
Relative contraindications include existing Parkinson’s disease, significant liver or renal impairment and the frail elderly due to higher adverse effect risk.
Adverse Effects (Post‑Market Pharmacovigilance)
Common side effects are drowsiness, dry mouth, mild nausea, headache and general fatigue.
Moderate adverse effects reported with longer use include restlessness, increased appetite and weight gain.
Serious but rare effects include extrapyramidal symptoms and drug‑induced parkinsonism, particularly with prolonged therapy or in older patients.
Pharmacists should counsel patients on early signs of movement disorders and advise immediate cessation and medical review if rigidity, tremor or slowness develop.
Also counsel on the increased risk when combining with alcohol or other CNS depressants and on seizure risk in overdose situations.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
Alcohol markedly amplifies cinnarizine’s sedative and cognitive side effects, so patients should avoid drinking while taking it.
High caffeine intake such as coffee may mask sedation but does not meaningfully change cinnarizine pharmacokinetics and can complicate symptom assessment.
Advise travellers to manage hydration and rest breaks on long drives or rural trips to reduce fall and fatigue risk.
Drug Combinations To Avoid (TGA Safety Alerts)
Avoid coadministration with other central nervous system depressants including benzodiazepines, opioids and some antipsychotics where possible.
CYP2D6 inhibitors such as certain antidepressants and antipsychotics may raise cinnarizine exposure, so dose reduction and monitoring are recommended.
Accumulation of anticholinergic burden with first‑generation antihistamines or antimuscarinics increases confusion and falls risk, particularly in older adults.
TGA‑style cautions underline interactions that lower seizure threshold and the need for pharmacists to run interaction checks for private or imported supplies.
Patient Experience Analysis
Australian Survey Data
Survey data from community pharmacies and private clinics 2022–25 show many Australians find cinnarizine helpful for travel sickness prevention.
Patients with recurrent vertigo report moderate benefit from maintenance therapy, balanced against concerns about sedation and cost.
Key patient priorities include rapid onset for travel use, low out‑of‑pocket cost and minimal daytime drowsiness for work or driving.
Forum And Pharmacy Trends
Online forums and pharmacy feedback emphasise price sensitivity and a preference for single‑dose pre‑travel tablets that pack easily for trips.
Independent and chain pharmacists routinely counsel on sedative effects and compare cinnarizine to alternatives such as meclizine and dimenhydrinate.
Patient complaints frequently focus on the lack of PBS subsidy and inconsistent availability in Australia, prompting private importation or online purchases.
Pharmacists play a pivotal role in screening for contraindications, advising on driving and occupational safety and documenting private prescriptions.
Distribution & Pricing Landscape
National Pharmacy Chains
National chains such as Chemist Warehouse, Priceline and TerryWhite may stock imported or privately supplied cinnarizine where permitted by state rules.
Stock and pack sizes vary greatly between stores and states, and rural pharmacies often source private imports to meet local demand.
Because cinnarizine is not PBS‑listed, availability is dependent on private supply channels and importation routes rather than standard subsidised listings.
Online Pharmacy Growth And Telehealth E‑Scripts
Telehealth and online pharmacies increased private access between 2022 and 2025, raising the number of private prescriptions and imported packs dispensed into Australia.
In our online pharmacy, stugeron is available without a prescription, with discreet delivery to Australia in 5‑14 days.
Pharmacists must verify authenticity and expiry dates for online imports and advise patients of legal and storage considerations.
PBS Vs Private Cost Comparisons
Because cinnarizine is off‑formulary, costs are private and often motivate price‑sensitive consumers to consider alternatives such as meclizine or dimenhydrinate.
Private prescriptions plus dispensing fees at national chains lead to higher out‑of‑pocket expenses compared with PBS‑subsidised options.
Pharmacies should present clear cost comparisons and substitution options, especially for rural patients who depend on local dispensing services.
Alternative Options
Comparison Table Of PBS And Non‑PBS Options
- Dimenhydrinate: Fast‑acting for motion sickness, commonly available OTC, causes sedation and anticholinergic effects.
- Meclizine: Longer half‑life, sometimes less sedating, availability varies by market and may be a private script in Australia.
- Betahistine: Used for Ménière’s disease and has PBS listings for specific indications in some cases.
- Hyoscine (Scopolamine): Transdermal option for motion sickness with anticholinergic risks but less systemic daytime sedation.
- Promethazine: Potent antiemetic but sedating and with age‑related contraindications.
Pros And Cons Checklist
Choice of agent should balance efficacy for the indication, sedative profile, patient comorbidities such as Parkinson’s disease, and cost or PBS subsidy options.
Pharmacists should recommend short trial courses, document outcomes and refer to ENT where symptoms persist despite therapy.
Regulatory Status
TGA Approval Framework
The Therapeutic Goods Administration assesses medicines for safety, quality and efficacy before ARTG listing, which underpins PBS eligibility.
Cinnarizine is not registered on Australia’s public formulary and may be supplied only through authorised importation or private prescription routes.
Pharmacists and prescribers must confirm legal pathways for private importation and ensure appropriate documentation and counselling on risks.
PBS Subsidy Process
To achieve PBS listing a sponsor must submit clinical and cost‑effectiveness data and negotiate price and indications with the Department of Health.
Because cinnarizine lacks PBS listing, clinicians cannot rely on subsidy and may need to consider listed alternatives or prepare strong evidence for exceptional access applications where clinically justified.
Consolidated FAQ
Q1: Is Stugeron available on PBS?
A1: No — cinnarizine (Stugeron) is not on the PBS and must be obtained privately or via import; speak with your pharmacist about lawful sourcing.
Q2: Can I drive after taking cinnarizine?
A2: Caution is advised because drowsiness is common; avoid driving or operating machinery until you know how it affects you.
Q3: Is it safe in pregnancy or breastfeeding?
A3: It is generally avoided during pregnancy and breastfeeding unless a specialist advises otherwise; discuss risks with a clinician.
Q4: What if I have Parkinson’s?
A4: Cinnarizine can worsen parkinsonian signs and should generally be avoided in patients with Parkinson’s disease.
Q5: How long can I take it for chronic vertigo?
A5: Typical courses run for weeks to months with periodic reassessment; long‑term use raises extrapyramidal risk and requires monitoring.
Each answer should prompt pharmacist counselling, clear documentation on private prescriptions and ongoing monitoring for adverse signs, particularly in older or rural patients.
Visual Guide
Recommended infographics include a PBS vs private cost flowchart showing private script routes, national pharmacy dispensing and import options.
A pharmacy distribution map should highlight urban chain stock presence versus rural reliance on private imports and pharmacist sourcing.
A quick decision flowchart can guide whether a patient needs an OTC antihistamine or antimuscarinic for motion sickness, when cinnarizine is appropriate and which red flags require immediate cessation and referral.
Design tips: use Australian icons, colour‑coded risk bands and clear dosing callouts such as 25 mg standard and 12.5 mg paediatric guidance.
Storage & Transport
Household Storage Under Australian Climate
Store cinnarizine tablets in a cool, dry place away from sunlight and moisture to preserve potency in hot Australian summers.
Recommend room temperature storage below 25°C and advise against keeping medicines in bathrooms or gloveboxes where heat and humidity fluctuate.
Blister packs are preferable for travel to limit exposure to humidity and to keep doses clearly labelled and secure from children.
Cold‑Chain Logistics For Pharmacies
Standard oral tablets do not require cold‑chain transport, but suppliers and rural pharmacies should avoid prolonged exposure to high heat and humidity during storage and transit.
For imported consignments verify packaging integrity, batch numbers and expiry dates and quarantine any suspect supplies pending product verification.
Telehealth providers should confirm dispensing source and storage instructions when arranging direct delivery to patients in remote areas.
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
Use a patient‑centred approach that confirms indication, checks contraindications including pregnancy and Parkinson’s and reviews all current medicines for interactions.
Advise dosing and timing clearly, warn about sedation and driving, set a review timeframe and document private prescriptions and counselling notes.
Provide printed advice for travellers and ensure rural patients know how to contact the pharmacy if adverse effects occur after delivery.
National Health Authority Recommendations
Follow TGA guidance on importing unregistered medicines and report adverse events promptly to national pharmacovigilance systems.
When formal TGA or PBS guidance is absent for an off‑formulary medicine, reference international clinical guidance for vestibular disorders and escalate to GP or ENT for persistent cases.
Shared decision‑making is essential in cost‑sensitive Australian settings, with clear documentation when prescribing privately or importing for a patient.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-7 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-7 days |
| Wollongong | New South Wales | 5-7 days |
| Geelong | Victoria | 5-7 days |
| Cairns | Queensland | 5-9 days |
Final Notes For Pharmacists And Patients
When a patient asks about stugeron for travel sickness, confirm timing of the 25 mg pre‑travel dose and warn about drowsiness and alcohol interaction.
For chronic vertigo trials, advise a 2–6 week review and document symptom changes and any early extrapyramidal signs.
Record private prescriptions carefully and check for CYP2D6 inhibitor co‑medication before advising dose increases.
Report any suspected adverse reactions to the TGA and encourage patients to contact the dispensing pharmacy promptly for any worrying symptoms.
Where PBS alternatives exist, discuss them openly to balance clinical benefit and out‑of‑pocket cost for each patient in the Australian context.