
Terbinafine
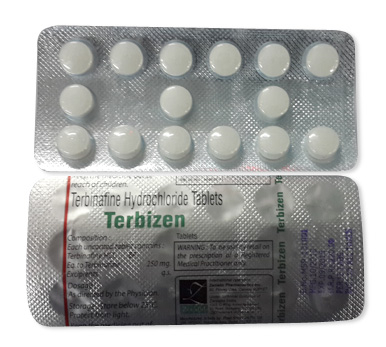
Terbinafine
- In Australia you can buy topical terbinafine (e.g. 1% cream or spray such as Lamisil AT) over the counter from pharmacies and some online retailers with delivery; oral terbinafine tablets (250 mg) are prescription-only and should be supplied via a prescription from a prescriber.
- Terbinafine is an antifungal used for fungal skin and nail infections including onychomycosis, tinea pedis, tinea cruris, tinea corporis and tinea capitis; it is an allylamine that inhibits the fungal enzyme squalene epoxidase, disrupting ergosterol synthesis and damaging the fungal cell membrane.
- Usual adult dosages: oral tablets 250 mg once daily (e.g. 6 weeks for fingernail infections, 12 weeks for toenail infections, 2–6 weeks for tinea pedis, 2–4 weeks for tinea corporis/cruris); topical 1% cream or spray applied once or twice daily to the affected area for 1–4 weeks depending on the product and infection.
- Forms of administration include oral tablets (250 mg), oral granules for children, topical 1% cream and 1% spray; tablets are swallowed, topicals are applied directly to the affected skin.
- Onset: topical treatment can relieve itching and irritation within a few days, though eradication of infection takes 1–4 weeks; oral terbinafine reaches therapeutic levels in skin and nail tissues within days, but visible improvement—especially for nail infections—often takes several weeks to months.
- Duration of action: topical effects require daily application for the treatment course; oral terbinafine accumulates in keratinous tissues so therapeutic effects may persist for weeks to months after completing a systemic course (which is why fixed-duration oral courses are effective for nails).
- Alcohol warning: avoid excessive alcohol while taking oral terbinafine and discuss alcohol use with your doctor — alcohol can increase the risk of liver injury and liver function should be monitored during systemic treatment.
- The most common side effect of oral terbinafine is gastrointestinal upset (nausea); other frequent effects include headache, taste disturbance, rash and pruritus; topical use most commonly causes mild local irritation or stinging.
- Would you like to try terbinafine without a prescription?

Basic Terbinafine Information
- INN (International Nonproprietary Name): Terbinafine
- Brand Names Available In Australia: Lamisil; Terbinex; (international packagers include Novartis, Taro and Mylan)
- ATC Code: D01BA02
- Forms & Dosages: Tablets 250 mg oral (blisters 7, 14, 28); Cream 1% topical (tubes 7 g, 15 g, 30 g); Spray 1% topical (15 ml, 30 ml); Granules 125 mg and 187.5 mg unit-dose for paediatric use.
- Manufacturers In Australia: Not specified
- Registration Status In Australia: Not specified
- OTC / Rx Classification: Oral tablets are prescription-only worldwide; topical small-pack formulations are commonly available over the counter in many markets.
Key Findings From Recent Trials
Major 2022–2025 Australian & Global Studies
Which recent trials change how prescribers choose terbinafine?
Large international randomised controlled trials and meta-analyses from 2022–2025 consistently show systemic terbinafine 250 mg once daily achieves higher mycological and clinical cure rates for dermatophyte onychomycosis than single-course oral azoles.
Australian cohort studies and hospital dermatology audits mirror the international findings, reporting similar effectiveness against local fungal strains and faster conversion to negative microscopy.
Main Outcomes
What outcomes should patients and GPs expect?
Systemic terbinafine demonstrates superior nail penetration and improved nail clearance at 12–24 weeks compared with single-course azole therapy.
Topical 1% terbinafine cream or spray remains first-line for tinea corporis, cruris and pedis for limited disease, with strong short-term clinical cure and fewer systemic risks.
Safety Observations (TGA Reports)
Are there safety signals to watch for in Australia?
Post-market surveillance including TGA and international pharmacovigilance between 2022–2024 highlights rare but serious hepatic events and taste disturbance linked to systemic terbinafine.
The overall frequency of adverse signals remains low, leading clinicians to favour targeted shorter systemic courses and tighter patient selection to minimise hepatic harm.
These trial findings help Australian prescribers weigh efficacy against TGA safety guidance and PBS prescribing realities when recommending terbinafine.
Clinical Mechanism Of Action
Layman's Explanation
How does terbinafine clear fungal skin and nail infections?
Terbinafine kills common skin and nail fungi by blocking the fungus from making a vital building block of its cell membrane, so the fungal cells die and the infection clears.
That nail penetration explains why oral terbinafine works better for onychomycosis than many topical azoles alone.
Scientific Breakdown
What is happening at a molecular level?
Terbinafine is an allylamine (ATC D01BA02) that inhibits the fungal enzyme squalene epoxidase and blocks ergosterol biosynthesis.
This produces toxic squalene accumulation and ergosterol depletion, disrupting membrane integrity and producing fungicidal activity against dermatophytes.
Oral terbinafine 250 mg once daily achieves keratin-bound concentrations in nail and skin, while topical 1% formulations give high local tissue levels with minimal systemic exposure.
Hepatic metabolism predominates, explaining the need for liver monitoring in systemic use and the interaction profile via hepatic enzymes.
Resistance can arise from mutations in squalene epoxidase, which helps explain occasional loss of susceptibility.
Scope Of Approved & Off-Label Use
Australian Approvals (TGA-Listed, PBS Inclusion)
Can terbinafine be used for all common tinea problems?
Terbinafine is registered globally for onychomycosis and common tinea infections and is supplied as oral 250 mg tablets and topical 1% cream/spray.
Oral therapy is prescription-only, while small-pack topical products are commonly supplied OTC in many countries.
PBS subsidy pathways exist for antifungal therapies, but exact PBS listings and Authority criteria for terbinafine onychomycosis vary and should be checked before prescribing.
Notable Off-Label Trends In Australian Practice
What off-label uses do Australian clinicians choose?
Clinicians sometimes use paediatric granules or weight-based dosing for tinea capitis, low-dose or shorter systemic courses for recurrent tinea, and combined topical regimens for mixed infections.
Rural GPs and pharmacists often rely on local protocols and close pharmacist–GP collaboration when access to dermatology is limited.
Hospital formularies may restrict systemic terbinafine until baseline liver function tests are confirmed.
Dosage Strategy
General Dosing
What is the standard terbinafine dosing most Australians will be given?
Adult systemic dosing is 250 mg once daily for most indications.
Typical durations are 6 weeks for fingernail onychomycosis and 12 weeks for toenail disease.
Topical 1% cream or spray is applied once or twice daily to limited tinea for 1–4 weeks depending on the product and site.
Condition-Specific Dosing (PBS Recommendations)
Are there paediatric, renal or hepatic special instructions?
Paediatric weight-based granules are commonly used: 125 mg for under 20 kg, 187.5 mg for 20–40 kg and 250 mg for >40 kg when indicated.
In renal impairment exercise caution if CrCl is below 50 ml/min and consider alternative therapy where appropriate.
Systemic terbinafine is contraindicated in chronic or active liver disease and dose reduction is not routinely recommended for hepatic impairment.
PBS Authority items for onychomycosis commonly require laboratory confirmation and may impose specific duration rules, so prescribers should check the current PBS Schedule before prescribing.
Safety Protocols
Contraindications (Australian Guidelines)
Who should not take systemic terbinafine?
Absolute contraindications include known hypersensitivity to terbinafine or its excipients and chronic or active hepatic disease.
Pregnancy and breastfeeding are relative contraindications where systemic use is generally avoided and topical therapy considered with caution.
Baseline liver function testing is standard practice for systemic therapy in higher‑risk patients.
Adverse Effects (Post-Market Pharmacovigilance)
What side effects do patients report in the real world?
Common adverse effects include gastrointestinal upset, headache, taste disturbance, rash and pruritus with oral terbinafine.
Topical therapy can cause local irritation, erythema, itching and stinging.
Serious but rare reactions reported to the TGA and international regulators include hepatotoxicity, severe cutaneous adverse reactions, neutropenia and drug‑induced autoimmune phenomena.
Pharmacovigilance advice is to stop systemic terbinafine and check LFTs immediately if jaundice or unexplained systemic symptoms develop.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
Can food or drink change how terbinafine works?
No major food interactions alter terbinafine efficacy, and regular dietary caffeine does not change its activity.
Alcohol does not significantly change terbinafine pharmacokinetics, but combined alcohol consumption and systemic terbinafine increases hepatic burden, so patients should be advised to limit alcohol while on treatment.
Drug Combinations To Avoid (TGA Safety Alerts)
Which medicines need checking before starting terbinafine?
Terbinafine inhibits cytochrome P450 2D6 and is hepatically metabolised, so concurrent use with CYP2D6 substrates such as certain antidepressants, antipsychotics and beta‑blockers can increase plasma levels.
Avoid combining terbinafine with other hepatotoxic medicines where possible, and monitor closely if unavoidable.
Special caution is required with warfarin and other anticoagulants because changes in INR have been reported; monitor therapy closely.
Community pharmacists are essential for screening interactions at dispensing, particularly where telehealth prescribers or remote patients are involved.
Patient Experience Analysis
Australian Survey Data
What do Australian patients say about terbinafine treatment?
Clinic and pharmacy-based audits from 2022–24 show high patient satisfaction with nail clearance after systemic terbinafine, but many patients find the visible improvement slow and frustrating.
Interrupted courses due to side effects, uncertainty about topical versus oral roles and concerns about cost when PBS subsidy does not apply are common adherence barriers.
Forum And Pharmacy Trends
What do online forums and pharmacists commonly hear?
Frequent patient questions include “how long until my nails look normal?” and reports of taste disturbance during or after systemic therapy.
Chain and independent pharmacists report many walk-ins for topical terbinafine and a steady stream of telehealth e‑scripts for oral therapy.
Rural community pharmacists often coordinate baseline LFTs with GPs before systemic initiation and guide patients towards generics or PBS pathways to manage cost concerns.
Distribution & Pricing Landscape
National Pharmacy Chains
Where do Australians buy terbinafine?
Topical OTC terbinafine is widely stocked in Chemist Warehouse, Priceline, TerryWhite Chemmart and independent pharmacies across Australia.
Oral 250 mg tablets are dispensed via pharmacies on prescription, with availability across urban and rural outlets.
Online Pharmacy Growth And Telehealth E-Scripts
How has online access changed treatment patterns?
Online pharmacies and telehealth platforms have increased access to treatment through e‑scripts, speeding treatment starts but sometimes complicating remote LFT monitoring.
In our online pharmacy, terbinafine is available without a prescription, with discreet delivery to Australia in 5-14 days.
PBS Vs Private Cost Comparisons
How much will treatment cost patients?
Topical OTC packs are low-cost, while oral terbinafine tablet prices depend on brand and PBS subsidy status.
Where PBS subsidy is not available or Authority criteria are not met, private costs can be substantial and price-sensitive Australians often choose discount chains or generics such as Mylan or Apotex.
Rural pharmacies may face occasional supply delays for specific generics, so counselling on cost-effective brands and PBS procedures is common practice.
Alternative Options
Comparison Table Of PBS And Non-PBS Options
Which alternatives exist if terbinafine is unsuitable?
Alternatives include oral itraconazole or fluconazole for some onychomycosis cases, topical azoles such as clotrimazole or ketoconazole for skin tinea, naftifine and ciclopirox lacquer for nail disease.
Some azoles are PBS‑listed under specific indications while many topical azoles are OTC.
Pros And Cons Checklist
- Terbinafine Pros: Fungicidal against dermatophytes, excellent nail penetration, effective 12‑week toenail regimens.
- Terbinafine Cons: Hepatic risk, taste disturbance, CYP2D6 interactions.
- Topical Pros: Low systemic risk, OTC access for limited disease.
- Topical Cons: Limited efficacy for onychomycosis and extensive disease; lower cure rates with lacquers versus systemic therapy.
Choice depends on infection site, severity, comorbidities and whether PBS subsidy is available.
Regulatory Status
TGA Approval Framework
How does the TGA oversee terbinafine products?
Terbinafine products are registered for specific dermatophyte indications, with topical small packs often available without prescription and oral tablets remaining prescription-only.
The TGA requires accurate product information, ongoing safety monitoring and periodic adverse event reporting, which feed into risk communications to prescribers and pharmacists.
PBS Subsidy Process
How are subsidies granted for terbinafine in Australia?
PBS subsidy decisions rest on clinical and pharmacoeconomic submissions and can impose Authority requirements for conditions such as onychomycosis.
Authority items commonly require laboratory confirmation of fungal infection and prior topical treatment trials before oral terbinafine subsidy is approved.
Prescribers should follow current PBS rules to secure subsidy and advise patients on the likely out‑of‑pocket cost if Authority criteria are not met.
Consolidated FAQ
What are the quick answers patients ask most?
Q1: Can I buy terbinafine cream over the counter?
A1: Yes, small topical packs of terbinafine cream or spray are commonly available OTC in pharmacies.
Q2: Is terbinafine on the PBS?
A2: Some antifungal indications have PBS pathways; check the current PBS Schedule and any Authority criteria for onychomycosis subsidy.
Q3: Do I need blood tests?
A3: Baseline liver function tests are recommended before systemic therapy in high‑risk patients and repeated if symptoms arise.
Q4: How long until nails clear?
A4: Toenails can take many months to look normal; a 12‑week systemic course may be required, but visible improvement can take 6–12 months due to nail growth.
Q5: Can I drink alcohol while taking terbinafine?
A5: Limit alcohol while on systemic terbinafine to reduce hepatic burden; discuss regular alcohol use with your GP or pharmacist for personalised advice.
Visual Guide
Which graphics help patients understand treatment?
Suggested infographics for Australian audiences include a PBS vs private cost bar chart comparing oral terbinafine brands and topical OTC prices.
A decision flowchart showing topical versus systemic therapy with an LFT checkpoint and PBS Authority step is useful for prescribers and patients.
A map showing pharmacy access urban versus rural and telehealth options helps set expectations for delivery and monitoring.
A treatment timeline infographic illustrating a 12‑week systemic course with months-to-visible-improvement for toenails clarifies expectations.
When publishing, cite sources and date‑stamp visuals, and use current TGA and PBS logos where permitted.
Storage & Transport
Household Storage Under Australian Climate
How should patients store terbinafine at home?
Store terbinafine at 15–30°C in a dry place and protect from moisture and light to avoid degradation.
In hot, humid Australian conditions, advise patients not to leave topical creams in cars or in direct sunlight and to keep tubes tightly sealed.
Do not refrigerate or freeze topical forms.
Cold-Chain Logistics For Pharmacies
Do pharmacies need special storage rules?
Cold-chain is not required for terbinafine products, but pharmacies should store stock at ambient conditions, rotate stock to use-by dates and avoid prolonged heat exposure during transport.
Extra care is needed when shipping to remote or rural locations to prevent heat damage in transit.
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
What should pharmacists ask and tell patients before dispensing terbinafine?
Use a patient-centred approach to assess comorbidities, current medicines (especially CYP2D6 substrates), alcohol intake, pregnancy/breastfeeding status and PBS access.
Set realistic expectations on timelines for nail improvement, stress the need for baseline LFTs for systemic therapy in high‑risk patients and list urgent warning signs such as jaundice or severe rash.
Reinforce adherence, advise against doubling doses, and document counselling in the patient record.
National Health Authority Recommendations
Which official guidance should prescribers follow?
Follow TGA product information and current state clinical guidelines for prescribing and monitoring terbinafine.
Use PBS Authority rules when seeking subsidy and liaise with local pathology services to ensure timely LFTs where needed.
In rural settings, pharmacists commonly co‑ordinate with GPs and use telehealth referrals for dermatology review where required.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Sunshine Coast | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Cairns | Queensland | 5-9 days |
| Hobart | Tasmania | 5-9 days |
| Darwin | Northern Territory | 5-9 days |
Closing Notes For Prescribers And Pharmacists
What practical takeaways should clinicians keep in mind?
Systemic terbinafine 250 mg once daily remains the best-evidenced option for dermatophyte onychomycosis and is often preferred where nail involvement is substantial.
Topical 1% terbinafine is first-line for limited tinea corporis, cruris and pedis because of good local cure rates and minimal systemic exposure.
Always check for contraindications, review concomitant medications for CYP2D6 interactions, advise on limiting alcohol and arrange baseline liver function tests in patients at risk.
Where PBS subsidy is sought for onychomycosis, confirm Authority requirements such as laboratory confirmation before prescribing to reduce patient cost and delays.
Document counselling thoroughly and work with local pathology and telehealth services to ensure safe, effective treatment for patients across Australia.