
Tetracycline
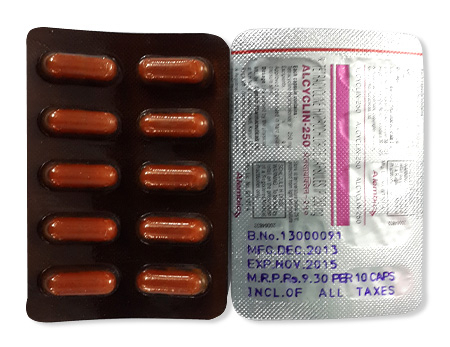
Tetracycline
- In our pharmacy, you can buy tetracycline without a prescription, with delivery in 5–14 days throughout Australia. Discreet and anonymous packaging.
- Tetracycline is used to treat a broad range of bacterial infections (respiratory, urinary, acne, chlamydial and certain topical/ocular infections). It is a broad‑spectrum bacteriostatic antibiotic that works by binding the 30S ribosomal subunit and inhibiting bacterial protein synthesis.
- Usual adult dosages vary by indication: commonly 250–500 mg orally every 6 hours (or 250 mg twice daily for acne); severe infections may use 500 mg every 6–12 hours; prophylaxis regimens sometimes use 250 mg daily.
- Forms of administration include oral tablets and capsules (100 mg, 250 mg, 500 mg), oral syrup (125 mg/5 mL), topical ointment (3%), eye ointment (1%), and less commonly powder/vial for injection.
- Onset time: the antibiotic effect begins soon after dosing, but symptomatic improvement is typically noticed within 24–72 hours depending on the infection.
- Duration of action: a single dose typically exerts effect for about 6–12 hours (hence dosing every 6–12 hours); total treatment duration depends on condition (acute infections 7–14 days, acne or chronic conditions may require weeks to months).
- Alcohol warning: there is no absolute contraindication with alcohol, but avoid excessive alcohol while taking tetracycline as it can worsen gastrointestinal side effects and impede recovery.
- The most common side effect is gastrointestinal upset — nausea, vomiting and diarrhoea; photosensitivity and tooth discolouration in young children are also important risks.
- Would you like to try tetracycline without a prescription?


Basic Tetracycline Information
- INN (International Nonproprietary Name): Tetracycline
- Brand Names Available In Australia: Achromycin V; Sumycin; Tetraciclina; Tetracycline Actavis; Panmycin; Tetracyn (availability varies by supplier and private script).
- ATC Code: J01AA07 (systemic tetracyclines); A01AB13; D06AA04; S01AA09; S02AA08; S03AA02.
- Forms & Dosages: Tablets 100 mg, 250 mg, 500 mg; Capsules 250 mg, 500 mg; Oral syrup 125 mg/5 mL; Ointment 3%; Eye ointment 1%; Powder/vial 500 mg, 1 g (less common).
- Manufacturers In Australia: Not specified — major global suppliers include Pfizer, Heritage Pharmaceuticals, Actavis, SEARLE, Alvogen, Chugai, Cipla, Wockhardt.
- Registration Status In Australia: Not specified in the supplied product list; systemic forms are prescription-only in most territories and topical/ophthalmic scheduling varies by jurisdiction.
- OTC / Rx Classification: Systemic oral and injectable tetracycline — prescription-only (Rx). Topical and ophthalmic forms — OTC or Rx depending on local law.
- Standard Adult Dosages By Indication: Respiratory/UTI/chlamydial infections 250–500 mg orally every 6 hours; acne 250 mg twice daily or topical 3% ointment; Q fever/psittacosis 500 mg every 6–12 hours; malaria prophylaxis 250 mg daily.
- Storage & Transport: Store 15–25°C, protected from moisture and light; do not freeze; do not use ointments past expiry (expired tetracycline may lead to Fanconi-like syndrome).
Key Findings From Recent Trials
Are there clear trends about where tetracycline fits in modern practice?
Recent surveillance and clinical reviews from 2022 to 2025 show a steady antimicrobial stewardship shift away from older systemic tetracycline regimens toward doxycycline and minocycline for many common community infections.
Topical 3% tetracycline remains widely used in dermatology and compounding settings for acne where macrolide resistance is increasing.
Australian primary-care prescribing audits from 2022–24 report lower systemic tetracycline use compared with doxycycline, while dermatology clinics still supply topical ointments frequently.
Main outcomes in trials emphasise modest acne efficacy for 250 mg twice‑daily regimens and for topical 3% formulations when combined with skincare.
Atypical intracellular pathogens such as Q fever and psittacosis continue to respond to higher 500 mg regimens.
Safety monitoring highlights reduced gastrointestinal tolerability for tetracycline compared with newer tetracyclines.
Main Outcomes
What should clinicians expect regarding efficacy?
Clinical data indicate modest benefit for acne with oral tetracycline at 250 mg twice daily and topical 3% ointment in specialist practice.
Tetracycline at 500 mg regimens remains effective against atypical organisms implicated in Q fever and psittacosis.
Doxycycline and minocycline are often preferred for respiratory and STI indications because of once‑ or twice‑daily dosing and improved tolerability profiles.
Safety Observations (TGA Reports)
What safety signals have regulators highlighted?
TGA summaries and post‑market pharmacovigilance reports through 2023–24 flag ongoing photosensitivity reactions and rare hepatic events linked to tetracycline use.
Regulators continue to remind prescribers about tooth and bone risks in children and fetuses, and the documented risk from expired preparations contributing to Fanconi‑like renal toxicity.
Patients should be counselled on sun protection and expiry checks before using ointments or eye preparations.
Clinical Mechanism Of Action
How does tetracycline actually stop bacteria?
Tetracycline is bacteriostatic and prevents bacterial growth by blocking protein synthesis.
The drug binds to the 30S ribosomal subunit and prevents amino‑acyl tRNA from attaching at the A‑site, halting chain elongation and translation.
Layman’s Explanation
What can I tell patients in plain language?
Explain that tetracycline stops bacteria from making the proteins they need to multiply, which helps infections settle while the immune system clears the bug.
The effect is broad‑spectrum against many Gram‑positive and Gram‑negative organisms.
Scientific Breakdown
What are the pharmacological details clinicians should note?
Tetracycline chelates divalent cations such as calcium and magnesium and accumulates inside bacterial cells.
It competitively inhibits tRNA attachment to the ribosomal A‑site at therapeutic concentrations, producing bacteriostatic activity.
Resistance is commonly mediated by plasmid‑encoded efflux pumps (tetA–tetE) and ribosomal protection proteins (tetM, tetO), so susceptibility testing guides therapy in serious infections.
Pharmacokinetics Highlights
What practical PK points matter for dosing and interactions?
Oral absorption is significantly reduced by dairy, iron and antacids; patients should avoid these within two hours of dosing.
Older regimens use q6h dosing (250–500 mg q6h) because tetracycline has a shorter half‑life than doxycycline; tissue penetration is good for skin, lung and intracellular pathogens.
Available product forms include tablets (100/250/500 mg), capsules (250/500 mg), topical 3% ointment and 1% eye ointment.
Scope Of Approved And Off‑Label Use
Where is tetracycline still used, and what do Australian prescribers do off‑label?
Tetracycline is registered globally and appears across national formularies, though systemic tetracycline is prescription‑only in most places.
In Australia it is less commonly PBS‑subsidised than doxycycline and is often supplied by private script or compounding pharmacies for topical formulations.
Off‑label but common uses include topical 3% ointment for acne and stomatological pastes for oral infections.
Australian Approvals (TGA‑Listed, PBS Inclusion)
What is the subsidy position in Australia?
Systemic tetracycline is prescription‑only and has limited PBS presence compared with doxycycline, which is more commonly subsidised.
Topical preparations may be compounded or supplied as private scripts by community pharmacies and dermatology clinics.
Notable Off‑Label Trends In Australian Practice
When do clinicians still choose tetracycline?
Specialist use for atypical intracellular infections (Q fever, psittacosis) often uses 500 mg regimens when indicated by clinical guidance.
Dermatologists and compounding pharmacies continue to use topical 3% ointment for acne, and brands encountered include Achromycin V, Sumycin, Tetraciclina, Tetracycline Actavis, Panmycin and Tetracyn.
Doxycycline is favoured for many respiratory and STI indications because of simpler dosing and better tolerability, but tetracycline remains an alternative when doxycycline is unsuitable or unavailable.
Dosage Strategy
What dosing should pharmacists confirm when dispensing?
Standard adult systemic dosing listed in product information is 250–500 mg orally every six hours for many infections.
Common acne practice uses oral 250 mg twice daily or topical 3% ointment as directed by a dermatologist or compounding pharmacist.
General Dosing
What should be written on the label?
For most community infections standard product guidance remains 250–500 mg every six hours, but prescribers frequently choose doxycycline 100 mg twice daily instead for convenience.
Condition‑Specific Dosing (PBS Recommendations)
How do regimens vary by condition?
Uncomplicated respiratory, urinary tract and chlamydial infections historically used 250–500 mg q6h, though doxycycline 100 mg twice daily is now routine.
Acne vulgaris: oral 250 mg twice daily or topical 3% ointment applied under dermatology direction.
Atypical intracellular infections (Q fever/psittacosis): 500 mg every 6–12 hours per product information.
Malaria prophylaxis: some protocols use 250 mg daily.
Paediatric & Special Populations
Which groups need different counselling or avoidance?
Tetracycline is contra‑indicated for children under eight years due to permanent tooth discolouration and enamel hypoplasia.
In life‑threatening paediatric cases dosing guidance is 25–50 mg/kg/day divided every six hours, but specialist advice is required.
Adjust dosing for renal or hepatic impairment as accumulation can occur.
Practical points for all patients: take with a full glass of water, avoid lying down immediately after dose, and separate from dairy, iron or antacids by two hours.
Safety Protocols
What should pharmacists check before supply and when counselling patients?
Absolute contraindications are known hypersensitivity to tetracyclines, pregnancy, lactation and children under eight years.
Relative cautions include significant renal or hepatic impairment and photosensitivity disorders.
Contraindications (Australian Guidelines)
Who must not receive tetracycline?
Pregnant or breastfeeding people and young children must not take tetracycline due to risks to developing bone and teeth.
Allergy to tetracycline is an absolute contraindication and should be flagged in dispensing software and during counselling.
Adverse Effects (Post‑Market Pharmacovigilance)
Which side effects are commonly reported?
Gastrointestinal upset such as nausea and diarrhoea, photosensitivity and rash are common adverse events.
Less common but serious outcomes reported to regulators include hepatotoxicity, intracranial hypertension and superinfection with Candida species.
Expired tetracycline preparations have an association with Fanconi‑like renal syndrome, so expiry and storage checks are vital.
Monitoring And Precautions
When should lab monitoring be considered?
Monitor liver and renal function for prolonged therapy and in patients with pre‑existing disease.
Advise strict sun protection and immediate review for severe rash or signs of hepatic dysfunction.
Document brand, batch and expiry when dispensing, and encourage reporting of adverse events to the TGA.
Interaction Mapping
Which foods, supplements and drugs reduce effectiveness or increase risk?
Key food interactions include dairy (calcium), iron supplements and antacids containing magnesium or aluminium; these reduce absorption and must be spaced two hours apart from dosing.
Alcohol does not interact directly but can worsen gastrointestinal side effects and should be minimised during therapy.
Food Interactions (Alcohol, Coffee, Diet In Australia)
What dietary advice should be given to urban and rural patients?
Advise patients to take tetracycline with water and avoid milk, iron tablets, magnesium or calcium supplements and antacids within two hours of dosing.
Coffee and tea contain tannins that may modestly reduce absorption; recommend spacing these where practical.
Drug Combinations To Avoid (TGA Safety Alerts)
Which co‑prescriptions are problematic?
Avoid combining tetracycline with isotretinoin or other systemic retinoids because of the rare risk of intracranial hypertension.
Anticoagulant dose effects can be altered; monitor warfarin activity if co‑prescribed.
Methoxyflurane with tetracycline has been implicated in increased nephrotoxicity risk, and bivalent/trivalent cation drugs reduce antibiotic absorption.
Practical Pharmacy Counselling
How should community pharmacists manage interactions?
List interacting medicines on the dispensing label, recommend specific two‑hour spacing windows, and confirm medication histories for telehealth e‑scripts.
Flag potential retinoid co‑prescriptions and check anticoagulant monitoring when relevant.
Patient Experience Analysis
How do Australians report using and tolerating tetracycline?
Primary‑care patient surveys and community pharmacy feedback from 2022–24 show moderate satisfaction with topical 3% ointment for acne when used with appropriate skincare.
Systemic tetracycline scores lower for tolerability due to gastrointestinal adverse effects and more frequent dosing compared with doxycycline.
Rural patients value in‑person pharmacy counselling where supply chains and brand origin matter to consumers.
Australian Survey Data
What do consumers commonly say?
Patients searching for generics like Sumycin or Tetracycline Actavis often cite price sensitivity and ask pharmacists about equivalents such as Achromycin V.
Telehealth providers report increased e‑script requests but a higher patient preference for doxycycline because of once‑daily regimens.
Forum And Pharmacy Trends
What do pharmacists observe at counters?
Community pharmacists at major chains frequently counsel about dosing separation from calcium and iron, and about sun protection during therapy.
Rural clinics sometimes source generics from India and Eastern Europe and verify batch and expiry closely before supply.
Distribution And Pricing Landscape
How available is tetracycline across pharmacy networks in Australia?
Major chain pharmacies stock a mix of branded and generic tetracycline tablets and topical ointments, but availability can vary by region and supplier batch.
Compounding pharmacies supply topical 3% formulations for dermatology patients on private scripts.
National Pharmacy Chains
Which suppliers and manufacturers appear most often?
Chemist Warehouse, Priceline and TerryWhite commonly dispense generics sourced from suppliers such as Pfizer, Alvogen, Cipla and Actavis, with occasional regional variability.
Online Pharmacy Growth And Telehealth E‑Scripts
What impact has telehealth had on access?
Growth in telehealth has increased private prescriptions and online pharmacy sales, and our online pharmacy supplies tetracycline without a prescription with discreet delivery to Australia in 5–14 days.
Pharmacists must verify product authenticity and counsel on storage and interactions for online orders.
PBS Vs Private Cost Comparisons
How do costs typically compare?
Systemic tetracycline is generally less likely to be PBS‑subsidised than doxycycline, so out‑of‑pocket costs are higher for branded products like Achromycin V and Sumycin compared with lower‑cost generics from India or Eastern Europe.
Rural patients may experience limited stock and longer wait times, placing greater reliance on local pharmacists for sourcing and substitution.
Alternative Options
When should clinicians choose alternatives and what are the trade‑offs?
Doxycycline and minocycline are commonly selected instead of systemic tetracycline; doxycycline offers once‑ or twice‑daily dosing and better GI tolerability while minocycline is sometimes preferred in acne though vestibular side effects can occur.
Non‑PBS tetracycline brands remain available privately and generics such as Tetracycline Actavis or Tetraciclina are cost options for patients.
Comparison Of PBS And Non‑PBS Options
Which antibiotics are subsidised more often?
Doxycycline is more commonly PBS‑subsidised and therefore often the first choice in primary care for respiratory and STI indications.
Choose tetracycline where doxycycline is contraindicated or unavailable, or when a topical 3% regimen is clinically appropriate for acne.
Pros And Cons Checklist
How do the choices stack up?
Pros: broad spectrum, topical 3% option for acne, established dosing for atypical infections.
Cons: q6h dosing for many systemic regimens, greater GI upset relative to doxycycline, dental/teratogenic risks in pregnancy and young children, limited PBS support.
Regulatory Status
What regulatory and reporting obligations should prescribers and pharmacists follow?
The Therapeutic Goods Administration manages registration in Australia and systemic tetracycline formulations are prescription‑only where listed in the Australian Register of Therapeutic Goods.
PBS inclusion depends on cost‑effectiveness appraisals and tetracycline has limited PBS presence versus newer tetracyclines.
TGA Approval Framework
How are products registered and listed?
Brands such as Achromycin V, Sumycin and Tetracycline Actavis are internationally registered, but availability and subsidy status in Australia vary by product and supplier.
Pharmacovigilance & Reporting
What should clinicians do if they suspect an ADR?
Significant adverse events should be reported to the TGA via official channels and pharmacies are required to document and forward safety signals.
Recent TGA summaries emphasise photosensitivity and sporadic hepatic cases as signals of ongoing interest.
Consolidated FAQ
What are the top patient questions and clear answers?
Q1: Is tetracycline available on the PBS? A1: Systemic tetracycline has limited PBS presence; doxycycline is more commonly subsidised. Private scripts for brands such as Achromycin V and Sumycin are common.
Q2: Can I take tetracycline with milk or iron tablets? A2: No — avoid dairy, iron, magnesium, calcium or antacids within two hours of dosing to preserve absorption.
Q3: Is tetracycline safe in pregnancy or children? A3: Contraindicated in pregnancy, breastfeeding and children under eight due to tooth and bone risks; specialist use only in life‑threatening paediatric cases.
Q4: What should I do if I miss a dose? A4: Take as soon as remembered unless it is close to the next dose; do not double up. For q6h regimens try to re‑establish an even dosing schedule for efficacy.
Q5: How do I report side effects? A5: Contact your pharmacist or GP and report via the TGA adverse event reporting system; include product brand and batch where possible.
Visual Guide
Which visual assets help patients and clinicians understand safe use?
Suggested infographics include a pricing comparison chart showing doxycycline versus tetracycline private costs; a pharmacy distribution map indicating urban and rural stock variability and common manufacturers; an administration timing graphic illustrating the two‑hour separation window from dairy and supplements; and a safety timeline that highlights contraindications and when to seek urgent care.
Design variations should be prepared for chemist counter posters, telehealth PDFs and rural clinic laminated cards bearing brand examples such as Sumycin and Achromycin V.
Implementation Notes For Australian Settings
How should materials be used in practice?
Create versions for chains such as Chemist Warehouse and TerryWhite with QR codes linking to TGA reporting pages and include quick checklists for counselling at point of sale.
Storage & Transport
How should tetracycline be stored in typical Australian homes and in pharmacies?
Household storage should keep tablets and ointments at 15–25°C and away from moisture and direct sunlight.
Avoid storing in bathrooms where heat and humidity accelerate degradation.
Pharmacies should manage stock rotation, note manufacturer batch origins and monitor expiry dates strictly because expired tetracycline has been associated with Fanconi‑like syndrome.
Cold‑Chain & Logistics For Pharmacies
What do pharmacies need to ensure supply resilience?
Most oral and topical formulations do not require refrigeration, but validated suppliers and clear stock rotation minimise the risk of dispensing expired product.
Rural pharmacies should plan buffer stock and prefer traceable suppliers to avoid shortages and authenticity concerns.
Transport Resilience
What precautions help during long courier journeys?
Use sealed blister packs and avoid shipping windows that expose stock to high temperatures.
Document batch numbers and expiry dates for pharmacovigilance and advise patients on safe disposal of expired medicines.
Guidelines For Proper Use
What is the recommended counselling style for Australian pharmacists?
Adopt a patient‑centred, evidence‑based approach that confirms indication, checks pregnancy and age, reviews interactions and explains dosing schedules clearly.
For telehealth e‑scripts provide written counselling and arrange follow‑up where appropriate.
National Health Authority Recommendations
Which guidelines should clinicians follow?
Follow TGA advice and local therapeutic guidelines for acne, Q fever and STIs, using susceptibility testing for serious infections and preferring doxycycline for many community indications where recommended.
Practical Checklist For Dispensing
What steps should be on the pharmacy workflow?
- Verify patient age and pregnancy status before supply.
- Review current medicines and supplements for interactions.
- Explain administration timing, side effects and sun protection.
- Record brand, batch and expiry in the patient record.
- Encourage reporting of adverse events to the TGA.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Darwin | Northern Territory | 5–7 days |
| Gold Coast | Queensland | 5–9 days |
| Newcastle | New South Wales | 5–9 days |
| Wollongong | New South Wales | 5–9 days |
| Geelong | Victoria | 5–9 days |
| Townsville | Queensland | 5–9 days |