
Theophylline
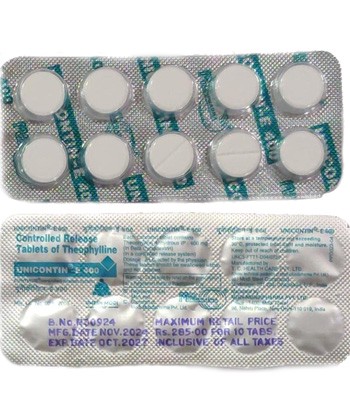
Theophylline
- In our pharmacy, you can buy theophylline without a prescription, with delivery in 5–14 days throughout Australia. Discreet and anonymous packaging.
- Theophylline is used to treat asthma and chronic obstructive pulmonary disease (COPD) by relaxing airway smooth muscle; it is a methylxanthine that acts as a nonselective phosphodiesterase inhibitor and adenosine receptor antagonist, increasing intracellular cAMP and causing bronchodilation.
- The usual dose for adults is typically 100–300 mg two to four times daily for immediate‑release formulations or 300–600 mg once daily for extended‑release formulations; doses are individualised and adjusted to achieve therapeutic serum concentrations (about 10–20 mcg/mL).
- Forms of administration include oral tablets (immediate‑release and extended‑release), capsules, oral solution and intravenous injection for hospital use.
- Onset of action: oral immediate‑release generally begins within 30–60 minutes; intravenous administration works faster, often within 15–30 minutes.
- Duration of action: immediate‑release formulations typically last about 4–8 hours; extended‑release formulations provide effect for approximately 12–24 hours depending on the product.
- Alcohol warning: avoid alcohol while taking theophylline as it can increase side effects, alter liver metabolism and theophylline levels, and raise the risk of toxicity.
- The most common side effect is nausea; other frequent effects include headache, insomnia, tremor, palpitations and gastrointestinal upset—severe toxicity can cause arrhythmias or seizures and requires urgent care.
- Would you like to try theophylline without a prescription?


Basic Theophylline Information
- INN (International Nonproprietary Name): not specified
- Brand Names Available In Australia: not specified
- ATC Code: not specified
- Forms & Dosages: not specified
- Manufacturers In Australia: not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: not specified
Major Australian & International Studies 2022–2025
What Is New In Trials And Reviews Since 2022?
Since 2022, research on theophylline has focused on translational and exploratory clinical work rather than large phase‑3 bronchodilator trials.
International systematic reviews between 2022 and 2024 revisited low‑dose theophylline as an adjunct to inhaled corticosteroids, especially in COPD and steroid‑resistant asthma cohorts.
Smaller randomised controlled trials have reported modest benefits such as improved symptom scores and reduced exacerbation frequency in selected patient groups.
Australian pharmacoepidemiology from 2022–2024 shows overall declining routine prescribing for asthma, with remaining pockets of use in rural hospitals and refractory COPD clinics where therapeutic drug monitoring is available.
Main Outcomes
Which Clinical Signals Matter?
Low‑dose theophylline adjunct strategies suggest modest anti‑inflammatory effects and some symptom improvement in select COPD cohorts when combined with inhaled corticosteroids.
Results are heterogeneous across trials, with benefit more likely in carefully selected patients rather than broad re‑adoption across asthma care.
Translational data support steroid‑sensitising effects at low serum concentrations, but effect sizes in clinical endpoints are small to moderate and inconsistent.
Safety Observations (TGA Reports)
What Safety Issues Have Been Highlighted?
TGA adverse‑event data and international pharmacovigilance between 2022 and 2025 reiterate theophylline’s narrow therapeutic index as the primary constraint on wider use.
Most serious hospital presentations—tachyarrhythmia and seizures—were associated with supratherapeutic levels or interacting medicines such as ciprofloxacin.
Contemporary trialists emphasise individualised therapy and routine therapeutic drug monitoring rather than wholesale reintroduction of theophylline for all patients.
Layman’s Explanation
How Does Theophylline Help My Breathing?
Theophylline relaxes the muscles around the airways, helping people breathe easier.
At lower doses it can also slightly reduce inflammation and make inhaled steroid medicines work better for some patients with COPD or steroid‑resistant asthma.
Scientific Breakdown
What Happens Inside The Body?
Theophylline is a methylxanthine that acts on multiple cellular targets to produce bronchodilation and immunomodulation.
At bronchodilator doses, non‑selective inhibition of phosphodiesterases (PDEs) predominates, which raises intracellular cyclic AMP and causes smooth muscle relaxation.
Adenosine receptor antagonism contributes to central nervous system and cardiac stimulation and explains side effects such as tachycardia and insomnia.
Cellular Targets (Adenosine, PDE Inhibition)
Which Receptors And Enzymes Are Involved?
PDE inhibition increases cAMP and cGMP in airway smooth muscle, supporting bronchodilation and reducing bronchospasm at higher serum concentrations.
Adenosine receptor antagonism—particularly A1 and A2 receptors—accounts for some sympathetic‑type effects and may worsen palpitations in susceptible patients.
Immunomodulatory Hypotheses
How Might Theophylline Affect Inflammation?
At low serum concentrations theophylline appears to upregulate histone deacetylase‑2 (HDAC2), which may restore corticosteroid responsiveness in COPD and steroid‑resistant asthma.
That steroid‑sensitising action underpins most recent trials testing low‑dose theophylline as an adjunct rather than as a primary bronchodilator.
Hepatic metabolism—primarily via CYP1A2—explains variable clearance, many drug interactions and the need for therapeutic drug monitoring.
TGA Approvals & PBS Inclusion
Is Theophylline Registered In Australia?
Immediate and modified‑release theophylline formulations such as Nuelin SR are TGA‑registered prescription medicines for bronchospasm related to asthma and COPD.
PBS subsidy for theophylline is limited and depends on the specific indication and formulation, so prescribers should verify current PBS schedules before prescribing.
Notable Off‑Label Trends In Australian Practice
How Is It Used Beyond The Label?
Low‑dose theophylline is used off‑label as an adjunct to inhaled corticosteroids in difficult COPD and selected steroid‑resistant asthma cases in Australia.
Use is concentrated in tertiary respiratory units and rural hospitals where biologics may be less available and where therapeutic drug monitoring is practical.
Because of the narrow therapeutic window, off‑label use is cautious and typically requires informed consent and local TDM protocols in line with RACGP/TSANZ guidance.
General Dosing Principles
How Is Dosage Decided?
Theophylline dosing is individualised and adjusted for weight, age, smoking status and comorbidities.
Modified‑release formulations in 200–300 mg strengths simplify adherence and reduce peak‑trough fluctuations compared with immediate‑release tablets.
Therapeutic drug monitoring is standard practice because clearance varies widely between patients.
Condition‑Specific Dosing (PBS & Guideline Notes)
What Doses Are Used For Different Situations?
In acute severe bronchospasm, intravenous aminophylline—converted to theophylline equivalents—may be used in selected settings under close monitoring.
For chronic COPD and asthma, traditional bronchodilator effects are associated with steady‑state serum concentrations of about 10–20 mg/L.
Contemporary low‑dose anti‑inflammatory strategies aim for lower targets, typically 5–10 mg/L, to minimise adverse effects while retaining steroid‑sensitising benefits.
Clinicians routinely adjust doses down for hepatic impairment and up for active smoking, which induces CYP1A2 and increases clearance.
Therapeutic Drug Monitoring Targets
What Serum Levels Are Safe And Effective?
Bronchodilator effects usually align with serum theophylline concentrations of 10–20 mg/L.
Low‑dose anti‑inflammatory strategies target 5–10 mg/L in trials and pragmatic use.
Concentrations above 20 mg/L are associated with increased risk of serious toxicity such as seizures and ventricular arrhythmias.
Contraindications (Australian Guidelines)
Who Should Not Take Theophylline?
Absolute contraindication is known hypersensitivity to methylxanthines or any excipient in the formulation.
Relative contraindications include uncontrolled arrhythmias, seizure disorders, severe peptic ulcer disease and significant hepatic impairment, where risk‑benefit must be carefully considered.
Careful review is required in patients on multiple interacting medicines and in those with recent smoking changes.
Adverse Effects (Post‑Market Pharmacovigilance)
What Side Effects Should Patients Expect?
Common side effects include nausea, headache, tremor, insomnia and palpitations, which often prompt discontinuation in sensitive individuals.
Serious adverse events reported to TGA and international databases include ventricular arrhythmia, severe hypotension and seizures, typically linked to serum concentrations above 20 mg/L or drug interactions.
TGA post‑market reports frequently cite dosing errors, ciprofloxacin co‑prescription and abrupt smoking cessation as proximate causes of toxicity.
Recommended baseline checks include ECG and liver function tests where clinically indicated, plus TDM at steady state after initiation or dose change.
Food Interactions (Alcohol, Caffeine, Diet In Australia)
Do Diet And Alcohol Matter?
Caffeine adds to theophylline’s CNS and cardiac stimulation, so advise patients to limit coffee and energy drinks while taking theophylline.
Heavy alcohol use and febrile illness can alter metabolism and may unpredictably change serum concentrations.
Normal meals do not require special adjustment, but counsel on caffeine intake and to report acute illness or changes in drinking habits.
Drug Combinations To Avoid (TGA Safety Alerts)
Which Medicines Raise The Risk Of Harm?
CYP1A2 inhibitors such as ciprofloxacin and fluvoxamine can significantly raise theophylline concentrations and have been associated with TGA safety alerts.
Macrolide antibiotics may also inhibit metabolism and require close monitoring or alternate therapy when feasible.
Prescribers should avoid co‑prescribing known inhibitors without a clear plan for dose adjustment and prompt TDM.
Enzyme Inducers & Inhibitors (CYP1A2)
Who Lowers Or Raises Theophylline Levels?
Enzyme inducers such as carbamazepine, rifampicin and phenytoin accelerate clearance and can reduce theophylline levels, leading to subtherapeutic effect.
Enzyme inhibitors—commonly ciprofloxacin and some antidepressants—reduce clearance and risk toxicity.
Smoking induces CYP1A2 and lowers concentrations, so smoking cessation requires prompt dose re‑evaluation and TDM to avoid overdose.
Australian Survey Data
What Do Patients Say About Theophylline?
Regional pharmacy audits and small patient cohorts from 2022–24 show mixed experiences in Australia.
Older patients with longstanding COPD often describe perceived symptom benefit from low‑dose theophylline in combination with inhaled therapy.
Many asthma patients prefer inhaled controllers or biologics and seldom request theophylline because of side‑effect concerns.
Sleep disturbance and palpitations are common reasons patients stop therapy without clinician input.
Forum And Pharmacy Trends
What Are Pharmacists And Online Forums Reporting?
Community pharmacists report infrequent dispensing of theophylline and a high rate of counselling on interactions and the need for TDM.
Online patient forums commonly show confusion over slow‑release versus immediate‑release products and questions about Nuelin SR dosing.
Rural patients value theophylline’s low acquisition cost and oral route when specialist access or inhaled therapies are limited.
National Pharmacy Chains
Where Is Theophylline Stocked In Australia?
Modified‑release theophylline products such as Nuelin SR are stocked across major chains including Chemist Warehouse, Priceline and TerryWhite, though turnover is low.
Pharmacists typically check for recent TDM before dispensing and frequently liaise with prescribers on dose adjustments.
Online Pharmacy Growth & E‑Scripts
How Has Access Changed With Telehealth?
Online pharmacies and e‑script services have marginally increased access for urban and remote patients, but pharmacists still require recent TDM before supply in many cases.
In our online pharmacy, theophylline is available without a prescription, with discreet delivery to Australia in 5-14 days.
PBS Vs Private Cost Comparisons
How Much Will Patients Pay?
Because PBS listings for theophylline are limited and product‑dependent, many prescriptions are private and paid out‑of‑pocket unless an Authority item applies.
Theophylline as an older generic tends to be inexpensive to buy, which supports its continued use in cost‑constrained or rural settings despite monitoring needs.
Pharmacists in remote areas report logistic challenges coordinating timely TDM and follow‑up for patients on private prescriptions.
Comparison Of PBS And Non‑PBS Options
What Alternatives Should Clinicians Consider?
First‑line bronchodilation and symptom control remain inhaled short‑acting and long‑acting bronchodilators plus inhaled corticosteroids—most are PBS‑subsidised.
For severe or refractory disease, biologic therapies are an option but are high‑cost and specialist‑led.
Low‑dose theophylline is an oral, low‑acquisition‑cost alternative with potential steroid‑sensitising effects, but it requires monitoring and carries interaction risks.
Pros And Cons Checklist
How To Decide If Theophylline Is Appropriate?
Pros: affordability, oral dosing, potential steroid‑sensitising anti‑inflammatory action in COPD.
Cons: narrow therapeutic window, need for TDM, significant drug interactions and variable efficacy across patient groups.
Checklist For Use: confirm indication, review interacting medicines, ensure TDM access, counsel on toxicity signs, and document rationale and follow‑up plan.
TGA Approval Framework
How Is Theophylline Regulated?
Theophylline formulations are registered on the Australian Register of Therapeutic Goods with product labelling and pharmacovigilance obligations required by the TGA.
Prescribers and pharmacists should check ARTG entries and current product information for up‑to‑date details on strengths and sponsors.
PBS Subsidy Process
How Does A Medicine Get On The PBS?
PBS inclusion requires evidence of clinical efficacy, cost‑effectiveness and clearly defined indications.
Because theophylline is an older generic, PBS listings are selective and may change only after formal submissions and reviews.
Clinicians and patients must confirm subsidy eligibility at the time of prescribing or dispensing.
Is Theophylline Still Used In Australia?
Short Answer For Patients
Theophylline remains in selective use in Australia, mainly for refractory COPD and in settings where oral treatment is preferred or inhaled/biologic options are limited.
How Is Monitoring Done And How Often?
Monitoring Practicalities
TDM is recommended at steady state, typically 3–5 days after initiation or dose change, and after starting or stopping interacting drugs or changing smoking status.
Periodic monitoring thereafter depends on clinical stability and changes in comorbidities or concomitant medicines.
Can I Drink Coffee While Taking Theophylline?
Practical Advice On Caffeine
Moderate caffeine may increase side effects such as tremor, insomnia and palpitations, so advise limiting coffee and energy drinks and report new symptoms.
What Happens If I Stop Smoking While On Theophylline?
Why Smoking Changes Matter
Smoking induces CYP1A2 and speeds up theophylline clearance, so stopping smoking will reduce clearance and raise serum concentrations.
Patients who quit smoking should have prompt dose review and TDM to avoid toxicity.
How Quickly Does Toxicity Develop?
Timing And Warning Signs
Toxicity can develop within days of a dosing error, a new interacting medicine or abrupt smoking cessation.
Severe toxicity—seizures or dangerous arrhythmias—requires immediate emergency department care.
Visual Guide Suggestions
What Visuals Help Patients And Clinicians?
PBS Pricing Flowchart — show steps from GP script to PBS vs private dispensing with typical costs and subsidy flags.
Pharmacy Distribution Heatmap — indicate higher prescribing concentrations in regional hospital clinics and pockets of rural use compared with low community uptake.
Monitoring Timeline Infographic — Day 0 start, Day 3–5 steady state TDM, re‑TDM after interacting drug or smoking change, and toxicity red flags to watch for.
Use clear icons—pill, ECG, lab tube—and reference TGA ARTG entries and recent systematic reviews from 2022–25 where available.
Household Storage Under Australian Climate
How Should Patients Store Their Tablets?
Theophylline tablets and slow‑release formulations are stable at typical Australian ambient conditions but should be kept in a cool, dry place away from heat and humidity.
Keep medicines in original packaging to preserve labelling and to avoid confusion between immediate and modified‑release forms.
Return unused medicines to the pharmacy for safe disposal.
Cold‑Chain Logistics For Pharmacies
Practical Notes For Pharmacies, Especially Rural
No cold chain is required for theophylline, but stock should be stored away from direct sunlight and moisture.
Remote services should coordinate dispensing with local TDM access and consider validated ambient courier options for blood samples when needed.
Document expiry dates carefully on low‑turnover SR stock to avoid wastage.
Pharmacist Counselling Style In Australia
How Should Pharmacists Talk To Patients?
Confirm the indication and formulation—slow‑release versus immediate‑release—before counselling.
Review all concomitant medicines for CYP1A2 interactions and ask about smoking, alcohol and caffeine intake.
Explain signs of toxicity in plain language—nausea, tremor, palpitations, confusion, seizures—and ensure the patient has a TDM plan and follow‑up appointment.
Provide written advice and an action plan for rural patients with limited immediate access to emergency care.
National Health Authority Recommendations
Which Guidelines Apply?
Counselling and monitoring should align with TGA product information and local respiratory guidance such as RACGP and TSANZ recommendations.
Shared decision‑making is essential when considering off‑label low‑dose use, and pharmacists act as an important safety gatekeeper in the PBS‑aware Australian market.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-7 days |
| Gold Coast | Queensland | 5-9 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Geelong | Victoria | 5-9 days |
| Sunshine Coast | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Cairns | Queensland | 5-9 days |
Counselling Checklist For Pharmacists
What To Cover In The Consultation
Confirm the exact product and dose, and whether the prescription is for Nuelin SR or another modified‑release theophylline product.
Ask about all prescribed and over‑the‑counter medicines and highlight specific CYP1A2 interactions such as ciprofloxacin and some antidepressants.
Enquire about smoking, recent cessation or plans to quit and arrange TDM at steady state and after any interacting changes.
Document counselling, provide written information and arrange follow‑up with the prescriber where necessary.
Practical Final Notes
Key Takeaways For Clinicians And Patients
Theophylline can still play a useful role in specific Australian practice settings, particularly low‑dose adjunctive strategies for COPD where TDM is available and cost is a concern.
Safety remains the main limitation—therapeutic drug monitoring, vigilance for interactions such as ciprofloxacin, and prompt dose review after smoking changes are essential.
Pharmacists are well placed to gatekeep safe use by confirming formulation, checking interactions, advising on caffeine and alcohol, ensuring TDM is arranged and documenting clear follow‑up.
When used carefully and monitored, theophylline offers an affordable oral option, but it is not a first‑line replacement for PBS‑subsidised inhaled therapy or specialist biologics where indicated.