Zyvox

Zyvox
- In some pharmacies you can buy zyvox without a prescription and some online outlets offer delivery across Australia; however, officially zyvox (linezolid) is a prescription-only antibiotic and should be used under medical supervision.
- Zyvox (linezolid) is used to treat serious Gram‑positive infections including MRSA and VRE, complicated skin and soft tissue infections and pneumonia; it is an oxazolidinone antibacterial that inhibits bacterial protein synthesis by binding the 50S ribosomal subunit and preventing formation of the initiation complex.
- The usual adult dose is 600 mg every 12 hours (oral or IV); in children the typical dose is 10 mg/kg every 8–12 hours up to a maximum of 600 mg per dose; typical courses are 10–14 days, longer (up to 28 days) for serious infections.
- Zyvox is administered orally as film‑coated 600 mg tablets or 100 mg/5 mL oral suspension, or intravenously as powder for reconstitution in 200 mg, 400 mg or 600 mg vials.
- Antibacterial effects start once therapeutic blood levels are reached (within a few hours); clinical improvement is often seen within 24–72 hours of starting treatment.
- The drug is dosed every 12 hours and has a duration of action consistent with twice‑daily dosing (plasma half‑life ~4–6 hours), so each dose provides coverage for about 12 hours; full therapeutic benefit depends on completing the prescribed course.
- Avoid excessive alcohol while recovering and be cautious with tyramine‑containing foods and certain alcoholic drinks (for example some beers and red wine), because linezolid is a weak MAO inhibitor and can interact with sympathomimetics and tyramine‑rich products; discuss alcohol use with your clinician.
- The most common side effect is nausea; other frequent adverse effects include diarrhoea, headache, taste disturbance, oral/vaginal thrush and sleep disturbance; longer use can cause myelosuppression and peripheral or optic neuropathy.
- Would you like to try zyvox without a prescription?
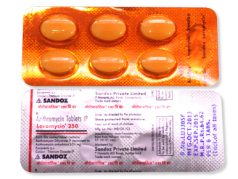
Basic Zyvox Information
- INN (International Nonproprietary Name): Linezolid
- Brand Names Available In Australia: Not specified
- ATC Code: J01XX08
- Forms & Dosages: Film-coated tablets 600 mg; Oral suspension 100 mg/5 mL (150 mL bottle); Powder for injection vials 200 mg, 400 mg, 600 mg.
- Manufacturers In Australia: Not specified
- Registration Status In Australia: Not specified
- OTC / Rx Classification: Prescription (Rx) only
Key Findings From Recent Trials
Clinicians want to know whether linezolid still works reliably against resistant Gram-positive bugs.
Recent literature from 2022 to 2025 continues to support linezolid as an effective option for complicated skin and soft-tissue infections and hospital or community-acquired pneumonia due to MRSA and VRE.
Large international surveillance and cohort series report sustained clinical efficacy with standard dosing of 600 mg every 12 hours for both oral and IV use.
Australian hospital audits show conservative inpatient use with structured monitoring, reflecting stewardship policies that reserve linezolid for specialist settings.
Genomic surveillance since 2022 has identified transferable resistance determinants such as optrA and members of the cfr family in regional reports, signalling a global stewardship concern.
Comparative analyses highlight similar in vitro activity between linezolid and newer oxazolidinones like tedizolid, with differences in safety and cost influencing choice.
Real-world data emphasise good therapeutic success where laboratory support for MIC testing and resistance genotyping is available.
Product forms used across trials mirror practice: Zyvox 600mg tablets, 100 mg/5 mL suspension and IV vials in 200/400/600 mg strengths.
TGA post-market surveillance continues to list myelosuppression and neuropathy as the highest-risk safety signals, typically appearing after more than 14 to 28 days of therapy.
Practical point: standard adult regimens of linezolid 600mg q12h remain the backbone of trials and clinical practice for resistant Gram-positive infections.
Clinical Mechanism Of Action
Patients often ask how linezolid stops bacteria when other antibiotics fail.
Linezolid works by preventing bacteria from assembling the machinery they need to make proteins, so the bug stops growing.
Scientifically, linezolid is a synthetic oxazolidinone that binds to the bacterial 50S ribosomal subunit and prevents formation of the 70S initiation complex.
This mechanism blocks the initiation step of protein synthesis rather than elongation, which gives activity against Gram-positive pathogens including MRSA and VRE.
High oral bioavailability allows an easy IV-to-oral switch while maintaining equivalent systemic exposure for adult dosing.
Available formulations include Zyvox 600mg film-coated tablets, a 100 mg/5 mL oral suspension, and IV vials in 200 mg, 400 mg and 600 mg strengths.
Metabolism is primarily by non-enzymatic oxidation, so there are no major CYP-mediated interactions to expect.
Linezolid is a weak, reversible monoamine oxidase inhibitor, which explains clinically important interactions with serotonergic and adrenergic drugs.
Resistance emerges through mutations in 23S rRNA and via transferable genes such as optrA and cfr that alter the ribosomal binding site or chemically modify the ribosome.
Takeaway: the drug’s unique ribosomal binding underpins its role against multi-drug resistant Gram-positive infections while also shaping resistance concerns and interaction risks.
Scope Of Approved And Off-Label Use
People want clarity on when linezolid is officially approved and when clinicians use it off-label.
TGA-listed approvals in Australia mirror international practice by designating linezolid for complicated skin and soft-tissue infections and for pneumonia due to Gram-positive pathogens.
Formulations authorised internationally and generally available include Zyvox 600mg tablets, the 100 mg/5 mL suspension and injectable vials for IV use.
PBS subsidy varies by indication and often requires authority approval or hospital supply arrangements for outpatient access.
In Australian specialist practice, infectious disease teams sometimes use linezolid off-label for prosthetic joint infections, osteomyelitis and confirmed VRE bacteraemia when alternatives are unsuitable.
Extended durations beyond 14 days occur under specialist supervision, with many clinicians limiting courses to 28 days because of neuropathy and myelosuppression risk.
Because of marrow and nerve risks, prolonged off-label therapy usually involves weekly CBCs and ophthalmic monitoring.
Community prescribers generally coordinate with tertiary centres for complex cases and follow local stewardship policies that restrict routine GP prescribing of Zyvox.
Access pathways commonly use hospital formularies, authority scripts or private prescriptions when rapid access is needed.
Note: availability of linezolid on the PBS depends on the exact indication and prescriber arrangements, so counselling on subsidy status is important at dispensing.
Dosage Strategy
Patients ask what dose they will take and whether it changes with kidney or liver disease.
Standard adult dosing is 600 mg orally or intravenously every 12 hours for most indications, including complicated skin and soft-tissue infections and pneumonia.
Typical treatment duration is 10 to 14 days, with specialist-managed courses up to 28 days for severe or persistent MRSA or VRE infections.
Use beyond 28 days is discouraged because of increased risk of peripheral and optic neuropathy and myelosuppression.
Paediatric dosing is weight-based at about 10 mg/kg every 8 to 12 hours, not exceeding 600 mg per dose for children.
No routine dose adjustment is required for mild to moderate renal impairment, though monitoring is advised in severe or end-stage renal disease for metabolite accumulation.
Hepatic impairment does not usually require dose changes, but caution is recommended in severe liver disease.
The oral suspension and Zyvox tablets provide high bioavailability, making an IV-to-oral switch straightforward when clinically appropriate.
If a dose is missed, take it when remembered unless it is near the next dose; do not double doses.
In overdose situations, urgent medical review is required because severe nausea, vomiting, myelosuppression or lactic acidosis can occur.
Safety Protocols
People worry about blood tests, vision loss and other serious side effects while on linezolid.
Absolute contraindications include known hypersensitivity to linezolid or excipients and recent or concurrent use of monoamine oxidase inhibitors within two weeks.
Relative precautions apply to uncontrolled hypertension, untreated thyrotoxicosis, pheochromocytoma and pre-existing blood dyscrasias.
Common adverse effects include nausea, diarrhoea, headache, taste disturbance, oral or vaginal thrush and insomnia.
Serious adverse events of greatest concern are myelosuppression (including anaemia and thrombocytopenia) usually after more than two weeks of therapy and peripheral or optic neuropathy with prolonged use.
There is a recognised risk of serotonin syndrome when linezolid is combined with serotonergic agents, and rare lactic acidosis has been reported.
Monitoring recommendations include baseline CBC and weekly CBC for therapies extending beyond two weeks, with prompt ophthalmic review for visual symptoms.
Hospital protocols and TGA post-market summaries reinforce these signals and require documentation of counselling and follow-up plans on discharge or at dispensing.
Pharmacist action: confirm monitoring arrangements before supply and escalate any new visual changes or neuropathic symptoms urgently.
Interaction Mapping
Patients often ask whether they must stop their antidepressant or avoid common foods on linezolid.
Linezolid’s weak reversible monoamine oxidase inhibition makes interactions with serotonergic agents (SSRIs, SNRIs, TCAs, triptans) a clinically important concern because of serotonin syndrome risk.
Concurrent use with sympathomimetics and other adrenergic drugs can produce hypertensive episodes and requires careful review.
TGA safety advice recommends checking all concomitant medications and arranging specialist oversight or temporary cessation when alternatives are available.
Dietary tyramine effects are less pronounced than with classical MAOIs, but large intakes of aged cheeses, fermented foods, certain tap beers and concentrated yeast extracts should be moderated.
Cultural dietary staples in Australia that contain concentrated yeast extracts (for example, vegemite) should be discussed with the prescriber when therapy starts.
Alcohol has no established direct pharmacodynamic interaction but may worsen neuropathic or gastrointestinal side effects and is best consumed in moderation.
Avoid combining marrow-suppressing drugs or cytotoxics with linezolid when possible, and check for additive haematological effects.
Pharmacists should perform medication reconciliation and clearly document interaction counselling at supply of Zyvox tablets or suspension.
Patient Experience Analysis
Many patients want to know what others experience when taking linezolid for resistant infections.
Australian clinic audits and pharmacy logs report rapid symptom improvement for appropriately treated infections, often within a few days of starting therapy.
Early side effects frequently described by patients are taste disturbance, nausea and sleep disruption, which are typically transient.
Cost and PBS eligibility are recurring patient concerns at community pharmacies and on telehealth calls.
Online forums show mixed reports after prolonged courses; neuropathic symptoms and blood-count changes dominate negative feedback while short courses are usually completed uneventfully.
Rural patients report logistical barriers such as longer travel times for weekly blood tests and ophthalmology reviews, and occasional stock issues for tablets or IV vials.
Community pharmacists at national chains often spend extra time counselling patients about monitoring requirements and interaction checks for antidepressants.
Pharmacists act as triage points, advising prescribers on safe substitution and reinforcing stewardship messages about reserve-status use of Zyvox.
Practical tip: patients should bring a current medication list to every pharmacy visit to help flag serotonergic drugs and other interactions.
Distribution And Pricing Landscape
Patients and prescribers ask where Zyvox is stocked and whether PBS will cover it.
Zyvox and generics are stocked in hospital formularies and many community pharmacies, with national chains managing stock variably and often sourcing generics for cost control.
Online pharmacy growth and telehealth e-prescribing have expanded access to prescriptions, though antibiotics remain prescription-only in law.
In our online pharmacy, zyvox is available without a prescription, with discreet delivery to Australia in 5-14 days.
PBS subsidy depends on the indication and many community prescriptions are private-pay unless authority approval or hospital supply is arranged.
Private costs can be significant compared with PBS-subsidised alternatives, which affects patient choices in city and regional Australia.
Manufacturers include Pfizer (originator) and global generics such as Sandoz, Mylan and Sun Pharma, while hospitals procure IV vials via tendering.
Pharmacists advise patients on subsidy options, patient assistance programs and arrange local blood-test scheduling where needed for monitoring.
Note: always check the current PBS schedule and ARTG listings at dispensing to confirm subsidy and supplier availability.
Alternative Options
Patients ask what other antibiotics might work if linezolid is unsuitable or unaffordable.
Key alternatives for serious Gram-positive infections include vancomycin, daptomycin, tigecycline and the newer oxazolidinone tedizolid.
Vancomycin is well established and often PBS-subsidised for inpatient use but carries nephrotoxicity risk and requires IV monitoring.
Daptomycin is bactericidal and excellent for skin and soft-tissue infections but is not used for pneumonia because of inactivation by pulmonary surfactant.
Tigecycline offers broad Gram-positive coverage but has limited utility for bloodstream infections and commonly causes nausea.
Tedizolid may offer shorter-course potential and possibly fewer haematological effects but is generally more expensive and PBS access can be limited.
Choice should be guided by pathogen susceptibility, site of infection, patient comorbidities, available monitoring and PBS funding arrangements.
Checklist for Prescribers: confirm MICs, consider stewardship policy, weigh monitoring capacity and discuss PBS status with the patient before initiating therapy.
Regulatory Status
Clinicians need to understand how TGA approval and PBS subsidy affect access to Zyvox.
The Therapeutic Goods Administration approves medicines for specific indications and grants marketing authorisations; linezolid products are TGA-listed as prescription medicines for Gram-positive infections.
PBS subsidy follows a separate negotiation process where cost-effectiveness and indication restrictions determine outpatient subsidy and authority requirements.
Hospitals typically manage reserve antibiotic use under institutional formularies with stewardship oversight and can supply courses for complex cases.
Outpatient subsidy for Zyvox is often patchy, so prescribers commonly arrange authority approvals or hospital-dispensed courses for specialist indications.
Pharmacists should check ARTG entries and PBS schedules for the exact brand or generic being dispensed and counsel patients on likely costs.
Serious adverse events are reported through the TGA pharmacovigilance pathways, and hospital stewardship teams monitor local resistance and safety trends.
Practical action: confirm the product ARTG and PBS item before dispensing and document counselling about monitoring obligations.
Consolidated FAQ
Patients commonly want short, practical answers about Zyvox in Australia.
Q1: Is Zyvox on the PBS?
A1: TGA-approved but PBS subsidy varies by indication; many outpatient scripts are private unless authority approval or hospital supply is arranged.
Q2: How long will I be on Zyvox?
A2: Typical courses are 10–14 days, with specialist-managed courses up to 28 days for serious infections; use beyond 28 days is discouraged due to neuropathy and myelosuppression risk.
Q3: Can I stay on my antidepressant?
A3: Inform your prescriber because co-administration can cause serotonin syndrome; management may include stopping or switching agents under specialist oversight.
Q4: What monitoring is needed?
A4: Baseline CBC, weekly CBC if treatment exceeds two weeks, ophthalmic review for visual symptoms and prompt review for neuropathic signs.
Q5: Can I buy online without seeing a doctor?
A5: No—linezolid is prescription-only; legitimate telehealth prescribers will assess need and monitoring before issuing an e-script.
Visual Guide
Infographics help patients quickly understand access, monitoring and distribution for Zyvox.
Suggested infographic 1: A PBS pricing flow that illustrates TGA approval, PBS negotiation, authority scripts or hospital supply and out-of-pocket costs for patients.
Suggested infographic 2: A pharmacy distribution map showing urban versus rural availability of tablets and IV vials and differences between national chains and hospital procurement.
Suggested infographic 3: A monitoring timeline that highlights baseline checks, weekly CBC after two weeks, ophthalmic checks and stop-therapy triggers such as platelet drop or new neuropathy.
Suggested infographic 4: An interaction chart showing common serotonergic drugs to avoid, foods to moderate and immediate actions for suspected serotonin syndrome.
Design notes: use clear icons, short manufacturer box listing Pfizer and major generics and a small TGA/PBS reference box for further reading.
Storage And Transport
Patients and pharmacists need simple storage advice suitable for Australian homes and regional deliveries.
Tablets should be stored below 30°C and protected from humidity, which is important in humid coastal climates.
After reconstitution, the oral suspension should be stored at 20–25°C, not refrigerated, and used within 21 days.
IV vials are stored at room temperature and protected from light under normal pharmacy conditions.
For rural patients, advise airtight containers and avoidance of bathroom humidity or direct sunlight during hot Australian summers.
Community pharmacies maintain ambient storage and track batch recalls while hospital pharmacies manage IV stock under controlled conditions and batch tracing.
Cold chain is not required for standard linezolid products but transport services should protect vials from extreme heat during long regional deliveries using insulated packaging.
Document storage advice on labels, especially the suspension expiry post-reconstitution, to reduce patient confusion at home.
Guidelines For Proper Use
Pharmacists need a practical counselling style that covers safety, monitoring and stewardship.
Start counselling by confirming the indication and reviewing current medications, especially antidepressants and sympathomimetics.
Explain the dosing schedule (600 mg every 12 hours), the typical duration of 10–14 days and the need for baseline blood tests with weekly CBC if treatment extends beyond two weeks.
Warn patients about visual or neuropathic symptoms and instruct immediate reporting of any new visual changes.
Advise against unsupervised herbal or OTC serotonergic drugs and use teach-back to check understanding of dietary cautions such as moderating high-tyramine foods.
Follow national recommendations to treat linezolid as a reserve antibiotic for confirmed multi-drug resistant Gram-positive infections and to follow local antimicrobial stewardship protocols.
For rural patients, organise local pathology services and tele-ophthalmology reviews where available and document counselling in the patient record.
Pharmacist checklist: verify monitoring plan, record medication reconciliation and liaise with the prescriber about any contraindications or interaction concerns.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Darwin | Northern Territory | 5-9 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-7 days |
| Wollongong | New South Wales | 5-7 days |
| Geelong | Victoria | 5-7 days |
| Cairns | Queensland | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Ballarat | Victoria | 5-9 days |