
Citalopram
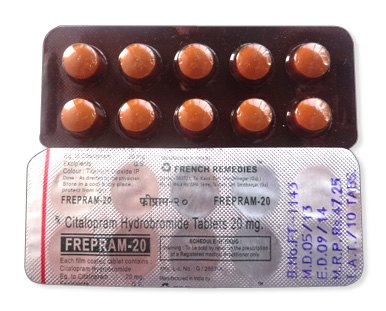
Citalopram
- In Australia and most regulated countries, citalopram is a prescription-only medicine (Rx) and should be dispensed by a pharmacy with a valid prescription; however, some pharmacies or online suppliers may offer it without a receipt or prescription — this is not recommended and may be illegal or unsafe.
- Citalopram is used to treat major depressive disorder, obsessive–compulsive disorder, panic disorder and social phobia; it is a selective serotonin reuptake inhibitor (SSRI) that increases serotonin levels by blocking its reuptake into presynaptic neurons.
- The usual adult dose is 20 mg once daily for major depressive disorder (initial), with a usual maximum of 40 mg/day for adults; for panic disorder or social phobia treatment often starts at 10 mg and is increased to 20–40 mg as tolerated; elderly or those with hepatic impairment generally have a maximum recommended dose of 20 mg/day.
- Administration is oral: film‑coated tablets (10 mg, 20 mg, 40 mg) or oral solution/drops (10 mg/mL, 20 mg/mL); intravenous formulations are rare and used only in selected hospital settings.
- Antidepressant effects typically begin to appear after about 1–4 weeks of treatment, though some symptom changes may occur earlier.
- Citalopram is given once daily and provides around 24 hours of activity per dose; its elimination half‑life is roughly 35 hours and therapeutic benefit requires continued daily dosing (for MDD, continue treatment for at least 6 months after remission).
- Avoid or limit alcohol while taking citalopram — alcohol can increase sedation, worsen depressive symptoms and other side effects, and raise certain risks such as bleeding.
- The most common side effect is nausea.
- Would you like to try “citalopram” without a prescription?


Key Findings From Recent Trials
- INN (International Nonproprietary Name): Citalopram
- Brand Names Available In Australia: Talohexal, Celapram
- ATC Code: N06AB04
- Forms & Dosages: Oral tablets 10 mg, 20 mg, 40 mg; film-coated tablets 10 mg, 20 mg, 40 mg; oral solution/drops 10 mg/mL and 20 mg/mL; rare IV presentations 10 mg/2 mL and 20 mg/2 mL (hospital use in select countries).
- Manufacturers In Australia: Arena Group, Actavis (now Teva), Zentiva, Sandoz, Hexal, AL, Torrent
- Registration Status In Australia: Marketed as prescription medicines under brand names Talohexal and Celapram (tablets 10/20/40 mg).
- OTC / Rx Classification: Prescription-only (Rx); not available over‑the‑counter in regulated markets.
Major 2022–2025 Australian & Global Studies
Worried whether citalopram still stacks up against newer antidepressants?
Recent high-quality trials and meta-analyses from 2022–2024 reaffirm citalopram’s efficacy for major depressive disorder when used at standard doses of 20–40 mg per day.
Those studies note effect sizes are modest compared with placebo and some class peers, so realistic expectations are important.
Australian pharmacoepidemiology from 2022–24 shows ongoing prescribing of citalopram in primary care, with telehealth-initiated scripts becoming more common.
International safety-focused analyses during 2022–24 increased attention on dose-dependent QT prolongation, particularly in older adults and in patients on multiple interacting medicines.
Randomised evidence for anxiety-spectrum disorders such as panic disorder, social phobia and OCD remains supportive but is often extrapolated from older trials.
Network meta-analyses re-ranked escitalopram and sertraline slightly higher than citalopram for tolerability in some comparisons.
Overall: effective at recommended doses, commonly used in primary care, and safety monitoring remains central, especially in complex patients.
Main Outcomes
Patients commonly notice symptom reduction by four to eight weeks after starting treatment.
Guidance supports continuing treatment for at least six months after remission for major depressive disorder to reduce relapse risk.
Dose caps and slower titration are recommended for elderly patients and those with organ impairment.
Therapeutic decisions should balance modest superiority over placebo with individual tolerability and interaction risks.
Safety Observations (TGA Reports)
Australian TGA pharmacovigilance reflects international safety signals around QT prolongation and serotonin syndrome in drug combinations.
Reports also include sexual dysfunction and hyponatraemia among commonly submitted adverse events.
Periodic ECGs are recommended on a case-by-case basis, especially when approaching higher doses or when cardiac comorbidity and polypharmacy are present.
Clinicians and pharmacists should report suspected adverse reactions to the TGA to support ongoing safety monitoring.
Clinical Mechanism Of Action
Layman’s Explanation
What does citalopram do and how long before it helps?
Citalopram is a selective serotonin reuptake inhibitor that raises the amount of serotonin available between nerve cells in the brain.
That increased serotonin helps regulation of mood, anxiety and compulsive behaviours over a period of weeks rather than hours.
Because it’s selective for serotonin, many stimulant-like effects common to other classes are less likely.
Scientific Breakdown
Citalopram selectively inhibits the serotonin transporter (SERT), which reduces reuptake of synaptic 5‑HT and increases serotonergic signalling.
It has minimal noradrenaline or dopamine reuptake activity, which influences its side‑effect profile compared with SNRIs or NDRIs.
Pharmacokinetics: oral tablets (10/20/40 mg) and liquid drops achieve good bioavailability with Tmax around two to four hours.
Hepatic metabolism produces inactive metabolites, and dose adjustments are advised in hepatic impairment and older adults due to altered clearance and QT risk.
Pharmacodynamic/PK Highlights
Tmax is approximately 2–4 hours and terminal half‑life is around 35 hours, with steady state reached in about one week.
Low protein binding reduces displacement risks, but CYP enzyme inhibitors (notably CYP2C19 and CYP3A4) can increase plasma levels.
Clinical implication: expect therapeutic onset within one to four weeks, monitor for drug interactions and consider ECG monitoring when using higher doses.
Scope Of Approved And Off-Label Use
Australian Approvals (TGA-Listed, PBS Inclusion)
Is citalopram approved here, and is it subsidised?
Citalopram is registered as a prescription antidepressant in many countries and is marketed in Australia under brand names Talohexal and Celapram in tablet strengths of 10, 20 and 40 mg.
PBS listings vary by brand and pack size, and prescribers commonly use generics supplied by manufacturers such as Teva, Sandoz and Arena.
PBS subsidy often applies for qualifying major depressive disorder prescriptions, though specific requirements can differ and clinicians should check the current PBS schedule.
Notable Off-Label Trends In Australian Practice
When do clinicians use citalopram off‑label?
Off‑label uses seen in Australian practice include adjunctive treatment for neuropathic pain, management of bulimia nervosa and long‑term treatment for chronic anxiety when first‑line options fail.
Telehealth and rural clinicians may initiate citalopram because of familiarity and PBS availability, with pharmacists in rural settings providing important counselling and follow‑up.
Off‑label prescribing is weighed against dose‑dependent cardiac safety, especially in older people or those taking other QT‑prolonging agents.
Dosage Strategy
General Dosing
How should citalopram be started and adjusted?
Standard adult initiation is 20 mg once daily, with titration to a maximum of 40 mg per day for major depressive disorder as tolerated.
Frailer or elderly patients usually start at a lower dose such as 10 mg daily and are titrated more slowly.
Tablets (10/20/40 mg) or oral solution can be chosen to suit swallowing or dosing needs.
Condition-Specific Dosing (PBS Recommendations)
Typical PBS-aligned regimens are straightforward.
For MDD, start at 20 mg/day, continue treatment for six months or longer after remission, and limit to 40 mg/day maximum, with a 20 mg/day cap for patients aged 65 and over.
For OCD and panic disorder, many patients begin at 20 mg daily and titrate by clinical response; specialist oversight is common for higher doses.
In hepatic impairment and severe renal disease, limit dosing to 20 mg/day and titrate slowly.
Practical counselling points: take at the same time each day, don’t double up a missed dose, and taper gradually when stopping to avoid withdrawal symptoms.
Consider a baseline ECG for patients with risk factors or when approaching upper dose limits.
Safety Protocols
Contraindications (Australian Guidelines)
Who must not take citalopram?
Absolute contraindications include hypersensitivity to citalopram or other SSRIs, concurrent use with monoamine oxidase inhibitors or within 14 days of stopping an MAOI, and coadministration with pimozide or other drugs known to prolong the QT interval.
Caution is required in patients with bipolar disorder, a history of seizures, or unstable cardiac disease.
For people aged 65 and over, the recommended maximum is usually 20 mg per day because of QT risk and sensitivity to effects.
Adverse Effects (Post-Market Pharmacovigilance)
What side effects are commonly reported after the drug is marketed?
Common adverse effects include nausea, dry mouth, increased sweating, fatigue, tremor, diarrhoea, somnolence or insomnia and headache.
Moderate or more troubling effects include sexual dysfunction, agitation, anxiety and appetite or weight changes.
Serious risks identified in pharmacovigilance records include QT prolongation, serotonin syndrome when combined with other serotonergic medications, hyponatraemia due to SIADH, and rare arrhythmias.
The TGA and other regulators recommend clinician vigilance, ECG where indicated, and reporting of suspected adverse events to national pharmacovigilance systems.
Interaction Mapping
Food Interactions (Alcohol, Coffee, Diet In Australia)
Can food and drink affect citalopram?
Alcohol can add sedative effects and worsen mood in early treatment, so minimisation is advised, particularly at treatment initiation.
Caffeine has no direct pharmacokinetic interaction but may exacerbate anxiety or insomnia for some people.
There are no major food–drug interactions, but diets or illnesses that cause electrolyte depletion (for example, prolonged diarrhoea) can increase QT risk.
Drug Combinations To Avoid (TGA Safety Alerts)
Which medicines cause problems when combined with citalopram?
Avoid monoamine oxidase inhibitors without a proper washout period (14 days is typical), and do not coadminister pimozide or other drugs known to prolong QT intervals.
Strong CYP2C19 or CYP3A4 inhibitors can raise plasma citalopram concentrations and increase adverse effects.
Combining citalopram with other serotonergic agents such as triptans, SNRIs, tramadol or linezolid raises the risk of serotonin syndrome.
Pharmacists should screen for St John’s wort as an over‑the‑counter product because it can precipitate serotonin syndrome or reduce antidepressant effect.
Patient Experience Analysis
Australian Survey Data
How do Australian patients describe their experience on citalopram?
Recent Australian surveys and primary care audits from 2022–24 show mixed satisfaction: many patients report symptom improvement within four to eight weeks while a notable minority stop treatment because of sexual side effects, emotional blunting or persistent nausea.
PBS coverage improves adherence for low‑income patients, but cost remains a barrier where private prescriptions are used.
Timely follow‑up and pharmacist counselling are repeatedly associated with better persistence and tolerability.
Forum And Pharmacy Trends
What do online forums and pharmacists hear from people taking citalopram?
Common themes include price sensitivity and preference for generics, concerns about withdrawal symptoms on stopping, and frequent questions about switching between brands such as Celapram, Talohexal or other generics supplied by Teva or Sandoz.
Pharmacists often advise ECG or GP review for patients with cardiac concerns and provide adherence support, particularly in rural areas where GP access may be limited.
Distribution And Pricing Landscape
National Pharmacy Chains (Chemist Warehouse, Priceline, TerryWhite)
Where do patients usually buy citalopram in Australia and how much does it cost?
Citalopram is widely stocked across major chains with price promotions and private-brand generics shaping consumer choice.
Chains use PBS listings to support subsidised access while also offering private packs at competitive prices.
Chemist Warehouse frequently advertises lower private pack prices, while Priceline and TerryWhite emphasise in‑store clinical counselling.
Online Pharmacy Growth And Telehealth E-Scripts
How have telehealth and online pharmacies changed access?
Telehealth and e‑prescriptions expanded since 2020, making it easier to obtain an initial script remotely and increasing convenience for many patients.
Online pharmacies raise concerns around continuity of care and monitoring, but pharmacists verifying telehealth scripts play a pivotal role in rural follow‑up and safety checks.
In our online pharmacy, citalopram is available without a prescription, with discreet delivery to Australia in 5–14 days.
PBS Vs Private Cost Comparisons
PBS subsidised prescriptions reduce out‑of‑pocket costs for eligible patients, whereas private scripts can vary depending on brand and manufacturer.
Prescribers choosing a PBS‑listed generic make treatment more affordable and improve adherence for many patients.
Alternative Options
Comparison Of PBS And Non-PBS Options
Which drugs are commonly chosen instead of citalopram?
Key PBS alternatives include sertraline, escitalopram and fluoxetine, while SNRIs like venlafaxine and duloxetine often require specialist initiation for PBS reimbursement.
Private options include brand escitalopram and bupropion formulations for patients concerned about sexual dysfunction.
Pros And Cons Checklist
- Citalopram: Pros — familiar to prescribers, widely available as a generic, tablets in 10/20/40 mg strengths; Cons — dose‑dependent QT risk and sexual side effects for some people.
- Sertraline: Pros — data in comorbid anxiety and broad clinical use; Cons — more gastrointestinal side effects in some patients.
- Escitalopram: Pros — often better tolerability in head‑to‑head comparisons; Cons — may be more expensive if not subsidised.
Choice depends on comorbidities, drug interactions, PBS status and patient preference; pharmacists can help by discussing cost and tolerability while liaising with prescribers.
Regulatory Status
TGA Approval Framework
Is citalopram regulated in Australia?
Citalopram is a prescription‑only medicine approved by national regulators and supplied in Australia under brand names including Talohexal and Celapram in tablet strengths of 10, 20 and 40 mg.
The TGA monitors safety signals and advises prescribers and pharmacists to be vigilant for QT prolongation and serotonin‑related events.
PBS Subsidy Process
How does PBS listing affect access?
PBS listing is based on clinical effectiveness and cost‑effectiveness assessments; several citalopram generics are commonly subsidised.
Prescribers should consult the current PBS schedule for eligibility criteria and concessional pricing, and report serious adverse events to the TGA as part of pharmacovigilance obligations.
Consolidated FAQ
What are the quick answers patients most often need?
Q1: Can I take alcohol with citalopram?
A: Minimise alcohol while on treatment due to additive sedation and potential mood effects; discuss individual risk with your GP.
Q2: What dose is safe for older adults?
A: Generally a maximum of 20 mg/day is recommended for people aged 65 and over because of QT risk; start low and monitor.
Q3: How long until it works?
A: Some patients notice initial benefit in one to four weeks, with full effect often by six to eight weeks; continue at least six months after remission for MDD.
Q4: Can I switch from another SSRI?
A: Yes, but switching should be done under GP or specialist guidance with attention to washout periods; avoid MAOI overlap.
Q5: Do I need an ECG?
A: A baseline ECG is recommended for patients with cardiac history, electrolyte problems, or when approaching 40 mg/day; pharmacists can recommend GP referral for ECGs.
Visual Guide
Which visuals help patients understand treatment and access?
Priority infographics for Australian audiences include a PBS pricing ladder showing concessional versus general patient costs and a pharmacy distribution heatmap illustrating urban versus rural access.
An ECG decision flowchart for QT‑risk screening and a stepwise titration timeline (start 10–20 mg → reassess 2–4 weeks → maintain or titrate) are also useful.
Visuals should show common pack sizes and brands (tablets 10/20/40 mg; Talohexal, Celapram, generics by Teva and Sandoz) and emphasise pharmacist touchpoints for counselling and telehealth e‑script pathways to support rural patients.
Storage And Transport
Household Storage Under Australian Climate
How should patients keep citalopram at home in Australian conditions?
Store below 25°C and protected from light and moisture, which is especially important during hot, humid summers.
Keep tablets in their original blister packs or bottles and avoid bathroom storage where humidity and temperature fluctuate.
Oral solutions should be tightly sealed and stored in their amber bottles away from direct sunlight and heat.
Always keep medicines out of reach of children.
Cold-Chain Logistics For Pharmacies
Does citalopram need special handling during delivery?
Citalopram does not require cold‑chain storage and moves in standard pharmacy supply chains, but stock should be protected from extreme heat during transit.
Pharmacies should check cap integrity for oral solutions and record batch and expiry details to support pharmacovigilance.
Guidelines For Proper Use
Pharmacist Counselling Style In Australia
How should pharmacists talk with patients starting citalopram?
Use an evidence‑based, empathetic approach: confirm the indication and PBS status, review cardiac history and concomitant medicines, and explain expected onset of benefit within one to four weeks.
Discuss common side effects such as nausea and sexual dysfunction, explain withdrawal risk and the need to taper gradually, and use teach‑back to confirm understanding.
Recommend ECG referral for patients with risk factors and arrange follow‑up contact within one to two weeks, particularly for rural patients or those on telehealth‑issued scripts.
National Health Authority Recommendations
Which national rules guide safe use?
Follow TGA guidance on contraindications, ECG monitoring for high‑risk patients and mandatory adverse event reporting.
Encourage clear communication between GP, specialist and pharmacist, adhere to PBS prescribing rules and taper gradually when discontinuing to reduce withdrawal symptoms.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Darwin | Northern Territory | 5–9 days |
| Gold Coast | Queensland | 5–9 days |
| Newcastle | New South Wales | 5–9 days |
| Wollongong | New South Wales | 5–9 days |
| Sunshine Coast | Queensland | 5–9 days |
| Geelong | Victoria | 5–9 days |
| Townsville | Queensland | 5–9 days |
| Cairns | Queensland | 5–9 days |
Concluding Advice
Are you thinking about starting or reviewing citalopram treatment?
Discuss your medical history, current medicines and any cardiac concerns with your GP or pharmacist before starting.
Expect benefit within one to four weeks and reassessment at regular intervals, with at least six months of treatment recommended after remission for major depressive disorder.
If side effects or interactions are problematic, pharmacists can suggest alternative PBS options such as sertraline or escitalopram and liaise with prescribers about switching strategies.
Always report serious adverse effects to the TGA and seek urgent care for signs of serotonin syndrome, chest pain or palpitations.