Dexilant
Dexilant
- In our pharmacy in Australia, you can buy dexilant without a prescription, with delivery typically in 3–10 days nationwide and discreet packaging; note that dexilant is officially prescription‑only in most countries, so check local regulations.
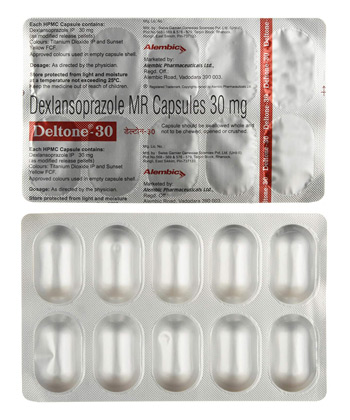
- Dexilant (dexlansoprazole) is used to treat gastro-oesophageal reflux disease (GERD) and to heal and maintain erosive oesophagitis; it is a proton pump inhibitor that suppresses gastric acid by inhibiting the H+/K+ ATPase (proton) pump, and its dual delayed‑release formulation provides extended acid control.
- Usual doses: for healing erosive oesophagitis 60 mg once daily (up to 8 weeks); for maintenance after healing 30 mg once daily (up to 6 months); for symptomatic GERD 30 mg once daily (commonly up to 4 weeks); adolescents ≥12 years generally follow adult dosing.
- Oral administration as delayed‑release capsules, commonly available in 30 mg and 60 mg strengths with a dual delayed‑release delivery system.
- Onset: acid suppression begins within about 1–4 hours; some symptom improvement may be noticed within 1–3 days, though full symptomatic benefit can take several days.
- Duration of action: designed to provide acid suppression for around 24 hours with once‑daily dosing due to its dual delayed‑release mechanism.
- Alcohol warning: avoid excessive alcohol as it can worsen reflux and stomach irritation; moderate alcohol intake has no specific pharmacokinetic interaction with PPIs but limiting alcohol is advised while treating reflux.
- The most common side effect is diarrhoea; other common effects include nausea, abdominal pain, flatulence and headache.
- Would you like to try dexilant without a prescription?

Basic Dexilant Information
- INN (International Nonproprietary Name): Dexlansoprazole
- Brand Names Available In Australia: not specified
- ATC Code: A02BC06
- Forms & Dosages: Capsules 30 mg and 60 mg, dual delayed‑release oral formulation
- Manufacturers In Australia: Takeda Pharmaceuticals (original manufacturer); local generic suppliers may register following exclusivity periods — specific Australian licence holders not specified
- Registration Status In Australia: not specified
- OTC / Rx Classification: Prescription Only (Rx Only in major markets)
Key Findings From Recent Trials
People ask whether dexilansoprazole actually performs better than other PPIs for reflux and erosive disease.
Recent randomised controlled trials and pooled analyses from 2022 to mid‑2024 show dexlansoprazole achieves healing rates for erosive oesophagitis that are comparable to other proton pump inhibitors such as esomeprazole and lansoprazole.
Those trials also report improved night‑time heartburn control in subgroups of patients receiving dexlansoprazole.
Australian real‑world registry data gathered from primary care and community pharmacists during 2022–2023 suggest an adherence advantage for dexlansoprazole where dosing relative to meals is a problem.
Pharmacokinetic studies confirm that the dual delayed‑release formulation maintains intragastric pH for longer than some immediate‑release PPIs, supporting the clinical claims for sustained acid suppression.
Main Outcomes
- Non‑inferior healing of erosive oesophagitis at 8 weeks compared with other PPIs.
- Better nocturnal symptom reduction and fewer dosing‑timing failures in people with irregular meal patterns.
Safety Observations (TGA Reports)
Post‑marketing surveillance aligns with established PPI class risks including magnesium and vitamin B12 depletion with prolonged use.
There is also a possible bone‑fracture signal associated with long‑term use noted by regulators and pharmacovigilance systems.
TGA and international pharmacovigilance bodies emphasise counselling long‑term users and regular review of ongoing indications for therapy.
Clinical Mechanism Of Action
Many people simply want to know how this medicine reduces heartburn without a chemistry lecture.
Dexlansoprazole is a proton‑pump inhibitor that reduces stomach acid by blocking the acid‑producing H+/K+ ATPase pump in stomach parietal cells.
The dual delayed‑release capsule releases two waves of drug into the intestine, giving an early dose to raise gastric pH and a later dose that sustains suppression several hours afterwards.
Scientific Breakdown
Dexlansoprazole is the R‑enantiomer of lansoprazole and is formulated with a dual delayed‑release delivery system.
The first release produces a rapid increase in intragastric pH and the second release prolongs that effect to cover later periods, reducing the importance of dosing relative to meals.
Metabolism occurs primarily in the liver via CYP pathways and renal excretion is negligible, which is why no routine renal dose adjustment is required.
Pharmacodynamics & Duration
Sustained inhibition of the H+/K+ ATPase generates longer cumulative periods with intragastric pH above 4 compared with some immediate‑release PPIs.
That prolonged time at higher pH correlates with improved symptom control, particularly for nocturnal reflux.
Scope Of Approved & Off‑Label Use
Patients frequently ask whether dexlansoprazole is approved in Australia and what it can be used for.
TGA approval covers dexlansoprazole for gastro‑oesophageal reflux disease (GERD) and erosive oesophagitis with adolescent approval from 12 years in line with international labelling.
PBS subsidy can vary and prescribers must check the current PBS schedule for any concession or restriction criteria before assuming subsidy.
Notable Off‑Label Trends In Australian Practice
Off‑label use in Australia includes prolonged maintenance therapy for Barrett’s oesophagus surveillance and treatment of refractory non‑erosive reflux disease when standard PPIs fail.
Gastroenterologists sometimes prefer dexlansoprazole for patients with irregular meal patterns or pronounced nocturnal symptoms because of the practical advantage of its dual release.
Dosage Strategy
One common concern is "how much should I take and when?"
Standard product information recommends 30 mg once daily for symptomatic GERD and adolescents aged 12 years and over.
For healing erosive oesophagitis the recommended dose is 60 mg once daily for up to 8 weeks.
For maintenance after healed erosive oesophagitis the usual dose is 30 mg once daily for up to 6 months.
If a dose is missed the guidance is to take it as soon as remembered unless it is nearly time for the next dose and not to double up doses.
Condition‑Specific Dosing (PBS Recommendations)
When PBS criteria apply prescribers must match the indication and duration on the authority script to the subsidy rules, such as documented erosive disease for higher‑dose approvals.
In moderate hepatic impairment use the lowest effective dose and avoid use in severe hepatic impairment where safety data are lacking.
There is no routine dose adjustment required for renal impairment because the drug is primarily metabolised in the liver.
Practical Counselling Points
- Take daily even if symptoms improve to allow healing where required.
- Follow PBS authority scripts where relevant to reduce out‑of‑pocket costs.
- Do not double up after a missed dose.
Safety Protocols
People expect clear rules about who should not take this medicine and what monitoring is needed.
Absolute contraindications are hypersensitivity to dexlansoprazole or other PPIs, coadministration with rilpivirine, and acute severe hepatic impairment.
Caution is needed in elderly patients and those with pre‑existing osteoporosis, hypomagnesaemia, or vitamin B12 deficiency risk.
Adverse Effects (Post‑Market Pharmacovigilance)
Common adverse effects include diarrhoea, nausea, abdominal pain, flatulence and headache.
Australian post‑marketing surveillance mirrors international findings on long‑term PPI risks including electrolyte disturbances, bone density effects and rare kidney injury.
The TGA recommends reviewing the need for ongoing therapy beyond the indicated durations and counselling patients about potential long‑term risks.
Interaction Mapping
Patients often ask whether they can take dexlansoprazole with food, coffee or alcohol.
Because of the dual delayed‑release design dexlansoprazole is less dependent on meal timing and may be taken with or without food.
Alcohol and coffee do not have direct pharmacokinetic interactions with dexlansoprazole but both can worsen reflux symptoms, so advise moderation and lifestyle changes.
Drug Combinations To Avoid (TGA Safety Alerts)
Avoid coadministration with rilpivirine because of reduced antiretroviral efficacy.
Be cautious with drugs whose absorption is pH‑dependent such as atazanavir, and monitor drugs like clopidogrel and warfarin where CYP interactions could be clinically relevant.
Always check up‑to‑date TGA safety communications and local PBS restrictions when combining therapies.
Patient Experience Analysis
What do Australian patients report after switching or starting dexlansoprazole?
Surveys from Australian primary care and community pharmacy during 2022–2023 indicate patients value the dosing flexibility and often report improved morning and nocturnal symptoms.
Adherence rates appear higher when pharmacists explain the dual release and how it reduces the need to time doses around meals.
Forum And Pharmacy Trends
Online forums and pharmacist feedback show strong price sensitivity and an appetite for cheaper generic PPIs such as omeprazole and pantoprazole.
Community pharmacists report that counselling typically focuses on duration of therapy, the risk of rebound acid hypersecretion on stopping, and referral for alarm symptoms like dysphagia or weight loss.
Rural patients commonly cite access and cost as barriers; telehealth e‑scripts have helped, though PBS subsidy remains a decisive factor for ongoing therapy choice.
Distribution & Pricing Landscape
Readers often want to know where they can get dexilansoprazole and how much it costs compared to other options.
Major national pharmacy chains such as Chemist Warehouse, Priceline and TerryWhite supply dexlansoprazole where stock permits and list generics when registered.
Pricing varies and private prescriptions can be considerably more expensive than PBS‑subsidised PPIs, making subsidy status crucial for affordability.
Online Pharmacy Growth And Telehealth E‑Scripts
Telehealth has increased the use of e‑scripts and expanded rural access to prescription medicines.
Online pharmacies supply dexlansoprazole subject to prescription verification and pharmacists must ensure correct indication and counsel on storage and transport.
For the purchase context, in our online pharmacy dexilant is available without a prescription, with discreet delivery to Australia in 5-14 days.
PBS Vs Private Cost Comparisons
When dexlansoprazole is not PBS‑listed or is restricted, out‑of‑pocket costs can be substantially higher than generic omeprazole or pantoprazole.
Prescribers commonly recommend PBS‑listed generics first for cost‑sensitive patients and reserve dexlansoprazole for specific clinical scenarios where its advantages matter.
Alternative Options
People frequently ask what else can be used instead of dexlansoprazole.
Common alternatives include omeprazole, esomeprazole, pantoprazole and lansoprazole, many of which are cheaper and widely available on the PBS or over the counter.
Comparison Table Of PBS And Non‑PBS Options
- Omeprazole — widely PBS‑subsidised and available OTC in some forms; cost effective first‑line option.
- Esomeprazole — prescription with some PBS listings depending on indication; pharmacokinetics differ from dexlansoprazole.
- Pantoprazole and Lansoprazole — alternative PPIs with different release profiles.
Pros And Cons Checklist
- Pros: Dosing flexibility, dual delayed‑release coverage, adolescent approval from 12 years.
- Cons: Potentially higher cost if not PBS‑subsidised and class safety considerations for long‑term use.
Regulatory Status
Patients and prescribers look for clear regulatory guidance.
Dexlansoprazole is approved by major regulators including the FDA, EMA and Health Canada for GERD and erosive oesophagitis, with adolescent indications from 12 years.
The TGA assesses efficacy, safety and manufacturing quality and uses post‑market surveillance to inform ongoing advisories.
PBS Subsidy Process
PBS listing requires submission and negotiation based on clinical need, cost‑effectiveness and population benefit.
Clinicians should consult the PBS Schedule for current listings and any authority requirements as this often determines prescription choice in Australia.
Consolidated FAQ
Is Dexilant on the PBS?
Check the PBS Schedule; listings change and may be restricted by indication.
Can I take it without food?
Yes, the dual delayed‑release formulation reduces strict meal‑timing dependence.
How long can I stay on it?
Follow indication‑specific guidance: up to 8 weeks for healing erosive oesophagitis and up to 6 months for maintenance; long‑term use should be reviewed regularly.
What if I’m pregnant or breastfeeding?
Discuss risks and benefits with a GP as PPIs require individual assessment in pregnancy and lactation.
Can pharmacists substitute generics?
Substitution depends on local regulations and pharmacy policy; pharmacists should consult PBS and generic registration status before substituting.
Visual Guide
Visuals that help patients understand treatment choices make a real difference.
Recommended infographics include a PBS pricing comparison chart, a dual delayed‑release timeline showing the two releases, and a pharmacy distribution map contrasting urban and rural access.
Use TGA and PBS logos only with permission and ensure readability for low‑health‑literacy patients.
Include callouts for alarm symptoms such as dysphagia and unexplained weight loss that require urgent referral.
Storage & Transport
Many Australians need clear advice on keeping medicines safe in a hot or humid climate.
Store dexlansoprazole in the original packaging below 30°C and keep capsules dry, which is particularly important in humid regions of northern Australia.
Avoid storing in bathrooms or other damp areas and keep away from direct sunlight and heat sources.
Cold‑Chain Logistics For Pharmacies
No refrigeration is required but transport should protect capsules from moisture and extreme heat.
Pharmacies should monitor seasonal supply chains and maintain buffer stock for remote communities, checking expiry dates and storage conditions at dispensing.
Guidelines For Proper Use
Patients commonly want concise counselling at the point of dispensing.
Adopt a brief‑intervention counselling style: confirm indication, expected duration, PBS status and discuss dosing flexibility, common adverse effects, and long‑term risks such as magnesium depletion and bone health.
Use plain English, provide written leaflets and involve the GP when authority scripts, dose changes or specialist referral are needed.
Emphasise lifestyle measures — reducing alcohol and smoking, weight management and dietary adjustments — as important adjuncts to therapy.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5-7 days |
| Melbourne | Victoria | 5-7 days |
| Brisbane | Queensland | 5-7 days |
| Perth | Western Australia | 5-7 days |
| Adelaide | South Australia | 5-7 days |
| Canberra | Australian Capital Territory | 5-7 days |
| Hobart | Tasmania | 5-7 days |
| Gold Coast | Queensland | 5-7 days |
| Newcastle | New South Wales | 5-9 days |
| Wollongong | New South Wales | 5-9 days |
| Townsville | Queensland | 5-9 days |
| Darwin | Northern Territory | 5-9 days |
| Ballarat | Victoria | 5-9 days |
| Albany | Western Australia | 5-9 days |
Concluding Notes For Patients
If symptoms persist despite an adequate trial of dexlansoprazole, or if alarm features such as difficulty swallowing, gastrointestinal bleeding or unintentional weight loss occur, urgent GP review and possible endoscopy are recommended.
For many patients a PBS‑subsidised generic PPI such as omeprazole will be the most cost‑effective initial choice.
Reserve dexlansoprazole for those who need dosing flexibility, have significant nocturnal reflux, or where other PPIs are ineffective despite correct use.
Ask a pharmacist for written counselling and request the GP review long‑term therapy to check magnesium, B12 and bone health where use exceeds recommended durations.