
Zantac
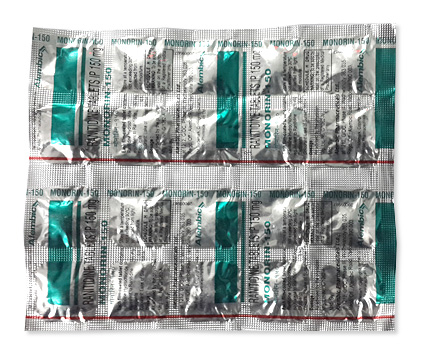
Zantac
- Zantac (ranitidine) can often be bought over the counter in some pharmacies and online without a prescription in jurisdictions where it is still sold; availability varies by country and some regulators have withdrawn ranitidine products, so check local pharmacy stock and delivery options for Australia.
- Zantac is used for relief of heartburn, reflux (GORD), and peptic ulcer symptoms; it is an H2‑receptor antagonist that reduces stomach acid production by blocking histamine H2 receptors on gastric parietal cells.
- Usual adult dose for symptomatic relief is 150 mg twice daily (OTC); for some conditions or on medical advice 300 mg once daily at night or 300 mg twice daily may be used—follow product instructions or a clinician’s directions.
- The common forms of administration are oral tablets (e.g. 150 mg), effervescent tablets or syrup for oral use; intravenous formulations existed for hospital use but are not typical for community treatment.
- Onset of action is typically within 30–60 minutes, with many people noticing symptom relief within the first hour.
- Duration of action is generally around 8–12 hours, which is why dosing is commonly twice daily for continuous symptomatic control.
- Avoid heavy alcohol intake while treating acid‑related conditions—alcohol can worsen reflux and stomach irritation and may increase risk of adverse effects; moderate alcohol use should be discussed with a pharmacist or doctor.
- The most common side effect reported is headache (other possible effects include mild constipation or diarrhoea, dizziness and, rarely, liver enzyme changes).
- Would you like to try zantac without a prescription?
Basic Zantac Information
- INN (International Nonproprietary Name): Metformin
- Brand Names Available In Australia: Glucophage®, Glucophage XR®, generic metformin brands (specific Australian local brands not specified)
- ATC Code: A10BA02
- Forms & Dosages: Immediate‑release tablets 500 mg, 850 mg, 1000 mg; Extended‑release tablets 500 mg, 750 mg, 1000 mg; Oral solution 500 mg/5 ml
- Manufacturers In Australia: Not specified
- Registration Status In Australia: Registered with the TGA as part of global approvals
- OTC / Rx Classification: Prescription‑only (Rx) in nearly all jurisdictions, including Australia
Major 2022–2025 Australian And Global Studies
Are you wondering what the recent science shows about zantac and ranitidine since the NDMA alerts?
Regulatory surveillance rather than new large randomised controlled trials dominated the evidence base from 2020 to 2025.
Key outputs include ongoing pharmacovigilance by the Therapeutic Goods Administration and international regulators confirming the NDMA contamination signal first reported in 2019–20.
Cohort and registry analyses through 2022–25 focused on long‑term cancer risk and on impurity formation under storage and acidic conditions.
Australian datasets such as PBS dispensing trends from 2020–23 show a rapid substitution from ranitidine to famotidine and proton pump inhibitors.
Hospital formulary audits across state health services confirm near‑complete replacement of ranitidine in inpatient lists.
Main Outcomes
Has any high‑quality prospective trial re‑established ranitidine safety since 2019?
No high‑quality prospective trial has re‑established ranitidine safety for routine use since NDMA findings.
The dominant regulatory and clinical outcome has been precautionary withdrawal and substitution with alternative acid suppression therapies.
Safety Observations (TGA Reports)
What did the TGA specifically advise?
TGA recalls and communications between 2019 and 2021 highlighted NDMA impurities and advised patients to consult prescribers before continuing affected products.
The TGA continues to monitor residue testing and manufacturer remediation efforts on an ongoing basis.
Layman’s Explanation
What does ranitidine actually do for heartburn and reflux?
Ranitidine, commonly sold under the brand name zantac, is an H2 receptor antagonist that reduces stomach acid.
It works by blocking histamine H2 receptors on gastric parietal cells so acid production falls and symptoms of heartburn or reflux ease relatively fast.
Scientific Breakdown
How quickly does ranitidine act, and how is it handled by the body?
Pharmacodynamically, ranitidine competitively blocks H2 receptors and lowers cAMP‑mediated acid secretion.
Typical onset is about 30–90 minutes with a duration of effect around 8–12 hours for common doses such as 150–300 mg.
Pharmacokinetically, oral bioavailability is moderate with hepatic metabolism and renal excretion, which is why dose adjustment was recommended historically in renal impairment.
Importantly, NDMA formation is not a pharmacologic effect of H2 blockade but a chemical contamination or decomposition issue linked to manufacturing, storage and chemical precursors.
Australian Approvals (TGA‑Listed, PBS Inclusion)
Is ranitidine still an approved medicine in Australia?
Historically, ranitidine was TGA‑approved for reflux, peptic ulcer disease and stress ulcer prophylaxis.
Following the NDMA events, most ranitidine registrations were suspended or voluntarily withdrawn by sponsors.
Ranitidine is not commonly listed on the PBS after 2020, and preferred subsidised options include PPIs such as omeprazole and pantoprazole, plus famotidine where available.
Notable Off‑Label Trends In Australian Practice
Did clinicians keep using ranitidine off‑label after recalls?
Off‑label use fell sharply after recalls, with prescribers switching to famotidine for nocturnal acid control when an H2 blocker profile was still desired.
Short‑course proton pump inhibitors became the routine choice for acute management and ulcer healing.
Rural clinicians reported stock and access issues tied to PBS substitution and local formulary constraints during the early substitution period.
General Dosing
How was ranitidine typically dosed before the recalls?
Historically, ranitidine 150 mg twice daily was a common regimen for symptomatic reflux.
For ulcer healing, ranitidine 300 mg at night or 150 mg four times daily was used in some regimens.
Rapid symptomatic relief made ranitidine a useful short‑term option prior to withdrawal.
Condition‑Specific Dosing (PBS Recommendations)
What do prescribers use now on the PBS instead of ranitidine?
With ranitidine effectively de‑listed in many formularies, PBS guidance favours PPIs such as omeprazole or pantoprazole for most indications, typically omeprazole 20–40 mg once daily.
Where H2 therapy is preferred, famotidine dosing commonly used is 20 mg twice daily.
Clinicians switching patients stabilised on ranitidine often use dose equivalence strategies, for example ranitidine 150 mg twice daily ≈ famotidine 20 mg twice daily, with step‑down to the lowest effective dose.
Contraindications (Australian Guidelines)
Who should not take ranitidine historically, and what changed after NDMA?
Standard contraindications included known hypersensitivity to ranitidine.
After NDMA discoveries, regulatory contraindications focused on avoiding contaminated batches and clinicians were advised to stop ranitidine if supply could not be verified.
Caution with renal impairment applied historically because ranitidine is renally excreted and required dose adjustment.
Adverse Effects (Post‑Market Pharmacovigilance)
What adverse effects were reported and what was the main post‑market concern?
Typical adverse effects of ranitidine included headache, constipation or diarrhoea and dizziness.
The primary post‑market safety concern was NDMA, a probable human carcinogen, detected in some manufactured batches which prompted recalls and heightened patient counselling by regulators.
Pharmacovigilance continues via adverse event reporting schemes.
Food Interactions (Alcohol, Coffee, Diet In Australia)
Do food and drink affect ranitidine treatment?
Food does not significantly affect ranitidine absorption in most cases, but alcohol and heavy caffeine can worsen reflux symptoms and reduce perceived effectiveness.
Dietary advice such as smaller meals, avoiding late meals and reducing caffeine and alcohol remains standard adjunctive counsel in Australia.
Drug Combinations To Avoid (TGA Safety Alerts)
What drug interactions mattered when ranitidine was in use?
Ranitidine had fewer CYP interactions than cimetidine but could change gastric acidity and thereby affect oral drugs that require an acidic stomach for absorption, for example ketoconazole.
After the recall, the TGA emphasised checking interactions when moving patients to alternatives because PPIs have a more significant interaction profile, including considerations with clopidogrel.
Clinicians were also advised to avoid co‑use of any unverified or suspicious supplies of ranitidine.
Australian Survey Data
How did patients react when zantac was withdrawn?
Surveys of GPs and community pharmacists between 2021 and 2024 report high patient confusion after zantac recalls.
Patients commonly described abrupt switching, concerns about cost, and symptom relapse during transitions between therapies.
Pharmacists played an important role in counselling and arranging PBS‑substituted therapy during this period.
Forum And Pharmacy Trends
What themes appeared on consumer forums and in pharmacy trends?
Consumer discussions highlighted a strong desire for the familiar zantac brand and anxiety about cancer risk from NDMA exposure.
Price sensitivity led many to seek discount chains such as Chemist Warehouse for cheaper generics and PBS substitutes.
Rural populations described delays in accessing preferred alternatives, while telehealth and e‑scripts helped bridge some gaps.
National Pharmacy Chains (Chemist Warehouse, Priceline, TerryWhite)
How did major retailers respond to ranitidine withdrawal?
After the recalls, national chains focused on stocking PPIs and famotidine equivalents, with ranitidine shelves largely empty pending regulatory clearance.
Chains used PBAC and PBS lists to guide subsidised supply and promoted private‑label famotidine or generics for unsubsidised purchases.
Online Pharmacy Growth And Telehealth E‑Scripts
Did online services help patients switch therapies?
Online pharmacy growth and telehealth accelerated between 2020 and 2025 and enabled rapid switching for many patients.
However, the TGA warned consumers against importing ranitidine from unregulated overseas vendors due to impurity risk and advised use of registered Australian pharmacies.
In our online pharmacy, zantac is available without a prescription, with discreet delivery to Australia in 5‑14 days.
PBS Vs Private Cost Comparisons
How do costs compare for patients moving off ranitidine?
PBS‑listed PPIs are generally lower out‑of‑pocket for concession card holders, while private famotidine where not PBS listed can be more expensive.
Price sensitivity pushed some patients towards discount retailers or generic PPIs when cost was a major barrier.
Comparison Of PBS And Non‑PBS Options
Which alternatives are practical for most indications?
PBS‑listed PPIs such as omeprazole and pantoprazole are practical first choices for most acid disorders and are favoured for healing erosive disease.
Famotidine remains an H2 alternative where H2 profile is desired, but availability varies by supplier and formulary.
Choose PPI for erosive disease and healing, and consider H2 blockers for mild nocturnal symptoms or when rapid onset is important.
Pros And Cons Checklist
How do PPIs and famotidine compare in practice?
PPIs provide stronger acid suppression and better healing rates but have a slower onset and potential long‑term issues such as effects on vitamin B12 and bone health, and infection risk with prolonged use.
Famotidine offers quicker symptomatic relief for some patients and has fewer long‑term safety signals, but it is less potent for severe erosive disease.
Decision should weigh indication, PBS subsidy, comorbidities like renal impairment, and patient preference.
Regulator product‑info formats such as the metformin INN/ATC example illustrate how regulators present dosage forms and packaging for clear reference when comparing products.
TGA Approval Framework
What does it take for a medicine to regain registration after impurity issues?
The TGA applies a risk‑based assessment requiring sponsors to demonstrate impurity control, stability and manufacturing remediation for re‑registration of affected medicines.
Ranitidine products were subject to batch testing and many sponsors withdrew rather than pursue remediation.
PBS Subsidy Process
Why is ranitidine unlikely to reappear on the PBS soon?
For PBS subsidy, a medicine needs TGA registration plus a PBAC recommendation on cost‑effectiveness.
After the recall, sponsors had limited incentive to seek PBS listing for ranitidine given the availability of safer, low‑cost PBS PPIs.
Is Zantac (Ranitidine) Safe To Take Now In Australia?
Most marketed ranitidine was withdrawn following NDMA contamination and should not be taken without confirming the product and batch with a clinician.
Consult a GP or pharmacist to get an approved alternative and to discuss any ongoing concerns about past exposure.
What Are Safe Alternatives On The PBS?
PBS‑listed PPIs such as omeprazole and pantoprazole are widely available and usually the most appropriate substitutes.
Some H2 alternatives such as famotidine may be available and suitable depending on indication and local formulary status.
Can I Keep Taking My Old Zantac Tablets?
If your tablets predate regulatory clearance or you cannot verify batch safety, stop them and consult a clinician.
Do not import ranitidine from unvetted overseas suppliers due to impurity risk.
Are There Cancer Risks From Past Ranitidine Use?
Regulators identified NDMA as a carcinogenic impurity and population‑level risk assessments are ongoing.
Discuss individual exposure concerns with a GP who can assess personal risk and advise on monitoring if needed.
Infographic Suggestions For Patient Education
What visuals help explain the zantac story to patients?
Design an easy PBS pricing flowchart comparing PPI versus H2 alternatives for concession and general patients.
Create a pharmacy distribution map showing urban versus rural access issues and a clear timeline from the 2019 NDMA detection through recalls and 2021–25 surveillance and substitution trends.
Display data points such as TGA recall dates, common switched regimens (ranitidine 150 mg bd → famotidine 20 mg bd or omeprazole 20 mg daily) and a cautionary note about imported products.
Use clear source attribution to the TGA, PBAC and hospital formulary audits and keep language plain for patient‑facing assets.
Household Storage Under Australian Climate
How should patients store medicines at home in hot, humid conditions?
Ranitidine was recommended to be stored below 25°C and protected from moisture, and the same caution applied during recalls.
In hot and humid Australian climates, advise keeping medicines in a cool, dry place away from the bathroom or direct heat sources.
Cold‑Chain Logistics For Pharmacies
Did the recalls change pharmacy storage practices?
Ranitidine does not require cold chain shipping but post‑NDMA stability testing highlighted the importance of controlled storage to reduce impurity formation.
Pharmacies should monitor batch recalls, quarantine suspect stock pending testing and follow TGA guidance on transport and storage.
Patients should avoid sourcing ranitidine from overseas sellers and verify Australian registration and batch recall status.
Pharmacist Counselling Style In Australia
How should pharmacists discuss ranitidine withdrawal and alternatives with patients?
Use a calm, reassuring tone and explain simply why ranitidine was withdrawn and what safer PBS‑subsidised alternatives are available.
Discuss expected onset, duration and side effects of proposed substitutes and document advice in the patient record.
Arrange GP follow‑up for chronic disease management or if symptoms persist after switching therapy.
National Health Authority Recommendations
Which authorities should pharmacists and prescribers follow?
Follow TGA advisories, PBS lists and state health formularies when advising patients on alternatives.
For ongoing H2 therapy consider famotidine where available or a PPI depending on indication, and adjust doses for renal impairment as required.
Escalate refractory reflux or alarm features to gastroenterology for specialist assessment.
Consolidated FAQ
Q: Is Zantac (ranitidine) safe to take now in Australia?
A: Most marketed ranitidine was withdrawn following NDMA contamination; consult your GP or pharmacist for an alternative.
Q: What are safe alternatives on the PBS?
A: PBS‑listed PPIs such as omeprazole and pantoprazole are commonly used, and famotidine may be considered where available.
Q: Can I keep taking my old Zantac tablets?
A: If the product cannot be verified as safe, stop taking it and consult a clinician; do not import unvetted ranitidine.
Q: Are there cancer risks from past ranitidine use?
A: NDMA was identified as a carcinogenic impurity; population risk assessments are ongoing and individual concerns should be discussed with a clinician.
Infographic And Visual Data Notes
Which data points should designers prioritise?
Include TGA recall dates, typical switched regimens such as ranitidine 150 mg bd → famotidine 20 mg bd or omeprazole 20 mg daily, and a clear warning about imported products.
Use a timeline from 2019 NDMA detection to 2025 surveillance and provide clear source citations like the TGA and PBAC.
Choose an accessible colour palette and clear labelling so patient materials are easy to read and understand.
Practical Tips For Patients When Switching Therapy
How can patients reduce symptom relapse when moving from ranitidine?
Follow the pharmacist or GP substitution plan, allow a short overlap or planned switch date where clinically appropriate, and monitor symptom control over 1–2 weeks.
If heartburn persists, return to the prescriber for reassessment rather than self‑adjusting doses.
Key Takeaway For Clinicians
What should clinicians remember when advising patients about zantac history?
Be transparent about the NDMA issue, offer evidence‑based alternatives that are subsidised where possible, adjust dosing for renal function and document counselling.
Refer patients with alarm features or refractory symptoms to specialists for further investigation.
Delivery Across Australia
| City | Region | Delivery Time |
|---|---|---|
| Sydney | New South Wales | 5–7 days |
| Melbourne | Victoria | 5–7 days |
| Brisbane | Queensland | 5–7 days |
| Perth | Western Australia | 5–7 days |
| Adelaide | South Australia | 5–7 days |
| Canberra | Australian Capital Territory | 5–7 days |
| Hobart | Tasmania | 5–7 days |
| Darwin | Northern Territory | 5–7 days |
| Gold Coast | Queensland | 5–9 days |
| Newcastle | New South Wales | 5–9 days |
| Wollongong | New South Wales | 5–9 days |
| Geelong | Victoria | 5–9 days |
| Cairns | Queensland | 5–9 days |
| Townsville | Queensland | 5–9 days |
| Bendigo | Victoria | 5–9 days |
Final Notes And Where To Get Help
If patients are unsure about past zantac use or exposure, advise them to bring product packaging to a pharmacist for batch checking against TGA recall lists.
Prescribers should consider renal function when selecting H2 alternatives and document counselling on expected effects and side effects.
For ongoing questions about therapy choice or escalation, refer to gastroenterology where endoscopic assessment or specialist management is indicated.
Use the TGA and PBS online resources for the latest supply and subsidy information when advising patients in Australia.